Patients › General-Health
Mga Nerve Test at Conduction Study
What nerve conduction studies and EMG are, why they are done for carpal tunnel and other nerve problems, what to expect, and how accurate they are.
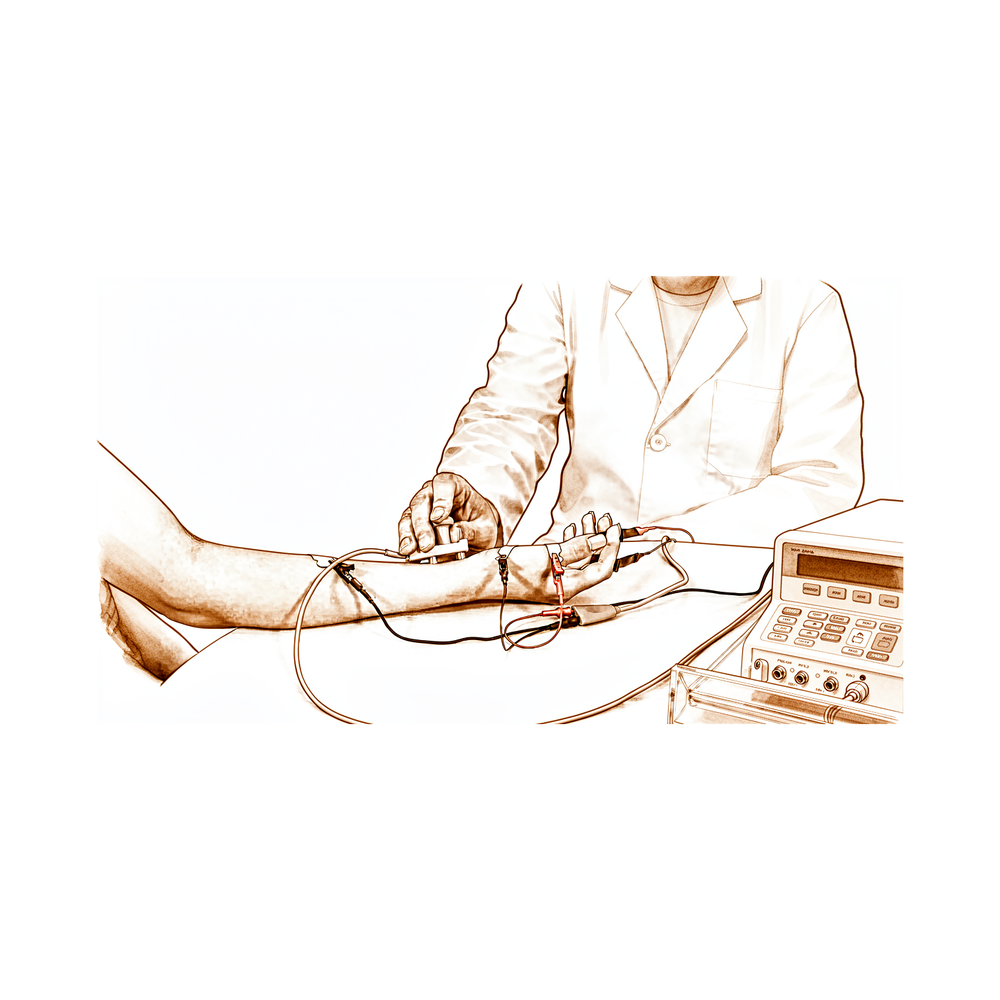
Ano ito
Sinusukat ng mga nerve test kung gaano kahusay nagdadala ng mga electrical signal ang iyong mga nerve. May dalawang electrical na paraan upang suriin ang paggana ng nerve, at kapwa napatunayang kapaki-pakinabang ang mga ito sa praktika [1]. Ang pangunahing test ay tinatawag na nerve conduction study. Nagpapadala ang isang maliit na device ng napakaliit na pulse sa iyong nerve at itinatala kung gaano kabilis dumadaloy ang signal. Kung naiipit o napinsala ang isang nerve, bumabagal o humihina ang signal.
Pinakamadalas gamitin ang mga test na ito para sa carpal tunnel syndrome, kung saan nasa ilalim ng pressure ang nerve sa harapan ng iyong pulso. Itinuturing ang mga ito na isang hindi maaaring mawalang bahagi ng pagsusuri bago ang operasyon para sa kondisyong iyon [2]. Karamihan sa mga doktor ay hindi mag-oopera nang walang ganitong kumpirmasyon [3]. Makatutulong din ang mga test sa iba pang problema sa nerve, gaya ng pressure sa nerve sa siko (cubital tunnel syndrome) [4].
Karaniwang magkakaroon ka ng pangalawang test sa parehong pagbisita. Para rito, inilalagay ang isang pinong karayom sa ilang kalamnan. Sinusuri nito kung gaano kahusay tumutugon ang mga kalamnan sa nerve na nagsusuplay sa kanila. Kapag pinagsama, tinatawag ang mga ito na electrodiagnostic studies, na ang ibig sabihin lamang ay mga test na gumagamit ng kuryente upang pag-aralan ang mga nerve at kalamnan.
Gumagana ang mga test dahil nagdadala ng mga signal ang mga nerve gaya ng pagdadala ng kuryente ng mga kawad. Ang naiipit na nerve ay kumikilos na parang naipit na kable, kaya naaantala o humihina ang signal sa kahabaan nito. Nagbibigay ang mga resulta ng sukat kung gaano kapinsala ang nerve, at ito ang pinakamahusay na makukuhang palatandaan ng pangkalahatang kalubhaan ng sakit [5]. Ang halaga ng mga test na ito ay nasa pagkuha ng tamang diagnosis at sa pagtasa kung gaano ito kalala, hindi sa paghula kung ano ang mararamdaman mo pagkatapos ng operasyon [6].
Isang puntong mabuting malaman: hindi inaalis ng normal na test ang posibilidad ng carpal tunnel syndrome, dahil maaaring dumating at umalis ang pagkaipit ng nerve.
Gumagana ba ito?
Ang tapat na sagot ay mahusay ang mga test na ito sa ilang trabaho at limitado sa iba. Kapaki-pakinabang na karagdagan ang mga ito kapag sinusuri ang carpal tunnel syndrome, lalo na kapag normal ang lumabas sa mga karaniwang test [7]. Natuklasan ng isang pag-aaral ng isang espesyal na nerve test na natukoy nito ang kondisyon sa 69% ng mga kaso, at tama ang bawat positibong resulta. Nang pagsamahin ang test na iyon at ang isa pang paraan ng pagsukat ng pakiramdam, natukoy nito ang 84% ng mga kaso [8].
Tumutulong din ang mga test na kumpirmahin ang diagnosis bago ang operasyon. Kapag tumuturo ang iyong mga senyales at sintomas sa banayad hanggang katamtamang pressure sa nerve at isinasaalang-alang ang operasyon, maaaring pataasin ng karagdagang pagsusuri ang tsansa na nakatutok ang operasyon sa isang tunay at nagagamot na problema [9]. Natuklasan ng isang pag-aaral ang malaking agwat sa pagitan ng bilang ng mga taong na-diagnose batay sa sintomas lamang (73%) at ng bilang na nakumpirma ng mga test na ito at ng ultrasound (51%) [10]. Ang agwat na iyon mismo ang dahilan kung bakit mahalaga ang pagsusuri: inaalam nito kung sino talaga ang may problema sa nerve na matutulungan ng operasyon.
May mga limitasyon. Iba-iba ang kalidad ng mga test na ito sa pagitan ng mga provider, at mas detalyado ang ilang ulat kaysa sa iba [11]. Kailangan ding mas malinaw na tukuyin ang mga pamantayan sa pagbasa sa mga ito, upang tumpak ang mga diagnosis at hindi magsagawa ng operasyon kapag hindi ito kailangan [12]. At hindi kayang sabihin sa iyo ng mga test ang lahat. Sinusukat nila ang nerve, hindi ang iyong mga sintomas.
Magkakahalo ang ilang natuklasan. Hindi naging makabuluhan sa loob ng dalawang taon ang mga pagbabago sa mga resulta ng test pagkatapos ng steroid injection [13]. Sa kabilang banda, ang magandang tugon sa isang iniksyon ay isang kapaki-pakinabang na senyales kung paano maaaring maging resulta ng operasyon [14]. Ang isang sukat mula sa mga test, na tinatawag na distal motor latency, na ang ibig sabihin lamang ay kung gaano katagal bago umabot ang signal sa isang kalamnan, ay may kaunting halaga sa paghula kung ano ang magiging lagay mo pagkatapos ng operasyon [15].
Kaya mahusay na gumagana ang mga test bilang kasangkapan sa pag-diagnose. Hindi sila gaanong maaasahan bilang bolang kristal para sa iyong paggaling.
Ano ang mga panganib?
Ligtas ang mga nerve test, ngunit dapat mong malaman kung ano ang aasahan. Ang pinakakaraniwang epekto ay hindi komportableng pakiramdam habang isinasagawa ang test mismo. Ang mga electrical pulse ay parang maliliit na tapik o kirot. Kung maglalagay ng pinong karayom sa isang kalamnan, makararamdam ka ng maikling hapdi, at maaaring mangalay ang kalamnan nang isa o dalawang araw pagkatapos. Mabilis ang bersyon ng test sa palasingsingan at napakaliit ng pagod na idinudulot nito sa iyo [16].
Walang pangmatagalang epekto sa iyong balat o tissue ang mga electrical pulse. Maliliit ang mga pulse, at dumadaan ang mga ito sa balat nang hindi ito pinipinsala. Kung magkakaroon ka ng needle test, maaaring bahagyang masakit kapag hinawakan ang mga lugar na tinusukan ng karayom, at maaaring lumitaw ang maliit na pasa. Kusang humuhupa ang mga ito.
Hindi inilalarawan ng ebidensya ang mga epekto sa iba pang bahagi ng iyong katawan, at hindi nito inilalarawan ang mga bihira ngunit malubhang komplikasyon mula sa mga test na ito. Mabuting sabihin iyon nang tahasan: ang mga pag-aaral sa likod ng pahinang ito ay nag-uulat kung gaano kahusay nagda-diagnose at humuhula ang mga test, hindi tungkol sa mga pinsala, kaya limitado ang impormasyon dito tungkol sa malulubhang panganib.
Ang isang panganib ay hindi pisikal. Maaaring magkakaiba ang pagbasa ng iba't ibang provider sa mga test, at mas detalyado ang ilang ulat kaysa sa iba [11]. Ang isang ulat na naglilista ng maliliit na abnormalidad nang hindi ipinapaliwanag ang mga ito ay maaaring humantong sa maling konklusyon [17]. Kailangan ding mas malinaw na tukuyin ang mga pamantayan sa pagbasa sa mga test, upang tumpak ang mga diagnosis at hindi magsagawa ng operasyon kapag hindi ito kailangan [12]. Ito ang pangunahing bagay na maaaring magkamali: hindi ang test mismo, kundi isang diagnosis na nakabatay sa isang hindi kumpleto o hindi malinaw na ulat.
Kung nagkaroon ka ng steroid injection para sa carpal tunnel syndrome, hindi naging makabuluhan sa loob ng dalawang taon ang mga pagbabago sa mga resulta ng test pagkatapos ng iniksyong iyon [13]. Ibig sabihin, mukhang hindi binabago ng iniksyon ang ipinapakita ng mga test sa mas mahabang panahon, kaya dapat pa ring magbigay ng patas na larawan ng iyong nerve ang isang inulit na test pagkatapos ng iniksyon.
Hilingin sa iyong doktor o sa taong gumagawa ng test na ipaliwanag sa iyo ang ulat. Ang malinaw na paglalarawan kung ano ang natuklasan ng test, at kung ano ang ibig sabihin nito, ay bahagi ng isang mabuting resulta.
Tama ba ito para sa iyo?
Kung tumuturo ang iyong mga sintomas sa carpal tunnel syndrome at pinag-iisipan ang operasyon, karaniwang bahagi ng plano ang mga test na ito. Karamihan sa mga doktor ay hindi mag-oopera nang walang ganitong kumpirmasyon [3]. Maaaring pataasin ng karagdagang pagsusuri ang tsansa na nakatutok ang operasyon sa isang tunay at nagagamot na problema sa nerve [9]. Mahalaga iyon, dahil nakukuha ng mga test ang tamang diagnosis at ipinapakita kung gaano kalala ang pressure sa iyong nerve [6].
Maaaring hindi gaanong kapaki-pakinabang ang mga ito kung malabo ang iyong mga sintomas o dumarating at umaalis. Maaaring hindi matukoy ang pagkaipit ng nerve sa araw ng test. Hindi inaalis ng normal na resulta ang posibilidad ng carpal tunnel syndrome. Hindi rin kayang hulaan ng mga test kung ano ang mararamdaman mo pagkatapos ng operasyon, kaya kasangkapan ang mga ito sa diagnosis, hindi pangako tungkol sa iyong paggaling [6].
Ang pangunahing alternatibo ay ultrasound, na maaari ring sumuri kung may pressure sa nerve [9]. Maaaring imungkahi ng iyong doktor ang isa o pareho. Bawat isa ay may kanya-kanyang kalakasan, at nakadepende ang tamang pagpili sa iyong mga sintomas at pagsusuri.
Dapat itong maging pinagsamang desisyon ninyo ng iyong doktor. Itanong kung ano ang inaasahang ipakita ng test, at kung ano ang mangyayari kung normal ang resulta. Kung may mga tanong ka tungkol sa mga panganib ng test mismo, basahin ang seksyon sa itaas tungkol sa mga panganib.
Ang pinaka-importanteng punto
Kung isinasaalang-alang ang operasyon para sa carpal tunnel syndrome, sulit gawin ang mga test na ito. Kinukumpirma nila kung totoo ang pressure sa iyong nerve at ipinapakita kung gaano ito kalala [6]. Maaaring pataasin ng karagdagang pagsusuri ang tsansa na nakatutok ang operasyon sa isang tunay at nagagamot na problema [9]. Pumasok nang may makatotohanang inaasahan: mahusay ang mga test sa diagnosis, ngunit hindi nila kayang hulaan kung ano ang mararamdaman mo pagkatapos ng operasyon [6]. Ang pinakamahalagang paalala ay hindi inaalis ng normal na resulta ang posibilidad ng carpal tunnel syndrome, dahil maaaring dumating at umalis ang pagkaipit ng nerve. Humingi ng malinaw na paliwanag sa iyong ulat bago gumawa ng anumang desisyon.
Mga Sanggunian
[1] Sensory threshold and conductance testing in nerve injuries. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1986. DOI: 10.1016/0266-7681(86)90252-4
[2] Correlation of Clinical Signs with Nerve Conduction Tests in the Diagnosis of Carpal Tunnel Syndrome. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90244-5
[3] Current Practice in the Use of Nerve Conduction Studies in Carpal Tunnel Syndrome by Surgeons in the Netherlands. Journal of Hand Surgery (European Volume). 2007. DOI: 10.1016/j.jhse.2007.09.007
[4] Diagnosis of Ulnar Neuropathy at the Elbow Using Ultrasound — A Comparison to Electrophysiologic Studies. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.08.014
[5] Use of nerve conduction studies in carpal tunnel syndrome. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231191685
[6] Electrical studies as a prognostic factor in the surgical treatment of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80384-4
[7] Provocative motor nerve conduction testing in presumptive carpal tunnel syndrome unconfirmed by traditional electrodiagnostic testing. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(97)80045-7
[8] The utility of portable nerve conduction testing for patients with carpal tunnel syndrome: A prospective clinical study. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90117-8
[9] Diagnosis of Mild-to-moderate Idiopathic Median Neuropathy at the Carpal Tunnel Based on Signs and Symptoms is Discordant From Diagnosis Based on Electrodiagnostic Studies and Ultrasound. Clinical Orthopaedics & Related Research. 2023. DOI: 10.1097/corr.0000000000002751
[10] CORR Insights®: Diagnosis of Mild-to-moderate Idiopathic Median Neuropathy at the Carpal Tunnel Based on Signs and Symptoms is Discordant From Diagnosis Based on Electrodiagnostic Studies and Ultrasound. Clinical Orthopaedics & Related Research. 2023. DOI: 10.1097/corr.0000000000002822
[11] Electrodiagnostic reports of median neuropathy at the wrist. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80089-0
[12] Electrodiagnostic testing and carpal tunnel release outcome. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(05)80209-6
[13] Nerve Conduction Studies after Treatment for Carpal Tunnel Syndrome. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90191-4
[14] Diagnostic and therapeutic value of carpal tunnel injection. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80065-9
[15] Carpal Tunnel Syndrome: Neurophysiological Results of Surgery Based on Preoperative Electrodiagnostic Testing. Journal of Hand Surgery. 1997. DOI: 10.1016/s0266-7681(97)80355-5
[16] Relative slowing of the median antidromic sensory nerve conduction velocity to the ring finger in screening for carpal tunnel syndrome. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2004.04.026
[17] Electrodiagnostic testing in hand surgery. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80298-x
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Nerve conduction studies serve as a measure of impaired nerve function and are the best available indicator of overall disease severity with some prognostic value for surgical outcome [1].
- Nerve conduction studies are considered an indispensable part of the pre-operative evaluation for carpal tunnel syndrome [2].
- Provocative nerve conduction testing is a useful and simple addition to the overall evaluation of patients with carpal tunnel syndrome, particularly those with otherwise normal findings on traditional electrodiagnostic studies [3].
- The selection of an appropriate electrical screening test for peripheral nerve injury depends on the prevalence and seriousness of the target disease and the relative consequences of over- and underdiagnosis [4].
- The absence of any real difference in nerve conduction time between a working group with symptoms and a group with diagnosed carpal tunnel syndrome indicates a high probability that many participants with symptoms would have had abnormal findings on standard electrodiagnostic tests [5].
- The value of preoperative nerve conduction studies lies in obtaining the correct diagnosis and determining the severity of the median nerve disease, not in predicting postoperative outcome [6].
- Electrodiagnostic criteria used in some referenced studies were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in carpal tunnel syndrome [7].
- The value of electrodiagnostic testing is not negated by findings that it does not predict postoperative outcome [8].
- When signs and symptoms suggest mild-to-moderate median neuropathy and surgery is being considered, patients and clinicians might consider additional testing, such as electrodiagnostic studies or ultrasound, to increase the probability of actual median neuropathy that can benefit from surgery [9].
- Clinical, electrodiagnostic, and physical examination criteria need better definition to avoid inaccurate diagnoses and unnecessary surgeries [10].
- Highly sensitive tests are required to assess or exclude the diagnosis in one quarter of cases of carpal tunnel syndrome [11].
- Nerve conduction studies were more sensitive than sensibility testing in confirming the diagnosis of carpal tunnel syndrome [13].
- The combination of nerve conduction studies and sensibility testing is more sensitive than either test alone in confirming the diagnosis of carpal tunnel syndrome [13].
- Given specific clinical criteria for establishing the diagnosis of carpal tunnel syndrome, electrodiagnostic testing does not appear to correlate with improved final symptomatic outcome after carpal tunnel release [20].
- Surgical intervention is advocated for patients with symptoms only, even when electrodiagnostic studies are normal, in the context of cubital tunnel syndrome [21].
- The majority of neurosurgeons and orthopaedic surgeons seldom operate without electrodiagnostic confirmation in line with the Dutch consensus guideline on this subject [29].
- When used together, Semmes-Weinstein monofilament mappings and sensory nerve conduction parameters present a clearer picture of the patient's sensory status than either test used alone [31].
- Receiver operating characteristic curves showed distal sensory latency measurement to be a superior diagnostic test for carpal tunnel syndrome, with 3.3 ms as optimal upper limit of normal, giving a sensitivity of 74% and a specificity of 87% [45].
How It Works
Diagnostic Utility and Role
- The clinical, electrodiagnostic, and physical examination criteria need better definition to avoid inaccurate diagnoses and unnecessary surgeries [10].
- Electrodiagnostic studies are used as part of a clinical evaluation process and are considered a reasonable way to practice medicine [12].
Sensitivity and Specificity
- Nerve conduction studies were more sensitive than sensibility testing in confirming the diagnosis of carpal tunnel syndrome, but the combination of the two studies is more sensitive than either test alone [13].
- The sensitivity of the neurometer test alone was 69% and specificity was 100%, increasing to 84% sensitivity when combined with quantitative sensibility testing [28].
- The relative slowing of the antidromic sensory conduction velocity of the median nerve to the ring finger is determined easily and efficiently and imposes minimal strain on the patient [34].
Prognostic Value and Outcomes
- Compound muscle action potential amplitude, but not other conventional electrodiagnostic parameters, was predictive of functional outcomes after in situ decompression of the ulnar nerve [22].
- Suprascapular nerve dysfunction, evidenced by reduced nerve amplitudes and supraspinatus muscle atrophy, significantly predicts poor functional outcomes following shoulder hemiarthroplasty, even when tuberosities are well healed [19].
- This strength recovers gradually as the median nerve heals, but never returns to normal, indicating that this test can be extrapolated to the reinnervation of the abductor pollicies brevis [23].
Technical Considerations and Reporting
- There is variability with respect to the thoroughness of electrodiagnostic studies and in the quality of information in the reports [16].
- Electrodiagnostic reports should specifically indicate abnormalities of latency and conduction and present a clear description of the probable pathophysiologic processes rather than just compiling slight abnormalities [26].
- The conduction velocity of the ulnar nerve after an anterior transposition is determined by both the position of the elbow and the location for the measurement of the skin distance [37].
Physiological Mechanisms and Intraoperative Findings
- When in situ nerve strain reached 8.1 ± 0.5%, the compound muscle action potential was not evoked [33].
- Intraoperative conduction latencies indicated a dramatic and immediate reduction in the conduction latency across the carpal canal in all but seven patients, two of whom had diabetes [36].
- Electrodiagnostic studies revealed an acute median nerve lesion at the wrist with motor and/or sensory conduction blocks in 20/30 women with pregnancy-related carpal tunnel syndrome [18].
Comparative Modalities
- Ultrasound is a valid alternative confirmatory test compared with electrodiagnostic studies in detecting ulnar neuropathy at the elbow [14].
- The study confirms the high diagnostic value of the pre-operative antidromic sensory conduction velocity findings [25].
What the Evidence Shows
Diagnostic Role and Sensitivity
- The absence of any real difference in nerve conduction time between the working group with symptoms and the group with diagnosed carpal tunnel syndrome indicates a high probability that many participants with symptoms would have had abnormal findings on standard electrodiagnostic tests [5].
- There is a severe discordance between the estimated prevalence of mild-to-moderate carpal tunnel syndrome based on clinical signs and symptoms (73%) versus electrodiagnostic studies and ultrasound (51%) [27].
- The authors argue that the electrodiagnostic criteria used in the referenced study were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in carpal tunnel syndrome [7].
- Carpal tunnel injection is a reasonably accurate diagnostic test, as a good response to injection is an excellent diagnostic and prognostic sign for surgical treatment [42].
Prognostic Value and Outcomes
- Upper arm motor nerve conduction velocity might be a useful predictor of poor surgical outcome in cubital tunnel syndrome [32].
- Distal motor latency is a simple test with a predictive value of the postoperative neurophysiological and clinical outcome of carpal tunnel syndrome [39].
- The changes in electrophysiological findings occurring spontaneously in carpal tunnel syndrome and after treatment by injection are not statistically significant at two years [38].
Clinical Application and Reporting
- The author continues to use electrodiagnostic studies as part of a clinical evaluation process and considers this a reasonable way to practice medicine [12].
- The author proposes that the clinical, electrodiagnostic, and physical examination criteria need better definition to avoid inaccurate diagnoses and unnecessary surgeries [10].
- The study confirms the high diagnostic value of the pre-operative antidromic sensory conduction velocity findings in carpal tunnel syndrome [25].
- Surgical intervention is advocated for patients with symptoms only, even when electrodiagnostic studies are normal, in cases of cubital tunnel syndrome [21].
- The incidence of abnormal conduction times was not reliably correlated with either age or duration of paralysis in the paraplegic hand [24].
- In primates, there is no significant difference in the conduction velocity of peripheral nerves repaired in adults and those repaired in early life [15].
- Although there are essential differences between Semmes-Weinstein monofilament mappings and sensory nerve conduction parameters, when used together they present a clearer picture of the patient's sensory status than either test used alone [31].
- The strength of the abductor pollicis brevis recovers gradually as the median nerve heals but never returns to normal, indicating that this test can be extrapolated to the reinnervation of the abductor pollicis brevis [23].
- Chitosan phonophoresis demonstrated significant improvements in nerve conduction, pain reduction, and enhancement of hand function for mild to moderate cubital tunnel syndrome [17].
- All patients had good clinical and electrophysiological recovery at 6 months following single-stage opponensplasty added at the time of release for severe carpal tunnel syndrome [41].
- Three weeks after the operation, 77% of the patients in the tourniquet group had denervation in other than thenar muscles [46].
Practical Considerations
Diagnostic Interpretation and Utility
- Nerve conduction studies serve as a measure of impaired nerve function and the best available indicator of overall disease severity, rather than a test that determines the diagnosis [1].
- The value of preoperative nerve conduction studies lies in obtaining the correct diagnosis and determining the severity of median nerve disease, not in predicting postoperative outcome [6].
- Electrodiagnostic testing does not appear to correlate with improved final symptomatic outcome after carpal tunnel release given specific clinical criteria for establishing the diagnosis [20].
- When signs and symptoms suggest mild-to-moderate median neuropathy and surgery is being considered, patients and clinicians might consider additional testing, such as EDS or US, to increase the probability of actual median neuropathy that can benefit from surgery [9].
- The authors argue that the electrodiagnostic criteria used in the referenced study were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in CTS [7].
- This does not negate the value of electrodiagnostic testing [8].
Testing Variations and Screening
- Provocative nerve conduction testing is a useful and simple addition to the overall evaluation of patients with CTS, particularly those with otherwise normal findings on traditional electrodiagnostic studies [3].
- The absence of any real difference in nerve conduction time between the working group with symptoms and the group with diagnosed CTS indicates a high probability that many of the participants with symptoms would have had abnormal findings on standard electrodiagnostic tests [5].
- There is a significant discrepancy between the practice recommended by the Danish Society of Neurophysiology of performing neurophysiological investigations in all cases of suspected CTS and what is actually done in most surgical departments [35].
Specific Clinical Scenarios
- Upper arm motor nerve conduction velocity (MNCV) might be a useful predictor of poor surgical outcome in cubital tunnel syndrome [32].
- Surgical intervention is advocated for patients with symptoms only, even when electrodiagnostic studies are normal, in cases of electrodiagnostic-negative cubital tunnel syndrome [21].
- SSN dysfunction, evidenced by reduced nerve amplitudes and supraspinatus muscle atrophy, significantly predicts poor functional outcomes following shoulder hemiarthroplasty, even when tuberosities are well healed [19].
- The incidence of abnormal conduction times in the paraplegic hand was not reliably correlated with either age or duration of paralysis [24].
- Intraoperative electrodiagnosis may offer limited value in neonatal brachial plexus palsy surgery, but there is insufficient evidence to reach robust conclusions [44].
- This underscores the need for surgeons to carefully evaluate suprascapular nerve integrity in cases of rotator cuff tear [40].
Methodological and Prognostic Notes
- Only studies with randomization, blinding, and sham injection or sham surgery can address subjective symptoms and satisfaction reliably and accurately [30].
Key Evidence
- [L5] Nerve conduction studies should be understood not as a test that determines the diagnosis but as a measure of impaired nerve function, serving as the best available indicator of overall disease severity with some prognostic value for surgical outcome. [1] (10.1177/17531934231191685)
- [L3] We consider nerve conduction studies to be an indispensable part of the pre-operative evaluation. [2] (10.1016/0266-7681(94)90244-5)
- [L2] Provocative nerve conduction testing is a useful and simple addition to the overall evaluation of patients with CTS, particularly those with otherwise normal findings on traditional electrodiagnostic studies. [3] (10.1016/s0363-5023(97)80045-7)
- [L3] The selection of an appropriate electrical screening test for peripheral nerve injury, such as entrapment neuropathy, depends on the prevalence and seriousness of the target disease and the relative consequences of over- and underdiagnosis. [4] (10.1016/s0363-5023(96)80165-1)
- [L3] The absence of any real difference in nerve conduction time between the working group with symptoms and the group with diagnosed CTS indicates a high probability that many of the participants with symptoms would have had abnormal findings on standard electrodiagnostic tests. [5] (10.1016/0363-5023(92)90116-7)
- [L5] The value of preoperative nerve conduction studies lies in obtaining the correct diagnosis and determining the severity of the median nerve disease, not in predicting postoperative outcome. [6] (10.1016/s0363-5023(96)80384-4)
- [L5] The authors argue that the electrodiagnostic criteria used in the referenced study were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in CTS. [7] (10.1067/jhsu.2000.jjhsu00025a1le01)
- [L5] This does not negate the value of electrodiagnostic testing. [8] (10.1016/s0363-5023(96)80222-x)
- [L3] When signs and symptoms suggest mild-to-moderate median neuropathy and surgery is being considered, patients and clinicians might consider additional testing, such as EDS or US, to increase the probability of actual median neuropathy that can benefit from surgery. [9] (10.1097/corr.0000000000002751)
- [L5] The author proposes that the clinical, electrodiagnostic, and physical examination criteria need better definition to avoid inaccurate diagnoses and unnecessary surgeries. [10] (10.1016/s0363-5023(05)80209-6)
- [L3] Highly sensitive tests are required to assess or exclude the diagnosis in one quarter of cases of carpal tunnel syndrome. [11] (10.1016/0266-7681(94)90245-3)
- [L5] The author continues to use electrodiagnostic studies as part of a clinical evaluation process and considers this a reasonable way to practice medicine. [12] (10.1016/s0363-5023(96)80380-7)
- [L4] The results indicate that nerve conduction studies were more sensitive than sensibility testing in confirming the diagnosis of carpal tunnel syndrome, but the combination of the two studies is more sensitive than either test alone. [13] (10.1016/s0363-5023(82)80176-7)
- [L4] Ultrasound is a valid alternative confirmatory test compared with electrodiagnostic studies in detecting ulnar neuropathy at the elbow. [14] (10.1016/j.jhsa.2023.08.014)
- [L3] The study demonstrates that in primates there is no significant difference in the conduction velocity of peripheral nerves repaired in adults and those repaired in early life. [15] (10.1016/s0363-5023(83)80199-3)
- [L4] There is variability with respect to the thoroughness of electrodiagnostic studies and in the quality of information in the reports. [16] (10.1016/s0363-5023(98)80089-0)
- [L1] This approach demonstrated significant improvements in nerve conduction, pain reduction, and enhancement of hand function. [17] (10.1016/j.jht.2024.02.006)
- [L4] Electrodiagnostic studies revealed an acute median nerve lesion at the wrist with motor and/or sensory conduction blocks in 20/30 women. [18] (10.1016/s0266-7681(98)80232-5)
- [L3] SSN dysfunction, evidenced by reduced nerve amplitudes and supraspinatus muscle atrophy, significantly predicts poor functional outcomes following SHA, even when tuberosities are well healed. [19] (10.1016/j.jse.2025.07.001)
- [L3] Given specific clinical criteria for establishing the diagnosis of carpal tunnel syndrome, electrodiagnostic testing does not appear to correlate with improved final symptomatic outcome after carpal tunnel release. [20] (10.1016/s0363-5023(96)80164-x)
- [L2] We advocate surgical intervention for patients with symptoms only, even when electrodiagnostic studies are normal. [21] (10.1053/jhsu.2001.26327)
- [L2] Compound muscle action potential amplitude, but not other conventional electrodiagnostic parameters, was predictive of functional outcomes after in situ decompression of the ulnar nerve. [22] (10.1016/j.jhsa.2022.10.008)
- [L5] This strength recovers gradually as the median nerve heals, but never returns to normal, indicating that this test can be extrapolated to the reinnervation of the abductor pollicies brevis. [23] (10.1016/s0266-7681(03)00022-6)
- [L4] The incidence of abnormal conduction times was not reliably correlated with either age or duration of paralysis. [24] (10.1016/s0363-5023(88)80132-1)
- [L4] The study confirms the high diagnostic value of the pre-operative antidromic sensory conduction velocity findings. [25] (10.1016/0266-7681(88)90161-1)
- [L5] EDX reports should specifically indicate abnormalities of latency and conduction and present a clear description of the probable pathophysiologic processes rather than just compiling slight abnormalities. [26] (10.1016/s0363-5023(96)80298-x)
- [L5] There is a severe discordance between the estimated prevalence of mild-to-moderate carpal tunnel syndrome based on clinical signs and symptoms (73%) versus electrodiagnostic studies and ultrasound (51%), calling into question whether clinicians can confidently diagnose patients with mild-to-moderate CTS. [27] (10.1097/corr.0000000000002822)
- [L3] The sensitivity of the neurometer test alone was 69% and specificity was 100%, increasing to 84% sensitivity when combined with quantitative sensibility testing. [28] (10.1016/0363-5023(92)90117-8)
- [L4] The majority of neurosurgeons and orthopaedic surgeons seldom operate without electrodiagnostic confirmation in line with the Dutch consensus guideline on this subject. [29] (10.1016/j.jhse.2007.09.007)
- [L4] Although there are essential differences in these two tests, when used together they present a clearer picture of the patient's sensory status than either test used alone. [31] (10.1016/s0894-1130(87)80010-8)
- [L3] Upper arm motor nerve conduction velocity (MNCV) might be a useful predictor of poor surgical outcome. [32] (10.1177/17585732241293360)
- [Paper] The results showed that when the in situ nerve strain reached 8.1 ± 0.5%, the compound muscle action potential was not evoked. [33] (10.1016/s0736-0266(02)00080-3)
- [L3] The relative slowing of the antidromic sensory conduction velocity of the median nerve to the ring finger is determined easily and efficiently and imposes minimal strain on the patient. [34] (10.1016/j.jhsa.2004.04.026)
- [L4] There is a significant discrepancy between the practice recommended by the Danish Society of Neurophysiology of performing neurophysiological investigations (NI) in all cases of suspected CTS and what is actually done in most surgical departments. [35] (10.1016/s0266-7681(97)80443-3)
- [L4] The results of intraoperative conduction latencies indicated a dramatic and immediate reduction in the conduction latency across the carpal canal in all but seven patients, two of whom had diabetes. [36] (10.1016/s0363-5023(78)80119-1)
- [L4] The conduction velocity of the ulnar nerve after an anterior transposition is determined by both the position of the elbow and the location for the measurement of the skin distance. [37] (10.1016/s0363-5023(87)80051-5)
- [L3] The changes in electrophysiological findings occurring spontaneously in carpal tunnel syndrome and after treatment by injection are not statistically significant at two years. [38] (10.1016/0266-7681(92)90191-4)
- [L3] DML is a simple test with a predictive value of the postoperative neurophysiological and clinical outcome of carpal tunnel syndrome. [39] (10.1016/s0266-7681(97)80355-5)
- [L5] This underscores the need for surgeons to carefully evaluate suprascapular nerve integrity in such cases. [40] (10.1186/s12891-025-09195-6)
- [L3] All patients had good clinical and electrophysiological recovery at 6 months. [41] (10.1177/1558944716660555fx)
- [L4] Results suggest that carpal tunnel injection is also a reasonably accurate diagnostic test, as a good response to injection is an excellent diagnostic and prognostic sign for surgical treatment. [42] (10.1016/s0363-5023(84)80065-9)
- [L4] Intraoperative electrodiagnosis may offer limited value in neonatal brachial plexus palsy surgery, but there is insufficient evidence to reach robust conclusions. [44] (10.1177/17531934261478357)
- [L3] Receiver operating characteristic curves showed distal sensory latency measurement to be a superior diagnostic test, with 3.3 ms as optimal upper limit of normal, giving a sensitivity of 74% and a specificity of 87%. [45] (10.1016/s0363-5023(96)80020-7)
- [L1] Three weeks after the operation 77% of the patients in the tourniquet group had denervation in other than thenar muscles. [46] (10.1016/s0363-5023(89)80011-5)
References
[1] Use of nerve conduction studies in carpal tunnel syndrome. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231191685
[2] Correlation of Clinical Signs with Nerve Conduction Tests in the Diagnosis of Carpal Tunnel Syndrome. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90244-5
[3] Provocative motor nerve conduction testing in presumptive carpal tunnel syndrome unconfirmed by traditional electrodiagnostic testing. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(97)80045-7
[4] A comparison of traditional electrodiagnostic studies, electroneurometry, and vibrometry in the diagnosis of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80165-1
[5] Use of motor nerve conduction testing and vibration sensitivity testing as screening tools for carpal tunnel syndrome in industry. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90116-7
[6] Electrical studies as a prognostic factor in the surgical treatment of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80384-4
[7] Diagnostic testing in carpal tunnel syndrome. The Journal of Hand Surgery. 2000. DOI: 10.1067/jhsu.2000.jjhsu00025a1le01
[8] Electrical studies as a prognostic factor in carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80222-x
[9] Diagnosis of Mild-to-moderate Idiopathic Median Neuropathy at the Carpal Tunnel Based on Signs and Symptoms is Discordant From Diagnosis Based on Electrodiagnostic Studies and Ultrasound. Clinical Orthopaedics & Related Research. 2023. DOI: 10.1097/corr.0000000000002751
[10] Electrodiagnostic testing and carpal tunnel release outcome. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(05)80209-6
[11] Sensitivity of the Various Tests for the Diagnosis of Carpal Tunnel Syndrome. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90245-3
[12] Electrical studies as a prognostic factor in the surgical treatment of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80380-7
[13] Nerve conduction studies and sensibility testing in carpal tunnel syndrome. The Journal of Hand Surgery. 1982. DOI: 10.1016/s0363-5023(82)80176-7
[14] Diagnosis of Ulnar Neuropathy at the Elbow Using Ultrasound — A Comparison to Electrophysiologic Studies. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.08.014
[15] Nerve conduction velocity, microscopic, and electron microscopy studies comparing repaired adult and baby monkey median nerves. The Journal of Hand Surgery. 1983. DOI: 10.1016/s0363-5023(83)80199-3
[16] Electrodiagnostic reports of median neuropathy at the wrist. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80089-0
[17] Effectiveness of chitosan phonophoresis on ulnar nerve conduction velocity, pain relief, and functional outcomes for mild to moderate cubital tunnel syndrome: A double-blind randomized controlled trial. Journal of Hand Therapy. 2024. DOI: 10.1016/j.jht.2024.02.006
[18] Pregnancy-Related Carpal Tunnel Syndrome. Journal of Hand Surgery. 1998. DOI: 10.1016/s0266-7681(98)80232-5
[19] Radiological and electrodiagnostic insights into suprascapular nerve dysfunction: a key predictor of poor functional outcomes in shoulder hemiarthroplasty. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2025.07.001
[20] Electrodiagnostic testing and carpal tunnel release outcome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80164-x
[21] The rationale for and efficacy of surgical intervention for electrodiagnostic-negative cubital tunnel syndrome. The Journal of Hand Surgery. 2001. DOI: 10.1053/jhsu.2001.26327
[22] Electrodiagnostic Predictors of Outcomes After In Situ Decompression of the Ulnar Nerve. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2022.10.008
[23] Re. Clinical value of electrodiagnostic testing following repair of peripheral nerve lesions: a prospective study. Th. H.J. Van de Kar, J.B. Jaquet, J. Meulstee, C.B.H. Molenaar, R.J. Schimsheimer, S.E.R. Hovius. Journal of Hand Surgery 2002: 27B(4): 345–349.. Journal of Hand Surgery. 2003. DOI: 10.1016/s0266-7681(03)00022-6
[24] The paraplegic hand: Electrodiagnostic studies and clinical findings. The Journal of Hand Surgery. 1988. DOI: 10.1016/s0363-5023(88)80132-1
[25] Assessment of sensory nerve conduction in carpal tunnel syndrome before, during and after operation. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90161-1
[26] Electrodiagnostic testing in hand surgery. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80298-x
[27] CORR Insights®: Diagnosis of Mild-to-moderate Idiopathic Median Neuropathy at the Carpal Tunnel Based on Signs and Symptoms is Discordant From Diagnosis Based on Electrodiagnostic Studies and Ultrasound. Clinical Orthopaedics & Related Research. 2023. DOI: 10.1097/corr.0000000000002822
[28] The utility of portable nerve conduction testing for patients with carpal tunnel syndrome: A prospective clinical study. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90117-8
[29] Current Practice in the Use of Nerve Conduction Studies in Carpal Tunnel Syndrome by Surgeons in the Netherlands. Journal of Hand Surgery (European Volume). 2007. DOI: 10.1016/j.jhse.2007.09.007
[30] Probability_and_Pathophysiology_S0363502312002821. 2002.
[31] Correlating Semmes-Weinstein monofilament mappings with sensory nerve conduction parameters in Hansen's disease patients: An update. Journal of Hand Therapy. 1987. DOI: 10.1016/s0894-1130(87)80010-8
[32] Clinical significance of upper arm motor nerve conduction velocity in cubital tunnel syndrome. Shoulder & Elbow. 2024. DOI: 10.1177/17585732241293360
[33] In situ strain and stress of nerve conduction blocking in the brachial plexus. Journal of Orthopaedic Research. 2002. DOI: 10.1016/s0736-0266(02)00080-3
[34] Relative slowing of the median antidromic sensory nerve conduction velocity to the ring finger in screening for carpal tunnel syndrome. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2004.04.026
[35] Operative Treatment of Carpal Tunnel Syndrome in Denmark. Journal of Hand Surgery. 1997. DOI: 10.1016/s0266-7681(97)80443-3
[36] Intraoperative changes in motor nerve conduction latency in carpal tunnel syndrome. The Journal of Hand Surgery. 1978. DOI: 10.1016/s0363-5023(78)80119-1
[37] Validity of nerve conduction velocity studies after anterior transposition of the ulnar nerve. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80051-5
[38] Nerve Conduction Studies after Treatment for Carpal Tunnel Syndrome. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90191-4
[39] Carpal Tunnel Syndrome: Neurophysiological Results of Surgery Based on Preoperative Electrodiagnostic Testing. Journal of Hand Surgery. 1997. DOI: 10.1016/s0266-7681(97)80355-5
[40] Electromyography does not show adequate effectiveness in diagnosis of suprascapular nerve lesions caused by rotator cuff tear in rat model. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-09195-6
[41] Should Single-Stage Opponensplasty Be Added at the Time of Release for Severe Carpal Tunnel Syndrome?. HAND. 2016. DOI: 10.1177/1558944716660555fx
[42] Diagnostic and therapeutic value of carpal tunnel injection. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80065-9
[44] Intraoperative electrodiagnostic testing as a decision-making tool for neonatal brachial plexus palsy: a scoping review. Journal of Hand Surgery (European Volume). 2026. DOI: 10.1177/17531934261478357
[45] Evaluation of portable nerve conduction testing in the diagnosis of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80020-7
[46] Upper extremity tourniquet effects in carpal tunnel release. The Journal of Hand Surgery. 1989. DOI: 10.1016/s0363-5023(89)80011-5