Patients › Rehabilitation
Fracture ng Distal Radius (ORIF)
Staged rehabilitation after plate fixation of a distal radius fracture, from the first days to return to full activity.
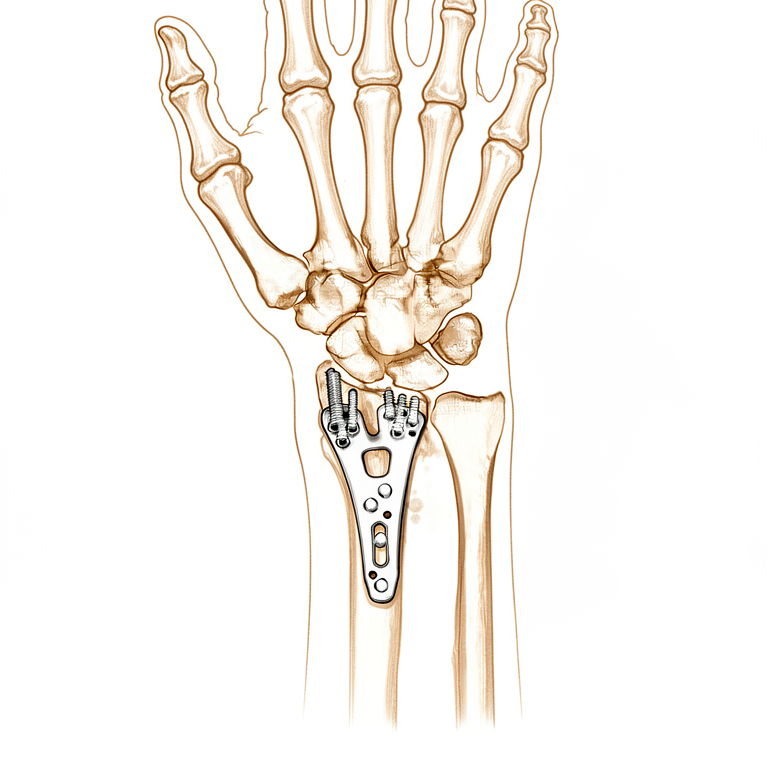
Ang protocol na ito ay nagsisilbing gabay sa iyong paggaling pagkatapos ng surgical fixation ng isang distal radius (pulso) fracture (open reduction and internal fixation, ORIF) kasama si Dr Kieran Hirpara sa Mater Private Hospital Rockhampton. Nagsisimula ito sa iyong home exercise program, na sinusundan ng structured clinical protocol na isinulat para sa iyong physiotherapist o hand therapist: dalhin ang pahinang ito o ang PDF nito sa iyong unang therapy visit upang manatiling coordinated ang iyong rehabilitasyon. Maaaring i-adjust ng iyong therapist ang plano depende sa pag-unlad ng iyong paggaling.
Kung mayroon kang anumang alalahanin tungkol sa iyong sugat pagkatapos ng operasyon, makipag-ugnayan sa mga rooms. Madalas na nakatutulong ang pagkuha ng larawan ng sugat at pag-email nito para sa pagsusuri.
Ano ang dapat asahan
Para sa pamamahala ng sugat, pamamaga, at peklat, tingnan ang gabay ng klinika para sa wound care.
Pagkatapos ng iyong operasyon, maaaring i-refer ka sa isang hand therapist para sa paggawa ng thermoplastic splint. Sa sitwasyong ito, ang splint ay isusuot nang pansamantala para sa ginhawa at proteksyon, at kakailanganin mo pa ring tanggalin ang splint para sa iyong home exercise program. Kung ikaw ay i-refer para sa isang splint, makakatanggap ka ng karagdagang impormasyon tungkol sa pagsuot at pag-aalaga nito.
Ang mga ehersisyo sa ibaba ay mahalaga para mabawi ang range of motion ng iyong mga daliri, pulso, at forearm. Ang init at yelo ay mabubuting modality na madalas gamitin para mabawi ang paggalaw, maibalik ang function, at mapabuti ang ginhawa. Kapag magaling na ang sugat, maaari kang maglagay ng init bago ang mga ehersisyo; maaaring gumamit ng ice pack pagkatapos upang maiwasan o mapakalma ang pamamaga.
Ang pamamahala ng peklat (partikular na ang masahe) ay napakahalaga pagkatapos ng distal radius surgery, upang ang mga tendon na dumadaan sa ilalim ng incision ay patuloy na dumulas nang malaya at hindi dumikit (adherent) sa naghihilom na peklat.
Ang volar locking plate ay idinisenyo upang hawakan ang fracture nang sapat na matatag para makapagsimula ng paggalaw nang maaga, at ang protocol na ito ay binuo batay doon. Ang pananaliksik na naghahambing ng maagang paggalaw ng pulso sa ilang linggong immobilisation pagkatapos ng volar plate fixation ay nagpapakita na ang pagsisimula ng paggalaw nang maaga ay maaaring mapabuti ang short-term movement, grip, at ginhawa nang hindi nakokompromiso ang posisyon ng fracture [1][2]. Kasabay nito, ang mga trial na naghahambing sa paggalaw ng pulso na nagsimula sa loob ng humigit-kumulang dalawang linggo laban sa paggalaw na nagsimula sa loob ng humigit-kumulang anim na linggo ay nakita na ang dalawang grupo ay magkatulad na pagdating ng tatlo hanggang anim na buwan [3], kaya habang may maagang benepisyo, hindi kailangang magmadali, at ang steady progression na nakasaad sa ibaba ay suportado nang husto. Ang paghilom ng buto ay sumusunod sa sarili nitong timeline anuman ang pakiramdam ng pulso, kung kaya't ang mga huling pag-iingat (walang weight-bearing, mabigat na pagbubuhat, o contact sport hanggang 12 linggo pagkatapos ng fracture) ay pinapanatili kahit na komportable na ang paggalaw.
Mga pag-iingat at limitasyon
Hinihikayat ang magaan na functional na paggamit ng iyong kamay para sa mga gawaing pang-araw-araw tulad ng pag-aalaga sa sarili, pagkain, pagbibihis, pagsusulat at pag-type.
Mahalagang protektahan ang wrist mula sa pagbuhat, paghawak nang mahigpit at impact sa mga unang linggo, at iwasan ang pagdadala ng bigat sa pamamagitan ng braso, ang mabibigat na pagbuhat at ang contact sport hanggang 12 linggo pagkatapos ng iyong bali. Ang banayad na pagpapalakas ay unti-unting ipinapakilala mula sa ika-4 na linggo, simula sa magaan na paggalaw ng mga daliri at isometric wrist exercises, at maingat na pinatataas upang hindi masira ang maagang proteksyong ito.
Ito ang mga ehersisyo mula sa iyong handout, para sa pagbawi ng paggalaw ng iyong mga daliri, pulso at forearm. Kung mayroon kang splint, tanggalin ito para sa iyong mga ehersisyo. Simulan ang mga ito ayon sa gabay ni Dr Hirpara at ng iyong therapist.
Iyong mga ehersisyo

Kieran Hirpara 4.0
Wrist flexion / extension
Ipatong ang iyong siko sa isang mesa at dahan-dahang i-rock ang iyong pulso nang pabalik-balik (o ipatong ito sa gilid ng isang mesa o armchair, gaya ng nasa larawan). Kapag mas komportable na, gamitin ang kabilang kamay sa palad upang itulak ang pulso pabalik (ang mga daliri ay nakaturo sa kisame), pagkatapos ay sa kabilang direksyon (ang mga daliri ay nakaturo sa sahig), habang pinapanatiling maluwag ang mga daliri. Panatilihin ang bawat stretch sa loob ng 15 segundo.
10 beses sa bawat direksyon, 4 na beses araw-araw

Kieran Hirpara 4.0
Rotasyon ng forearm (pronation / supination)
Habang ang iyong siko ay nasa iyong tabi at ang iyong forearm ay nasa neutral na posisyon (nakataas ang hinlalaki), dahan-dahang i-rotate ang iyong palad pataas patungo sa kisame (supination), manatili sa posisyong ito sa loob ng 3–5 segundo, pagkatapos ay ibalik sa neutral. Ulitin ang pag-rotate ng palad pababa patungo sa sahig (pronation). Huwag hayaang humiwalay ang iyong siko mula sa iyong katawan. Maaari mong tulungan ang paggalaw gamit ang iyong kabilang kamay, na nakahawak sa antas ng pulso.
10 beses sa bawat direksyon, 4 na beses araw-araw
Kieran Hirpara 4.0
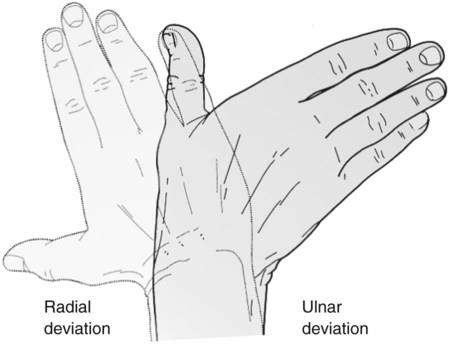
Ulnar / radial deviation
Ipatong ang iyong kamay at forearm sa isang patag na ibabaw. Habang pinapanatiling hindi gumagalaw ang iyong forearm, dahan-dahang igalaw ang iyong pulso at kamay mula sa magkabilang panig (gaya ng nasa larawan).
10 beses, 4 na beses araw-araw
Kieran Hirpara 4.0
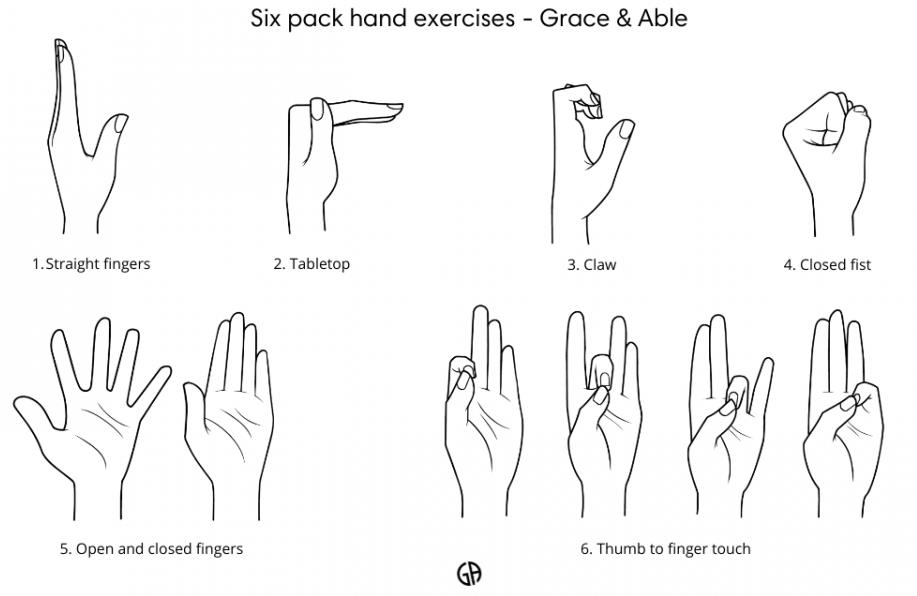
Anim na ehersisyo para sa kamay
Habang ang iyong kamay ay nasa harap mo at ang iyong pulso ay diretso, gawin ang anim na posisyong ipinapakita: direktong mga daliri; “tabletop” (itiklop sa ibabang mga knuckles, diretso ang mga daliri); “hook” (itiklop ang mga dulo ng daliri, nakataas ang mga knuckles); mahigpit na kamao na may hinlalaki sa ibabaw ng mga daliri; ibuka ang mga daliri pagkatapos ay pagdikitin muli; at idikit ang hinlalaki sa bawat dulo ng daliri, mula sa hintuturo hanggang sa kalingkingan.
5–10 ng bawat isa, 2–3 beses sa isang araw; ituloy ayon sa kakayahan
Simulan lamang ang mga ehersisyo sa ibaba ayon sa gabay ni Dr Hirpara at ng iyong hand therapist, at manatili sa anumang range at limitasyong ibinigay sa iyo. Dahil ang bali ay pinagkakabit ng isang plate, maaaring simulan nang maaga ang paggalaw ng wrist sa halip na hintayin pang magdugtong ang buto. Ang pagbaluktot ng wrist, pag-ikot ng forearm, at paggalaw nang side-to-side ay pumipigil sa paninigas ng joint, at ang six-pack hand exercises ay pinapanatiling gumagalaw ang mga daliri, thumb, at knuckles — ang paninigas ng mga daliri ay mas karaniwang problema pagkatapos ng operasyong ito kaysa sa problema sa buto. Gawin ang mga ito nang paunti-unti ngunit madalas. Itigil ang anumang nagdudulot ng matalas na sakit sa bahagi ng bali.
Ang iyong clinical protocol
Ang natitirang bahagi ng pahinang ito ay ang accelerated clinical protocol para sa isang distal radius fracture na ginamot sa pamamagitan ng open reduction and internal fixation gamit ang isang volar plate. Ang seksyong ito ay ibibigay sa iyong physiotherapist o hand therapist, at ang bawat phase sa ibaba ay nagsisimula sa isang paliwanag sa simpleng Ingles tungkol sa kung ano ang nangyayari.
1–4 Araw pagkatapos ng iyong operasyon
Sa unang ilang araw, ang pokus ay ang pagprotekta sa fixation, pagpapababa ng pamamaga, at pagpapanatiling gumagalaw ng iyong mga daliri, pulso, forearm, siko at balikat. Ang iyong surgical bandage ay mananatili hanggang sa ika-3 araw, kung kailan ito babawasan at muling bibigyan ng dressing ang sugat. Panatilihing nakataas ang kamay kapag nagpapahinga, gamitin ito para sa mga magagaan na pang-araw-araw na gawain (mas mababa sa 1–2 kg) sa loob ng komportableng limitasyon, at iwasan ang paglalagay ng bigat (weight-bearing) sa braso, mahigpit na paghawak o pagbuhat. Ang splint ay hindi rutinang kinakailangan, ngunit maaaring mag-ayos nito kung ikaw ay babalik sa trabaho o kung mas masakit ang pulso.
Para sa iyong physiotherapist:
Bago ang paggamot, suriin ang x-ray ng pasyente, ulat ng operasyon at nakaraang kasaysayang medikal (PMHx), at makipag-ugnayan sa surgeon na nanggamot tungkol sa katatagan ng fixation ng fracture at sa inaasahang prognosis.
Edukasyon at mga pag-iingat
- Iwasan ang paglalagay ng bigat (weight-bearing) sa braso, mahigpit na paghawak o pagbuhat
- Hikayatin ang paggamit ng apektadong kamay para sa mga magagaan (mas mababa sa 1–2 kg) na gawaing pang-araw-araw (ADL) sa loob ng limitasyon ng sakit at normal na pattern ng paggalaw
Pamamahala
- Splint: walang kinakailangan, ngunit maaaring gamitin kung ang pasyente ay babalik sa trabaho o kung mayroong pagtaas ng sakit; isaalang-alang ang isang thermoplastic splint o off-the-shelf support
- Sugat: ang mga surgical dressing/bandage ay dapat manatiling hindi nagagalaw hanggang sa ika-3 araw; bawasan ang bandage at muling lagyan ng dressing ang sugat mula sa ika-3 araw pagkatapos ng operasyon; edukasyon tungkol sa pamamahala ng sugat
- Oedema: magbigay ng edukasyon tungkol sa elevation; magbigay ng compression therapy at retrograde massage kung kinakailangan
- Mga Ehersisyo: magbigay ng active six pack exercises upang mapanatili ang range of motion (ROM) ng daliri; magbigay ng active wrist, forearm at finger range of motion exercises; hikayatin ang regular na active elbow at shoulder ROM
Ika-2–4 linggo pagkatapos ng iyong operasyon
Ang iyong mga tahi ay tatanggalin sa ika-10–14 araw, at ang scar massage ay magsisimula kapag ang sugat ay sapat na ang paghilom. Magpapatuloy ang exercise program (ang six pack exercises ay ititigil kapag nabawi na ng iyong mga daliri ang buong paggalaw) at magsisimula ang banayad na muscle-activation (isometric) wrist strengthening. Sa yugtong ito, ang pulso ay dapat gumalaw pa rin gamit lamang ang sarili nitong lakas ng kalamnan: walang sinuman, kabilang ka, ang dapat na magtulak o mag-stretch nito nang passively sa ngayon, dahil ang bali ay naghihilom pa lamang. Patuloy na iwasan ang weight-bearing, mahigpit na paghawak (gripping) at pagbuhat; hinihikayat ang mga magagaan na gawaing pang-araw-araw na mababa sa 1–2 kg. Hindi ka dapat magmaneho habang ang iyong pulso ay nasa splint; ang pagmamaneho ay magpapatuloy kapag wala ka na sa splint, gaya ng kumpirmasyon sa iyong review.
Para sa iyong physiotherapist:
Mga Assessment
- Self-reported assessments: Patient-Rated Wrist Evaluation (PRWE), Disabilities of the Arm, Shoulder and Hand (DASH)
- Oedema circumferential measurements
- Visual analogue pain scale (VAS) o numerical rating scale
- Active range of motion (AROM) goniometry measurements: kamay, pulso
- Subjective review, kabilang ang compliance ng pasyente sa regime, functional use ng kamay sa mga ADL task, at mga problema/alalahanin
Edukasyon at mga pag-iingat
- Iwasan ang weight-bearing gamit ang braso, mahigpit na paghawak o pagbuhat
- Walang passive wrist movement
- Hikayatin ang paggamit ng apektadong kamay para sa magagaan na (mas mababa sa 1–2 kg) ADL tasks sa loob ng limitasyon ng sakit at normal na movement patterns
- Bawal magmaneho habang nasa splint; ang pagmamaneho ay magpapatuloy kapag wala na sa splint, kumpirmado sa review
Pamamahala (Management)
- Sugat/scar: pagtanggal ng mga tahi sa ika-10–14 araw; simulan ang scar management kung naaangkop, depende sa pag-unlad ng paghilom
- Oedema: isaalang-alang ang paggamit ng compression bandaging, retrograde massage, manual oedema mobilisation (MEM), contrast bathing at/o elevation kung kinakailangan
- Mga ehersisyo: itigil ang active six pack exercises kapag nakamit na ang full finger range; isaalang-alang ang passive finger at thumb exercises, kabilang ang place/hold, kung ang active ROM sa kamay ay hindi buo; ipagpatuloy ang active wrist ROM exercises; hikayatin ang regular na active elbow at shoulder ROM; simulan ang wrist isometric strengthening
Troubleshooting
- Bantayan ang mga palatandaan ng impeksyon sa sugat, mga pagbabago sa sensory sa kamay, o mga maagang palatandaan ng complex regional pain syndrome (CRPS)
- Tukuyin ang mga aberrant movement patterns at mamagitan kung kinakailangan
Ika-4–6 linggo pagkatapos ng iyong operasyon
Ang pagpapalakas ay nagsisimula nang dahan-dahan sa yugtong ito: low-resistance finger strengthening mula ika-4 na linggo, habang ang isometric wrist work ay nagpapatuloy at unti-unting itinataas ang antas. Kung ang iyong x-ray ay kasiya-siya at ang fixation ay stable, ang mga gentle passive wrist stretch (kung saan ang wrist ay iginagalaw sa tulong ng iyong kabilang kamay o ng iyong therapist) ay maaaring magsimula sa ika-4–6 linggo. Ang pagbabalik ng paggalaw ay nananatiling prayoridad kaysa sa pagbuo ng lakas. Patuloy na iwasan ang weight-bearing gamit ang braso at ang mabibigat na pagbuhat, habang patuloy na ginagamit ang kamay para sa mga magagaan na pang-araw-araw na gawain.
Para sa iyong physiotherapist:
Mga Assessment
- Oedema circumferential measurements
- Visual analogue pain scale o numerical rating scale
- AROM goniometry measurements at kalidad ng movement patterns
- Subjective review, kabilang ang compliance ng pasyente sa regime, functional use ng kamay sa mga ADL task, at mga problema/alalahanin
- Grip strength gamit ang dynamometer (3 sa bawat limb)
Edukasyon at mga pag-iingat
- Iwasan ang weight-bearing gamit ang braso, o mabibigat na pagbuhat
- Hikayatin ang paggamit ng apektadong kamay para sa mga magagaan (mas mababa sa 1–2 kg) na ADL task sa loob ng limitasyon ng sakit at normal na movement patterns
Pamamahala
- Scar: ipagpatuloy ang scar management kung kinakailangan
- Oedema: ipagpatuloy ang compression therapy, retrograde massage, MEM at elevation kung kinakailangan; itigil ang contrast bathing
- Mga Ehersisyo: ipagpatuloy ang passive finger at thumb exercises kung hindi pa full ang ROM; ipagpatuloy ang active wrist ROM exercises; simulan ang finger strengthening exercises laban sa low resistance sa ika-4 na linggo; simulan ang gentle passive wrist exercises sa ika-4–6 linggo kung ang ORIF ay stable at ang x-ray ay kasiya-siya; hikayatin ang regular na active elbow at shoulder ROM; ipagpatuloy/itaas ang antas ng isometric wrist strengthening exercises
Troubleshooting
- Suriin para sa mga palatandaan ng CRPS at shoulder pain
- Isaalang-alang ang dami ng mga ehersisyo sa home programme at bigyang-prayoridad ang ROM kaysa sa lakas
- Kung ang wrist ROM ay labis na limitado, isaalang-alang ang pagsisimula ng gentle passive range of motion (PROM) wrist exercises sa loob ng 4/10 VAS, nang may pahintulot ng surgeon
Ika-6–8 linggo pagkatapos ng iyong operasyon
Ang yugtong ito ay nagsisimula ng unti-unting pagbabalik sa buong aktibidad sa susunod na 3 linggo. Ang pagpapalakas ng pulso (wrist strengthening) ay tataas hanggang sa magaan na mga pabigat (0.5–1.0 kg) o low-resistance theraband, at tataas ang resistance para sa pagpapalakas ng mga daliri. Dalawang mahigpit na limitasyon ang nananatili: walang weight-bearing, mabigat na pagbubuhat o contact sport hanggang 12 linggo pagkatapos ng bali (fracture). Isasaalang-alang ng iyong therapist ang pag-discharge sa iyo kapag mayroon ka nang buong paggalaw at angkop na pagbabalik ng function.
Para sa iyong physiotherapist:
Mga Assessment
- Oedema circumferential measurements kung kinakailangan
- Visual analogue pain scale o numerical rating scale
- AROM goniometry measurements
- Grip strength
- Subjective review
Edukasyon at mga pag-iingat
- Unti-unting pagbabalik sa buong aktibidad sa susunod na 3 linggo
- Iwasan ang weight-bearing, mabigat na pagbubuhat at contact sport hanggang 12 linggo post fracture
Pamamahala (Management)
- Scar: ipagpatuloy ang scar management kung kinakailangan
- Oedema: ipagpatuloy ang oedema management kung kinakailangan
- Mga Ehersisyo: ipagpatuloy ang passive finger at thumb exercises kung hindi buo ang ROM; ipagpatuloy ang active at passive wrist ROM exercises kung kinakailangan; dagdagan ang resistance sa mga finger strengthening exercises; simulan ang wrist strengthening exercises gamit ang 0.5–1.0 kg weights o low-resistance theraband; itaas ang mga weights at resistance na ginagamit sa wrist strengthening programme ayon sa tolerance
Troubleshooting
- Isaalang-alang/simulan ang night serial progressive splinting, boxing glove o dynamic splinting kung mabagal ang pag-unlad ng ROM
- Bantayan ang anumang mga palatandaan ng wrist instability at gamutin nang naaayon
- Isaalang-alang ang discharge kapag buo na ang ROM at angkop na ang pagbabalik ng function
- Isaalang-alang ang referral pabalik sa treating doctor kung ang kondisyon ay nag-plateau at/o mayroong poor outcome
Ang protocol na ito ay isinulat sa pakikipagtulungan kina Sarah Farrell, BOccThy AHT, at Kristy Gerlach, BOccThy AHT.
Pagkatapos ng iyong protocol
Ang protocol na ito ay kasabay ng pangkalahatang payo sa paggaling ng klinika; tingnan ang pamamahala ng sakit pagkatapos ng operasyon, pag-aalaga ng sugat at mga pangunahing kaalaman sa hand therapy. Para sa mismong operasyon at sa pinsalang ginagamot nito, tingnan ang distal radius fixation (ORIF) at distal radius fracture. Ang phased plan sa itaas ay naaayon sa nailathalang ebidensya sa rehabilitasyon pagkatapos ng volar locking plate fixation, at ang iyong patuloy na paggaling ay ginagabayan nang indibidwal ng iyong physiotherapist o hand therapist ayon sa pag-unlad ng iyong pulso.
Mga Sanggunian
[1] Quadlbauer S, Pezzei C, Jurkowitsch J, et al. Immediate mobilization of distal radius fractures stabilized by volar locking plate results in a better short-term outcome than a five week immobilization: a prospective randomized trial. Arch Orthop Trauma Surg. 2022;142(5):1–11. https://pubmed.ncbi.nlm.nih.gov/34852677/ [2] Gutiérrez-Espinoza H, Araya-Quintanilla F, Olguín-Huerta C, et al. Effectiveness of early versus delayed motion in patients with distal radius fracture treated with volar locking plate: a systematic review and meta-analysis. Hand Surg Rehabil. 2020;39(4):261–271. https://www.sciencedirect.com/science/article/abs/pii/S2468122920302231 [3] Lozano-Calderón SA, Souer S, Mudgal C, Jupiter JB, Ring D. Wrist mobilization following volar plate fixation of fractures of the distal part of the radius. J Bone Joint Surg Am. 2008;90(6):1297–1304. https://pubmed.ncbi.nlm.nih.gov/18519324/ [4] Miller LK, Jerosch-Herold C, Shepstone L. Effectiveness of edema management techniques for subacute hand edema: a systematic review. J Hand Ther. 2017;30(4):432–446. https://pubmed.ncbi.nlm.nih.gov/28807598/
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Distal Radius Fracture (ORIF) — Post-operative Rehabilitation Evidence Brief
Topic scope: post-operative rehabilitation after open reduction and internal fixation (ORIF) of a distal radius fracture with a volar locking plate. This brief backs an early-motion-but-protected hand/wrist pathway delivered with hand therapy, where wrist motion begins early while bone-dependent loading (weight-bearing, heavy lifting, contact sport) is deferred until ~12 weeks. It does not cover the indications for surgery vs casting, nor fragment-specific/dorsal/bridge-plate constructs (which carry their own loading rules).
Defining principle of the rehab here: a volar locking plate is a fixed-angle construct stable enough to permit immediate wrist motion — the screws lock to the plate and hold the articular reduction independent of the cast. So (unlike a cast-treated fracture, and unlike a tendon or ligament repair) the wrist does not need weeks of immobilisation to protect the reduction: the rehab is an early-movement pathway — finger/forearm/wrist active motion and oedema control from day one, splint for comfort only, isometric then progressive strengthening from ~weeks 4–6. The one timeline that is not negotiable is bone healing: union takes ~6–12 weeks regardless of how the wrist feels, which is why weight-bearing, heavy lifting and impact are held to 12 weeks even once motion is comfortable.
A. PROCEDURE & CONSTRUCT — what the rehab is protecting
Volar locking plate fixation is the dominant operative construct for displaced distal radius fractures and is the reference standard against which other techniques are compared. Key surgical-outcome facts that shape the rehab:
- Volar locking plates restore and hold articular reduction reliably, and across randomised comparisons give equivalent or better functional outcomes than non-operative care and competing fixation methods (dorsal plating, intramedullary nailing, fragment-specific), with most differences favouring early function rather than final endpoint [JAAOS controversies review 2014; Hand Clinics plate-fixation review 2021; IM-nail-vs-volar-plate RCTs].
- The fixed-angle construct is the rationale for early motion. Because the locking screws hold the subchondral fragments rigidly, the plate — not a cast — maintains the reduction, so wrist motion can start before union without displacing the fracture [Hand Clinics 2021; accelerated-rehab RCT, JBJS 2014].
- In older patients the operative-vs-conservative outcome gap is small. A 3-year RCT in patients >70 found volar plating and non-operative care converged on similar patient-reported function — context that keeps post-operative rehab pragmatic and patient-centred rather than aggressive [BMC Musculoskelet Disord 2022; Hand Clinics geriatric review 2021].
- Recovery is gradual. Range, grip and patient-reported scores improve steadily over the first 3–6 months; the construct permits early motion but does not accelerate the biology of healing or the return of grip strength.
B. REHABILITATION / HAND-THERAPY EVIDENCE
The central rehab questions for this construct are (1) when to start wrist motion, (2) how much supervised therapy is needed, and (3) what the strengthening timeline should be. The evidence is clear on the first, nuanced on the second, and consensus-driven on the third.
- Early motion is safe and gives a short-term advantage. Multiple RCTs and a systematic review show that starting wrist motion early after volar plating improves short-term ROM, grip and comfort without compromising the radiographic reduction [accelerated-rehab RCT, JBJS 2014; early-vs-late motion RCT, HAND 2018; Hand Therapy systematic review 2020]. This is the direct warrant for the day-1 finger/forearm/wrist program in this protocol.
- "Early" need not mean "immediate," and the advantage washes out by 3–6 months. The landmark trial comparing wrist mobilisation at ~2 weeks vs ~6 weeks found the two groups equivalent by 3–6 months [Lozano-Calderón / JBJS 2008]. So there is a genuine early benefit but no penalty for a measured, comfort-led progression — which is exactly why this protocol can be unhurried.
- Routine supervised physiotherapy adds little over a coached home program for most patients. Systematic reviews and RCTs repeatedly find that a structured home exercise program preceded by instruction/coaching performs as well as formal supervised therapy for uncomplicated cases, and that prescribed exercise programs add limited benefit over advice for impairment/activity outcomes [HEP-vs-supervised SR, J Hand Ther 2014; J Physiother SR 2017; Hand Clinics "is therapy needed?" 2021; Arch Orthop Trauma Surg 2020]. This supports a home-program-first model with hand-therapy review, escalating supervision for stiffness, oedema or slow progress — the structure of this protocol.
- Oedema control and scar/tendon-glide management are standard therapy elements. Elevation, retrograde massage, manual oedema mobilisation and (early) compression are the evidence-informed oedema toolkit [edema-management SR, J Hand Ther 2017]; scar massage to keep the flexor tendons gliding under the volar incision is consensus hand-therapy practice rather than RCT-derived.
Phased post-op timeline (volar locking plate, early-motion pathway)
Phases match this topic's synthesis.md. Timings are post-operative weeks; the 12-week
loading limit is referenced to the fracture (injury) date.
| Phase | Window | Splint | Motion / use | Strengthening | Notes |
|---|---|---|---|---|---|
| I — Protect & move | Days 1–4 | Comfort only, not routine | Active finger (six-pack), wrist, forearm, elbow & shoulder ROM from day 1; light ADL < 1–2 kg within pain limits | — | Surgical bandage to day 3, then redress. Oedema control + elevation. No weight-bearing, gripping or lifting |
| II — Active range & oedema | Week 2–4 | Comfort/work only (no driving while splinted) | Continue active wrist ROM (no passive yet); six-pack stops once fingers full | Isometric wrist activation begins | Sutures out day 10–14; start scar massage once healed. Watch for CRPS. PRWE/DASH baseline |
| III — Passive range & light load | Week 4–6 | Off | Add gentle passive wrist stretches at 4–6 wk if x-ray satisfactory & fixation stable | Finger strengthening (low resistance) from wk 4; upgrade isometrics | Movement still prioritised over strength |
| IV — Graded strengthening & return | Week 6–8 | Off | Restore/maintain full active & passive ROM | Wrist strengthening with 0.5–1.0 kg / light theraband, progress as tolerated | Graded return over ~3 wk. No weight-bearing, heavy lifting or contact sport until 12 weeks post-fracture. Discharge on full ROM + functional return |
The phase structure mirrors published surgeon/hand-therapy ORIF protocols (early ROM → scar + oedema → passive range + light resistance → progressive strengthening, with heavy load/sport held to ~12–16 weeks) [Physiopedia Colles' ORIF protocol; institutional ORIF rehab guidelines].
C. KEY CONTROVERSIES / EVIDENCE QUALITY
- How early to mobilise. Early motion (immediate–2 wk) gives a real short-term ROM/grip/comfort advantage that equalises by 3–6 months vs starting at ~6 weeks. The evidence therefore supports early motion but does not mandate aggression — a measured progression is fully defensible. Moderate–strong (multiple RCTs + SR).
- Supervised therapy vs coached home program. For uncomplicated fractures the best available evidence finds no consistent benefit of routine formal physiotherapy over a well-instructed home program; supervision is best targeted to stiffness, oedema, CRPS risk or slow progress. Moderate (SRs/RCTs), but heterogeneous.
- Strengthening and return-to-load timing. The week-by-week strengthening ramp and the 12-week loading hold are construct- and biology-based consensus, drawn from surgeon/hand- therapy protocols rather than a strengthening-timing RCT. Weak/consensus.
- Whether the wrist needs any immobilisation at all. Some trials report that omitting post-op immobilisation does not worsen outcomes after volar plating, supporting the "splint for comfort only" stance here. Moderate.
D. EVIDENCE STRENGTH FLAGS (summary)
- STRONG / MODERATE–STRONG (RCT / SR): early wrist motion after volar plating is safe and improves short-term ROM/grip/comfort without loss of reduction (accelerated-rehab RCT JBJS 2014; early-vs-late RCT HAND 2018; Hand Therapy SR 2020); ~2-wk vs ~6-wk mobilisation equivalent by 3–6 months (Lozano-Calderón JBJS 2008).
- MODERATE: volar locking plate is a reliable fixed-angle construct with equivalent/favourable outcomes vs alternatives (JAAOS 2014; Hand Clinics 2021); operative-vs-conservative outcomes converge in the elderly (BMC 2022); coached home program ≈ supervised therapy for uncomplicated cases (J Hand Ther 2014; J Physiother 2017; Hand Clinics 2021); evidence-based oedema management (J Hand Ther 2017).
- WEAK / CONSENSUS: the detailed strengthening ramp and 12-week loading limit (surgeon & hand-therapy protocols; biology- and construct-based, not trial-derived); scar/tendon-glide massage practice.
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Accelerated rehabilitation compared with a standard protocol after distal radial fractures treated with volar open reduction and internal fixation. J Bone Joint Surg Am. 2014. DOI: 10.2106/jbjs.m.00860
- Wrist mobilization following volar plate fixation of fractures of the distal part of the radius. J Bone Joint Surg Am. 2008. DOI: 10.2106/jbjs.g.01368
- Early versus late motion following volar plating of distal radius fractures. HAND. 2018. DOI: 10.1177/1558944718787880
- A systematic review of how daily activities and exercises are recommended following volar plating of distal radius fractures and the efficacy and safety of early versus late mobilisation. Hand Therapy. 2020. DOI: 10.1177/1758998320967032
- AAOS/ASSH Clinical Practice Guideline Summary: Management of Distal Radius Fractures. J Am Acad Orthop Surg. 2022. DOI: 10.5435/jaaos-d-21-00719
- Controversies in the management of distal radius fractures. J Am Acad Orthop Surg. 2014. DOI: 10.5435/jaaos-22-09-566
- Plate fixation of distal radius fractures. Hand Clinics. 2021. DOI: 10.1016/j.hcl.2021.02.008
- Non-operative treatment or volar locking plate fixation for dorsally displaced distal radius fractures in patients over 70 years — a three-year follow-up of a randomized controlled trial. BMC Musculoskelet Disord. 2022. DOI: 10.1186/s12891-022-05394-7
- Distal radius fracture: HEP versus supervised therapy — a systematic review. J Hand Ther.
- DOI: 10.1016/j.jht.2013.08.017
- Prescribed exercise programs may not be effective in reducing impairments and improving activity during upper limb fracture rehabilitation: a systematic review. J Physiother. 2017. DOI: 10.1016/j.jphys.2017.08.009
- Is therapy needed after distal radius fracture treatment — what is the evidence? Hand Clinics.
- DOI: 10.1016/j.hcl.2021.02.012
- Rehabilitation after distal radius fractures: is there a need for immobilization and physiotherapy? Arch Orthop Trauma Surg. 2020. DOI: 10.1007/s00402-020-03367-w
- Management of complications of distal radius fractures. Hand Clinics. 2015. DOI: 10.1016/j.hcl.2014.12.002
- A comparison of the accuracy of two sets of diagnostic criteria in the early detection of complex regional pain syndrome following surgical treatment of distal radial fractures. J Hand Surg Eur Vol. 2012. DOI: 10.1177/1753193412469142
Distal radius / rehabilitation literature (URLs)
- AAOS/ASSH Clinical Practice Guideline Summary: Management of Distal Radius Fractures (full summary). PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC9196973/
- Practical application of the 2020 distal radius fracture AAOS/ASSH clinical practice guideline: a clinical case. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC9035062/
- Rehabilitation for distal radial fractures in adults (Cochrane-style review). PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC9250132/
- Rehabilitation after distal radius fractures: opportunities for improvement. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC10569825/
- Rehabilitation following surgically treated distal radius fractures: do immobilization and physiotherapy affect the outcome? PMC. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8343619/
Published rehab protocols (surgeon / hand-therapy — basis for the phase structure)
- British Society for Surgery of the Hand / British Association of Hand Therapists — Distal Radius Fractures Working Group rehabilitation guidance (2024). https://www.hand-therapy.co.uk/_userfiles/pages/files/distal_radius_fractures_working_group_2024.pdf
- Colles' Fracture Post-Operative Rehabilitation Protocol. Physiopedia. https://www.physio-pedia.com/Colles%E2%80%99_Fracture_Post_Operative_Rehabilitation_Protocol
- Distal Radius ORIF Rehabilitation Guidelines. University of Virginia Department of Orthopaedic Surgery. https://med.virginia.edu/orthopaedic-surgery/wp-content/uploads/sites/242/2024/09/Distal-radius-ORIF.pdf
- Distal Radius ORIF Rehabilitation. Jared Lee, MD. https://jaredleemd.com/pdf/distal-radius-orif-rehabilitation/