Patients › Hand
Arthritis sa Basal ng Hinlalaki
Basal thumb arthritis — causes, symptoms, non-surgical options, and when surgery might help.
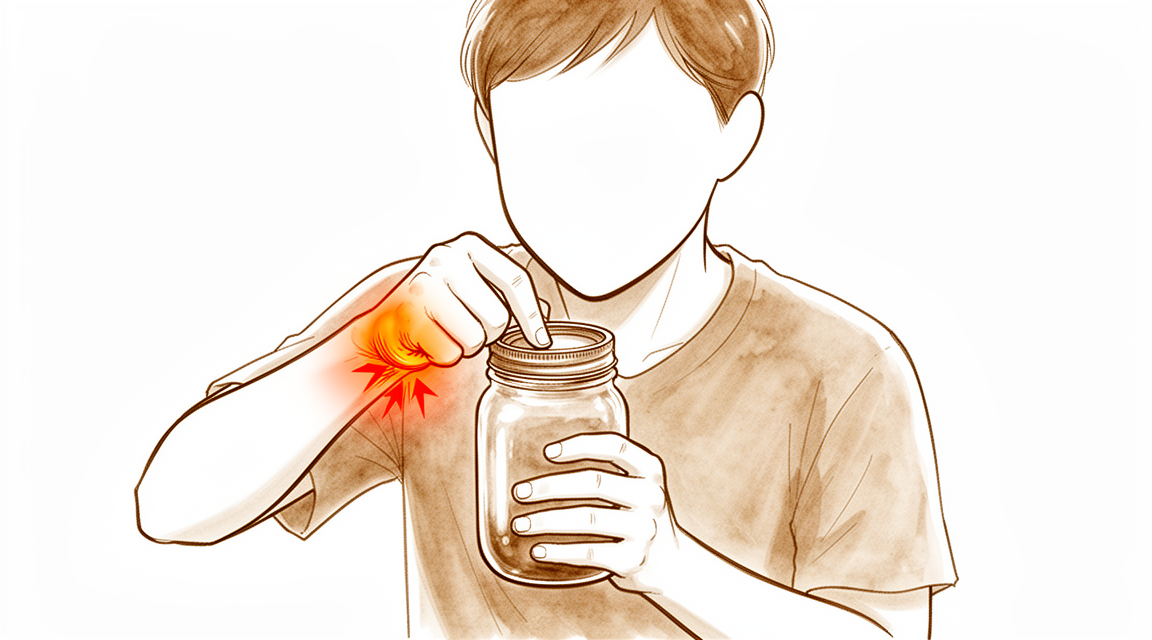
Ang iyong nararamdaman
Ang sakit ay nasa base ng iyong hinlalaki, sa malaman na bahagi malapit sa iyong pulso. Maaari itong umakyat patungo sa iyong forearm. Ang pag-pinch at pag-grip ang karaniwang nagdudulot nito, dahil direktang dinidiinan ng mga galaw na iyon ang pudpod na joint. Ang pagpihit ng susi, pagbubukas ng garapon, paghawak ng panulat o pagbuhat ng kettle ay pare-parehong dumidiin sa parehong lugar.
Madalas na naaapektuhan ang iyong pinch strength bago ang iyong pangkalahatang grip. Iyan ang dahilan kung bakit maaaring kaya mo pang magdala ng mga bag ng pinamili ngunit nahihirapan ka sa maliliit at maseselang gawain tulad ng pagsusulot ng sinulid sa karayom o paghila pataas ng zipper. Ang panghihina at sakit ay hindi laging tumutugma sa ipinapakita ng X-ray, kaya ang ilang tao na may kaunting pinsala sa joint ay maraming nararamdamang sintomas, at ang ilan na may pudpod na joint ay kaunti lamang ang nararamdaman.
Ang sakit ay madalas na sumisidhi pagkatapos gamitin ang iyong hinlalaki nang matagal-tagal, at maaari ka nitong gisingin sa gabi o naroroon na ito pagkagising mo. Karaniwang humuhupa ito sa pamamagitan ng pahinga, ngunit ang kirot ay may tendensiyang bumalik sa susunod na pagkakataong ikaw ay mag-pinch o mag-grip. Kung hindi humuhupa ang iyong mga sintomas, lumalala sa loob ng ilang linggo, ginigising ka sa gabi, o pumipigil sa iyong pagtatrabaho o paggamit ng iyong kamay, magpatingin sa iyong GP o humingi ng specialist review.
Sa paglipas ng panahon, ang mga pang-araw-araw na gawaing nangangailangan ng matibay na pinch ang nagiging pinakamahirap. Ang paghawak ng telepono, pagsusulat, paggamit ng gunting o pagpihit ng gripo ay maaaring maging asiwa o masakit.
Ano ang aktwal na nangyayari
Sa kailaliman ng base ng iyong hinlalaki ay may isang maliit na joint kung saan nagtatagpo ang buto ng hinlalaki at isang buto ng pulso. Gumagana ito na parang saddle: bilugan sa isang panig at hugis-tasa sa kabila, kaya ang iyong hinlalaki ay nakakaugoy, nakakaikot at nakakadiin sa iyong mga dulo ng daliri. Ang kalayaang iyon ang nagpapahintulot sa iyong mag-pinch, mag-grip at pumihit, ngunit nangangahulugan din ito na malaking puwersa ang sinasalo ng joint sa tuwing ginagamit mo ang iyong kamay.
Sa kondisyong ito, napupudpod ang makinis at madulas na surface sa loob ng joint na iyon. Kung wala ito, nagkikiskisan ang buto sa buto, at ang joint ay nagiging inflamed at namamaga. Nagiging masakit ang lining sa paligid nito, kaya pakiramdam ay sensitibo ang base ng iyong hinlalaki at maaari itong pulikatin sa malaman na bahagi sa ilalim ng iyong hinlalaki. Dahil hindi na napapanatili ng pudpod na joint sa lugar ang buto ng hinlalaki, maaaring dumulas palabas ng linya ang buto at magdulot ng nakikitang umbok kung saan nagtatagpo ang iyong hinlalaki at pulso.
Ang pagkapudpod ay karaniwang dahan-dahang nabubuo sa loob ng maraming taon. Mas karaniwan ito sa mga babaeng lampas na sa menopause, at madalas nitong naaapektuhan ang parehong hinlalaki. Habang lumalala ito, ang joint sa itaas ng base ng iyong hinlalaki, kung saan bumabaluktot ang hinlalaki, ay maaari ring lumuwag. Ang pagluwag na iyon ay maaaring magpabagsak o magpabaluktot nang patagilid sa hinlalaki kapag ikaw ay nagpi-pinch, na nagdaragdag sa panghihinang nararamdaman mo.
Ang sakit, panghihina at pagka-asiwa na nararamdaman mo ay pawang resulta ng pagkapudpod na ito. Ang pag-pinch at pag-grip ay nagdidiin sa mga pudpod na surface, kaya ang mga galaw na iyon ang pinakamasakit.
Ano ang maaari naming gawin tungkol dito
Si Dr Kieran Hirpara, isang upper-limb surgeon sa Mater Private Hospital Rockhampton, ay nagsisimula sa mga opsyon na hindi gaanong invasive na angkop sa iyong kondisyon. Ang mga pasyente ay karaniwang nirerefer sa aming klinika ng kanilang GP; kung iminungkahi ng isang physiotherapist na magpatingin sa amin, kakailanganin mo pa rin ng referral mula sa iyong GP upang maging eligible para sa Medicare rebate. Sa iyong appointment, kumukuha kami ng history, sinusuri ang iyong kamay at nagsasaayos ng imaging kung kinakailangan upang kumpirmahin ang diagnosis.
Ang unang hakbang ay pangangalagang kaya mong gawin nang mag-isa. Ang pagbabago sa kung paano mo ginagamit ang iyong kamay, ang pagbabawas sa mga gawaing nagbibigay ng load sa base ng hinlalaki, at ang pagsusuot ng splint na sumusuporta sa joint ay pawang makapagpapakalma sa mga sintomas. Layunin ng hand therapy na palakasin ang mga kalamnan na sumusuporta at nagpapatatag sa hinlalaki, na nag-aalis ng load sa mga pudpod na surface. Mabisa ang mga hakbang na ito sa mga unang yugto, at karaniwan naming binibigyan ang mga ito ng sapat na pagsubok bago pag-usapan ang anumang karagdagang hakbang.
Kung hindi sapat ang pangangalaga sa sarili, makatutulong ang mga gamot sa sakit at mga anti-inflammatory upang patuloy mong magamit ang iyong kamay. Ang injection ng cortisone sa loob ng joint ay maaaring magpakalma ng masakit na flare sa maikling panahon, bagaman karaniwang hindi nagtatagal ang ginhawa. Makatutulong din ito upang kumpirmahin na ang base ng hinlalaki ang tunay na pinagmumulan ng iyong sakit.
Pumapasok sa usapan ang operasyon kapag hindi nagbigay sa iyo ng sapat na pagbuti ang non-operative care, o kapag pinipigilan ka ng iyong mga sintomas na magtrabaho o gamitin ang iyong kamay. Nag-aalok kami ng joint replacement sa base ng hinlalaki, kung saan pinapalitan ang mga pudpod na surface upang maibsan ang sakit at mapanatiling gumagalaw ang hinlalaki. Gumagamit ang ilang surgeon ng ibang operasyon na tinatawag na trapeziectomy, na nag-aalis sa maliit na buto ng pulso sa halip na palitan ito. Pag-uusapan natin kung ano ang kahulugan ng bawat opsyon para sa iyong kamay at sabay nating pagpapasyahan kung ano ang angkop sa iyo.
Ano ang dapat asahan
Kung walang gamutan, ang arthritis sa base ng hinlalaki ay karaniwang dahan-dahang nabubuo sa loob ng maraming taon sa halip na biglang dumating nang sabay-sabay. Ang sakit ay may tendensiyang pabalik-balik: sumisidhi ito pagkatapos mong gamitin ang iyong hinlalaki, humuhupa sa pamamagitan ng pahinga, at pagkatapos ay bumabalik sa susunod na pagkakataong ikaw ay mag-pinch o mag-grip. Kung pababayaan, karaniwang lumalala ang panghihina at pagka-asiwa sa mga pang-araw-araw na gawain, dahil patuloy na sinasalo ng pudpod na joint ang parehong load araw-araw.
Karamihan sa mga taong mahusay na namamahala nito ay nakakakuha ng tunay na ginhawa. Ang pagbabawas sa mga gawaing nagbibigay ng load sa base ng hinlalaki, ang pagsusuot ng splint, at ang hand therapy ay pawang nagpapakalma sa mga sintomas para sa maraming tao, lalo na sa mga unang yugto. Ang isang injection ay maaaring magpakalma ng masakit na flare sa maikling panahon, bagaman karaniwang hindi nagtatagal ang ginhawa. Kung hindi sapat ang mga hakbang na iyon, layunin ng operasyon na alisin ang sakit at mapanatiling gumagalaw ang iyong hinlalaki. Nangangailangan ng panahon ang paggaling mula sa operasyon sa base ng hinlalaki: kakailanganin mong lumiban sa trabaho, mas matagal kung ang iyong trabaho ay nangangailangan ng mabigat na paggamit ng iyong mga kamay, at gugugol ka ng ilang linggo na nakapahinga ang iyong kamay habang humihilom ito. Ang hand therapy pagkatapos, kasama si Ruby Doolan sa Extend Rehabilitation, ang gagabay sa kung kailan at gaano kabigat ang maaari mong buhatin habang muling bumabalik sa paggana ang iyong hinlalaki.
Ang operasyon ay hindi pangako ng hinlalaking walang sakit. Karamihan sa mga tao ay may mas kaunting sakit at mas mahusay na paggamit ng kanilang kamay, ngunit maaaring manatili ang ilang sintomas. Ang maliit na bilang ng mga tao ay nangangailangan ng isa pang operasyon sa kalaunan, maaaring dahil napupudpod muli ang joint o dahil nagkakaproblema ang isang implant. Kung mangyari iyon, makatutulong pa rin ang ikalawang operasyon: karamihan sa mga taong sumailalim dito ay nagsasabing mas mabuti ang kanilang hinlalaki kaysa bago ang kanilang unang operasyon, bagaman ang resulta ay karaniwang hindi kasinghusay ng unang operasyon. Ang paglalayo ng mabibigat na load sa iyong hinlalaki pagkatapos ng operasyon ay nakatutulong upang tumagal ang naayos na bahagi.
Kung ang iyong kamay ay naging mainit, mapula, namamaga at masakit, lalo na kung may lagnat, pumunta sa emergency department sa araw ding iyon. Hindi kailangan ng referral mula sa GP.
Kailan dapat magpatingin
Magpatingin sa iyong GP o humingi ng specialist review kung ang sakit sa base ng iyong hinlalaki ay hindi humuhupa, lumalala sa loob ng ilang linggo, ginigising ka sa gabi, o pumipigil sa iyong pagtatrabaho o paggamit ng iyong kamay. Magpatingin nang mas maaga kung ang pag-pinch at pag-grip ay naging mahina o hindi maaasahan, o kung ang pagpihit ng susi at pagbubukas ng garapon ay lalong humihirap sa kabila ng pahinga at splint.
Ang ilang babalang palatandaan ay nangangailangan ng pangangalaga sa araw ding iyon. Pumunta sa emergency department kung ang iyong kamay ay naging mainit, mapula, namamaga at masakit, lalo na kung may lagnat. Maaaring ito ay isang impeksyon, at kailangan itong gamutin kaagad. Hindi kailangan ng referral mula sa GP.
Pumunta rin sa emergency department kung ang iyong mga daliri o kamay ay namutla, lumamig, pumuti o naging kulay asul, o kung bigla kang nawalan ng pakiramdam o paggalaw sa iyong kamay pagkatapos ng isang pinsala.
Kung hindi mo maabot ang klinika, sa labas ng oras ng opisina o sa katapusan ng linggo, pumunta sa pinakamalapit na emergency department.
Higit pang detalye
Advanced reading: the deeper science (optional)
Ang seksyong ito ay lumalampas sa kailangan mo para sa iyong sariling mga desisyon sa paggamot. Ang arthritis sa base ng hinlalaki ay karapat-dapat sa karagdagang pagbabasa dahil ito ang kondisyon sa upper-limb kung saan pinakamalawak ang agwat sa pagitan ng kung ano ang unang inaalok sa mga pasyente at kung ano ang sinusuportahan ng ebidensya, at dahil ang mga opsyong pang-operasyon ay hindi kailanman nagkaroon ng malinaw na pagkakaiba sa isa't isa sa kabila ng ilang dekada ng pagsubok.
Ang ebidensya para sa non-operative ay mas mabuti kaysa sa reputasyon nito
Ang mga splint at hand therapy ay madalas na ipinapakita bilang mga bagay na ginagawa habang naghihintay para sa operasyon. Isang systematic review at network meta-analysis ng 1,962 na pasyente ang naglalagay sa mga ito sa mas matibay na batayan: ang multimodal treatment at hand exercises ay nagpababa ng short-term pain at nagpahusay sa grip strength, habang ang isang rigid CMC-MCP splint, isang uri na humaharang sa joint sa itaas pati na rin sa base ng thumb — ay nagpahusay sa medium-term outcomes [1].
Dalawang detalye ang mahalaga. Ang splint na gumana ay tumatawid sa parehong joints, na hindi ang soft neoprene sleeve na karaniwang ibinibigay sa karamihan ng mga tao. At ang ehersisyo ay nagpahusay sa grip strength, hindi lamang sa comfort; ito ay isang joint na ang pagkasira ay mechanical, at ang pagpapalakas ng mga kalamnan na nag-compress at nag-stabilize dito ay ang paggamot sa mekanismo.
Ang injection ay nagbibigay ng ilang linggo, hindi buwan
Ang corticosteroid injection ang karaniwang susunod na hakbang. Sa pagsasama-sama ng 673 na pasyente, ang intra-articular corticosteroid injection ay nagdulot ng panandaliang pagbuti ngunit walang makabuluhang pagkakaiba sa sakit at functional outcomes sa mga sumunod na follow-up [2].
Nararapat itong marinig nang malinaw. Ang injection dito ay isang paraan upang makaraos sa isang itinakdang panahon — isang biyahe, isang deadline, isang abalang yugto sa trabaho, o upang kumpirmahin na ang joint ang pinagmumulan ng sakit. Hindi ito isang gamutan na nagbabago sa trajectory, at ang mga paulit-ulit na injection para sa isang permanenteng resulta ay paghahabol sa isang bagay na hindi ipinapakita ng ebidensya.
Walang operasyon ang nanalo
Kapag ang operasyon ay nasa mesa na, mayroong ilang kapani-paniwalang opsyon, at ang kapansin-pansing bagay ay kung gaano pagkakapareho ng kanilang mga resulta.
Arthrodesis, ang pag-fuse ng joint, ay nagbubunga ng mabuting functional outcomes na may mababa hanggang katamtamang pain at disability scores, sa kapalit ng isang makabuluhang nonunion rate [3]. Ipinagpapalit nito ang paggalaw para sa tibay, na angkop para sa kamay na ginagamit sa mabigat na manual labor at hindi angkop para sa isang piyanista.
Dual-mobility trapeziometacarpal arthroplasty, ang pagpapalit ng joint, ay nagpakita ng mga pagpapabuti sa lakas, range of motion, sakit, function at kasiyahan sa 1,421 na mga pasyente, na may 13% complication rate at 0.6% dislocation risk [4]. Ang mga numerong ito ay kagalang-galang, at sila rin ang dahilan kung bakit ang mga implant ay nananatiling isang pinag-iisipang pagpipilian sa halip na ang default: ang 13% ay hindi maliit, at ang follow-up sa literaturang ito ay maikli kumpara sa kung gaano katagal dapat tumagal ang isang thumb.
Ang tapat na buod ay ang pagpipilian ay nakadepende sa kung ano ang kailangang gawin ng iyong kamay, at kung aling failure mode ang mas gusto mong isapalaran, isang joint na hindi nababaluktot, o isang implant na maaaring kailangang balikan.
Bakit madalas na ang hinlalaki ang unang kasukasuan na nasisira
Ang trapeziometacarpal joint ay isang saddle joint na binuo para sa isang hindi pangkaraniwang kombinasyon ng mobility at load. Ang bawat pinch ay lumilikha ng puwersa sa base ng hinlalaki na maraming beses na mas malakas kaysa sa puwersa sa dulo ng daliri, dahil sa lever arm. Iyan ang kapalit ng opposability: ang kasukasuan na nagpapagamit sa kamay ng tao ay mas mabigat ang load, at mas madalas, kaysa sa anumang iba pang maliit na kasukasuan sa katawan, kung kaya't ito ang unang napupudpod, at kung bakit ang pagpapalakas sa mga sumusuporta rito ay hindi isang mababaw na hakbang.
Mga Sanggunian
[1] Thakker A, Ramchandani JP, Divall P, Sutton A, Johnson N, Dias J. Ano ang mga pinaka-clinically effective na nonoperative intervention para sa thumb carpometacarpal osteoarthritis? Isang systematic review at network meta-analysis. Clin Orthop Relat Res. 2024;483(4):719-36. https://doi.org/10.1097/CORR.0000000000003300
[2] Krez AN, Wu KA, Klifto KM, Pidgeon TS, Klifto CS, Ruch DS. Efficacy ng intra-articular corticosteroid injection para sa nonsurgical management ng thumb carpometacarpal osteoarthritis: isang systematic review. J Hand Surg Am. 2024;49(6):511-25. https://doi.org/10.1016/j.jhsa.2024.02.001
[3] Dharamsi MS, Caudle K, Fares A, Dunn J. Arthrodesis para sa carpometacarpal joint arthritis: isang systematic review. Hand (N Y). 2022;18(8):1284-90. https://doi.org/10.1177/15589447221105541
[4] Maling L, Rooney A. Mga outcome ng dual-mobility trapeziometacarpal arthroplasties: isang systematic review. J Hand Surg Eur Vol. 2024;50(5):587-95. https://doi.org/10.1177/17531934241292249
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Basal thumb arthritis is a common condition where a comprehensive history and clinical examination are sufficient for diagnosis [2].
- The purpose of providing an anatomic and scientific basis is to support the rational management of patients with arthritis of the thumb basal joint complex [1].
- An anatomically based radiological classification aims to differentiate between different forms of thumb basal joint arthritis to allow prospective studies to assess results [5].
- The CMC joint defines the workspace of the thumb in all three dimensions [15].
- The MCP joint acts as a force transmitter and is the linked bar to the IP joint [15].
- The IP joint provides fine motor skills and must be stable enough to interact with the index and middle finger in pinching [15].
- Active mobility of the IP joint is strongly correlated with hand function [15].
- Thumb deformities have a negative impact on grasp and pinch function [15].
- Nalebuff and colleagues classified thumb deformities based on joint involvement and deformity pattern [15].
- Six distinguished types of thumb deformities are described, with various disease stages categorized for more common types [15].
- Osteoarthritis is likely to remain the most common indication for basal joint arthroscopy [21].
- Chronic pain and inflammation are useful indications for metacarpophalangeal arthroscopy [21].
- The interest of arthroscopy in the surgical treatment of thumb carpometacarpal arthritis remains to be demonstrated in the absence of series with sufficient level of evidence [165].
- Arthroscopic total trapeziectomy appears to be a safe and effective treatment for end-stage arthrosis of the thumb basal joint [66].
- The presented treatment approach of denervation, joint lavage, and capsular imbrication could be a good alternative to more invasive surgical options in patients with earlier stages of thumb carpometacarpal joint osteoarthritis [64].
- The treatment approach of denervation, joint lavage, and capsular imbrication has advantages including a low rate of complications, low invasiveness, and short recovery times [64].
- Thumb carpometacarpal joint denervation is not recommended in cases of advanced thumb CMC disease or for de novo scaphotrapeziotrapezoidal (STT) arthritis [75].
- Long-term clinical outcomes of trapeziectomy for basal thumb arthritis are very positive [3].
- Interpositioning as an isolated procedure appears to be the preferred treatment for basal thumb arthritis despite greater radiological degradation when compared to suspensionplasty [3].
- Removal of the trapezium as treatment for basal thumb osteoarthritis does not increase the risk of developing wrist osteoarthritis in the long term [4].
- Total trapeziectomy is currently the only surgical technique for thumb basal joint arthritis that can lay claim to being a potential life-long procedure [11].
- Total trapeziectomy does not require an implant and provides long-lasting benefits [11].
- Health state utility gains are demonstrated after basal thumb osteoarthritis surgery regardless of the surgical techniques used [10].
- TMC arthroplasty (simple or dual mobility) is a reliable option in thumb basal joint arthritis with an implant survival rate of 90% at 10 years of follow-up [50].
- TMC arthroplasty provides pain relief and restores strength and mobility [50].
- Pyrocarbon implants are used for the surgical treatment of basal thumb arthritis [25].
- The RegJoint™ implant is considered a useful adjunct in the management of a select cohort of patients with base of thumb arthritis [26].
- The Artelon CMC Spacer is no longer used for the management of basal joint arthritis of the thumb due to an unacceptably high complication rate [30].
- The porous polyurethaneurea (Artelon) joint spacer has been abandoned for the treatment of basilar thumb osteoarthritis [49].
- The authors advocate a specific procedure for basal thumb arthritis in men [6].
- A new technique of first carpometacarpal joint suspension arthroplasty with palmaris longus tendon graft adds an additional option for complicated cases of thumb base arthritis [7].
- Indications for the first carpometacarpal joint suspension arthroplasty with palmaris longus tendon graft are limited [7].
- A new technique for the correction of thumb metacarpophalangeal joint hyperextension is presented for patients with concomitant basal thumb osteoarthritis [24].
- Partial trapezial resection with local capsular interposition arthroplasty utilizes remaining local tissue as an interposition without ligament reconstruction [160].
- Partial trapezial resection with local capsular interposition arthroplasty eliminates the need for tendon harvest and the morbidity associated with the harvest [160].
- The Swanson silastic interposition arthroplasty provides good medium-term results and high satisfaction rates in revision thumb-base surgery for failed trapeziectomy [22].
- The Swanson silastic interposition arthroplasty is advocated as an effective treatment option for revision thumb-base surgery provided other treatable causes of poor outcome are excluded [22].
- 1-year postoperative outcomes are similar for tendon arthroplasty and total joint replacement [44].
- It is crucial to delve into the comparative efficacy, long-term outcomes, and potential complications associated with tendon arthroplasty and total joint replacement given the complexity of thumb arthritis and diversity of patients' needs [44].
- The most common complications after surgery for basal thumb arthritis include those associated with resection arthroplasty, joint replacement, and joint fusion [8].
Anatomy & Pathophysiology
Joint Anatomy & Biomechanics
- The thumb carpometacarpal (CMC) joint is a biconcave, reciprocating saddle joint with little inherent stability [144].
- The thumb CMC joint has two longitudinal axes and two degrees of freedom, functioning similarly to a universal joint [35].
- The distal articular surface of the trapezium is asymmetrical, with a longitudinal crest and transverse groove that are curved [35].
- The articular surfaces of the trapeziometacarpal joint are asymmetrical, creating an "open joint" configuration [35].
- The thumb metacarpal is 34% smaller in diameter than the distal articular surface of the trapezium [144].
- There are 16 surrounding ligaments that impart stability to the thumb CMC joint [144].
- The deep anterior oblique ligament, also known as the palmar "beak" ligament, is the primary stabilizer of the thumb CMC joint [144].
- The deep anterior oblique ligament is an intracapsular ligament emanating from the volar tubercle of the trapezium and inserting on the ulnar volar aspect of the first metacarpal [144].
- The deep anterior oblique ligament tightens with pronation, abduction, and extension, preventing ulnar and dorsal translation of the first metacarpal [144].
- The dorsoradial ligament and posterior oblique ligament stabilize the joint and inhibit dorsal and ulnar translation, respectively [144].
- The dorsal intermetacarpal ligament prevents radial translation of the thumb metacarpal and proximal migration following trapeziectomy [144].
- The radial side of the thumb CMC joint has a much weaker ligament than the ulnar side, creating intrinsic instability at the site of high pressure [35].
- Stability of the thumb CMC joint is dynamically provided by the abductor pollicis longus tendon only when the first metacarpal is abducted [35].
- In adduction, the abductor pollicis longus increases the risk of subluxation of the thumb CMC joint [35].
- Joint compression forces during simple pinch averaged 12.0 kg at the carpometacarpal joint [35].
- Compression forces of up to 120 kg may occur at the carpometacarpal joint during strong grasp [35].
- High compressive forces across the thumb CMC during pinch may reach in excess of 12 times the applied load and approach 20 times the applied load during maximum grasp [144].
- Cantilever bending occurs with applied forces, creating shear forces that are highest at the volar half of the joint’s articular surface [144].
- Flexion of the thumb metacarpophalangeal (MCP) joint produces unloading of the volar portion of the trapezial metacarpal joint [144].
- The observed compressive load at the trapeziometacarpal joint in a biomechanical model ranged from 8 to 16 times the thumb-fingertip pressure [80].
- In palmar abduction, 28% of the trapezium was in contact with 28% of the metacarpal [124].
- In radial abduction, 25% of the trapezium was in contact with 25% of the metacarpal [124].
- During thumb oppositional motion, internal rotation of the first metacarpal occurred, with the palmar base rotating primarily with respect to the dorsal base [117].
- The higher the thumb mobility, the more the trapezium tilts under load [104].
Ligament Pathology & Innervation
- Ultrastructural analysis of the deep anterior oblique ligament in patients with osteoarthritis found disorganized connective tissue with little evidence of collagen fibers and few signs of innervation [144].
- Mechanoreceptors were identified in the dorsoradial ligament, which was innervated to a much greater extent than the anterior oblique ligament [144].
- The collagen bundles of the dorsoradial ligament were found to be better organized than those of the anterior oblique ligament [144].
- No association was noted between ligament innervation patterns and patient age in patients with osteoarthritis [144].
- Changes in the type and distribution of mechanoreceptors were found among symptomatic patients with degenerative arthritis of the CMC joint [144].
- The beak ligament was essential for translational stability of the metacarpal on the trapezium with flexion of the thumb ray [201].
- There was a direct correlation between the status of the articular surfaces and the integrity of the beak ligament [201].
- Normal articular surfaces were associated with an intact beak ligament confluent with the hyaline cartilage of the palmar lip of the metacarpal [201].
- Degeneration of the palmar lip cartilage was always associated with attritional detachment of the beak ligament [201].
- Advanced articular disease occurred only in the palmar contact areas and was predicted by degeneration of the adjacent beak ligament [201].
- Only nonprogressive chondromalacia was found on the dorsal portions of the articular surfaces [201].
Etiology & Risk Factors
- The pathophysiology of basal thumb joint arthritis includes both intrinsic and extrinsic factors [9].
- The prevalence of thumb CMC arthritis increases with age, rising from 6.6% in individuals aged 40 to 49 years to 36.4% in individuals aged 80 years [9].
- With the exception of the youngest age group, women uniformly had a higher prevalence of thumb CMC arthritis than men [9].
- Female sex is a risk factor for the development of thumb CMC osteoarthritis, with up to a sixfold increased incidence compared with men [9].
- The increased incidence in women may be associated with an increased risk of ligamentous laxity [9].
- Thumb CMC morphology has been shown to be similar between men and women after controlling for size, implying that physiology rather than anatomy is the predominant risk factor [9].
- The relaxin hormone, which increases laxity in pelvic ligaments, may play a role in ligamentous laxity through a matrix metalloproteinase pathway [9].
- Degeneration associated with relaxin may play a role in the development of CMC arthritis, especially in women [9].
- Hormones such as prolactin and estrogen have been implicated in the pathophysiology of thumb CMC arthritis [9].
- Patients with generalized ligamentous laxity, such as Ehlers-Danlos syndrome, have a considerably higher incidence of thumb CMC arthritis [9].
- Patients with generalized ligamentous laxity begin to exhibit radiographic changes at a younger age than counterparts without generalized ligamentous laxity [9].
- A higher Beighton score is positively associated with increased mobility of the CMC joint [9].
- There is a strong association between excessive basal joint laxity and the development of premature degenerative changes [14].
- There is no longitudinal natural history study that has established a clear etiology for basal joint disease [14].
- The condition appears most consistently associated with increased ligamentous laxity about the CMC joint of the thumb, allowing varying degrees of subluxation and incongruous articulation [205].
- An average 10:1 sexual predilection for the postmenopausal woman is widely recognized for basal joint arthrosis [205].
- Radiographic evidence of marked osteoarthritis of the CMC joint was found in more than 20% of nearly 100 asymptomatic women over 40 years of age [205].
- In a similar population of men, only one individual was affected, and he had a history of previous Bennett's fracture [205].
- Primary osteoarthrosis is rare in men, and a history of previous fracture is frequent in the few men reported in series of surgical treatment [205].
- Altered thumb rotation patterns during pinch may contribute to joint misalignment and the development of osteoarthritis [136].
- Carpometacarpal and metacarpophalangeal joint collapse is associated with increased pain but not functional impairment in persons with thumb carpometacarpal osteoarthritis [140].
Articular Degeneration Patterns
- Pellegrini showed an association with degeneration of the volar half of the thumb CMC joint as the integrity of the deep anterior oblique ligament diminishes [144].
- The dorsal cartilage is relatively spared, even in cases of advanced osteoarthritis [144].
- Articular degeneration consistently involved a greater portion of the surface area of the trapezium compared with the metacarpal by a ratio of 3:1 [144].
- A decrease in the ratio of trapezial to metacarpal degeneration was associated with more advanced disease [144].
- Joint contact patterns shift dorsally and are more diffuse with progressive trapeziometacarpal disease [80].
- The first sign of degenerative change in thumb metacarpophalangeal arthritis is synovitis [197].
- Synovitis manifests clinically as pain, swelling, and weakness of grasp [197].
Radiographic Staging
- Eaton and colleagues described a widely accepted radiographic staging system for thumb CMC joint degenerative arthritis [16].
- Stage I is defined as normal or slight widening of the joint shadow due to synovitis [16].
- Stage II is defined as mild joint shadow narrowing with osteophyte formation of 2 mm or less [16].
- Stage III is defined as marked joint shadow narrowing with osteophyte formation of more than 2 mm [16].
- Stage IV is defined as Stage III disease with scaphotrapeziotrapezoidal (STT) osteoarthritis [16].
Classification
Radiographic Staging Systems
- The Eaton classification of basal joint arthritis demonstrates moderate reliability, with overall mean intrarater and interrater reliabilities of .657 and .529, respectively [135].
- A systematic review of the literature indicates that while radiographs assist in assessing CMC joint disease, there is not a reliable system for classifying disease severity [40].
- The reliability of the Eaton classification is improved when the combination of PA–lateral and Bett’s views are used in radiographic evaluation compared to using posterior–anterior and lateral views or the Bett’s view alone [34].
- The radiological classification of carpometacarpal joint osteoarthritis does not describe all stages accurately enough to permit reliable and consistent communication between clinicians [73].
- An anatomically based radiological classification has been proposed to differentiate between different forms of thumb basal joint arthritis to allow prospective studies to assess results [5].
- Dell's X-ray classification for trapeziometacarpal arthritis defines Stage 1 as a normal X-ray picture or slight narrowing of the joint space at the ulnar side or subchondral sclerosis [27].
- Dell's X-ray classification defines Stage 2 as narrowing of the joint space, increased density of the subchondral bone, subluxation of the trapeziometacarpal joint limited to less than one-third of its base, and early osteophytosis of the trapezium and the base of the second metacarpal [27].
- Dell's X-ray classification defines Stage 3 as a prominent osteophyte at the ulnar border of the distal trapezium, marked narrowing of the joint space, subluxation of the first metacarpal by one-third of the width of its base, sclerosis of the subchondral bone, geodes, osteophytosis, and early peritrapezial arthritis [27].
- Dell's X-ray classification defines Stage 4 as total loss of joint space, a prominent ulnar osteophyte, subluxation of the metacarpal base, frequently osteoarthritic subchondral cysts, and significant peritrapezial arthritis [27].
- The Eaton and Littler classification defines Stage I as preceding any cartilage degeneration with normal articular contours, where the joint space may be widened if an effusion is present [83].
- The Eaton and Littler classification defines Stage II as slight narrowing of the thumb metacarpal-trapezium joint space with maintained articular contours [83].
- The Eaton and Littler classification defines Stage III as disease limited to the trapeziometacarpal joint with sparing of the scaphotrapezial joint [79].
- The Eaton and Littler classification defines Stage IV as involvement of both the trapeziometacarpal and scaphotrapezial joints [79].
- A modification to the Eaton and Littler classification includes an additional category called Stage III +, characterized by moderate degenerative changes in the scaphotrapezial joint with some joint space narrowing, mild subchondral sclerosis, and minimal osteophyte formation [79].
- Roentgenographic evaluation of basal joint arthritis tends to overdiagnose the extent of disease because elongation of the common osteophyte on the palmar horn of the thumb metacarpal facet of the trapezium frequently projects across the index metacarpal facet [86].
- In cadaver studies correlating roentgenographic with anatomic findings, the index and trapezoid facets are rarely involved (1%) in cases where the CMC facet of the thumb is arthritic [86].
- In cadaver studies, the scaphotrapezial facets are involved in 46% of specimens in which the CMC facet of the thumb is arthritic [86].
- The metacarpal surface of the trapezium demonstrates three distinct patterns of wear in arthritic surgical specimens [76].
- Subjects presenting with early CMC OA have significantly lower bone density as assessed with Hounsfield units at the thumb CMC joint (trapezium and first metacarpal base) [12].
- The prevalence of midcarpal arthritis in patients with basal joint arthritis is 24% [13].
Arthroscopic Staging Systems
- A proposed arthroscopic classification for basal joint osteoarthritis provides additional clinical information and can direct further treatment depending on the stage of disease [157].
- Arthroscopic assessment of the first carpometacarpal joint allows for the identification and classification of joint pathology with minimal morbidity [170].
- An arthroscopic staging system has been described to determine treatment for basal joint osteoarthritis [170].
Anatomical and Biomechanical Classification
- A system for staging CMC-OA degeneration grades cartilage lesions based on location and degree, dividing the trapezium and metacarpal into six anatomical areas (dorsoradial, voloradial, dorsoulnar, and voloulnar trapezial; volar and dorsal metacarpal) [121].
- The degree of cartilage lesion in CMC-OA staging is graded on a five-point scale based on the observations of specific common types of cartilage lesions [121].
- An overall joint grade in CMC-OA staging is assigned to each specimen on the basis of the highest site-specific grade for that joint [121].
- The authors suggest that ulnar instability should be included in the classification of thumb CMC joint osteoarthritis stages and considered in treatment options [164].
Clinical Presentation
Epidemiology and Risk Factors
- The prevalence of thumb carpometacarpal (CMC) arthritis increases with age, rising from 6.6% in individuals aged 40 to 49 years to 36.4% in individuals aged 80 years [9].
- Women have a uniformly higher prevalence of thumb CMC arthritis than men, with the exception of the youngest age group [9].
- Female sex is a risk factor for thumb CMC osteoarthritis, associated with up to a sixfold increased incidence compared with men [9].
- Thumb CMC morphology is similar between men and women after controlling for size, implying that physiology rather than anatomy is the predominant risk factor [9].
- Patients with generalized ligamentous laxity, such as Ehlers-Danlos syndrome, have a considerably higher incidence of thumb CMC arthritis and exhibit radiographic changes at a younger age [9].
- Occupations involving repetitive thumb use and heavy manual labor are associated with an increased risk of thumb CMC arthritis [9].
- Basal joint osteoarthritis is not common in Asia, where radiocapitellar and radioulnar osteoarthritis are more common conditions [72].
Clinical Examination
- A comprehensive history and clinical examination are sufficient for the diagnosis of basal thumb arthritis [2].
- Patients with osteoarthritis of the thumb CMC joint may present with pain localized to the area or vague complaints of throbbing or burning in the radial aspect of the hand [190].
- Advanced osteoarthritis often displays a thumb adduction contracture and a compensatory thumb metacarpophalangeal (MCP) joint hyperextension deformity [190].
- Examination of the thumb MCP joint in patients with advanced CMC osteoarthritis shows laxity of the joint in hyperextension [190].
- The CMC grind test involves stabilizing the wrist and applying axial loading to the thumb axis to elicit pain or crepitus [190].
- The CMC subluxation test, or lever test, involves gently forcing the CMC joint to sublux to assess for a pain response or crepitus [190].
- Pinch strength testing, such as the two-point key pinch test or three-point pinch, is part of the physical examination for thumb CMC osteoarthritis [190].
- Thumb metacarpophalangeal instability is commonly found in conjunction with trapeziometacarpal osteoarthritis [70].
- A reduction in cylindrical grasp strength is associated with early symptomatic and radiographic CMC osteoarthritis, whereas gross grasp is not associated with early disease [41].
- Clinical involvement of the thumb basal joint in patients with established hand osteoarthritis is associated with a higher clinical burden [63].
- The high prevalence of other symptomatic disorders of the hand requires a complete and standardized clinical examination to consider them during surgical planning [112].
Radiographic Assessment
- Radiographs to profile the thumb CMC joint include PA, lateral, and oblique views of the hand or PA and lateral views of the wrist [16].
- The Robert view is a true PA view of the thumb CMC joint that requires shoulder flexion, internal rotation, and wrist hyperpronation [16].
- Advanced imaging studies such as MRI or CT scanning are seldom necessary for operative procedures or surgical decision making about the thumb CMC joint [16].
- The Eaton classification stages thumb CMC joint degenerative arthritis from Stage I (normal or slight widening) to Stage IV (Stage III disease with scaphotrapeziotrapezoidal osteoarthritis) [16].
- The reliability of the Eaton classification is better when the combination of PA–lateral and Bett’s views are used compared to using posterior–anterior and lateral views or the Bett’s view alone [34].
- A systematic review demonstrates that radiographs assist in the assessment of CMC joint disease, but there is not a reliable system for classification of disease severity [40].
- The anatomically based radiological classification proposed for thumb basal joint arthritis aims to differentiate between different forms to allow prospective study assessment [5].
- Subjects presenting with early CMC osteoarthritis had significantly lower bone density as assessed with Hounsfield units at the thumb CMC joint [12].
- Scaphotrapeziotrapezoid osteoarthritis is common and often associated with thumb basal joint arthritis, characterized by pain at the base of the thumb on the volar aspect and during resisted extension [118].
- Radiographic involvement of the thumb basal joint in patients with established hand osteoarthritis is associated with older age and more structural abnormalities [63].
Associated Pathologies
- Trapeziometacarpal osteoarthritis is frequently associated with other disorders of the hand that must be considered during surgical planning [112].
- Scaphotrapeziotrapezoid osteoarthritis is characterized by pain at the base of the thumb on the volar aspect and during resisted extension [118].
- Midcarpal arthritis is present in 24% of patients with basal joint arthritis [13].
Investigations
Clinical Diagnosis
- A reduction in cylindrical grasp strength is associated with early symptomatic and radiographic carpometacarpal osteoarthritis, whereas gross grasp is not associated with early thumb carpometacarpal osteoarthritis [41].
- A negative grind test does not necessarily reflect negative radiographic evidence of thumb carpometacarpal osteoarthritis [209].
Radiographic Imaging
- Radiographs to profile the thumb carpometacarpal joint include PA, lateral, and oblique views of the hand or, alternatively, PA and lateral views of the wrist [16].
- The Robert view is a true PA view of the thumb carpometacarpal joint that requires special positioning including shoulder flexion, shoulder internal rotation, and wrist hyperpronation [16].
- Advanced imaging studies such as MRI or CT scanning are seldom necessary for operative procedures or surgical decision making about the thumb carpometacarpal joint [16].
- The reliability of the Eaton classification is better when the combination of PA–lateral and Bett’s views are used in the radiographic evaluation of basal arthritis of the thumb compared to using the posterior–anterior and lateral views or the Bett’s view alone [34].
- Wrist radiographs demonstrate a 47% sensitivity and 94% specificity in predicting end-stage scaphotrapezoid joint arthritis [191].
- The M1/M2 ratio can be easily measured for radiological follow-up of trapeziometacarpal surgery and is independent of radiographic conditions [198].
- Radiographic development of trapeziometacarpal arthrosis is an expected part of human aging, although clinically significant, functionally limiting trapeziometacarpal arthrosis is less common [196].
- In patients with established hand osteoarthritis, radiological involvement of the thumb basal joint is associated with older age and more structural abnormalities [63].
Radiographic Classification
- The Eaton classification stages thumb carpometacarpal joint degenerative arthritis as Stage I (normal or slight widening of the joint shadow due to synovitis), Stage II (mild joint shadow narrowing with osteophyte formation of 2 mm or less), Stage III (marked joint shadow narrowing with osteophyte formation of more than 2 mm), and Stage IV (Stage III disease with scaphotrapeziotrapezoidal osteoarthritis) [16].
- A systematic review of the literature demonstrates that radiographs assist in the assessment of carpometacarpal joint disease, but there is not a reliable system for classification of disease severity [40].
- The radiological classification does not describe all stages of carpometacarpal joint osteoarthritis accurately enough to permit reliable and consistent communication between clinicians [73].
- An anatomically based radiological classification aims to differentiate between the different forms of thumb basal joint arthritis so as to allow a prospective study to assess the results [5].
Advanced Imaging
- Musculoskeletal ultrasound power Doppler has a significant relationship with pain severity in thumb base osteoarthritis, suggesting it might be a useful tool in understanding pain aetiology [65].
- Subjects presenting with early carpometacarpal osteoarthritis had significantly lower bone density as assessed with Hounsfield units at the thumb carpometacarpal joint (trapezium and first metacarpal base) [12].
- Pigmented villonodular synovitis can cause bicortical erosion in the thumb, which was not obvious on plain radiographs but appreciated on MRI [208].
- The significantly greater trabecular bone volume, thickness, and connectivity in the volar-ulnar quadrant compared with the dorsal-radial and dorsal-ulnar quadrants provides evidence that the greatest compressive loads at the first carpometacarpal joint occur at the volar-ulnar quadrant of the trapezium [206].
Treatment
Non-Operative Management
- Nonoperative treatment is the first phase of management for patients with osteoarthritis of the thumb CMC joint [23].
- Thumb spica splinting is a component of nonoperative treatment, preferably leaving the thumb IP joint free for patient comfort [23].
- NSAIDs may be used orally or topically as part of nonoperative treatment depending on patient tolerance or physician preference [23].
- Outpatient hand therapy may consist of ultrasound, paraffin wax, heat, and deep tissue massage, along with activity modifications [23].
- Sustained benefit from splinting and corticosteroid injections has been demonstrated by several authors [23].
- A randomized controlled, blinded trial showed no difference in scores on the visual analog pain scale at 24 weeks when comparing a group treated with a thumb CMC joint steroid injection and another group treated with saline injection [23].
- Non-surgical treatments of the carpometacarpal (CMC) arthritis of the thumb provide adequate pain relief for the majority of patients, particularly in the early stages of disease [110].
- The European League Against Rheumatism (EULAR) 2018 treatment guidelines recommend surgery for thumb CMC arthritis only if pain persists following non-pharmacologic treatment [110].
- The American College of Rheumatology strongly recommends splinting but does not mention the role of surgical management in its guidelines [110].
- Various studies have demonstrated that non-surgical treatments, such as hand therapy and splinting, can delay or obviate the need for surgical management [110].
- Although steroid intra-articular injections are commonly used for osteoarthritis, this intervention would not be more effective than saline injections for TMO according to scientific evidence of moderate quality [128].
- The efficacy for pain reduction and/or improvement of physical function of saline injections in tender subcutaneous areas, custom-made thermoplastic thumb, custom-made thermoplastic hand-based trapeziometacarpal (TM) joint orthosis, radial nerve mobilization and a combination of hand exercises, TM-joint/nerve mobilization is supported by scientific evidence of low quality which is still the best available evidence [128].
- Degenerative arthritis of the thumb CMC joint is a common treatable condition where nonoperative modalities are effective for early stages, while surgical options are reserved for cases refractory to conservative measures [158].
- The use of anti-inflammatories, splinting, and corticosteroid injections serve only as palliative measures, with none of them altering joint mechanics or affecting the articular surface itself in any manner [20].
- The use of injectable steroids can accelerate cartilage loss and worsen capsular attenuation [20].
Surgical Indications and Timing
- Surgery is presently the mainstay of treatment for severely symptomatic osteoarthritis [113].
- The present indication for surgical treatment is generally described as ‘troublesome painful osteoarthritis which restricts thumb and hand function and has not been adequately managed with non-operative treatments’ [113].
- One study reported that 68% of patients referred for consideration of surgery did not undergo surgery during the following 2 years [113].
- It is sensible to delay surgery for at least 3–6 months after the onset of intolerable pain, or even longer, to see if the restrictive pain is due to a temporary flare up of the osteoarthritis that will settle spontaneously or with non-operative treatment [113].
- Prior to surgery, all patients in a specific cohort had had appropriate non-operative treatment for at least six months including one or more of the following: activity modification, splinting, nonsteroidal anti-inflammatory drugs, or steroid injections [129].
- The SCOOTT trial is a multicentre, three-arm randomized controlled trial designed to determine the clinical and cost-effectiveness of treating basal osteoarthritis of the thumb with or without surgery, and to compare trapeziectomy versus thumb CMCJA [115].
Early Stage Surgical Procedures
- A 30-degree closing wedge, extension osteotomy of the thumb metacarpal has been theorized to unload the volar segment of the thumb CMC joint by redistributing the load through the more dorsal segment of the joint [23].
- The first metacarpal osteotomy is indicated for patients with stage I or II disease but contraindicated in patients with hypermobility, fixed subluxation, or hyperextension of the joint [23].
- In 1999, Tomaino et al. reported on 12 patients with stage I disease treated with extension osteotomy of the thumb metacarpal, where all osteotomies healed within 7 weeks; 11 of the 12 were satisfied with the outcome, and all had increased grip and pinch strength at 2 years of follow-up [23].
- For patients with stage I or II disease of the thumb CMC joint, ligament reconstruction alone may be preferred over other salvage techniques [23].
- Instability of the volar ligamentous complex of the joint, particularly the deep anterior oblique ligament, has been proposed as the potential cause of osteoarthritis of the joint [23].
- In a biomechanical study, Koff and coworkers have shown that ligament reconstruction improved stability of the joint [23].
- Ligament reconstruction has been typically reserved for patients with very mild articular changes and is contraindicated in patients with stages III and IV disease [23].
- This laboratory investigation suggests that there is a sound biomechanical basis for the application of extension metacarpal osteotomy to unload the palmar compartment of the pre-arthritic and early arthritic trapeziometacarpal joint [80].
- Improvement in symptoms following osteotomy in the joint with endstage arthritis may still occur by virtue of a poorly understood biologic mechanism, but would not appear to be related to mechanical joint-surface load redistribution on the basis of the osteotomy [80].
- The findings indicate that denervation, joint lavage and capsular imbrication could be a good alternative to more invasive surgical options in patients with earlier stages of thumb carpometacarpal joint osteoarthritis, with advantages including a low rate of complications, low invasiveness, and short recovery times [64].
- Selective denervation of the TMC joint aims to provide pain relief without compromising the thumb’s strength and mobility, especially when the patient’s job requires active pinch grips [141].
- In the denervation procedure, all of the afferent nerves to the joint are transected completely: superficial branches of the radial nerve, cutaneous palmar branch of the median nerve, lateral cutaneous nerve of the forearm and recurrent branch of the median nerve [141].
- The denervation procedure is well tolerated with short postoperative recovery and fast results [141].
- The efficacy of denervation is short-lived with symptoms re-appearing in an unpredictable time frame [141].
- The authors do not recommend denervation technique in cases of advanced thumb CMC disease or for de novo scaphotrapeziotrapezoidal (STT) arthritis [75].
Resection Arthroplasty and Interposition
- The majority of reconstructive procedures for thumb CMC osteoarthritis involve resection arthroplasty of the trapezium, with removal of the articular base of the first metacarpal with or without ligament reconstruction and with or without interposition of autograft material [23].
- Resection arthroplasty is typically reserved for patients with stage III or IV disease, although durability of this procedure has been reported in a younger population with stage I disease [23].
- In 1984, Burton and Pellegrini described a technique for “advanced osteoarthritis of the thumb CMC joint” involving resection of the trapezium and base of the first metacarpal, along with a stabilization procedure they termed the flexor carpi radialis sling suspension interposition [23].
- A portion of the flexor carpi radialis (FCR) tendon is used to reconstruct the deep anterior oblique ligament (or perhaps more accurately, the intermetacarpal ligament) and to create an interposition arthroplasty, filling the void left by trapezium resection [23].
- Theoretically, this interposition and deep anterior oblique ligament reconstruction provides support and resists subsidence of the thumb metacarpal [23].
- Shah et al. have shown in a cadaver study that wrist biomechanics are altered following trapeziectomy, and the ligament reconstruction and tendon interposition (LRTI) procedure helps restore wrist biomechanics [23].
- Weilby has reported on a technique that involves passing half of the FCR tendon around the abductor pollicis longus (APL) tendon, making a suspension lattice in the void created by the trapezium resection [23].
- Routing a slip of the APL tendon around the extensor carpi radialis longus (ECRL) or passing half of the FCR around the ECRL has also been described to gain suspension and may be beneficial in revision procedures [23].
- Kuhns and colleagues have described a procedure whereby no interposition material or ligament reconstruction was employed, termed the hematoma and distraction arthroplasty, with temporary Kirshner wire stabilization [23].
- Excision of the trapezium alone without stabilization of any kind has been reported by Gervis as well as others [23].
- Long-term clinical outcomes of trapeziectomy for basal thumb arthritis are very positive, with interpositioning as an isolated procedure appearing, clinically, to be the preferred treatment despite greater radiological degradation when compared to suspensionplasty [3].
- Without the need for an implant and because of its long-lasting benefits, total trapeziectomy is currently the only surgical technique for thumb basal joint arthritis that can lay claim to being a potential life-long procedure [11].
- The multiplicity of treatment modalities for carpometacarpal joint arthritis shows that the underlying trapezium excision is probably the prime factor in patients' clinical improvement, and thumb index metacarpal stabilization needs to be based on each individual clinical scenario [69].
- Patients who underwent suture-button suspensionplasty (SBS) surgery for thumb CMC osteoarthritis achieve excellent long-term outcomes by maintaining favorable subjective and objective results, despite some radiographic subsidence over time [45].
- The Modified Zancolli Arthroplasty shows good results without any changes with passing of time, with 95% of cases having complete pain-free thumbs and no noted weakness or instability [19].
- This study demonstrates health state utility gains after basal thumb osteoarthritis surgery regardless of surgical techniques used [10].
- When post-operative values were compared to values obtained in non-arthritic thumbs, a reduction of 42% was found in thumbs treated operatively [172].
Arthroscopic Techniques
- Osteoarthritis will likely remain the most common indication for basal joint arthroscopy while chronic pain and inflammation are useful indications for metacarpophalangeal arthroscopy [21].
- Arthroscopic surgery for thumb base arthritis is a safe and feasible procedure that can provide longlasting symptom relief [153].
- The use of arthroscopic-assisted techniques for thumb CMC OA is still limited; however, it may be a reasonable option for patients with thumb CMC OA who do not respond to non-operative treatment [175].
- Endoscopic diagnostic evaluation and therapeutic procedures have been developed for the thumb basal joint in several indications related to osteoarthritis (OA): preventive, diagnostic and therapeutic [37].
Implant Arthroplasty
- In 2020, TMC arthroplasty (simple or dual mobility) is a reliable option in thumb basal joint arthritis with an implant survival rate of 90% at 10 years of follow-up, while providing pain relief and restoring strength and mobility [50].
- This series demonstrates that thumb arthroplasty is a reliable long-term solution for thumb base arthritis, with significant pain reduction and functional improvement, even after 15 years of follow-up [51].
- The ISIS® prosthesis is a reliable implant for treating disabling thumb basal joint arthritis, with a low complication rate and long-lasting clinical and functional improvements [52].
- The RegJoint™ is considered a useful adjunct in the management of a select cohort of patients with base of thumb arthritis [26].
- This paper focuses on the surgical techniques and outcomes of pyrocarbon implants for the treatment of basal thumb arthritis [25].
- Eighty-four percent of the thumbs had satisfactory results with good-to-excellent pain relief and function in a study of long-term results of trapeziometacarpal silicone arthroplasty [78].
- The study found good medium-term results and high satisfaction rates for the use of Swanson silastic interposition arthroplasty in revision thumb-base surgery for failed trapeziectomy, advocating the technique as an effective treatment option provided other treatable causes of poor outcome are excluded [22].
- Due to an unacceptably high complication rate, the Artelon CMC Spacer is no longer used for the management of basal joint arthritis of the thumb [30].
- Due to findings in a comparative study, the porous polyurethaneurea (Artelon) joint spacer has been abandoned for treatment of basilar thumb osteoarthritis [49].
Arthrodesis
- The procedure is contraindicated in patients with arthritis in the scaphotrapeziotrapezoid joint [120].
- Arthrodesis of the thumb MCP joint is routinely performed on the thumb MCP joint in cases of primary osteoarthritis or posttraumatic arthritis [171].
- The preferred position for arthrodesis of the thumb MCP joint is 20 degrees of flexion [171].
- Fixation for thumb MCP arthrodesis can be achieved with the tension band technique, two crossing percutaneous 0.0625-inch (1.5 mm) Kirshner wires, a 2.0 dorsal plate obtaining six cortices proximal and six cortices distal to the arthrodesis site, variable-pitch cannulated headless screw fixation with one or two screws, or a standard cortical screw and washer [171].
Complications and Revision
- The article reviews the most common complications after surgery for basal thumb arthritis, emphasizing resection arthroplasty, joint replacement, and joint fusion, and highlights possible management strategies for the different types of complications [8].
- Although indications for a new technique of first carpometacarpal joint suspension arthroplasty with palmaris longus tendon graft are limited, it adds an additional option for complicated cases of thumb base arthritis [7].
- The author notes that despite 70 years of research and numerous treatment options, the best management for trapeziometacarpal arthritis remains debated, with a constant proportion of patients remaining unhappy or symptomatic post-surgery [167].
Complications
- Foreign body reactions have been reported following trapeziectomy with Dacron interposition [192].
- Intracarpal synovitis has been reported as a complication related to Dacron interposition after trapeziectomy [192].
- The main cause of revision surgery for failed trapeziectomy is collapse of the thumb column resulting in arthrogenic contact of the first metacarpal with the scaphoid [200].
- Revision surgery for failed trapeziometacarpal joint arthritis can result in satisfactory long-term outcomes when metacarpophalangeal joint pathology is addressed and complications are avoided [169].
- Failure to recognize and treat the accompanying hyperextension deformity of the metacarpophalangeal joint in basal joint arthritis may lead to suboptimal results [189].
- The ISIS prosthesis for trapeziometacarpal arthritis is associated with a low complication rate [52].
- Simultaneous dual prosthetic replacement of the trapeziometacarpal and scaphotrapezial-trapezoid joints achieves a low complication rate [43].
- Long-term clinical outcomes of trapeziectomy with interposition show greater radiological degradation compared to suspensionplasty [3].
- Suture-button suspensionplasty for thumb carpometacarpal arthritis is associated with radiographic subsidence over time [45].
- Convex condylar arthroplasty failures occurred in osteoarthritic thumbs rather than rheumatoid thumbs [32].
Recovery
- Bone union for V-shaped osteotomy in thumb basal joint arthrodesis was confirmed radiographically after a mean of 6 weeks [55].
- A change of 0.7 to 0.9 cm on the Visual Analogue Scale is clinically meaningful in the context of long-term osteoarthritis of the thumb [31].
- Clinical and radiographic follow-up at 6 months after revision surgery for the Ivory trapeziometacarpal prosthesis was uneventful [212].
- Increased degenerate-like changes were observed at the pseudarthrosis site after simple excision of the trapezium at 6-year follow-up, but these changes did not influence the clinical outcome [213].
Key Evidence
- [Paper] The purpose of this paper is to provide an anatomic and scientific basis for the rational management of the patient with arthritis of the thumb basal joint complex. [1] (10.1016/s0894-1130(00)80034-4)
- [L4] Basal thumb arthritis is a common condition where a comprehensive history and clinical examination are sufficient for diagnosis. [2] (10.1136/pgmj.2006.046300)
- [L3] Long-term clinical outcomes of trapeziectomy for basal thumb arthritis are very positive, with interpositioning as an isolated procedure appearing, clinically, to be the preferred treatment despite greater radiological degradation when compared to suspensionplasty. [3] (10.1016/j.otsr.2016.08.014)
- [L3] Removal of the trapezium as treatment for basal thumb osteoarthritis does not increase the risk of developing wrist osteoarthritis in the long term. [4] (10.1186/s13018-021-02856-x)
- [L5] The anatomically based radiological classification that is proposed here aims to differentiate between the different forms of thumb basal joint arthritis so as to allow a prospective study to assess the results. [5] (10.1016/j.hansur.2020.04.013)
- [L4] The authors advocate this procedure for basal thumb arthritis in men. [6] (10.1016/j.main.2010.09.007)
- [L5] Although indications for this technique are limited, we believe it adds an additional option for complicated cases of thumb base arthritis. [7] (10.1097/bth.0000000000000045)
- [L5] The article reviews the most common complications after surgery for basal thumb arthritis, emphasizing resection arthroplasty, joint replacement, and joint fusion, and highlights possible management strategies for the different types of complications. [8] (10.1177/17531934231197787)
- [L5] [9] (10.5435/jaaos-d-17-00374)
- [L3] This study demonstrates health state utility gains after basal thumb osteoarthritis surgery regardless of surgical techniques used. [10] (10.1177/1753193420909753)
- [Paper] Without the need for an implant and because of its long-lasting benefits, total trapeziectomy is currently the only surgical technique for thumb basal joint arthritis that can lay claim to being a potential life-long procedure. [11] (10.1016/j.hansur.2020.05.015)
- [L2] Subjects presenting with early CMC OA had significantly lower bone density as assessed with HU at the thumb CMC joint (trapezium and first metacarpal base). [12] (10.1016/j.jhsa.2017.09.004)
- [L4] The prevalence of midcarpal arthritis in patients with basal joint arthritis is 24%. [13] (10.1177/1558944716660555hw)
- [L5] [14] (10.5435/00124635-200807000-00007)
- [L4] It shows good results without any changes with passing of time, with 95% of cases having complete pain-free thumbs and no noted weakness or instability. [19] (10.1097/bth.0b013e3181f79ae2)
- [L5] [20] (10.1016/j.hcl.2006.02.006)
- [L5] Osteoarthritis will likely remain the most common indication for basal joint arthroscopy while chronic pain and inflammation are useful indications for metacarpophalangeal arthroscopy. [21] (10.1016/j.jhsa.2007.02.020)
- [L4] The study found good medium-term results and high satisfaction rates, advocating the technique as an effective treatment option for revision thumb-base surgery provided other treatable causes of poor outcome are excluded. [22] (10.1177/1753193412447496)
- [L5] We present a new technique for the correction of thumb metacarpophalangeal joint hyperextension in patients with concomitant basal thumb osteoarthritis. [24] (10.1097/bth.0b013e3181f60b7d)
- [L4] This paper focuses on the surgical techniques and outcomes of pyrocarbon implants for the treatment of basal thumb arthritis. [25] (10.1016/j.hansur.2020.08.012)
- [L4] We consider the RegJoint™ a useful adjunct in the management of a select cohort of patients with base of thumb arthritis. [26] (10.1016/j.hansur.2019.11.001)
- [L4] [27] (10.1016/s0266-7681(97)80348-8)
- [L4] Due to an unacceptably high complication rate, we no longer use the Artelon CMC Spacer for the management of basal joint arthritis of the thumb. [30] (10.1016/j.jht.2013.12.001)
- [Paper] The authors propose that a change of 0.7 to 0.9 cm on the VAS is clinically meaningful in the context of long-term OA of the thumb. [31] (10.1177/15589447241235344)
- [L4] The three failures were in the osteoarthritic thumbs and not in the rheumatoid thumbs. [32] (10.1016/s0363-5023(09)90018-1)
- [L4] The reliability of the Eaton classification is better when the combination of PA–lateral and Bett’s views are used in the radiographic evaluation of basal arthritis of the thumb compared to using the posterior–anterior and lateral views or the Bett’s view alone. [34] (10.1016/j.jhsb.2003.09.003)
- [Paper] [37] (10.1016/j.hansur.2020.05.014)
- [L1] Review of the literature demonstrates that radiographs assist in the assessment of CMC joint disease, but there is not a reliable system for classification of disease severity. [40] (10.1007/s11999-013-3208-z)
- [L3] A reduction in cylindrical grasp is associated with early symptomatic and radiographic CMC OA, whereas gross grasp is not associated with early thumb CMC OA, suggesting that cylindrical grasp may be a better tool to detect changes in thumb and hand function seen during early disease stages. [41] (10.1007/s11999-016-5151-2)
- [L4] By preserving carpal stability and thumb function, this approach achieves favorable functional outcomes and a low complication rate, making it a potentially superior alternative for patients with high functional demands or those requiring durable long-term results. [43] (10.1016/j.jhsa.2025.12.013)
- [L5] Given that 1-year postoperative outcomes are similar for both tendon arthroplasty and total joint replacement and given the complexity of thumb arthritis and the diversity of patients’ needs, it is crucial to delve into the comparative efficacy, long-term outcomes and potential complications associated with each surgical approach. [44] (10.1177/17531934231206267)
- [L4] Patients who underwent SBS surgery for thumb CMC osteoarthritis achieve excellent long-term outcomes by maintaining favorable subjective and objective results, despite some radiographic subsidence over time. [45] (10.1016/j.jhsg.2023.12.002)
- [L3] Due to these findings, we have abandoned its use for treatment of basilar thumb osteoarthritis. [49] (10.1016/j.jhsa.2013.05.013)
- [Paper] In 2020, TMC arthroplasty (simple or dual mobility) is a reliable option in thumb basal joint arthritis with an implant survival rate of 90% at 10 years of follow-up, while providing pain relief and restoring strength and mobility. [50] (10.1016/j.hansur.2020.09.013)
- [L4] This series demonstrates that thumb arthroplasty is a reliable long-term solution for thumb base arthritis, with significant pain reduction and functional improvement, even after 15 years of follow-up. [51] (10.1177/15589447241233367)
- [L4] The ISISVR prosthesis is a reliable implant for treating disabling thumb basal joint arthritis, with a low complication rate and long-lasting clinical and functional improvements. [52] (10.1177/17531934221123166)
- [L4] The authors reviewed results in 65 patients (66 thumbs) and found that bone union was confirmed radiographically after a mean of 6 weeks. [55] (10.1097/bth.0b013e3181d148cb)
- [L3] In patients with established hand OA clinical involvement of the TBJ is associated with a higher clinical burden whereas radiological involvement of the TBJ is associated with older age and more structural abnormalities. [63] (10.1016/j.jht.2014.01.006)
- [L4] The findings indicate that the presented treatment approach could be a good alternative to more invasive surgical options in patients with earlier stages of thumb carpometacarpal joint osteoarthritis, with advantages including a low rate of complications, low invasiveness, and short recovery times. [64] (10.1177/1753193416632149)
- [L4] The significant relationship of power Doppler with pain severity in thumb base OA suggests this might be a useful tool in understanding pain aetiology. [65] (10.1186/s12891-019-2610-4)
- [L2] Arthroscopic total trapeziectomy appears to be a safe and effective treatment for end-stage arthrosis of the thumb basal joint. [66] (10.1177/15589447241262055)
- [L5] The multiplicity of treatment modalities for carpometacarpal joint arthritis shows that the underlying trapezium excision is probably the prime factor in patients' clinical improvement, and thumb index metacarpal stabilization needs to be based on each individual clinical scenario. [69] (10.1016/j.jhsa.2007.02.013)
- [L4] Thumb metacarpophalangeal instability is commonly found in conjunction with trapeziometacarpal osteoarthritis. [70] (10.1016/j.hansur.2020.05.013)
- [Paper] Basal joint osteoarthritis is not common in Asia, where radiocapitellar and radioulnar osteoarthritis with associated extensor tendon rupture at the wrist are the common conditions. [72] (10.1016/0363-5023(93)90408-u)
- [L3] The radiological classification does not describe all stages of carpometacarpal joint osteoarthritis accurately enough to permit reliable and consistent communication between clinicians. [73] (10.1016/j.jhsa.2014.09.007)
- [L3] The authors do not recommend this technique in cases of advanced thumb CMC disease or for de novo scaphotrapeziotrapezoidal (STT) arthritis. [75] (10.1016/j.hansur.2017.01.007)
- [L3] The metacarpal surface of the trapezium demonstrates three distinct patterns of wear in arthritic surgical specimens. [76] (10.1055/s-0033-1350088)
- [L4] Eighty-four percent of the thumbs had satisfactory results with good-to-excellent pain relief and function. [78] (10.1053/jhsu.2002.31733)
- [L4] [79] (10.1016/0363-5023(92)90303-7)
- [L5] [80] (10.1016/s0363-5023(96)80149-3)
- [L4] [83] (10.1016/s0363-5023(84)80015-5)
- [L4] [86] (10.1016/j.jhsa.2025.01.018)
- [L4] However, it has been found that the higher the thumb mobility, the more the trapezium tilts under load. [104] (10.1016/j.main.2011.04.002)
- [L2] [110] (10.1177/1753193420950600)
- [L3] The high prevalence of other symptomatic disorders of the hand requires a complete and standardized clinical examination of the hand, as they must be considered during surgical planning. [112] (10.1177/17531934231220644)
- [L5] [113] (10.1177/1753193420970343)
- [L2] The SCOOTT trial is a multicentre, three-arm randomized controlled trial designed to determine the clinical and cost-effectiveness of treating basal osteoarthritis of the thumb with or without surgery, and to compare trapeziectomy versus thumb CMCJA. [115] (10.1302/0301-620x.108b1.bjj-2025-0483.r1)
- [L5] During thumb oppositional motion, internal rotation of the first metacarpal occurred, with the palmar base rotating primarily with respect to the dorsal base. [117] (10.1016/j.jhsa.2017.07.028)
- [Paper] Scaphotrapeziotrapezoid osteoarthritis (STT OA) is common and often associated with thumb basal joint arthritis, characterized by pain at the base of the thumb on the volar aspect and during resisted extension. [118] (10.1016/j.hansur.2020.12.007)
- [L5] The procedure is contraindicated in patients with arthritis in the scaphotrapeziotrapezoid joint. [120] (10.1097/00130911-200212000-00004)
- [Paper] [121] (10.1016/s0894-1130(04)00179-6)
- [L5] In palmar abduction, 28% of the trapezium was in contact with 28% of the metacarpal, and in radial abduction, 25% of the trapezium was in contact with 25% of the metacarpal. [124] (10.1053/jhsu.1999.0491)
- [L1] [128] (10.1002/acr.24084)
- [L4] [129] (10.1177/1753193412469127)
- [L4] The Eaton classification of basal joint arthritis is moderately reliable, with overall mean intrarater and interrater reliabilities of .657 and .529, respectively. [135] (10.1053/jhsu.2002.35310)
- [L3] Altered thumb rotation patterns during pinch may contribute to joint misalignment and the development of osteoarthritis. [136] (10.1177/17531934251383073)
- [L3] Future studies should determine the relationship between thumb hypermobility and joint collapse and how to manage these conditions effectively. [140] (10.1016/j.jht.2020.07.003)
- [L3] [141] (10.1016/j.otsr.2023.103772)
- [L4] Arthroscopic surgery for thumb base arthritis is a safe and feasible procedure that can provide longlasting symptom relief. [153] (10.1177/1558944716660555r)
- [L5] A proposed arthroscopic classification for basal joint osteoarthritis provides additional clinical information and can direct further treatment depending on the stage of disease. [157] (10.1016/j.main.2006.07.026)
- [Paper] Degenerative arthritis of the thumb CMC joint is a common treatable condition where nonoperative modalities are effective for early stages, while surgical options are reserved for cases refractory to conservative measures. [158] (10.1016/j.hcl.2008.03.001)
- [L5] Our newly described procedure—partial trapezial resection with local capsular interposition arthroplasty for thumb basal joint arthritis—utilizes remaining local tissue as an interposition without ligament reconstruction, eliminating the need for tendon harvest and the morbidity associated with the harvest. [160] (10.1097/bth.0000000000000048)
- [L3] The authors suggest that ulnar instability should be included in the classification of thumb CMCj osteoarthritis stages and considered in treatment options. [164] (10.1055/s-0039-1697650)
- [L4] According to our results and in the absence of series published with a sufficient level of evidence, the interest of arthroscopy in the surgical treatment of thumb carpometacarpal arthritis remains to be demonstrated. [165] (10.1016/j.hansur.2016.10.026)
- [L5] The author notes that despite 70 years of research and numerous treatment options, the best management for trapeziometacarpal arthritis remains debated, with a constant proportion of patients remaining unhappy or symptomatic post-surgery. [167] (10.1177/17531934221122987)
- [L4] Revision surgery, however, can result in satisfactory long-term outcomes particularly when metacarpophalangeal joint pathology is addressed and complications are avoided. [169] (10.1016/j.jhsa.2018.10.025)
- [L4] [170] (10.1097/bth.0b013e3180437602)
- [L4] When post-operative values were compared to values obtained in non-arthritic thumbs, a reduction of 42% was found in thumbs treated operatively. [172] (10.1016/s0266-7681(96)80093-3)
- [L1] The use of arthroscopic-assisted techniques for thumb CMC OA is still limited; however, it may be a reasonable option for patients with thumb CMC OA who do not respond to non-operative treatment. [175] (10.1177/1753193418757122)
- [L5] [189] (10.1016/j.jhsa.2011.12.012)
- [L3] Wrist radiographs demonstrate a 47% sensitivity and 94% specificity in predicting end-stage ST joint arthritis, emphasizing the importance of directly visualizing the ST joint after trapeziectomy. [191] (10.1177/1558944718765246)
- [L4] [192] (10.1016/j.hansur.2015.11.001)
- [L5] Radiographic development of trapeziometacarpal arthrosis is an expected part of human aging, although clinically significant, functionally limiting trapeziometacarpal arthrosis is less common, and its development may be unrelated to hand use. [196] (10.1016/j.jhsa.2015.04.038)
- [L5] [197] (10.5435/jaaos-d-18-00683)
- [L4] This ratio can be easily measured and is independent of radiographic conditions. [198] (10.1016/j.hansur.2017.01.002)
- [L4] The main cause of revision was collapse of the thumb column resulting in arthrogenic contact of the first metacarpal with the scaphoid. [200] (10.1016/j.hansur.2021.03.014)
- [L5] [201] (10.1016/s0363-5023(10)80054-1)
- [L4] [205] (10.1016/s0363-5023(86)80136-8)
- [L4] The significantly greater trabecular bone volume, thickness, and connectivity in the volar-ulnar quadrant compared with the dorsal-radial and dorsal-ulnar quadrants provides evidence that the greatest compressive loads at the first carpometacarpal joint occur at the volar-ulnar quadrant of the trapezium, representing a consistently affected region of wear in both normal and arthritic states. [206] (10.1016/j.jhsa.2012.10.038)
- [L5] The case illustrates that pigmented villonodular synovitis (PVNS) can cause bicortical erosion in the thumb, which was not obvious on plain radiographs but appreciated on MRI. [208] (10.1177/1753193409352712)
- [L3] However, a negative grind test does not necessarily reflect negative radiographic evidence of thumb CMC osteoarthritis. [209] (10.1016/j.jht.2010.02.001)
- [L5] Clinical and radiographic follow-up at 6 months after surgery was uneventful. [212] (10.1016/j.hansur.2020.08.003)
- [L2] Increased degenerate-like changes were observed after simple excision of the trapezium but these did not influence the clinical outcome. [213] (10.1007/s11999-013-2956-0)
References
[1] Arthritis of the thumb basal joint complex. Journal of Hand Therapy. 2000. DOI: 10.1016/s0894-1130(00)80034-4
[2] Basal thumb arthritis. Postgraduate Medical Journal. 2007. DOI: 10.1136/pgmj.2006.046300
[3] Minimum 10-year clinical and radiological follow-up of trapeziectomy with interposition or suspensionplasty for basal thumb arthritis. Orthopaedics & Traumatology: Surgery & Research. 2016. DOI: 10.1016/j.otsr.2016.08.014
[4] Trapeziectomy for basal thumb osteoarthritis does not increase the risk of developing wrist osteoarthritis in the long term. Journal of Orthopaedic Surgery and Research. 2021. DOI: 10.1186/s13018-021-02856-x
[5] Anatomically based radiological classification of thumb basal joint arthritis. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.04.013
[6] La rhizarthrose chez l’homme : des enjeux différents. Résultats de trois techniques chirurgicales. Chirurgie de la Main. 2011. DOI: 10.1016/j.main.2010.09.007
[7] A New Technique of First Carpometacarpal Joint Suspension Arthroplasty With Palmaris Longus Tendon Graft. Techniques in Hand & Upper Extremity Surgery. 2014. DOI: 10.1097/bth.0000000000000045
[8] Basal thumb arthritis surgery: complications and its management. Journal of Hand Surgery (European Volume). 2024. DOI: 10.1177/17531934231197787
[9] Thumb Basal Joint Arthritis. Journal of the American Academy of Orthopaedic Surgeons. 2018. DOI: 10.5435/jaaos-d-17-00374
[10] Basal thumb osteoarthritis surgery improves health state utility irrespective of technique: a study of UK Hand Registry data. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420909753
[11] Total trapeziectomy. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.05.015
[12] Changes in Local Bone Density in Early Thumb Carpometacarpal Joint Osteoarthritis. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2017.09.004
[13] Midcarpal and STT Arthritis in Patients With CMC Arthritis. HAND. 2016. DOI: 10.1177/1558944716660555hw
[14] Basal Joint Arthritis of the Thumb. Journal of the American Academy of Orthopaedic Surgeons. 2008. DOI: 10.5435/00124635-200807000-00007
[15] Green S Operative Hand Surgery. The Rheumatoid Thumb.
[16] Green S Operative Hand Surgery. Treatment of the Osteoarthritic Hand and Thumb > ANATOMY AND BIOMECHANICS > Diagnostic Imaging.
[19] The Modified Zancolli Arthroplasty for Basal Thumb Arthritis. Techniques in Hand & Upper Extremity Surgery. 2010. DOI: 10.1097/bth.0b013e3181f79ae2
[20] Trapeziometacarpal Arthroscopy: A Classification and Treatment Algorithm. Hand Clinics. 2006. DOI: 10.1016/j.hcl.2006.02.006
[21] Arthroscopy of the Trapeziometacarpal and Metacarpophalangeal Joints. The Journal of Hand Surgery. 2007. DOI: 10.1016/j.jhsa.2007.02.020
[22] The use of Swanson silastic interposition arthroplasty in revision thumb-base surgery for failed trapeziectomy; a case series of 10 patients. Journal of Hand Surgery (European Volume). 2012. DOI: 10.1177/1753193412447496
[23] Green S Operative Hand Surgery. Treatment of the Osteoarthritic Hand and Thumb > Treatment > Indications and Contraindications.
[24] New Transfer for Correction of Thumb Metacarpophalangeal Hyperextension in Cases With Associated Surgery for Basal Thumb Osteoarthritis (Transfer of the Volar Half of the Abductor Pollicis Brevis). Techniques in Hand & Upper Extremity Surgery. 2011. DOI: 10.1097/bth.0b013e3181f60b7d
[25] Pyrocarbon implants for the basal thumb arthritis. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.08.012
[26] The use of the RegJoint™ implant for base of thumb osteoarthritis: Results with a minimum follow-up of 2 years. Hand Surgery and Rehabilitation. 2020. DOI: 10.1016/j.hansur.2019.11.001
[27] Trapeziometacarpal Joint Arthrodesis for Osteoarthritis. Journal of Hand Surgery. 1997. DOI: 10.1016/s0266-7681(97)80348-8
[30] The use of the Artelon CMC Spacer for osteoarthritis of the basal joint of the thumb. Journal of Hand Therapy. 2014. DOI: 10.1016/j.jht.2013.12.001
[31] Estimating the Minimal Clinically Important Difference on the Visual Analogue Scale for Carpometacarpal Thumb Joint Osteoarthritis. HAND. 2024. DOI: 10.1177/15589447241235344
[32] Convex condylar arthroplasty of the basal joint of the thumb: Failure under load. The Journal of Hand Surgery. 1990. DOI: 10.1016/s0363-5023(09)90018-1
[34] Radiographic Optimization of the Eaton Classification. Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsb.2003.09.003
[35] Exam Of The Hand Wrist 2Ed. Movements of the thumb.
[37] Basal joint arthroscopy indications in first CMC joint arthritis. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.05.014
[40] Intra- and Interobserver Reliability of the Eaton Classification for Trapeziometacarpal Arthritis: A Systematic Review. Clinical Orthopaedics & Related Research. 2014. DOI: 10.1007/s11999-013-3208-z
[41] Reduction in Cylindrical Grasp Strength Is Associated With Early Thumb Carpometacarpal Osteoarthritis. Clinical Orthopaedics & Related Research. 2017. DOI: 10.1007/s11999-016-5151-2
[43] Simultaneous Dual Prosthetic Replacement of Trapeziometacarpal and Scaphotrapezial-Trapezoid Joints in Pantrapezial Osteoarthritis: Midterm Results of a Combined Implant Strategy. The Journal of Hand Surgery. 2026. DOI: 10.1016/j.jhsa.2025.12.013
[44] Re: Herren DB, Marks M, Neumeister S, Schindele S. Short-term recovery after implant versus resection arthroplasty in trapeziometacarpal joint osteoarthritis. J Hand Surg Eur. 2023. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231206267
[45] Long-Term Results of Suture-Button Suspensionplasty in the Treatment of Thumb Carpometacarpal Arthritis: A Minimum 10-Year Follow-Up. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2023.12.002
[49] Porous Polyurethaneurea (Artelon) Joint Spacer Compared to Trapezium Resection and Ligament Reconstruction. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2013.05.013
[50] Trapeziometacarpal prostheses. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.09.013
[51] Thumb Arthroplasty as Reliable Long-term Solution for Trapeziometacarpal Osteoarthritis: A Minimum of 15 Years of Follow-up. HAND. 2024. DOI: 10.1177/15589447241233367
[52] The ISIS® prosthesis in 77 cases of trapeziometacarpal arthritis: outcomes and survival at a minimum follow-up of 5 years. Journal of Hand Surgery (European Volume). 2022. DOI: 10.1177/17531934221123166
[55] A New Concept For Thumb Basal Joint Arthrodesis: The V-shaped Osteotomy. Techniques in Hand & Upper Extremity Surgery. 2010. DOI: 10.1097/bth.0b013e3181d148cb
[63] Thumb Base Involvement in Established Hand Osteoarthritis. Journal of Hand Therapy. 2014. DOI: 10.1016/j.jht.2014.01.006
[64] Outcomes of denervation, joint lavage and capsular imbrication for painful thumb carpometacarpal joint osteoarthritis. Journal of Hand Surgery (European Volume). 2016. DOI: 10.1177/1753193416632149
[65] Musculoskeletal ultrasound in symptomatic thumb-base osteoarthritis: clinical, functional, radiological and muscle strength associations. BMC Musculoskeletal Disorders. 2019. DOI: 10.1186/s12891-019-2610-4
[66] Arthroscopic Total Trapeziectomy for Thumb Carpometacarpal Arthrosis. HAND. 2024. DOI: 10.1177/15589447241262055
[69] Extensor Carpi Radialis Longus Technique for Thumb Arthritis. The Journal of Hand Surgery. 2007. DOI: 10.1016/j.jhsa.2007.02.013
[70] Metacarpophalangeal joint instability in trapeziometacarpal osteoarthritis: A systematic review. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.05.013
[72] Primary idiopathic osteoarthritis in the upper extremity. The Journal of Hand Surgery. 1993. DOI: 10.1016/0363-5023(93)90408-u
[73] Inter- and Intrarater Reliability of Osteoarthritis Classification at the Trapeziometacarpal Joint. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.09.007
[75] Thumb carpometacarpal joint denervation for primary osteoarthritis: A prospective study of 31 thumbs. Hand Surgery and Rehabilitation. 2017. DOI: 10.1016/j.hansur.2017.01.007
[76] Trapezial Topography in Thumb Carpometacarpal Arthritis. Journal of Wrist Surgery. 2013. DOI: 10.1055/s-0033-1350088
[78] Long-term results of trapeziometacarpal silicone arthroplasty. The Journal of Hand Surgery. 2002. DOI: 10.1053/jhsu.2002.31733
[79] Long-term follow-up of trapeziometacarpal arthroplasty with coexisting scaphotrapezial disease. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90303-7
[80] Extension metacarpal osteotomy in the treatment of trapeziometacarpal osteoarthritis: A biomechanical study. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80149-3
[83] Ligament reconstruction for the painful thumb carpometacarpal joint: A long-term assessment. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80015-5
[86] Tendon interposition arthroplasty for degenerative arthritis of the trapeziometacarpal joint of the thumb. The Journal of Hand Surgery. 2025. DOI: 10.1016/j.jhsa.2025.01.018
[104] Relationship between thumb laxity and trapezium kinematics. Chirurgie de la Main. 2011. DOI: 10.1016/j.main.2011.04.002
[110] Discrepancies in conservative treatment for thumb carpometacarpal arthritis: a comparison between different specialities and patient characteristics. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420950600
[112] Trapeziometacarpal osteoarthritis: do not forget other disorders. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231220644
[113] Trapeziometacarpal joint arthritis: a personal approach to its treatment. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420970343
[115] What is the most effective treatment for basal osteoarthritis of the thumb?. The Bone & Joint Journal. 2026. DOI: 10.1302/0301-620x.108b1.bjj-2025-0483.r1
[117] In Vivo 3-Dimensional Kinematics of Thumb Carpometacarpal Joint During Thumb Opposition. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2017.07.028
[118] Scaphotrapeziotrapezoid osteoarthritis: From the joint to the patient. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.12.007
[120] Indications and Techniques for Thumb Carpometacarpal Arthrodesis. Techniques in Hand and Upper Extremity Surgery. 2002. DOI: 10.1097/00130911-200212000-00004
[121] The human first carpometacarpal joint: Osteoarthritic degeneration and 3-dimensional modeling. Journal of Hand Therapy. 2004. DOI: 10.1016/s0894-1130(04)00179-6
[124] Contact area of the trapeziometacarpal joint. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.0491
[128] Efficacy of Nonsurgical Interventions for Trapeziometacarpal (Thumb Base) Osteoarthritis: A Systematic Review. Arthritis Care & Research. 2020. DOI: 10.1002/acr.24084
[129] Trapeziometacarpal narrow pseudarthrosis: a new surgical technique to treat thumb carpometacarpal joint arthritis. Journal of Hand Surgery (European Volume). 2012. DOI: 10.1177/1753193412469127
[135] Intrarater and interrater reliability of the Eaton classification of basal joint arthritis. The Journal of Hand Surgery. 2002. DOI: 10.1053/jhsu.2002.35310
[136] Thumb rotation patterns during pinch in patients with trapeziometacarpal osteoarthritis. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934251383073
[140] Carpometacarpal and metacarpophalangeal joint collapse is associated with increased pain but not functional impairment in persons with thumb carpometacarpal osteoarthritis. Journal of Hand Therapy. 2021. DOI: 10.1016/j.jht.2020.07.003
[141] Thumb basal joint arthritis in 2023. Orthopaedics & Traumatology: Surgery & Research. 2024. DOI: 10.1016/j.otsr.2023.103772
[144] Green S Operative Hand Surgery. Treatment of the Osteoarthritic Hand and Thumb > ANATOMY AND BIOMECHANICS.
[153] Arthroscopic Management of Thumb Base Arthritis. HAND. 2016. DOI: 10.1177/1558944716660555r
[157] Arthroscopie des articulations trapézométacarpienne et métacarpophalangienne : installation, voie d'abord et exploration. Chirurgie de la Main. 2006. DOI: 10.1016/j.main.2006.07.026
[158] Early Treatment of Degenerative Arthritis of the Thumb Carpometacarpal Joint. Hand Clinics. 2008. DOI: 10.1016/j.hcl.2008.03.001
[160] Partial Trapeziectomy With Capsular Interposition Arthroplasty (PTCI). Techniques in Hand & Upper Extremity Surgery. 2014. DOI: 10.1097/bth.0000000000000048
[164] Treatment of Severe Ulnar Instability of the MCP Joint Improves Function in LRTI Arthroplasty for Osteoarthritis of the Thumb CMC Joint. Journal of Wrist Surgery. 2019. DOI: 10.1055/s-0039-1697650
[165] Interposition sous arthroscopie dans la rhizarthrose du pouce : à propos d’une série de 26 cas. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.10.026
[167] Trapeziometacarpal arthritis: 70 years after Gervis. Journal of Hand Surgery (European Volume). 2022. DOI: 10.1177/17531934221122987
[169] Outcomes of Revisions for Failed Trapeziometacarpal Joint Arthritis Surgery. The Journal of Hand Surgery. 2019. DOI: 10.1016/j.jhsa.2018.10.025
[170] Treatment of Early Basal Joint Arthritis Using a Combined Arthroscopic Debridement and Metacarpal Osteotomy. Techniques in Hand & Upper Extremity Surgery. 2007. DOI: 10.1097/bth.0b013e3180437602
[171] Green S Operative Hand Surgery. Treatment of the Osteoarthritic Hand and Thumb > Metacarpophalangeal Joint Arthrodesis.
[172] Basal Joint Arthrosis. Journal of Hand Surgery. 1996. DOI: 10.1016/s0266-7681(96)80093-3
[175] A systematic review and meta-analysis of arthroscopic assisted techniques for thumb carpometacarpal joint osteoarthritis. Journal of Hand Surgery (European Volume). 2018. DOI: 10.1177/1753193418757122
[189] Metacarpophalangeal Joint Hyperextension and the Treatment of Thumb Basilar Joint Arthritis. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2011.12.012
[190] Green S Operative Hand Surgery. Treatment of the Osteoarthritic Hand and Thumb > Evaluation.
[191] Comparison of Radiographic and Intraoperative Visual Assessment of Scaphotrapezoid Joint Arthritis in Patients With End-Stage Carpometacarpal Arthritis of the Thumb Base. HAND. 2018. DOI: 10.1177/1558944718765246
[192] Foreign body reaction after trapeziectomy and Dacron interposition. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2015.11.001
[196] Epidemiology of Trapeziometacarpal Arthrosis. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.04.038
[197] Thumb Metacarpophalangeal Joint Arthritis. Journal of the American Academy of Orthopaedic Surgeons. 2019. DOI: 10.5435/jaaos-d-18-00683
[198] M1/M2 ratio for radiological follow-up of trapeziometacarpal surgery. Hand Surgery and Rehabilitation. 2017. DOI: 10.1016/j.hansur.2017.01.002
[200] Revision of trapeziectomy failures in thumb base osteoarthritis: retrospective analysis of ten cases and review of the literature. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2021.03.014
[201] Osteoarthritis of the trapeziometacarpal joint: The pathophysiology of articular cartilage degeneration. I. Anatomy and pathology of the aging joint. The Journal of Hand Surgery. 1991. DOI: 10.1016/s0363-5023(10)80054-1
[205] Surgical management of basal joint arthritis of the thumb. Part I. Long-term results of silicone implant arthroplasty. The Journal of Hand Surgery. 1986. DOI: 10.1016/s0363-5023(86)80136-8
[206] Trapezium Trabecular Morphology in Carpometacarpal Arthritis. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2012.10.038
[208] Pigmented villonodular synovitis with bicortical erosions in the thumb. Journal of Hand Surgery (European Volume). 2010. DOI: 10.1177/1753193409352712
[209] Diagnostic Value of Clinical Grind Test for Carpometacarpal Osteoarthritis of the Thumb. Journal of Hand Therapy. 2010. DOI: 10.1016/j.jht.2010.02.001
[212] Revision surgery for the Ivory® trapeziometacarpal prosthesis: compatibility with the Touch® prosthesis allows the stem to be retained. Hand Surgery and Rehabilitation. 2020. DOI: 10.1016/j.hansur.2020.08.003
[213] Degenerative Change at the Pseudarthrosis After Trapeziectomy at 6-year Followup. Clinical Orthopaedics & Related Research. 2014. DOI: 10.1007/s11999-013-2956-0