Clinicians › Shoulder
Os Acromiale
Patient-facing topic on os acromiale — failed fusion of an acromial ossification centre that may cause shoulder pain and contribute to subacromial impingement.
For patients: a plain-language version of this topic is available. See the patient guide.
Overview
Os acromiale is an accessory bone at the acromion that is predominantly asymptomatic and requires no treatment in the majority of patients [1]. Diagnosis relies on imaging features rather than age restrictions [3]. The condition is frequently associated with rotator cuff injuries and serves as a co-condition in patients with rotator cuff tears [4, 10]. A multicenter study has examined the prevalence and associated factors of os acromiale within the Japanese population [11].
For symptomatic cases, initial management is nonsurgical [2]. When nonoperative measures fail, surgical intervention predictably leads to decreased symptoms and improved clinical outcomes [5, 6]. Surgical options include arthroscopic sub-total excision, arthroscopic subacromial decompression of stable fragments, and open reduction and internal fixation of unstable fragments [18]. Osteosynthesis to achieve bony union is a safe, effective, and reliable technique for large and unstable symptomatic os acromiale [27]. In athletes, this technique is a predictable and consistent treatment [9]. However, surgical treatment of symptomatic meso-os acromiale with concomitant rotator cuff pathology yielded poorer outcomes, with only 53% achieving satisfactory results overall [16]. Surgical treatment is usually not indicated for os acromiale in the professional tennis player [20], and care should be taken not to perform acromioplasty in the presence of painful os acromiale [21].
In the context of reverse total shoulder arthroplasty, the presence of os acromiale does not appear to have a negative impact on clinical outcomes, and rTSA remains a safe and effective treatment option [8, 17]. Shoulders with os acromiale had a similar overall complication rate compared with matched controls (14% vs. 12%; P = 0.658) [12]. Postoperative local tenderness at the os acromiale can be expected in 1 out of 4 patients but resolves spontaneously over time in the majority of patients [7]. Ipsilateral os acromiale may be a relative contraindication to the clavicle hook plate [24].
Anatomy & Pathophysiology
Bony Anatomy
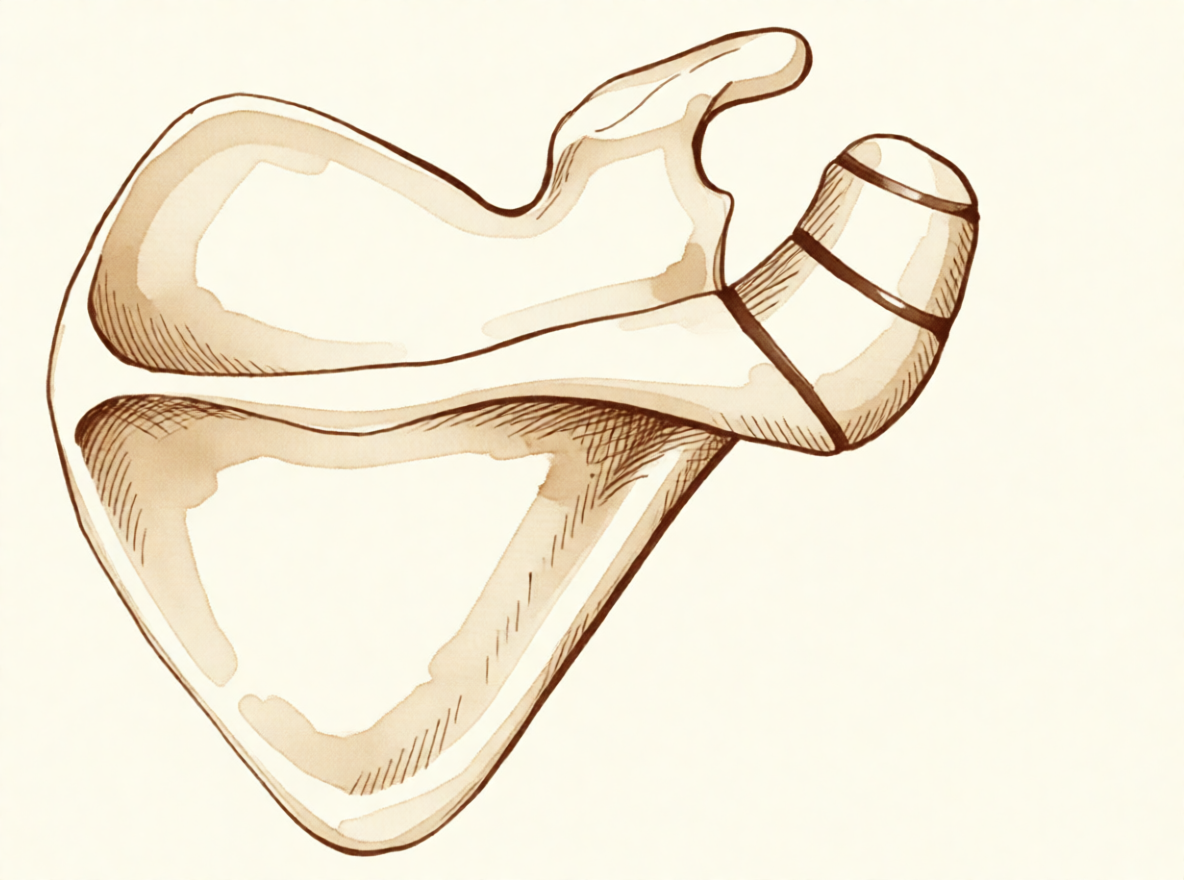
The acromion develops from three distinct ossification centers: the metacromion at the base, the mesoacromion in the middle, and the preacromion at the tip [41]. Os acromiale is defined as the failure of fusion between these secondary ossification centers, most commonly occurring between the mesoacromion and metacromion [52]. The unfused segment is most frequently the meso-acromion [28]. Anatomically, the acromion, coracoacromial ligament, and coracoid process form the coracoacromial arch, a rigid bony-ligamentous structure that imparts stability to the shoulder girdle [38]. The rotator cuff, subacromial bursa, and subdeltoid bursa pass underneath this arch [38]. The lateral acromion serves as the insertion site for the deltoid muscle [14].
Pathophysiology
Diagnosis of os acromiale is typically incidental, identified on axillary view radiographs of the shoulder [28]. The axillary lateral radiographic view specifically demonstrates the presence of the unfused bone [66]. Primary shoulder pain is usually unrelated to the unfused os acromiale, with no relation between the presence of os acromiale and shoulder pain regardless of diagnosis [28, 13]. When os acromiale drives symptoms, the two principal causes are motion at the non-union site or an impingement-type syndrome resulting from flexion of the os fragment during deltoid contraction and arm elevation [28]. Pain from these mechanisms has been reported in throwing athletes and swimmers [28]. Previously stable non-unions can become unstable following blunt trauma to the region [28].
Extrinsic impingement occurs when the space available for the rotator cuff is diminished, with pathologic os acromiale cited as an example [65]. A tear of the rotator cuff may often be associated with os acromiale, likely due to impingement from abnormal motion at the fibrous union site [15]. One study supports previous findings that os acromiale is associated with rotator cuff injuries [10]. However, the rate of rotator cuff tears for patients with os acromiale was comparable with that of patients without os acromiale, indicating no definitive connection between os acromiale and rotator cuff pathology [14].
Classification
Other Considerations: Meta–os acromiale is the rarest subtype of os acromiale [32]. The rate of rotator cuff tears for patients with os acromiale was comparable with that of patients without os acromiale, indicating that there is no definitive connection between os acromiale and rotator cuff pathology [14].
Clinical Presentation
General Presentation and Prevalence
Primary shoulder pain is usually unrelated to an unfused os acromiale [28]. The prevalence of this condition is reported to range from 1.1% to 15% [67]. In a sample of 1594 skeletons, the overall frequency was 8.34% [19]. Among Korean patients visiting a shoulder outpatient clinic, os acromiale was observed in 7 per 1,000 individuals [14]. Bilateral involvement was found in 15.4% of cases in this Korean patient population [14]. Racial differences in prevalence are consistent, with Black people showing a higher rate (13.2%-18.2%) than white people (5.8%-9.5%) [14].
Symptomatic Presentation
Patients with a symptomatic os acromiale typically present with anterolateral shoulder pain localized to the acromion [67]. Complaints of pain with overhead activities are common [67]. Physical examination may reveal rotator cuff weakness, a positive impingement sign, or decreased forward elevation [67]. Two specific clinical findings aid in diagnosis: tenderness directly over the superior acromion and palpable motion at the pseudarthrosis site [67]. The presence of one or both of these findings is useful for making the correct diagnosis [67].
Os acromiale must be included in the differential diagnosis for swimming athletes presenting with shoulder pain, particularly when there is a failed response to physical therapy, activity modification, or steroid injection [23]. In young athletes, awareness of the condition, appropriate clinical examination, and image studies are crucial to confirm the diagnosis [26].
Imaging and Diagnosis
Anteroposterior, scapular Y, and axillary radiographic views of the shoulder should be routinely obtained to help confirm the diagnosis [67]. The os acromiale can be easily overlooked radiographically and is best visualized on the axillary lateral radiograph [67]. On magnetic resonance images, edema or fluid may be noted at the pseudoarthrosis site in symptomatic cases [67].
Etiology of Symptoms
The etiology of symptoms in symptomatic os acromiale is not definitively understood but has been postulated to arise from two potential causes [67]. One source is a painful inflammatory reaction due to motion at the pseudoarthrosis site [67]. Another source is an impingement-type syndrome resulting from flexion of the os fragment during deltoid contraction and arm elevation [28]. Pain from either motion at the non-union site or impingement has been reported in a variety of sports, particularly among throwing athletes and swimmers [28]. Previously stable non-unions can become unstable following an episode of blunt trauma to the region [28].
Investigations
Plain radiography: Standardized plain films are almost always sufficient for shoulder evaluation, and the temptation to "overimage" should be resisted [31]. The purpose of imaging is to establish the diagnosis, determine pathoanatomy severity, assist in surgical planning, and illustrate the condition to the patient [31]. The standard shoulder series includes orthogonal views: a true AP view in the scapular plane (Grashey view), an AP view with the arm in internal rotation, an axillary view, and a scapular Y view [62, 64]. The Grashey view is oriented to the scapula with the beam centered on the glenohumeral joint line, visualizing the anterior greater tuberosity in profile and revealing proximal humeral migration [62, 64]. The AP view with internal rotation visualizes the posterior aspect of the greater tuberosity and the lesser tuberosity in profile [62]. The axillary view is necessary for evaluating glenohumeral joint instability, determining humeral head position, and assessing glenoid morphology in osteoarthritis [62, 64]. It provides an unambiguous view of anteroposterior glenohumeral alignment and is centered on the epicenter of the humeral head and glenoid [64]. The scapular Y view visualizes the coracoacromial arch, reveals coracoacromial spurs associated with rotator cuff pathology, and serves as a reliable alternative for evaluating subluxation and dislocation [62]. It also shows acromial shape [62]. In patients unable to abduct the arm due to acute injury, a scapular “Y” view must be obtained to evaluate the relationship of the humeral head to the glenoid [64]. A Velpeau view can be obtained in guarding patients with the plate positioned posteriorly and under the shoulder [64]. Modified axillary views include positioning the patient sitting on the table with the arm abducted 60 degrees, or leaning slightly forward with the beam aiming down 45 degrees toward a plate positioned behind the patient, providing greater comfort in acute traumatic dislocation [64]. Special views include the Zanca view (10° cephalic tilt centered over the AC joint) for AC joint evaluation, the Stryker notch view for Hill-Sachs lesions, the West point view for anterior glenoid bone loss, the Apical oblique view for glenoid rim fractures, and the Serendipity view for the sternoclavicular joint [62]. The Stryker Notch, West Point, and Bernageau profile views assist in identifying pathology related to shoulder instability [64]. Conventional radiographs are appropriate for patients with shoulder pain, trauma history, dislocation, night pain, or chronic pain [62]. Normal acromiohumeral distance is 7 to 14 mm, the glenohumeral joint space should be symmetric superiorly and inferiorly, and the coracoclavicular distance is normally 1.1 to 1.3 cm [62]. Neer classified acromial morphology as type I (flat), type II (curved), and type III (hooked); type III morphology correlates with rotator cuff disease, though no direct causal relationship has been demonstrated, and the classification shows relatively poor interobserver reliability [62]. In a systematic review of posterior shoulder dislocations, 73% of patients had a missed initial diagnosis due to the lack of an axillary view, Y view, or CT imaging [64]. Of these, 98% (147/150) had only AP or lateral views [64]. When axillary or Y-view radiographs were made subsequently, the diagnosis was confirmed in 100% of patients [64]. In a comparison of 75 consecutive patients with suspected dislocations, the axillary and scapular “Y” views resulted in the same diagnosis in 92% (69 patients) [64]. 81% of patients preferred the scapular “Y” view due to less pain, and radiology technicians preferred it due to ease of acquisition [64]. The synchondrosis of an os acromiale can be injured following trauma, emphasizing the need for appropriate radiographic investigation including axillary views [33].
MRI: MRI is the modality of choice for evaluating the rotator cuff, biceps, and subacromial/subdeltoid bursa [61]. It is useful to identify osteonecrosis of the humeral head, bone tumours, labral tears, and rotator cuff tears [55]. T1-weighted MRI can reveal Hill-Sachs lesions and is often used with MR arthrograms to provide a more detailed picture of joint surfaces [61]. T2-weighted MRI provides better visualization of full-thickness rotator cuff tears [61]. The accuracy for identifying labral and rotator cuff tears is enhanced by combining the scan with arthrography [55]. In a meta-analysis, MR arthrography (MRA) had greater diagnostic test accuracy for detecting glenoid labral lesions than MRI, with MRA sensitivity of 88% and specificity of 93% versus MRI sensitivity of 76% and specificity of 87% [59]. MRA is considered the benchmark for evaluation of labral tears and is rarely indicated for rotator cuff pathology [61]. Abduction and external rotation (ABER) of the arm is an alternative position utilized to increase sensitivity and specificity for detecting anteroinferior labroligamentous injury [59]. Full routine MRI or MRA examination had similar accuracy as the ABER sequence in evaluating the anteroinferior labral–ligamentous complex [59]. The sensitivity of MRA with the ABER position for detecting anteroinferior labral lesions was significantly higher than that of MRA in the neutral position [59]. MRAs can demonstrate a patulous capsule on coronal, sagittal, and axial imaging in patients with multidirectional instability [59]. MRAs can be helpful in evaluating lesions of the rotator interval and other associated findings that may affect the surgical plan [59]. The presence of glenoid dysplasia, increased capsular cross-sectional area, and increased glenoid retroversion have been found to be associated with increased posterior labral tears and symptomatic instability [59]. Glenoid retroversion was significantly increased in patients with symptomatic posterior labral tears, but there was no significant association between instability and increased humeral head subluxation [59]. The diagnosis of multidirectional instability is a clinical one, and the need for expensive and/or invasive imaging should be weighed against the information gained [59]. MRI has a sensitivity of 100%, specificity of 68%, positive predictive value of 85%, negative predictive value of 100%, and accuracy of 89% for the detection of full-thickness rotator cuff tears [62].
CT: CT scans may offer a few degrees of increased precision in the measurement of glenoid version, but this precision does not necessarily improve the quality of the surgery or the clinical outcome [31]. CT is helpful for planning fracture surgery and shoulder joint replacement [55]. CT with three-dimensional reconstructions is the advanced imaging study of choice for determining the extent of glenoid bone loss in the setting of shoulder instability [62]. When MRI or MR arthrography is contraindicated, CT arthrography is indicated [61]. Arthrography involves injection of contrast agent in conjunction with either an MRI or CT scan, enhancing imaging of the joint to enable better identification of normal structures and pathology involving the joint surfaces [61].
Ultrasonography: Ultrasonography is a low-cost alternative to MRI and arthrography for evaluating both skeletal and soft-tissue structures of the shoulder [61]. It can provide immediate, real-time visualization of the rotator cuff, biceps tendon, and calcific deposits [61]. It can be used to measure the subacromial space and detect atrophy of rotator cuff muscles [61]. It can evaluate impingement in various positions and motions due to real-time imaging capabilities [61]. Ultrasonography is highly operator dependent and is not as useful for evaluating labral tears or rotator cuff tears that are very small or larger than 3 cm [61]. It has a sensitivity of 98%, specificity of 80%, positive predictive value of 90%, negative predictive value of 95%, and accuracy of 94% for the detection of full-thickness rotator cuff tears [62].
Arthroscopy: Arthroscopy is useful for diagnosing and treating subacromial impingement, intra-articular lesions, detachment of the glenoid labrum, and rotator cuff tears [55].
Other Considerations: Bilateral os acromiale was found in only two cases (15.4%) in the Korean patient study [14]. The prevalence of os acromiale in the Korean study population was very low (less than 1%) as compared with other ethnic groups [14]. Black people consistently showed a higher prevalence of os acromiale (13.2%-18.2%) than white people (5.8%-9.5%), indicating genetic influences in the formation of os acromiale [14].
Treatment
Non-Operative Management
For symptomatic os acromiale, management is initially nonsurgical [2].
Operative Management
Other Considerations: Meta–os acromiale is the rarest subtype of os acromiale, and special consideration must be given to the type of tension-band construct used to achieve adequate compression and fixation [32].
Complications
Other Considerations: Postoperative local tenderness at the os acromiale is expected in 1 out of 4 patients following reverse total shoulder arthroplasty [7]. This tenderness resolves spontaneously over time in the majority of patients [7]. Internal fixation of symptomatic os acromiale is associated with relatively minor complications [36].
Recovery
Other Considerations: Postoperative local tenderness at the os acromiale can be expected in 1 out of 4 patients after reverse total shoulder arthroplasty but resolves spontaneously over time in the majority of patients [7].
Key Evidence
- [L4] The majority of os acromiale is asymptomatic and requires no treatment. [1] (10.2147/orr.s141480)
- [L5] For the symptomatic os acromiale, management is initially nonsurgical. [2] (10.5435/00124635-200601000-00004)
- [L4] The diagnosis of os acromiale should be based on imaging features and not limited by age. [3] (10.1007/s00256-015-2098-4)
- [L4] Os acromiale is a co-condition in patients with rotator cuff tear. [4] (10.1080/00016470510030643)
- [L4] Operative management of a symptomatic os acromiale that has failed initial nonoperative treatment leads to decreased symptoms and improvement in clinical outcomes. [5] (10.1016/j.jse.2019.05.047)
- [L4] Surgical management of symptomatic os acromiale that has failed nonoperative measures may predictably lead to improved outcomes. [6] (10.4103/0973-6042.80461)
- [L3] Postoperative local tenderness at the os acromiale can be expected in 1 out of 4 patients but resolves spontaneously over time in the majority of patients. [7] (10.1177/2325967120965131)
- [L4] The presence of os acromiale does not appear to have a negative impact on the clinical outcomes after surgery and rTSA remains a safe and effective treatment option. [8] (10.1016/j.xrrt.2025.01.002)
- [L4] This technique is a predictable and consistent treatment for symptomatic os acromiale in this population. [9] (10.1016/j.jse.2005.09.019)
- [L3] The study supports previous findings that os acromiale is associated with rotator cuff injuries. [10] (10.1016/j.jseint.2025.05.015)
- [L3] This multicenter study aimed to determine the prevalence of and factors associated with os acromiale in the Japanese population. [11] (10.1016/j.jse.2025.01.008)
- [L3] Shoulders with os acromiale had a similar overall complication rate compared with matched controls (14% vs. 12%; P = 0.658). [12] (10.5435/jaaos-d-25-00614)
- [L3] There was no relation between the presence of os acromiale and shoulder pain, regardless of diagnosis. [13] (10.1177/23259671221078806)
- [L4] [14] (10.4055/cios.2013.5.3.202)
- [L4] A tear of the rotator cuff may often be associated with os acromiale, likely due to impingement from abnormal motion at the fibrous union site. [15] (10.2106/00004623-198466080-00029)
- [L4] Surgical treatment of symptomatic meso-os acromiale with concomitant rotator cuff pathology yielded poorer outcomes than previously reported, with only 53% achieving satisfactory results overall. [16] (10.1016/j.jse.2005.08.024)
- [L4] The outcome of RTSA does not seem to be negatively affected by the presence of an os acromiale. [17] (10.1016/j.jse.2017.02.012)
- [L5] Surgical options for symptomatic os acromiale include arthroscopic sub-total excision, arthroscopic subacromial decompression of stable fragments, and open reduction and internal fixation of unstable fragments. [18] (10.5435/jaaos-d-17-00011)
- [L4] The overall frequency of os acromiale in the sample of 1594 skeletons was 8.34%. [19] (10.1002/oa.877)
- [L4] Surgical treatment is usually not indicated for os acromiale in the professional tennis player. [20] (10.1177/2325967118773723)
- [L4] Care should be taken not to perform acromioplasty in the presence of painful os acromiale. [21] (10.1016/j.otsr.2012.10.020)
- [L5] An os acromiale should be included in the differential diagnosis of the swimming athlete who presents with shoulder pain, particularly in the setting of a failed response to physical therapy, activity modification, or steroid injection. [23] (10.1177/1941738108326705)
- [L4] Ipsilateral os acromiale may be a relative contraindication to the clavicle hook plate. [24] (10.1186/s12891-021-04841-1)
- [L4] Awareness of the os acromiale in the young athlete, appropriate clinical examination, and image studies are crucial to confirm diagnosis. [26] (10.1016/j.jseint.2020.02.008)
- [Paper] Osteosynthesis to achieve bony union is a safe, effective, and reliable technique for the treatment of large and unstable symptomatic os acromiale, though high-level studies are still needed to compare outcomes between different techniques. [27] (10.1016/j.eats.2017.03.025)
- [L4] [28] (10.1302/2058-5241.4.180100)
- [L4] Meta–os acromiale is the rarest subtype of os acromiale, and special consideration must be given to the type of tension-band construct used to achieve adequate compression and fixation. [32] (10.1177/03635465211028238)
- [L4] This case highlights that the synchondrosis of an os acromiale can be injured following trauma, though rarely, and emphasizes the need for appropriate radiographic investigation including axillary views and a flexible surgical approach. [33] (10.1016/j.jse.2008.02.012)
- [L4] The procedure eliminates pain, preserves both acromial length and deltoid origin, and is associated with relatively minor complications. [36] (10.1016/j.jse.2004.01.023)
- [Paper] [67] (10.1016/j.eats.2021.01.016)
See Also
- Rotator Cuff
- Subacromial Decompression
- Internal Fixation
- Total shoulder arthroplasty
- Fractures
- Shoulder Instability
References
[1] Optimal management of symptomatic os acromiale: current perspectives. Orthopedic Research and Reviews. 2018. DOI: 10.2147/orr.s141480
[2] Symptomatic Os Acromiale. Journal of the American Academy of Orthopaedic Surgeons. 2006. DOI: 10.5435/00124635-200601000-00004
[3] Differentiating os acromiale from normally developing acromial ossification centers using magnetic resonance imaging. Skeletal Radiology. 2015. DOI: 10.1007/s00256-015-2098-4
[4] Rotator cuff tears associated with os acromiale. Acta Orthopaedica. 2005. DOI: 10.1080/00016470510030643
[5] Os acromiale: systematic review of surgical outcomes. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2019.05.047
[6] Systematic review of the surgical treatment for symptomatic os acromiale. International Journal of Shoulder Surgery. 2011. DOI: 10.4103/0973-6042.80461
[7] Os Acromiale in Reverse Total Shoulder Arthroplasty: A Cohort Study. Orthopaedic Journal of Sports Medicine. 2020. DOI: 10.1177/2325967120965131
[8] Clinical implications of reverse total shoulder arthroplasty with an os acromiale: a systematic review. JSES Reviews, Reports, and Techniques. 2025. DOI: 10.1016/j.xrrt.2025.01.002
[9] Painful os acromiale (or unfused acromial apophysis) in athletes. Journal of Shoulder and Elbow Surgery. 2006. DOI: 10.1016/j.jse.2005.09.019
[10] Prevalence and factors associated with os acromiale: a multicenter study. JSES International. 2025. DOI: 10.1016/j.jseint.2025.05.015
[11] The prevalence and associated factors of os acromiale: a multicenter study. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2025.01.008
[12] The Influence of Os Acromiale on Patient Outcomes After Reverse Total Shoulder Arthroplasty: A Matched Cohort Study. Journal of the American Academy of Orthopaedic Surgeons. 2026. DOI: 10.5435/jaaos-d-25-00614
[13] Prevalence of Os Acromiale in Thai Patients With Shoulder Problems: A Magnetic Resonance Imaging Study. Orthopaedic Journal of Sports Medicine. 2022. DOI: 10.1177/23259671221078806
[14] The Prevalence of Os Acromiale in Korean Patients Visiting Shoulder Clinic. Clinics in Orthopedic Surgery. 2013. DOI: 10.4055/cios.2013.5.3.202
[15] Rotator cuff tears associated with os acromiale.. The Journal of Bone & Joint Surgery. 1984. DOI: 10.2106/00004623-198466080-00029
[16] Surgical treatment of os acromiale with and without associated rotator cuff tears. Journal of Shoulder and Elbow Surgery. 2006. DOI: 10.1016/j.jse.2005.08.024
[17] Reverse shoulder arthroplasty in patients with os acromiale. Journal of Shoulder and Elbow Surgery. 2017. DOI: 10.1016/j.jse.2017.02.012
[18] Symptomatic, Unstable Os Acromiale. Journal of the American Academy of Orthopaedic Surgeons. 2018. DOI: 10.5435/jaaos-d-17-00011
[19] The frequency of os acromiale in the Robert J. Terry Collection. International Journal of Osteoarchaeology. 2006. DOI: 10.1002/oa.877
[20] Os Acromiale in Professional Tennis Players. Orthopaedic Journal of Sports Medicine. 2018. DOI: 10.1177/2325967118773723
[21] Os acromiale, a cause of shoulder pain, not to be overlooked. Orthopaedics & Traumatology: Surgery & Research. 2013. DOI: 10.1016/j.otsr.2012.10.020
[23] Os Acromiale as a Cause for Shoulder Pain in a Competitive Swimmer: A Case Report. Sports Health: A Multidisciplinary Approach. 2009. DOI: 10.1177/1941738108326705
[24] Os acromiale may be a contraindication of the clavicle hook plate: case reports and literature review. BMC Musculoskeletal Disorders. 2021. DOI: 10.1186/s12891-021-04841-1
[26] The unstable os acromiale: a cause of pain in the young athlete. JSES International. 2020. DOI: 10.1016/j.jseint.2020.02.008
[27] Operative Treatment of Symptomatic Meso‐Type Os Acromiale. Arthroscopy Techniques. 2017. DOI: 10.1016/j.eats.2017.03.025
[28] Os acromiale: a review of its incidence, pathophysiology, and clinical management. EFORT Open Reviews. 2019. DOI: 10.1302/2058-5241.4.180100
[31] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Radiographic Evaluation.
[32] Rare Symptomatic Meta–Os Acromiale in an Athlete. The American Journal of Sports Medicine. 2021. DOI: 10.1177/03635465211028238
[33] Fracture of an os acromiale with associated rupture of the coracoclavicular ligaments. Journal of Shoulder and Elbow Surgery. 2008. DOI: 10.1016/j.jse.2008.02.012
[36] Internal fixation of symptomatic os acromiale: a series of twenty-six cases. Journal of Shoulder and Elbow Surgery. 2004. DOI: 10.1016/j.jse.2004.01.023
[38] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > ANATOMY.
[41] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Shoulder, Arm, and Elbow > I. Shoulder.
[52] Miller S Review Of Orthopaedics. Genetics of musculoskeletal conditions and abnormalities are summarized in Table 1.27 > UPPER EXTREMITY > SHOULDER.
[55] Apley And Solomon S Concise System Of Orthopaedics And Trauma. INVESTIGATION.
[59] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Magnetic Resonance Imaging and Arthrography.
[61] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Shoulder Anatomy and Biomechanics, Clinical Evaluation, Imaging > Clinical Evaluation > Imaging.
[62] Aaos Comprehensive Orthopaedic Review 3. Imaging of the Shoulder and Elbow > I. Shoulder.
[64] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Radiography.
[65] Campbell S Operative Orthopaedics 4 Volume Set. ANTERIOR CRUCIATE LIGAMENT RECONSTRUCTION WITH BONE-PATELLAR TENDON-BONE GRAFT > Developmental Stages of Impingement Syndrome.
[66] Campbell S Operative Orthopaedics 4 Volume Set. ARTHROSCOPIC REPAIR OF POSTERIOR HUMERAL AVULSION OF THE GLENOHUMERAL LIGAMENT > SUBACROMIAL IMPINGEMENT SYNDROME.
[67] Arthroscopic “Wallow” Procedure for Resection of Symptomatic Os Acromiale Pseudoarthrosis. Arthroscopy Techniques. 2021. DOI: 10.1016/j.eats.2021.01.016