Patients › Rehabilitation
Giải ép dây thần kinh trên vai
Rehabilitation after isolated arthroscopic suprascapular nerve decompression, with honest framing of nerve recovery.
Quy trình này mô tả phương pháp phục hồi chức năng sau ca phẫu thuật giải ép dây thần kinh trên vai bằng phương pháp nội soi do bác sĩ Kieran Hirpara thực hiện tại Bệnh viện tư nhân Mater Rockhampton: đó là việc giải phóng dây thần kinh tại chỗ lõm trên vai và/hoặc chỗ lõm xương vai – mà không có bất kỳ phẫu thuật sửa chữa nào khác. Vui lòng mang theo trang này hoặc bản PDF tương ứng trong lần trị liệu vật lý đầu tiên để quá trình phục hồi của bạn được thực hiện một cách nhất quán. Quá trình phục hồi sẽ được chuyên viên vật lý trị liệu điều chỉnh tùy theo tiến triển hồi phục của vai bạn qua các giai đoạn dưới đây.
Lưu ý quan trọng: vui lòng đọc kỹ trước. Thông thường, việc giải ép dây thần kinh trên vai được thực hiện đồng thời với phẫu thuật sửa chữa cơ chóp xoay. Quy trình này chỉ áp dụng cho trường hợp chỉ thực hiện giải ép dây thần kinh mà thôi. Nếu ca phẫu thuật của bạn còn bao gồm cả việc sửa chữa cơ chóp xoay, vui lòng tuân theo quy trình phục hồi sau phẫu thuật cơ chóp xoay: các gân vừa được sửa chữa sẽ khiến tốc độ hồi phục chậm lại, vì vậy quy trình đó có tính ưu tiên cao hơn quy trình này. Nếu bạn không chắc chắn mình đã trải qua ca phẫu thuật nào, hãy liên hệ với phòng khám trước khi bắt đầu phục hồi.
Nếu có bất kỳ thắc mắc nào về vết mổ sau phẫu thuật, hãy liên lạc ngay với phòng khám. Việc chụp ảnh vết mổ rồi gửi qua email để được đánh giá cũng là một cách hữu ích.
Những điều có thể mong đợi
Khi dây thần kinh được giải phóng mà không cần sửa chữa gân nào, việc phục hồi chức năng có thể diễn ra nhanh chóng. Dây đeo vai chỉ được dùng để tạo cảm giác thoải mái và chỉ trong thời gian ngắn (thường là khoảng tuần đầu tiên, tối đa hai tuần); sau khi vai ổn định thì nên hạn chế đeo dây đeo này càng nhiều càng tốt. Các chuyển động nhẹ nhàng sẽ được bắt đầu sớm, khi bệnh nhân cảm thấy thoải mái; hầu hết mọi người đều có thể trở lại các hoạt động sinh hoạt hàng ngày trong vòng vài tuần.
Quá trình hồi phục của chính dây thần kinh diễn ra theo một tiến trình riêng, không phụ thuộc vào khả năng vận động của vai. Ca phẫu thuật giúp giảm áp lực lên dây thần kinh; cơn đau do áp lực này thường giảm đi tương đối nhanh. Việc phục hồi sức mạnh và khối lượng cơ ở các cơ do dây thần kinh này chi phối (cơ trên gai và cơ dưới gai nằm trên xương bả vai) diễn ra chậm hơn và mất nhiều tháng. Mức độ phục hồi sức mạnh và khối lượng cơ ở mỗi người là khác nhau: ở một số người là hoàn toàn, ở người khác chỉ là một phần; những trường hợp có vấn đề về dây thần kinh kéo dài có thể không hồi phục hoàn toàn. Chương trình vật lý trị liệu sẽ bao gồm các bài tập cụ thể nhằm kích hoạt lại các cơ này khi dây thần kinh dần hồi phục. Chuyên viên vật lý trị liệu cùng đội ngũ y tế sẽ hướng dẫn bạn về những gì có thể mong đợi trong trường hợp của mình.
Giai đoạn I — Vận động sớm (Tuần 0–2)

Kieran Hirpara 4.0
Mở và nắm tay
Hãy liên tục cử động tay và các ngón tay bằng cách mở ra, khép lại, hoặc nắm chặt một quả bóng mềm. Hãy thực hiện ngay từ bây giờ để duy trì hoạt động của tay trong lúc vai đang hồi phục.
Theo hướng dẫn của chuyên viên vật lý trị liệu của bạn.

Kieran Hirpara 4.0
Chuyển động cổ tay
Hãy cử động cổ tay bằng cách gập về phía trước, phía sau và sang hai bên. Thực hiện động tác này khi cánh tay đã được tháo ra khỏi nẹp treo cánh tay, đồng thời kết hợp với các chuyển động của bàn tay và khuỷu tay.
Theo hướng dẫn của chuyên viên vật lý trị liệu của bạn.

Kieran Hirpara 4.0
Bài tập đu đưa
Cúi người về phía trước, để cánh tay vừa được phẫu thuật buông thõng ra xa khỏi thân. Để cánh tay đung đưa theo những vòng tròn nhỏ, thả lỏng — chuyển động này xuất phát từ cơ thể chứ không phải từ các cơ vai. Chỉ thực hiện trong phạm vi vận động thoải mái và không gây đau đớn.
Theo hướng dẫn của chuyên viên vật lý trị liệu của bạn.

Kieran Hirpara 4.0
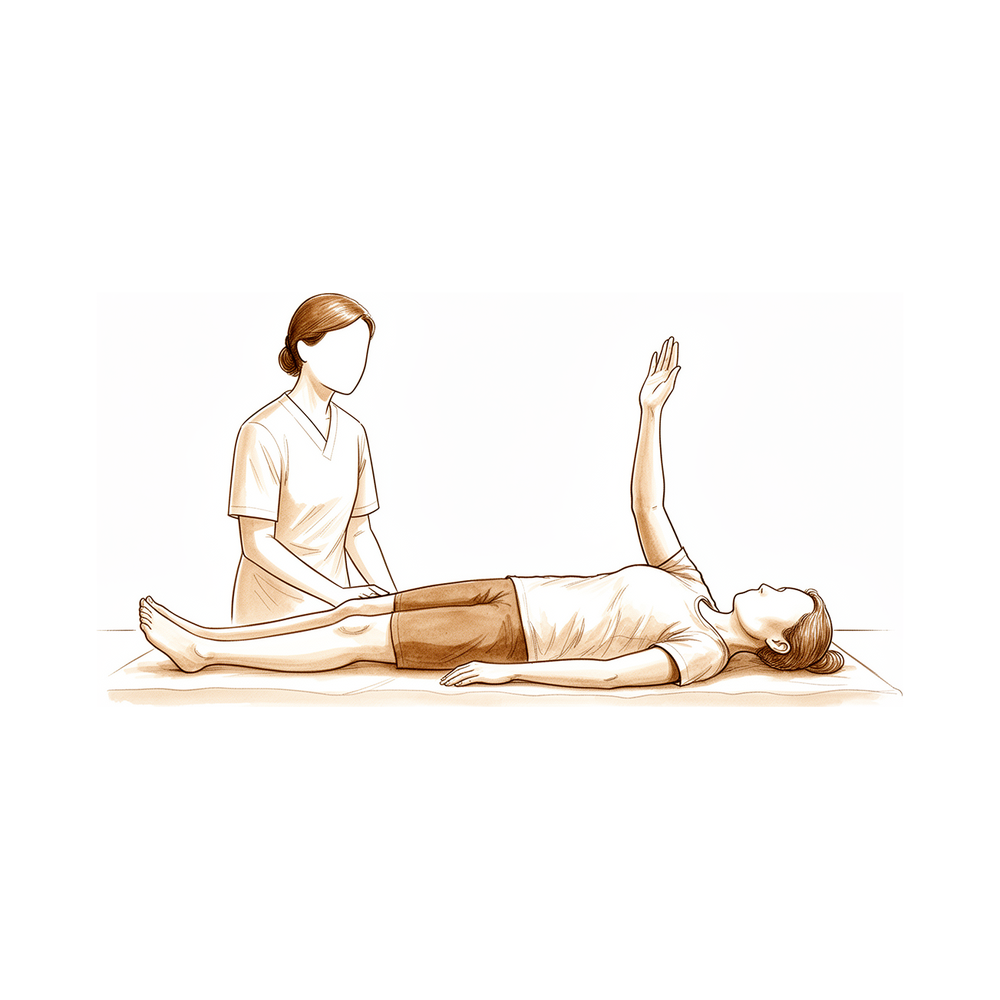
Nâng tay có hỗ trợ (khi nằm)
Nằm ngửa, dùng cánh tay lành để hỗ trợ nâng cánh tay vừa được phẫu thuật lên trên; sau đó hạ cánh tay xuống dưới cũng với sự hỗ trợ của cánh tay lành. Chỉ thực hiện các chuyển động trong phạm vi thoải mái, không gây đau đớn; mục tiêu là những động tác nhẹ nhàng và sớm, chứ không phải cố gắng mở rộng biên độ vận động hết mức có thể.
Theo hướng dẫn của chuyên viên vật lý trị liệu của bạn.

Kieran Hirpara 4.0
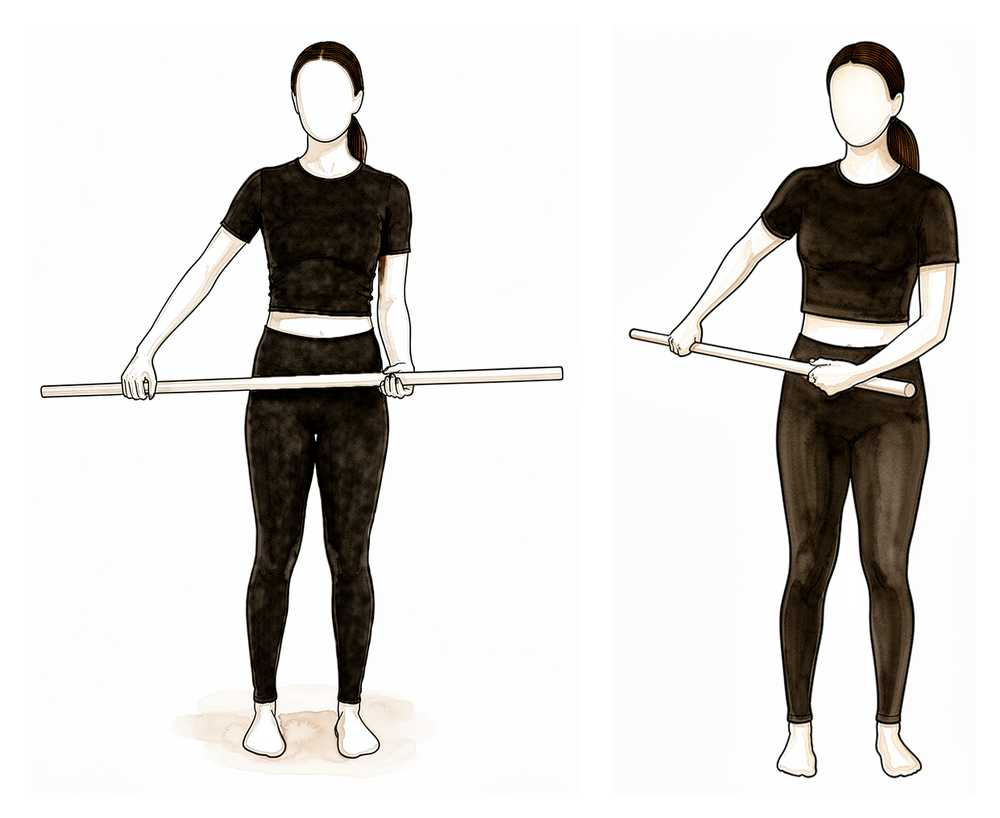
Phương pháp xoay ngoài có hỗ trợ bằng dụng cụ
Nằm ngửa, cầm một cây gậy hoặc chiếc gậy chống bằng cả hai tay; khuỷu tay gập thành góc vuông và sát vào hai bên thân. Dùng cánh tay lành để nhẹ nhàng đẩy cẳng tay vừa được phẫu thuật ra ngoài, xa khỏi cơ thể, sau đó đưa trở lại vị trí cũ. Hãy thực hiện động tác một cách thoải mái và không gây đau đớn.
Theo hướng dẫn của chuyên viên vật lý trị liệu của bạn.
Kieran Hirpara 4.0
Phương pháp xoay trong có hỗ trợ bằng dụng cụ
Hãy cầm một cây gậy phía sau lưng bằng cả hai tay. Dùng tay lành để nhẹ nhàng dẫn tay vừa được phẫu thuật lên phía sau lưng, rồi từ từ hạ nó xuống. Thao tác này giúp khôi phục lại khả năng xoay vào trong của tay một cách dễ chịu; hãy thực hiện trong phạm vi không gây đau đớn.
Theo hướng dẫn của chuyên viên vật lý trị liệu của bạn.

Kieran Hirpara 4.0
Cử động gập khuỷu tay
Gập và duỗi khuỷu tay trong toàn bộ phạm vi chuyển động. Ngay từ đầu, hãy vận động tay, cổ tay và khuỷu tay để phần còn lại của cánh tay vẫn giữ được độ mềm dẻo trong lúc vai dần ổn định.
Theo hướng dẫn của chuyên viên vật lý trị liệu của bạn.

Kieran Hirpara 4.0
Cách đặt xương bả vai
Dù ngồi hay đứng thẳng, hãy nhẹ nhàng kéo hai bả vai lại gần nhau và hạ xuống, tránh xa hai tai. Giữ nguyên tư thế vài giây rồi thả lỏng. Trong những ngày đầu, hãy thực hiện động tác này tùy theo mức độ thoải mái của bạn.
Theo hướng dẫn của chuyên viên vật lý trị liệu của bạn.
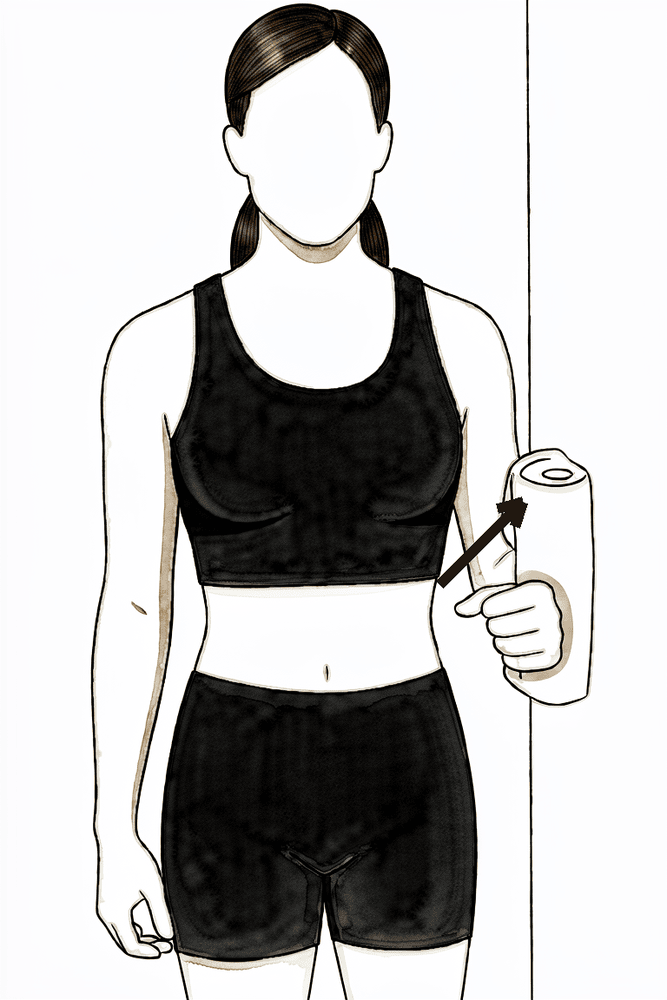
Kieran Hirpara 4.0
Căng cơ deltoid theo kiểu đẳng tĩnh
Đứng nghiêng người so với bức tường, sao cho khuỷu tay vừa phẫu thuật nằm sát bên hông. Nhẹ nhàng ấn phía ngoài cánh tay vào tường, như thể muốn đưa cánh tay ra ngoài, nhưng không để cánh tay thực sự di chuyển. Giữ nguyên tư thế vài giây rồi thả lỏng. Cách này sẽ kích hoạt cơ delta một cách nhẹ nhàng mà không gây ra bất kỳ chuyển động nào, tùy theo mức độ thoải mái của bạn.
Theo hướng dẫn của chuyên viên vật lý trị liệu của bạn.
Mục tiêu đầu tiên là đảm bảo sự thoải mái và khuyến khích vận động nhẹ nhàng, sớm sau phẫu thuật. Dây đeo vai chỉ dùng để tăng cảm giác thoải mái; sau khi vai ổn định, bạn nên tháo dây đeo ra càng nhiều càng tốt; bạn không cần phải đeo dây đeo khi ngủ. Sau bất kỳ ca phẫu thuật vai nào, bạn không được lái xe trong ít nhất sáu tuần, ngay cả khi đã tháo dây đeo; bác sĩ phẫu thuật sẽ cho phép bạn lái xe trở lại, thường là trong buổi tái khám vào tuần thứ sáu. Trong những ngày đầu, hãy uống thuốc giảm đau đều đặn để có thể bắt đầu vận động cánh tay. Ngay từ đầu, hãy vận động tay, cổ tay và khuỷu tay; đồng thời bắt đầu các động tác nhẹ nhàng ở vai trong phạm vi mà bạn cảm thấy thoải mái theo hướng dẫn.
Dành cho chuyên viên vật lý trị liệu:
Mục tiêu
- Đảm bảo sự thoải mái và bảo vệ vết mổ
- Vận động nhẹ nhàng, sớm trong phạm vi không gây đau
- Duy trì vận động ở tay, cổ tay và khuỷu tay
Cách xử lý
- Dùng dây đeo vai chỉ để tăng cảm giác thoải mái; thường dùng đến khoảng ngày thứ 7 sau phẫu thuật (tối đa hai tuần nếu cần thiết), sau đó giảm dần tùy theo tình trạng bệnh nhân
- Vận động nhẹ nhàng sớm khi bệnh nhân cảm thấy thoải mái: các động tác đung đưa cánh tay, nâng cánh tay chủ động hoặc hỗ trợ chủ động, xoay vai ra ngoài và vào trong, gập/duỗi khuỷu tay
- Thực hiện các động tác co cơ hình khối delta và cơ vùng vai theo khả năng chịu đựng của bệnh nhân
- Dùng thuốc giảm đau trước khi tập luyện; chườm lạnh để giảm đau khi cần thiết
Lưu ý phòng ngừa
- Chỉ thực hiện các động tác vận động trong phạm vi thoải mái, không gây đau
- Không nâng vật nặng, không đẩy hoặc kéo mạnh
- Không lái xe trong sáu tuần (quy định này áp dụng cho mọi ca phẫu thuật vai)
Tiêu chí để chuyển sang giai đoạn tiếp theo
- Cơn đau giảm dần và bệnh nhân cảm thấy thoải mái
- Vết mổ lành tốt
- Bệnh nhân chịu đựng được các động tác vận động sớm
Giai đoạn II — Phục hồi vận động và kích hoạt cơ (Tuần 2–6)
Kieran Hirpara 4.0
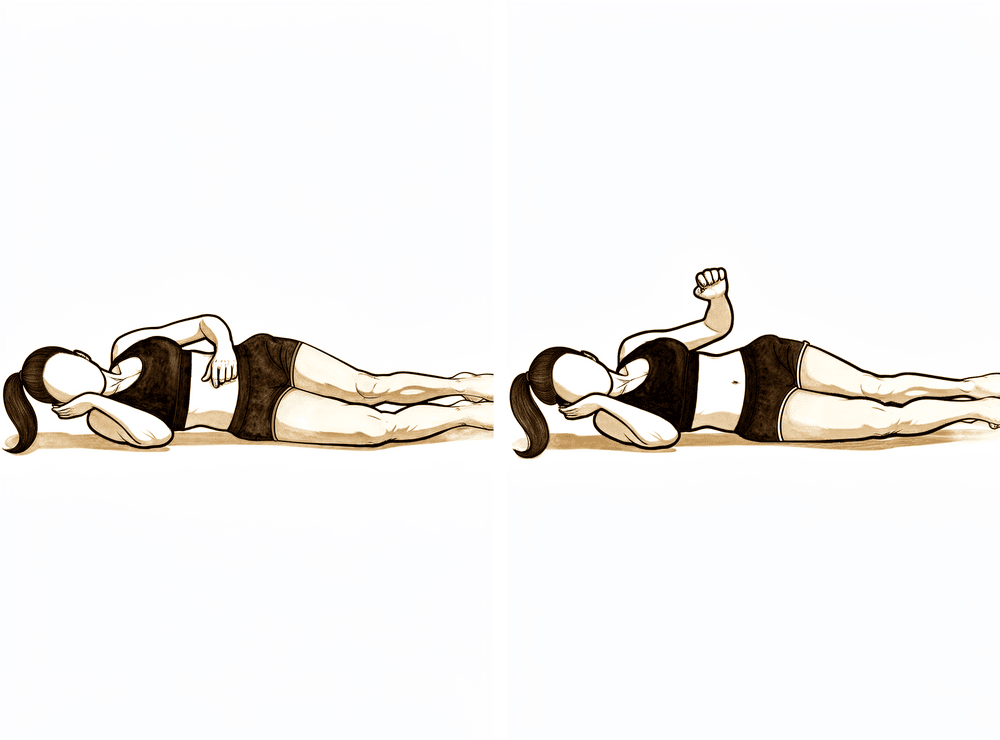
Tư thế nằm nghiêng với xoay ngoài
Nằm nghiêng về phía không phải vùng phẫu thuật, khuỷu tay phía trên gập thành góc vuông và áp sát vào thân mình. Giữ nguyên vị trí khuỷu tay sát người, xoay cẳng tay hướng lên trần nhà rồi từ từ hạ xuống một cách có kiểm soát. Việc thực hiện động tác xoay ngoài cánh tay mà không gây đau đớn như vậy sẽ giúp tái kích hoạt các cơ mà dây thần kinh chi phối.
Theo hướng dẫn của chuyên viên vật lý trị liệu của bạn.
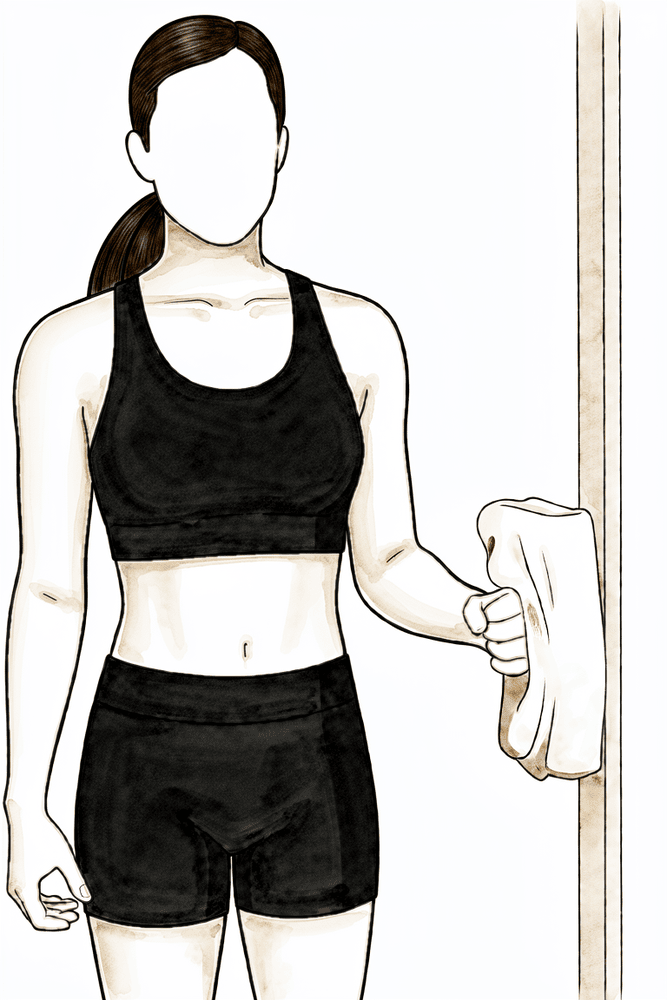
Kieran Hirpara 4.0
Xoay ngoài đẳng trường
Đứng thẳng, khuỷu tay áp sát vào hông và gập thành góc vuông; mu bàn tay chạm vào tường hoặc khung cửa. Nhẹ nhàng đẩy tay ra phía ngoài mà không để cánh tay di chuyển, giữ nguyên tư thế vài giây rồi thả lỏng. Đây là bước khởi đầu để kích hoạt lại các cơ mà dây thần kinh chi phối, trước khi sử dụng dây chun tập luyện.
Theo hướng dẫn của chuyên viên vật lý trị liệu của bạn.

Kieran Hirpara 4.0
Xoay ngoài với dây thun
Đứng thẳng, khuỷu tay áp sát vào hông và gập thành góc vuông; cầm một dây đàn hồi được cố định ở độ cao vòng eo. Giữ nguyên khuỷu tay sát hông, xoay cẳng tay ra ngoài chống lại sức căng của dây đàn hồi, sau đó từ từ quay trở lại vị trí ban đầu. Sử dụng lực cản thấp và thực hiện nhiều lần — đây là bài tập xoay ngoài quan trọng nhằm kích hoạt lại cơ infraspinatus khi dây thần kinh đang hồi phục.
Tải trọng thấp, số lần lặp lại nhiều hơn; theo hướng dẫn của chuyên viên vật lý trị liệu.
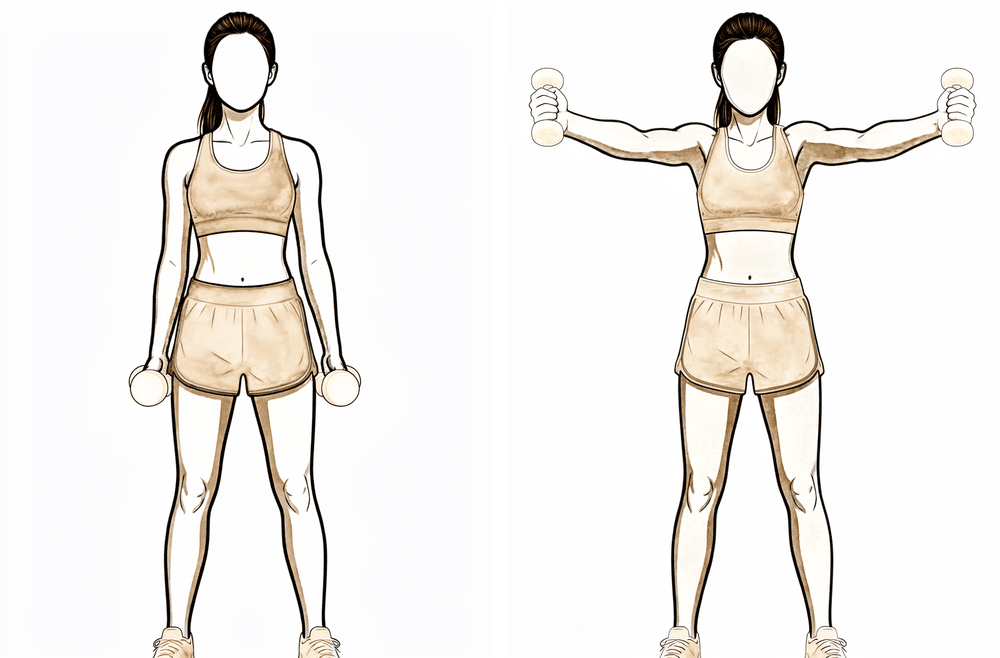
Kieran Hirpara 4.0
Động tác nâng cánh tay kiểu full-can
Đứng thẳng, giơ cánh tay vừa được phẫu thuật ra phía trước và hơi sang một bên, ngón cái hướng lên trên như thể đang cầm một chiếc lon đầy, nâng lên đến độ cao vai rồi hạ xuống một cách từ từ và có kiểm soát. Bài tập này nhắm vào cơ trên gai – một trong những cơ được dây thần kinh chi phối – và được thực hiện với tốc độ phù hợp với quá trình hồi phục của cơ, không được thực hiện một cách gượng ép.
Tải trọng thấp, số lần lặp lại nhiều hơn; theo hướng dẫn của chuyên viên vật lý trị liệu.
Sau khi tháo nẹp treo cánh tay, giai đoạn này nhằm khôi phục hoàn toàn khả năng vận động và bắt đầu các bài tập tăng cường sức mạnh nhẹ; trong đó có các bài tập đặc hiệu nhằm kích hoạt lại cơ trên gai và cơ dưới gai khi dây thần kinh dần hồi phục. Hầu hết bệnh nhân có thể trở lại các hoạt động sinh hoạt hàng ngày trong giai đoạn này. Tiến độ phục hồi được xác định dựa trên mức độ thoải mái của người bệnh, chứ không phụ thuộc vào thời gian.
Dành cho chuyên viên vật lý trị liệu:
Mục tiêu
- Khôi phục hoàn toàn phạm vi vận động chủ động ở mọi hướng
- Bắt đầu các bài tập tăng cường sức mạnh nhẹ và kích hoạt lại cơ vùng vai (cơ trên gai và cơ dưới gai)
- Bệnh nhân có thể tự thực hiện các hoạt động sinh hoạt hàng ngày một cách độc lập
Cách thức thực hiện
- Dần dần đạt được phạm vi vận động chủ động đầy đủ ở mọi hướng
- Từ khoảng tuần thứ 2, bắt đầu các bài tập tăng cường sức mạnh nhẹ: từ các bài tập co cứng cơ không vận động tiến dần sang sử dụng dây thun để tập cho cơ vùng vai, cơ delta và các cơ ổn định xương bả vai; áp dụng tải trọng thấp nhưng số lần lặp lại nhiều
- Đặc biệt chú ý đến việc thực hiện động tác xoay ngoài cánh tay mà không gây đau, đồng thời kích hoạt lại cơ trên gai và cơ dưới gai khi dây thần kinh hồi phục
- Dần dần trở lại các hoạt động sinh hoạt hàng ngày; thường là sau khoảng bốn tuần
Lưu ý phòng ngừa
- Các bài tập tăng cường sức mạnh chỉ nên thực hiện ở mức độ thoải mái; không được gây ra cơn đau kéo dài
- Tránh các động tác đẩy mạnh, kéo mạnh hoặc nâng vật nặng cho đến khi sức mạnh cơ bắp hồi phục hoàn toàn
- Cần hiểu rằng sức mạnh cơ bắp sẽ phục hồi từ từ; các bài tập kích hoạt cơ được điều chỉnh phù hợp với tốc độ hồi phục của dây thần kinh, chứ không nên ép buộc
Tiêu chí để chuyển sang giai đoạn tiếp theo
- Phạm vi vận động chủ động đầy đủ hoặc gần như đầy đủ, không gây đau
- Có thể thực hiện các bài tập tăng cường sức mạnh nhẹ mà không gây đau tái phát
Giai đoạn III — Tăng cường sức mạnh và trở lại các hoạt động bình thường (Tuần 6–12 trở đi)

Kieran Hirpara 4.0
Tư thế nằm nghiêng, xoay ngoài cánh tay có tải trọng
Kể từ khoảng tuần thứ 12, bệnh nhân thực hiện động tác xoay cánh tay ở tư thế nằm nghiêng tương tự, nhưng lần này cầm một quả tạ nhẹ: khuỷu tay gập thành góc vuông và áp sát vào thân, sau đó xoay cẳng tay hướng lên trần nhà rồi hạ xuống từ từ. Động tác này giúp tập trung kích hoạt các cơ mà dây thần kinh chi phối trong quá trình hồi phục; tiến độ thực hiện phải phù hợp với khả năng phục hồi của dây thần kinh, không được ép buộc.
Theo hướng dẫn của chuyên viên vật lý trị liệu của bạn.
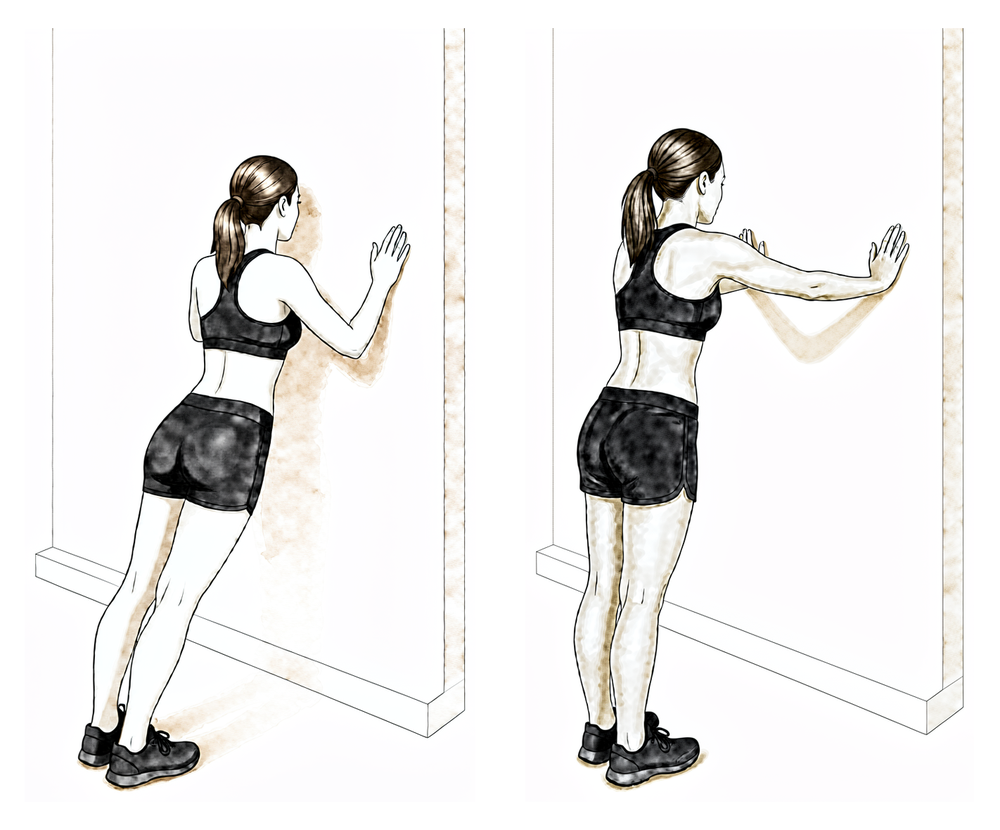
Kieran Hirpara 4.0
Chống đẩy plus (đẩy thêm để tách bả vai)
Kể từ khoảng tuần thứ sáu, khi thực hiện động tác hít đất dựa vào tường, ghế hoặc sàn nhà (dần dần tăng độ khó), hãy đẩy người lên hết mức rồi tiếp tục đẩy thêm một chút nữa sao cho vùng lưng trên cong lại và hai bả vai tách rời ra. Đây là bài tập chuỗi khép, giúp cải thiện khả năng kiểm soát các bả vai nhằm hỗ trợ cơ vùng vai.
Theo hướng dẫn của chuyên viên vật lý trị liệu của bạn.
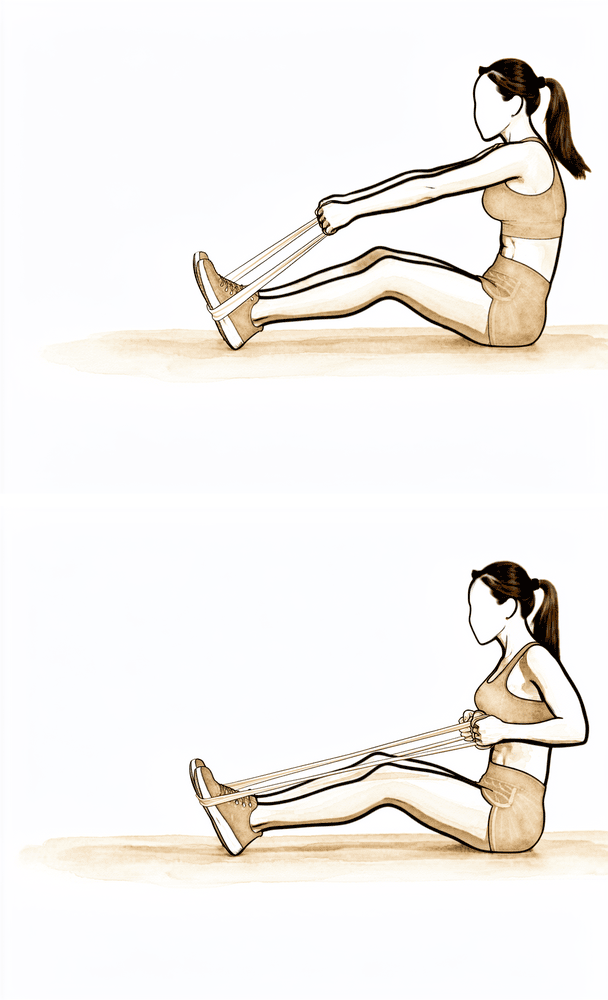
Kieran Hirpara 4.0
Tập kéo dây ở mức thấp
Giữ sợi dây đàn hồi được cố định ở phía trước người, ngang tầm eo. Giữ cánh tay gần như thẳng, kéo nó ra phía sau và xuống hướng hông, đồng thời siết xương bả vai xuống dưới và về phía sau; sau đó từ từ đưa tay về vị trí ban đầu. Đây là bài tập kháng lực tăng dần giúp phát triển các cơ bả vai hỗ trợ cho cơ vùng vai.
Theo hướng dẫn của chuyên viên vật lý trị liệu của bạn.
Khoảng từ tuần thứ 6 trở đi, việc tăng cường sức mạnh có thể tiến hành mà không có hạn chế cụ thể, nhằm hướng tới việc trở lại các hoạt động cần nâng tay lên cao, các công việc nặng và các môn thể thao. Việc tập luyện riêng cho cơ trên gai và cơ dưới gai cũng được tăng cường dần khi dây thần kinh tiếp tục hồi phục; quá trình này thường kéo dài vài tháng.
Dành cho chuyên viên vật lý trị liệu:
Mục tiêu
- Tăng cường sức mạnh toàn diện mà không có hạn chế
- Trở lại từ từ các hoạt động cần nâng tay lên cao, các công việc nặng và các môn thể thao
- Tiếp tục phục hồi sức mạnh của cơ vùng vai khi dây thần kinh hồi phục
Cách thức thực hiện
- Từ khoảng tuần thứ 6, bắt đầu các bài tập tăng cường sức mạnh toàn diện, bao gồm cả các bài tập kháng lực tiến triển và các bài tập dạng vòng khép kín
- Từ khoảng tuần thứ 12, tăng cường các bài tập riêng cho cơ trên gai và cơ dưới gai
- Điều chỉnh tiến độ trở lại các hoạt động cần nâng tay lên cao và các môn thể thao; các công việc nhẹ cần nâng tay lên cao thường có thể trở lại trong giai đoạn này; sau đó dần dần trở lại các môn thể thao trong những tuần đến những tháng tiếp theo tùy theo mức độ sức mạnh và khi không còn đau
- Tiếp tục duy trì chương trình tập luyện để hỗ trợ quá trình hồi phục của dây thần kinh và cơ bắp
Lưu ý phòng ngừa
- Việc tăng cường sức mạnh phải dựa trên mức độ triệu chứng của người bệnh
- Sức mạnh và khối lượng cơ ở vùng bị tổn thương có thể tiếp tục phục hồi trong vài tháng; mức độ phục hồi có thể chỉ là một phần; vì vậy cần đặt kỳ vọng hợp lý và tránh gây quá tải cho cơ bắp khi sức mạnh chưa đầy đủ
Sau khi thực hiện theo phác đồ
Các giai đoạn nêu trên được điều chỉnh từ các bài báo kỹ thuật và nghiên cứu lâm sàng đã công bố về phương pháp giải ép dây thần kinh trên vai bằng nội soi. Các khoảng thời gian được đề cập chỉ mang tính chất tham khảo chứ không cố định; quá trình phục hồi của bạn sẽ được điều chỉnh riêng biệt bởi chuyên viên vật lý trị liệu, phối hợp cùng phòng khám, dựa trên mức độ hồi phục của vai và dây thần kinh. Trang này bổ trợ cho các hướng dẫn phục hồi chung từ phòng khám; vui lòng tham khảo mục kiểm soát cơn đau sau phẫu thuật và chăm sóc vết thương. Để biết thêm thông tin về ca phẫu thuật cũng như bệnh lý được điều trị, hãy xem mục giải ép dây thần kinh trên vai. Các bằng chứng khoa học hỗ trợ phác đồ này (các nghiên cứu về hiệu quả giảm đau và phục hồi sức mạnh sau giải ép dây thần kinh) được tóm tắt trong mục “Bằng chứng khoa học”, có sẵn dưới dạng tệp PDF ở đầu trang này.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Suprascapular Nerve Decompression — Post-operative Rehabilitation (Arthroscopic Release)
Topic scope: Post-operative rehabilitation after an isolated arthroscopic suprascapular nerve decompression / release — release of the nerve at the suprascapular notch (division of the transverse/superior scapular ligament) and/or the spinoglenoid notch, performed for nerve entrapment, often with excision of an associated paralabral / spinoglenoid ganglion cyst. This page covers the isolated decompression only; when the procedure is combined with a rotator cuff repair the slower, protected rotator-cuff-repair pathway takes precedence.
Defining principle of the rehab here: decompression relieves pressure on a nerve and creates no construct that needs months of protection — there is no tendon repair or capsular reconstruction to safeguard. So (like a debridement/decompression, and unlike a cuff repair or labral repair) this is an early-movement pathway: a short sling for comfort only (about the first week, two at most), early range of motion as comfort allows, and return to daily activities within a few weeks. The crucial separate timeline is the nerve itself: the compression pain often settles relatively quickly, but recovery of strength and bulk in the muscles the nerve supplies (supraspinatus and infraspinatus) is paced over weeks to months and is frequently only partial — functional recovery follows the nerve, not the calendar. The single branch point is whether a rotator cuff repair was also performed — if so, the recovery converts to the protected rotator-cuff-repair pathway.
The procedure
The suprascapular nerve can be entrapped at two fibro-osseous tunnels as it crosses the scapula: the suprascapular notch (under the superior transverse scapular ligament — entrapment here affects both supraspinatus and infraspinatus) and the spinoglenoid notch (under the spinoglenoid ligament — entrapment here is more selective for the infraspinatus). A paralabral ganglion cyst, often arising from a posterosuperior labral tear, is a common space-occupying cause at the spinoglenoid notch.
Arthroscopic decompression releases the offending ligament (and decompresses/excises any cyst); where the cyst arises from a labral tear, the labral source may be addressed at the same sitting. Because the operation removes a compressive lesion rather than creating a repair, there is no healing construct that dictates a protected immobilisation period — the rehab is governed by comfort and by the nerve's own recovery.
Evidence by theme
Pain relief is the most reliable benefit
Across cohorts and a systematic review, decompression gives good pain relief and functional improvement in the majority. In a retrospective series of 112 arthroscopic decompressions, VAS pain fell from a mean of 6.5 to 2.9 (p < 0.0001) at a mean follow-up of ~9 months, with no neurovascular injuries, infections or fractures [112-patient series, PMC6994808]. A 2018 systematic review of decompression outcomes reported broad improvements in patient-reported scores and high rates of return to sport/duty [systematic review, JSES 2018, DOI 10.1016/j.jse.2017.09.025]. A volleyball-player cohort and a spinoglenoid-notch technique series likewise report reliable return of arm function [Brzoska 2023; Plancher 2021]. Moderate (cohorts + SR of level III–IV studies).
Strength recovery follows the nerve — slower, and often incomplete
This is the key counselling point. The same 112-patient series showed measurable strength gains (supraspinatus 3.3 → 4.9; infraspinatus 3.3 → 4.8 on the 0–5 scale) but over months, not weeks [PMC6994808]. A systematic review of motor recovery after notch decompression found that full strength was NOT regained in the majority (~60%) of reported cases, and that established fatty (structural) muscle degeneration generally did not reverse — "patients should be informed about this" [motor-recovery SR, PubMed 32392599]. Open spinoglenoid-notch series report better external- rotation strength figures (e.g. ~66% regaining full ER strength) for cyst-related entrapment, where the lesion is discrete and recovery potential higher [open decompression, PubMed 23664748]. Earlier diagnosis and decompression, and a discrete compressive cause (cyst) rather than chronic idiopathic entrapment, predict more complete muscular recovery. Moderate–weak; consistent direction across studies.
Ganglion-cyst vs idiopathic entrapment
Cyst-related entrapment (a removable, space-occupying cause) tends to do well — decompression removes the cause and electrodiagnostic recovery of the nerve has been documented post- decompression [Feinberg 2019, Muscle Nerve]. Chronic idiopathic entrapment, longstanding denervation, and established fatty infiltration carry a more guarded prognosis for strength return. This distinction underlies the variable, partly-incomplete recovery seen in the pooled literature. Weak (case series / mechanistic).
The rehabilitation protocol itself is consensus/expert
The phased post-op programme below is drawn from published technique papers and patient-guidance protocols, not from a rehabilitation RCT — there is no trial defining the optimal post- decompression regimen. Phase timings are typical, not trial-derived. Weak/consensus.
Phased post-op timeline (isolated decompression — no cuff repair)
| Phase | Window | Sling | ROM / use | Strengthening | Notes |
|---|---|---|---|---|---|
| I — Early movement | Week 0–2 | Comfort only, ~first week (up to 2 wk), off ASAP; not worn to sleep | Early gentle ROM as comfort allows — pendulums, passive/active-assisted elevation, ER/IR, elbow flexion/extension; keep hand/wrist/elbow moving from day 1 | Isometric deltoid + scapular setting as comfortable | Settle post-op flare; no driving while in sling; no heavy lifting/forceful push-pull |
| II — Range & muscle reactivation | Week 2–6 | Off | Progress to full active ROM in all planes | Light strengthening from ~wk 2 (isometric → band), low-load/high-rep cuff, deltoid, scapular stabilisers; particular attention to pain-free ER and to reactivating supraspinatus/infraspinatus as the nerve recovers | Most return to normal daily activities (~wk 4); progress guided by comfort, not calendar |
| III — Strengthening / return | Week 6–12 and beyond | Off | Full ROM maintained | Full strengthening without restriction from ~wk 6; isolated supraspinatus/infraspinatus strengthening advanced from ~wk 12; staged return to overhead work and sport | Strength + muscle bulk may keep recovering over several months and may be only partial — pace expectations to the nerve |
Branch point — if a rotator cuff repair was also performed: recovery converts to the protected rotator-cuff-repair pathway (sling ~6 weeks, ROM restrictions, strengthening deferred). The surgeon confirms which pathway applies.
Key controversies / evidence quality
- Strength recovery is the honest weak point. Decompression reliably relieves pain but does not reliably restore full strength — a systematic review found ~60% of cases fell short of full strength recovery, and fatty muscle degeneration generally did not reverse [PubMed 32392599]. This is the single most important thing to counsel before surgery. Moderate (SR of level III–IV).
- Evidence is small cohorts and case series. The largest single series is ~112 patients; most are < 30; the systematic reviews pool level III–IV studies. There is no RCT for isolated decompression rehab, and no rehab trial at all. Weak overall evidence base — stated honestly.
- Indication / patient selection. When to decompress (especially for asymptomatic or mildly symptomatic cysts, or chronic idiopathic entrapment with established atrophy) remains debated — reflected in editorial commentary in the corpus ("should you have the nerve to do it?", Arthroscopy 2021, DOI 10.1016/j.arthro.2020.12.192). Consensus/expert.
- The rehab protocol is consensus, drawn from technique papers and surgeon patient-guidance documents rather than a rehab trial — phase timings are typical, not trial-derived.
Evidence-strength flags (summary)
- MODERATE (cohorts + SR): decompression relieves pain and improves function in the majority (112-patient series VAS 6.5→2.9; 2018 JSES SR; volleyball-player cohort).
- MODERATE–WEAK (SR of level III–IV): strength recovery is slower and often incomplete (~60% short of full strength; fatty degeneration usually does not reverse — motor-recovery SR).
- WEAK (case series / mechanistic): cyst-related entrapment outperforms chronic idiopathic entrapment; earlier decompression predicts fuller recovery; documented electrodiagnostic nerve recovery post-release.
- WEAK / CONSENSUS: the post-operative rehabilitation protocol itself (technique papers + surgeon patient-guidance; no defining rehab RCT).
Citations
RAG corpus (180,000+ Orthopaedic articles)
- Clinical outcomes of suprascapular nerve decompression. J Shoulder Elbow Surg. 2011. DOI: 10.1016/j.jse.2010.10.032
- Clinical outcomes of suprascapular nerve decompression: a systematic review. J Shoulder Elbow Surg. 2018. DOI: 10.1016/j.jse.2017.09.025
- Arthroscopic Decompression of the Suprascapular Nerve at the Spinoglenoid Notch and Suprascapular Notch Through the Subacromial Space. Arthroscopy. 2009. DOI: 10.1016/j.arthro.2008.10.024
- Arthroscopic suprascapular nerve decompression: indications and surgical technique. J Shoulder Elbow Surg. 2010. DOI: 10.1016/j.jse.2010.01.006
- Suprascapular neuropathy: what does the literature show? J Shoulder Elbow Surg. 2012. DOI: 10.1016/j.jse.2011.11.033
- The Evaluation and Management of Suprascapular Neuropathy. J Am Acad Orthop Surg. 2020. DOI: 10.5435/jaaos-d-19-00526
- Suprascapular Neuropathy. J Bone Joint Surg Am. 2010. DOI: 10.2106/jbjs.i.01743
- Outcomes of Arthroscopic Nerve Release in Patients Treated for Large or Massive Rotator Cuff Tears and Associated Suprascapular Neuropathy: A Prospective, Randomized, Double-Blinded Clinical Trial. Am J Sports Med. 2021. DOI: 10.1177/03635465211021834
- Editorial Commentary: Suprascapular Nerve Decompression Can Be Effective, But Should You Have the Nerve to Do It? Arthroscopy. 2021. DOI: 10.1016/j.arthro.2020.12.192
- Complete Fatty Infiltration of Intact Rotator Cuffs Caused by Suprascapular Neuropathy. Arthroscopy. 2014. DOI: 10.1016/j.arthro.2014.01.010
Literature (URLs)
- A retrospective review of 112 patients undergoing arthroscopic suprascapular nerve decompression (VAS 6.5→2.9; supraspinatus/infraspinatus strength gains; no neurovascular/infective/fracture complications). PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC6994808/
- Motor Recovery of the Suprascapular Nerve after Arthroscopic Decompression in the Scapular Notch — a Systematic Review (~60% do not regain full strength; fatty degeneration generally not reversed). PubMed. https://pubmed.ncbi.nlm.nih.gov/32392599/
- Suprascapular nerve entrapment isolated to the spinoglenoid notch: surgical technique and results of open decompression (~66% regained full ER strength). PubMed. https://pubmed.ncbi.nlm.nih.gov/23664748/
- Arthroscopic release of suprascapular nerve entrapment at the suprascapular notch: technique and preliminary results. PubMed. https://pubmed.ncbi.nlm.nih.gov/17210425/
- Compression of the suprascapular nerve by a ganglion cyst of the spinoglenoid notch: the arthroscopic solution. PubMed. https://pubmed.ncbi.nlm.nih.gov/14595536/
Published protocols / technique papers (basis for the phase structure)
- Plancher KD, Evely TB, Brite JE, Briggs KK, Petterson SC. Endoscopic/arthroscopic decompression of the suprascapular nerve at the spinoglenoid notch: indications and surgical technique. JSES Rev Rep Tech. 2021;1(3):198-206. https://www.sciencedirect.com/science/article/pii/S2666639121000250
- Harkin WE, Kerzner B, Scanaliato J, et al. Open Suprascapular Nerve Decompression at the Spinoglenoid Notch. Arthrosc Tech. 2024;13(9):103051. https://pmc.ncbi.nlm.nih.gov/articles/PMC11411363/
- Brzoska R, Laprus H, Klaptocz P, et al. Arm Function After Arthroscopic Decompression of the Suprascapular Nerve at the Spinoglenoid Notch and Suprascapular Notch in Volleyball Players. Orthop J Sports Med. 2023;11(2):23259671221147892. https://pmc.ncbi.nlm.nih.gov/articles/PMC9974621/
- Feinberg JH, Mehta P, Gulotta LV, et al. Electrodiagnostic evidence of suprascapular nerve recovery after decompression. Muscle Nerve. 2019;59(2):247-249. https://pubmed.ncbi.nlm.nih.gov/30291636/