Patients › Hand
U nang bao gân cơ gập
A benign, fluid-filled cyst arising from the flexor tendon sheath – often painless, but can cause clicking or limited finger movement.
Những triệu chứng bạn đang gặp
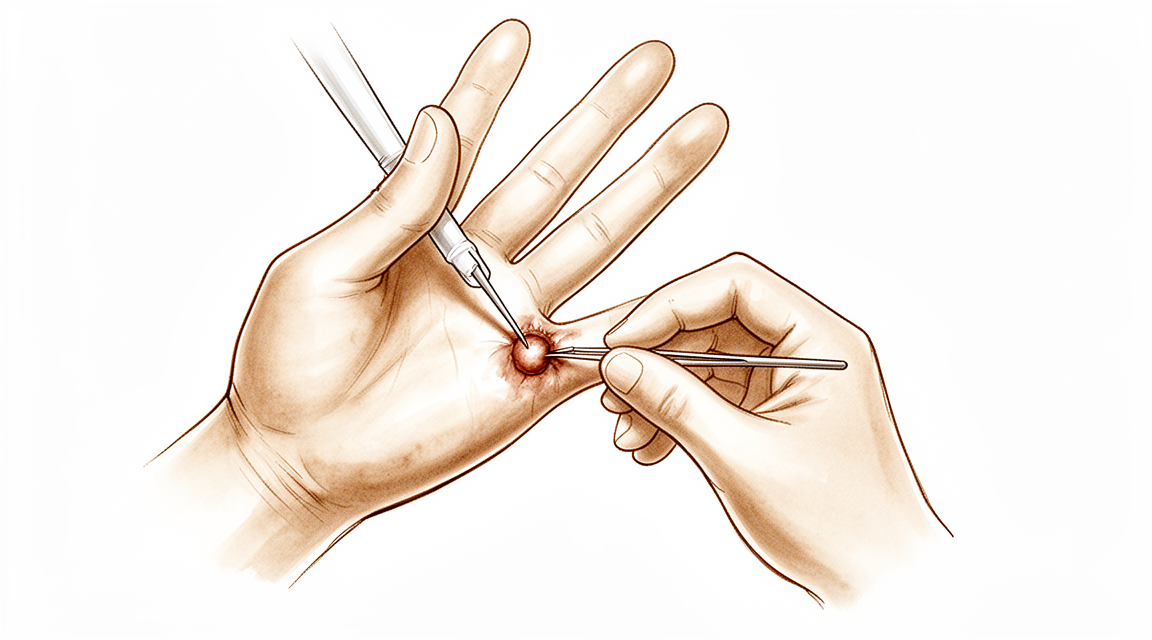
U nang bao gân gập là một khối u nhỏ, cứng ở gốc một ngón tay, trong lòng bàn tay. Khối u thường chỉ có kích thước vài milimét, nhưng có thể gây đau nhiều hơn bạn nghĩ đối với một thứ nhỏ như vậy. Cơn đau xuất hiện khi bạn nắm chặt một vật cứng và có thân hẹp, như vô lăng ô tô, gậy golf, tay lái xe đạp hoặc quai túi mua sắm. Khối u bị ép giữa vật đó và xương ngón tay, mà không có mô mềm nào làm đệm.
Cơn đau thường bùng lên trong hoặc sau những việc cầm nắm đó. Những việc như xách túi đồ nặng, cầm dụng cụ hay vắt quần áo giặt có thể trở nên khó chịu. Một số người nhận thấy cơn đau âm ỉ dịu đi khi họ buông vật đó ra. Bản thân khối u có tính chất cứng chứ không mềm, và nằm ngay tại chỗ các ngón tay gập vào lòng bàn tay.
Vì cơn đau gắn liền với việc cầm nắm, nó có thể bắt đầu hạn chế những việc bạn làm bằng bàn tay đó. Bạn có thể thấy mình tránh một số công việc, hoặc thay đổi cách cầm đồ vật để không đè lên chỗ đó.
Nếu ngón tay, bàn tay hoặc cánh tay của bạn trở nên nóng, đỏ, sưng và đau, đặc biệt là khi kèm theo sốt, hãy đến khoa cấp cứu để được chăm sóc ngay trong ngày. Bạn không cần giấy giới thiệu của bác sĩ đa khoa để đến đó.
Chuyện gì đang thực sự xảy ra
Ngón tay của bạn gập lại được là nhờ hai gân chạy từ cẳng tay, dọc theo mặt lòng của ngón tay, và bám vào xương ngón tay. Hãy hình dung chúng như những sợi dây thừng kéo lại khi bạn co ngón tay. Để giữ những sợi dây này sát vào xương thay vì bị cong vồng ra xa xương, chúng chạy bên trong một đường hầm được tạo bởi những dải mô dai gọi là ròng rọc. Đường hầm này được lót bởi một lớp mỏng, trơn giúp nuôi dưỡng gân và giúp gân trượt êm.
U nang bao gân gập là một túi nhỏ chứa dịch đặc, giống như thạch, lồi ra từ đường hầm đó. Túi được làm đầy bởi dịch từ chính lớp lót của bao gân, vì vậy nó hoạt động giống như một chỗ rò rỉ nhỏ có áp lực: hút hết dịch thì túi lại đầy trở lại, vì chỗ rò vẫn còn đó. Túi nằm ngay ở gốc ngón tay trong lòng bàn tay, nơi đường hầm bám chặt vào xương mà không có lớp đệm mềm nào phía trên. Đó là lý do tại sao một khối u chỉ vài milimét lại có thể gây đau nhiều đến vậy khi bạn nắm chặt: khối u bị kẹp giữa vật bạn đang cầm và xương bên dưới.
Chính vị trí này cũng giải thích những điều khác mà bạn có thể đã nhận thấy. Vì khối u chiếm chỗ bên trong một đường hầm hẹp, nó có thể chèn ép gân khi gân trượt qua, đó là lý do một số người có khối u ở vị trí này cũng bị vướng hoặc phát ra tiếng “click” ở ngón tay. Các dây thần kinh chi phối ngón tay chạy ngay cạnh bao gân, mỗi bên một dây, vì vậy khối u đè lên dây thần kinh có thể gây ngứa ran hoặc tê chứ không chỉ gây đau.
Bạn cũng nên biết rằng khối u ở đúng vị trí này cũng có thể do những nguyên nhân khác, chẳng hạn như gân bị vướng khi trượt, hoặc tình trạng dày lên của mô lòng bàn tay kéo ngón tay gập về phía lòng bàn tay. Bác sĩ phẫu thuật thường có thể phân biệt các tình trạng này bằng cách khám bàn tay, và mỗi tình trạng được điều trị theo cách khác nhau.
Những biện pháp chúng tôi có thể áp dụng
Bác sĩ Kieran Hirpara, bác sĩ phẫu thuật chi trên tại Bệnh viện Mater Private Rockhampton, sẽ bắt đầu bằng các phương pháp ít xâm lấn nhất phù hợp với tình trạng của bạn. Thông thường, bệnh nhân được bác sĩ đa khoa giới thiệu đến phòng khám chúng tôi; nếu nhà vật lý trị liệu khuyên bạn nên đến gặp chúng tôi, bạn vẫn cần có giấy giới thiệu từ bác sĩ đa khoa để được hưởng mức hoàn trả từ Medicare. Trong buổi khám, chúng tôi sẽ hỏi về tiền sử bệnh, khám bàn tay và chỉ định chụp hình như siêu âm nếu cần để xác nhận bản chất của khối u.
Vì khối u này lành tính và không tiếp tục lớn lên, việc điều trị hoàn toàn phụ thuộc vào mức độ nó làm bạn khó chịu. Một khối u bạn sờ thấy được nhưng không gây đau khi cầm nắm bình thường có thể không cần làm gì cả. Nếu một kiểu cầm nắm nào đó cứ gây đau, việc thay đổi cách cầm đồ vật hoặc tạm giảm bớt công việc đó một thời gian có thể là đủ. Trị liệu tay cũng có thể giúp bạn tìm cách sử dụng bàn tay sao cho ít đè ép lên chỗ đó hơn.
Hút dịch trong khối u bằng kim, gọi là chọc hút, thường được thử trước khi phẫu thuật. Thủ thuật này làm rỗng dịch trong túi, nhưng vì túi được bao gân cung cấp dịch nên nó thường đầy trở lại. Một số khối u cũng tự ổn định theo thời gian. Chúng tôi sẽ cùng bạn trao đổi xem có nên thử hút dịch trong trường hợp của bạn hay không.
Nếu các bước đơn giản này vẫn chưa giúp bạn đỡ đáng kể, phẫu thuật có thể được cân nhắc. Ca mổ cắt bỏ khối u qua một vết rạch nhỏ ở gốc ngón tay, cùng với mảnh nhỏ bao gân nơi khối u phát sinh, và chính điều này giúp khối u không tái phát. Chúng tôi thường đề nghị phẫu thuật khi một hoạt động cụ thể, lặp đi lặp lại trong sinh hoạt hằng ngày của bạn bị hạn chế do cơn đau, và chúng tôi cùng bạn đưa ra quyết định đó.
Nếu ngón tay, bàn tay hoặc cánh tay của bạn trở nên nóng, đỏ, sưng và đau, đặc biệt là khi kèm theo sốt, hãy đến khoa cấp cứu ngay trong ngày.
Những điều bạn có thể mong đợi
Hầu hết các u nang như thế này đều lành tính và không tiếp tục lớn lên. Một số tự ổn định theo thời gian, và một số cứ xuất hiện rồi biến mất. Nếu khối u của bạn không gây đau, có thể bạn sẽ không bao giờ cần điều trị.
Nếu khối u gây đau khi bạn cầm nắm, những bước đơn giản có thể giúp ích. Hút dịch bằng kim làm rỗng túi, nhưng vì túi được bao gân cung cấp dịch nên nó thường đầy trở lại. Thay đổi cách cầm đồ vật, hoặc giảm bớt công việc làm cơn đau bùng lên, có thể là đủ trong khi bạn chờ xem khối u có tự ổn định hay không.
Nếu các bước đó chưa giúp đủ, phẫu thuật sẽ cắt bỏ khối u cùng với mảnh nhỏ bao gân nơi khối u phát sinh, và chính điều này giúp khối u không tái phát. Hầu hết mọi người nhận thấy việc cầm nắm trở nên dễ chịu hơn khi chỗ đó không còn bị kẹp nữa. Như mọi ca mổ ở bàn tay, có những rủi ro cần cân nhắc, bao gồm một vùng tê dọc theo một bên ngón tay, cứng khớp, nhiễm trùng và sẹo dày hoặc đau. Bác sĩ phẫu thuật sẽ trao đổi kỹ những điều này với bạn trước khi bạn quyết định.
Quá trình hồi phục sau phẫu thuật tính bằng tuần chứ không phải bằng ngày. Ban đầu bàn tay của bạn sẽ đau, và vết rạch nhỏ ở gốc ngón tay sẽ cần thời gian để lành. Việc trị liệu tay sau phẫu thuật sẽ do Ruby Doolan tại Extend Rehabilitation thực hiện. Ruby là chuyên gia trị liệu tay; cô ấy sẽ hướng dẫn các bài tập và làm nẹp cho bạn nếu cần trong khi ngón tay lành lại. Hầu hết mọi người quay lại các công việc cầm nắm bình thường trong vòng vài tuần, dù cảm giác đau khi chạm vào vết sẹo có thể kéo dài lâu hơn một chút.
Nếu các triệu chứng không thuyên giảm, ngày càng nặng hơn qua nhiều tuần, khiến bạn thức giấc vào ban đêm, hoặc khiến bạn không thể làm việc hay sử dụng bàn tay, hãy đến gặp bác sĩ đa khoa hoặc đề nghị được bác sĩ chuyên khoa thăm khám.
Khi nào nên đi khám
Hầu hết các khối u ở gốc ngón tay là u nang lành tính, nhưng một vài tình trạng khác có thể trông giống hệt ở vị trí đó. Ngón tay bị kẹt hoặc phát ra tiếng “click” khi gập, hoặc một dải cứng trong lòng bàn tay kéo ngón tay gập về phía lòng bàn tay, là những tình trạng mà bác sĩ phẫu thuật có thể phân biệt bằng cách khám bàn tay. Bạn nên đi kiểm tra bất kỳ khối u mới nào để biết mình mắc tình trạng nào.
Hãy đề nghị được bác sĩ chuyên khoa thăm khám nếu khối u gây đau khi bạn cầm nắm, nếu bạn thấy ngứa ran hoặc tê ở ngón tay, hoặc nếu ngón tay bị vướng hoặc phát ra tiếng “click”. Bạn cũng nên đề nghị khám nếu các triệu chứng không thuyên giảm, ngày càng nặng hơn qua nhiều tuần, khiến bạn thức giấc vào ban đêm, hoặc khiến bạn không thể làm việc hay sử dụng bàn tay.
Nếu ngón tay, bàn tay hoặc cánh tay của bạn trở nên nóng, đỏ, sưng và đau, đặc biệt là khi kèm theo sốt, hãy đến khoa cấp cứu ngay trong ngày. Bạn không cần giấy giới thiệu của bác sĩ đa khoa để đến đó.
Phân tích chi tiết hơn
Advanced reading: the deeper science (optional)
Phần này đi sâu hơn so với những gì bạn cần biết để đưa ra quyết định điều trị. U nang bao gân gập ngón tay là một chủ đề đáng để tìm hiểu thêm, bởi đây là khối u nhỏ nhất trong phẫu thuật tay vẫn có thể gây ra các triệu chứng nghiêm trọng một cách không tương xứng; đồng thời, vị trí gắn kết của khối u này quyết định cả nguyên nhân gây đau lẫn lý do khiến các phương pháp điều trị đơn giản không mang lại hiệu quả.
Một khối u nhỏ bằng hạt đậu gây đau đớn một cách bất tương xứng
Những nang này, còn được gọi là nang retinacular hoặc nang gân vùng lòng bàn tay, hình thành từ lớp màng sợi nối các gân gấp với các xương ngón tay [1]. Chúng nằm ở gốc ngón tay, trong lòng bàn tay; thường chỉ có kích thước vài milimét và có tính chất cứng chứ không mềm.
Triệu chứng này rất đặc trưng và dễ hiểu nếu ta nắm rõ cấu trúc giải phẫu: cảm giác đau khi nắm chặt những vật cứng và hẹp như vô lăng ô tô, gậy golf, tay cầm xe đạp, hoặc quai túi mua sắm. Lúc này, nang bị kẹt giữa vật thể đó và xương phía dưới; do lớp màng sợi này dính trực tiếp vào xương ngón tay nên không có mô mềm nào để làm đệm cho nang.
Đó là lý do tại sao kích thước của nang hầu như không liên quan đến mức độ triệu chứng. Một khối u mềm, có kích thước lớn ở mặt sau cổ tay có thể không gây đau đớn; trong khi một khối u nhỏ hơn nhiều ở gốc ngón tay lại gây ra những hạn chế thực sự trong sinh hoạt.
Nguyên tắc vận hành cũng tương tự như các dạng u nang khác
Cách hoạt động của nó phụ thuộc vào những cấu trúc mà nó liên kết với. U nang này phát sinh từ màng bao gân và được làm đầy bởi dịch từ đó; vì vậy cơ chế vận hành của nó giống với u nang cổ tay và u nang nhầy: túi chứa dịch chỉ là biểu hiện bên ngoài của vấn đề chứ không phải nguyên nhân gốc rễ.
Do đó, việc chọc hút hoặc rút dịch chỉ giúp giảm sưng mà không giải quyết được nguyên nhân gây rò rỉ dịch. Tình trạng tái phát sau khi chỉ thực hiện thao tác dẫn lưu là rất phổ biến; phương pháp điều trị triệt để là cắt bỏ u nang cùng với đoạn màng bao gân bị ảnh hưởng nơi u nang phát sinh.
Tại sao ca phẫu thuật này có vẻ đơn giản hơn so với vẻ bề ngoài nhưng vẫn không hề dễ dàng
Thủ thuật cắt bỏ chỉ là một ca phẫu thuật ngắn gọn, thực hiện qua một vết mổ nhỏ ở gốc ngón tay; nhìn chung nó mang lại hiệu quả chữa trị tốt. Tuy nhiên, có hai đặc điểm giải phẫu khiến việc thực hiện ca phẫu thuật này cần được thực hiện một cách cẩn trọng.
Các dây thần kinh chi phối ngón tay chạy ngay cạnh bao gân gập, mỗi bên một dây; ở vùng gốc ngón tay, chúng nằm nông dưới da và gần các cấu trúc giữa ngón tay cần được loại bỏ. Việc xuất hiện vùng tê ở một bên mép ngón tay là một biến chứng thường gặp khi thực hiện ca phẫu thuật nhỏ ở vị trí này.
Thứ hai, chỉ phần bao gân thừa mới được phép cắt bỏ. Các cấu trúc gân nối giúp giữ các gân cơ sát với xương là những thành phần chịu lực quan trọng; nếu mất đi một cấu trúc quan trọng như vậy, gân cơ sẽ bị lệch ra khỏi vị trí bình thường, làm suy giảm khả năng nắm chặt. Vì vậy, thủ thuật cắt bỏ chỉ được giới hạn ở đoạn bao gân không còn chức năng hỗ trợ nữa.
Khi nào nên để nguyên không xử lý
Vì khối u này lành tính và không phát triển to ra theo thời gian, việc điều trị chỉ được quyết định dựa trên các triệu chứng. Nếu khối u có thể nhìn thấy được nhưng không gây đau đớn khi cầm nắm hàng ngày thì không cần can thiệp gì. Việc điều trị chỉ được thực hiện khi một hoạt động cụ thể và thường xuyên bị ảnh hưởng; đây là dấu hiệu rõ ràng hơn hầu hết các dấu hiệu khác, vì người bệnh thường dễ dàng xác định được kiểu cầm nắm gây ra triệu chứng.
Các khối u tương tự ở khớp đầu ngón tay và cổ tay sẽ được đề cập riêng trên các trang tương ứng; nguyên tắc chung cho cả ba trường hợp này là phần cuống của khối u, chứ không phải chính khối u, mới là yếu tố quyết định liệu bệnh có tái phát hay không.
Tài liệu tham khảo
[1] Foret AL, Chhabra AB. Các u nang vùng dây chằng mu bàn tay. Tạp chí Phẫu thuật Bàn tay Hoa Kỳ. 2012;37(3):566-7. https://doi.org/10.1016/j.jhsa.2011.05.013
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
Epidemiology and Natural History
- Pediatric ganglions are more commonly found on the volar surface of the hand and wrist compared to adults [7].
- Pediatric ganglions more commonly have a tendon sheath origin compared to adults [7].
- Approximately 40% of wrist ganglion lesions decrease over the first 6 years after evaluation by a hand surgeon [25].
Diagnosis
- Ultrasound is useful for assisting in the diagnosis of suspected flexor tendon sheath ganglions [1].
- Ultrasound is useful for determining whether patients with suspected flexor tendon sheath ganglions should undergo aspiration or surgical excision [1].
- Routine wrist radiography is not cost-effective in the evaluation and treatment decision-making process for patients with a wrist ganglion due to a low prevalence of therapeutically significant findings [21].
Non-Operative Management
- A nonsurgical approach to flexor tendon sheath ganglions is both cost-effective and successful [3].
- Most ganglions recur after aspiration [25].
- Percutaneous puncture is a practical option for managing flexor tendon sheath ganglions given its low cost, lack of downtime, and low recurrence rate [5].
- No recurrences were observed after a second puncture in the cohort assessed for percutaneous puncture of flexor sheath ganglions [5].
Operative Management
- Surgical excision is a simple, safe, and effective method for treating a painful ganglion of the digital flexor tendon sheath [2].
- Surgical intervention for wrist ganglions has about a 10% recurrence rate [25].
- Surgical intervention for wrist ganglions leaves scars and has some risk for adverse events [25].
- Ultrasound-guided excision of flexor tendon sheath ganglion using a 2-mm portal under local anaesthesia was reliable and efficient without specific morbidity [4].
- Endoscopic ganglionectomy via flexor carpi radialis tendoscopy is a minimally invasive approach that offers better cosmesis and less soft tissue trauma [9].
- Endoscopic ganglionectomy via flexor carpi radialis tendoscopy allows for the management of concomitant FCR tendon pathology [9].
- Endoscopic ganglionectomy via flexor carpi radialis tendoscopy carries risks of recurrence and nerve or vessel injury [9].
- Operation-related complications after arthroscopic volar wrist ganglionectomy are associated with the anatomical location of the ganglion being distal to the bifurcation of the radial artery and concurrently penetrated up to the superficial fascia layer [60].
Pediatric Management
- There is no consensus within the literature regarding the best management of pediatric wrist ganglia [22].
- No single treatment modality confers a particular advantage or disadvantage over another for pediatric wrist ganglia [22].
Anatomy & Pathophysiology
Flexor Tendon Sheath Anatomy
- The fibroosseous tunnel, or digital flexor sheath, extends distally from the metacarpal neck to the proximal aspect of the distal phalanx [75].
- The tendinous sheath consists of annular pulleys that provide mechanical stability and cruciate pulleys that provide flexibility [75].
- The A2 and A4 pulleys are situated over the middle portion of the proximal and middle phalanges, respectively [75].
- The A2 and A4 pulleys are the most essential in maintaining the mechanical advantage of the flexor tendons [75].
- The tenosynovium lining the fibroosseous tunnel supplies both nutrition and lubrication to the poorly vascularized flexor tendons [75].
- Within the sheath, tendon vascularity is supplied via the vincula system, specifically the vinculum longus and brevis [75].
- Anatomical studies have identified two annular and one oblique pulley in the thumb [91].
- A branch from the digital nerve enters the flexor tendon sheath at the same place as the transverse branch of the digital artery [8].
- The nerve branch entering the flexor tendon sheath supplies the nerve fibres found within the vinculum [8].
- The transverse branch of the digital artery enters the edge of the sheath to reach the area of the vinculum brevis [8].
Gliding Mechanisms and Biomechanics
- In narrow crowded areas, the gliding mechanism is assured by the synovial sheath, which allows a considerable amplitude of movement [76].
- Fibrous sheaths surrounding synovial sheaths keep the tendon close to the skeleton, particularly when the tendon crosses an articular angle [76].
- The fibrous sheath assumes the role of a pulley when the tendon changes direction [76].
- Each synovial sheath has a visceral and parietal component separated by a potential synovial cavity containing a very thin layer of synovial fluid [76].
- This synovial fluid constitutes the basic gliding and nutritional mechanism for the tendon [76].
- Diffusion is a significant nutrient pathway to the flexor tendon, supporting the importance of sheath closure at the time of tendon suture [36, 37].
- At half the total tendon excursion, the force required to flex the digit through half its range is always less than a third of the force required to flex the digit fully [46].
- The force required to fully flex the digit decreased with more extensive A1 pulley release, becoming significant when more than 50% of the pulley was released [97].
Pathophysiology of Triggering and Ganglions
- Triggering results from the loss of smooth gliding of a tendon within its tendon sheath [6].
- Inflammation of the synovium lining the tendon sheath interferes with the normal gliding mechanism [6].
- Interference with the gliding mechanism is especially troublesome at a point of change in direction of a tendon [6].
- Ganglions are defined as cystic swellings closely connected to joints or tendon sheaths which contain mucinous material [141].
- The etiology of ganglions is unknown [141].
- The articular (synovial) theory has gained worldwide acceptance as a scientifically proven explanation for the formation of intraneural ganglions [17].
- Triggering of the finger can occur secondary to a partial flexor tendon tear after closed direct injury [98].
Classification
- Volar wrist ganglions may arise from a variety of locations, unlike dorsal wrist ganglions which typically arise from a specific location at the dorsal margin of the scapholunate interosseous membrane [16].
- Approximately two thirds of anterior wrist ganglions reportedly arise from the radiocarpal joint [16].
- One third of anterior wrist ganglions reportedly arise from the scaphotrapezial joint [16].
- Ganglion cysts that arise from the flexor carpi radialis (FCR) sheath are often in a slightly more medial location, either just radial or palmar to the sheath [16].
- Ganglions arising from the FCR sheath are typically less mobile than ganglions arising from the wrist joint [16].
- Ganglions arising from the first extensor compartment tend to adhere to the sheath (extensor retinaculum) [16].
- Ganglions arising from the first extensor compartment tend to be quite firm and are less mobile [16].
- In children aged <10 years, ganglion cysts present on the volar aspect of the wrist [13].
- In patients aged >10 years, ganglions resemble those in the adult population and present on the dorsal aspect of the wrist [13].
Clinical Presentation
General Characteristics
- Ganglions are the most common cause of focal masses in the hand and foot [50].
- Ganglions commonly arise from the synovium of joints, tendon sheaths, or the epineurium of nerves [50].
- Ganglions are filled with synovial fluid that may become jelly-like over time [50].
- Most patients with intraneural ganglions present with a painless mass [17].
- Some patients with intraneural ganglions present with symptoms of nerve irritation or entrapment neuropathy [17].
- In many patients with intraneural ganglions, definitive diagnosis is made only at the time of surgery [17].
Volar Wrist and Hand
- Volar wrist ganglia tend to arise in the interval between the first extensor compartment and flexor carpi radialis (FCR) tendon sheath, just proximal to the wrist flexion crease [16].
- Volar wrist ganglia typically appear to be 1 to 2 cm in size but may be significantly larger at the time of surgical dissection [16].
- Patients with volar wrist ganglions often present with complaints of a mass that has been present for a number of months or years and is typically asymptomatic [16].
- Patients with volar wrist ganglions often note discomfort when the mass is "bumped" [16].
- Volar wrist ganglia are clinically compressible, slightly mobile, nontender, and visible when transilluminated [16].
- Volar wrist ganglia are nonpulsatile but are often intimate with the radial artery, which is palpable alongside the lesion [16].
- Approximately one third of anterior wrist ganglions reportedly arise from the scaphotrapezial joint [16].
- Ganglion cysts that arise from the FCR sheath are often in a slightly more medial location, either just radial or palmar to the sheath [16].
- Ganglion cysts arising from the FCR sheath are typically less mobile than ganglions arising from the wrist joint [16].
Pediatric Population
- In children aged <10 years, ganglion cysts are generally amenable to observation with spontaneous regression [13].
- Ganglions in pediatric populations most commonly affect the dorsal wrist [47].
- Ganglions in pediatric populations demonstrate a female predilection [47].
- Pediatric ganglions of the hand have a greater rate of resolution than ganglions of the wrist [52].
Diagnostic Imaging
- Ultrasound is useful for assisting in diagnosis and determining whether patients should undergo aspiration or surgical excision for suspected flexor tendon sheath ganglions [1].
- MRI scans provide relatively good reliability in establishing the diagnosis of an occult dorsal wrist ganglion, with a sensitivity of 83% when using intra-operative findings as the standard [48].
- MRI is an excellent diagnostic modality to evaluate rapidly growing upper extremity masses and distinguish ganglions from malignant processes [33].
- The use of the 3-dimensional FSE extended echo train MRI sequence, called cube, has revolutionized the visualization of intraneural ganglions and articular branches that connect them to the joint [17].
Investigations
Imaging Modalities
- The architecture and relationship of the FDS to FDP within the flexor sheath is accurately defined using a non-invasive imaging technique and the pulley system can be clearly imaged in cross-section [58].
- Sonography-guided wrist arthroscopy provides visualization of the ganglions and ganglion stalk, as well as of the arthroscopic shaver and adjacent structures such as nerves, vessels, and tendons to perform surgery safely [124].
- Sonography-assisted arthroscopy allows clear visualization of ganglia, vessels, nerves, and tendons, enabling safe guidance of the arthroscopic shaver to the lesion without blind resection [126].
Diagnostic Limitations and Utility
- The study concludes that routinely performing wrist radiography is not cost-effective in the evaluation and treatment decision-making process for patients with a wrist ganglion due to a low prevalence of therapeutically significant findings [21].
- Radiologists are less likely to identify occult dorsal ganglion cysts on MRI if the cyst is smaller or if the requisition form does not mention a cyst [138].
Pathology and Histology
- In patients with the clinical diagnosis of wrist ganglion cyst, quality of care would not be compromised by abandoning the practice of routinely submitting surgical specimens for pathological examination after excision of the ganglion cyst [27, 31].
Treatment
Non-Operative Management
- Ultrasound imaging assists in determining whether patients with suspected flexor tendon sheath ganglions should undergo aspiration or surgical excision [1].
- Percutaneous puncture is a practical option for managing flexor tendon sheath ganglions due to its low cost, lack of downtime, and low recurrence rate [5].
- No recurrences were observed after a second percutaneous puncture in the cohort assessed for recurrence [5].
- Ganglion aspiration should be considered as a first-line intervention [55].
- Nonsurgical treatment is largely ineffective in treating ganglion cysts, though it may be considered for symptomatic relief in patients who do not want surgery [125].
- Aspiration, with or without cortisone injection, has an average success rate of 35% to 50% [122].
- Approximately 40% of lesions decrease over the first 6 years after evaluation by a hand surgeon [25].
Operative Management
- Ultrasound-guided excision of flexor tendon sheath ganglions using a 2-mm portal under local anaesthesia was reliable and efficient without specific morbidity [4].
- Open surgical excision offers a significantly lower chance of recurrence compared with aspiration in the treatment of wrist ganglions [135].
- Surgical intervention for ganglions has about a 10% recurrence rate [25].
- Surgical intervention for ganglions leaves scars and carries some risk for adverse events [25].
- In patients with a clinical diagnosis of wrist ganglion cyst, quality of care would not be compromised by abandoning the practice of routinely submitting surgical specimens for pathological examination after excision [27, 31].
- Arthroscopic resection is an effective treatment strategy for intra-articular synovial ganglions refractory to conservative measures, providing complete resolution of symptoms and functional recovery with minimal soft tissue damage [119].
- Arthroscopic ganglionectomy through an intrafocal cystic portal is a safe and efficacious option for the treatment of painful wrist ganglia [120].
- Arthroscopic ganglionectomy is a safe and reliable alternative to open resection [140].
- At 12 months follow-up, the rates of recurrence with arthroscopic dorsal ganglion excision are comparable with and not superior to those of open excision [24].
- Routine midcarpal joint exploration during arthroscopic excision of dorsal wrist ganglions appeared to reduce recurrence at 1 year without negatively impacting patient outcomes [35].
- Recurrent ganglion cysts originating from the midcarpal joint are not contraindications for arthroscopic resection [38].
- Arthroscopy allows for the simultaneous treatment of ganglions and other pathologies [29].
- Endoscopic ganglionectomy via flexor carpi radialis tendoscopy is a minimally invasive approach that offers better cosmesis, less soft tissue trauma, and the ability to manage concomitant FCR tendon pathology [9].
- There was no impairment of wrist motion and function in all patients following arthroscopic resection of palmar ganglions [51].
- The key to successful open treatment of dorsal wrist ganglions is excision of the ganglion stalk based at the scapholunate ligament and its associated dorsal-capsular attachments [122].
- Open ganglionectomy creates a defect in the capsule of 1 to 1.5 cm, which is left open [122].
- Stiffness has been reported from prolonged immobilization following open ganglionectomy [122].
- The rate of recurrence for open ganglionectomy can be as high as 40% [122].
- Indications for surgery include pain, restricted motion, and/or aesthetic complaints as a result of the ganglion cyst [113].
- Ultrasound, magnetic resonance imaging, or X-rays are performed to confirm the presence of a ganglion cyst or to rule out other conditions when surgery is indicated [113].
- The operation for dorsal wrist ganglion excision is generally performed under regional anaesthesia and a tourniquet [113].
- A dorsal incision distal to Lister’s tubercle is used, with the extensor retinaculum between the tendons of the second and fourth extensor compartments incised [113].
- A small arthrotomy is performed over the scapholunate ligament, where the dorsal wrist ganglion usually originates [113].
- Complete excision of the ganglion along with its capsule is performed with local synovectomy [113].
- The capsule is either fenestrated or sutured, depending on the surgeon [113].
- A compressive dressing is applied after skin closure and left in place for 3 days [113].
- Active mobilization of the wrist starts after the hand therapist changes the dressing [113].
- Sutures are removed 10 to 14 days postoperatively [113].
- Splints are not used on a regular basis [113].
- Patients start with a stabilizing and strength programme under the guidance of the hand therapist after 3 weeks [113].
- In pediatric wrist ganglion excision, a transverse incision is made over the ganglion to expose the cyst's wall [123].
- Fluid is aspirated and 0.3e0.5 mL of methylene blue is injected into the cavity to facilitate dye penetration into the cyst wall [123].
- The base of the ganglion is ligated with a 4e0 absorbable suture [123].
- All blue-stained ganglion tissue is thoroughly resected [123].
- The wrist is immobilized with a plaster cast for 7 to 10 days following pediatric excision [123].
- Followup examinations occur monthly for 6 months and every 3 months thereafter [123].
- Recurrence is assessed within 48 months' follow-up by palpation alone [123].
- Patients undergoing initial pediatric excision had been treated conservatively for more than 1 year [123].
- Recurrence of the wrist ganglion cyst occurred in 9% of patients in a cohort of 53 arthroscopic resections [116].
- PRWE scores were significantly higher in patients with a recurrence (30 vs. 12, p = 0.002) [116].
- Patients initially presenting with a new ganglion cyst had fewer recurrences at final follow-up compared with patients initially presenting with recurrence (4 vs. 15%) [116].
- Asymptomatic ganglion cysts were left untreated in the arthroscopic cohort [116].
- One patient experienced neuropraxia of the radial superficial nerve, which resolved spontaneously [116].
- One patient developed extensor carpi ulnaris (ECU) tendinitis, which was successfully treated with splinting [116].
- One patient experienced painful scar tissue, which was successfully removed surgically [116].
Complications
- Surgical intervention for wrist ganglions carries a recurrence rate of approximately 10% [25].
- Surgical intervention for wrist ganglions leaves scars and carries some risk for adverse events [25].
- Operation-related complications after arthroscopic volar wrist ganglionectomy are associated with the anatomical location of the cyst, specifically when it is distal to the bifurcation of the radial artery and concurrently penetrated up to the superficial fascia layer [60].
- Open surgical excision of pediatric wrist ganglions demonstrates minimal complications [13].
Recovery
Non-Operative Management
- No recurrences were observed after a second puncture in the cohort assessed for percutaneous puncture management [5].
- About 40% of lesions decrease over the first 6 years after evaluation by a hand surgeon [25].
- In a child with a wrist ganglion, if the cyst ultimately resolved, it usually did so within 18 months [20].
Operative Management
- Surgical intervention has about a 10% recurrence rate [25].
- Surgical intervention leaves scars and has some risk for adverse events [25].
Key Evidence
- [L4] Ultrasound is useful for assisting in diagnosis and determining whether patients should undergo aspiration or surgical excision for suspected flexor tendon sheath ganglions. [1] (10.1016/s0363-5023(97)80043-3)
- [L4] Surgical excision is a simple, safe, and effective method for treating a painful ganglion of the digital flexor tendon sheath. [2] (10.1007/s11552-007-9028-4)
- [L4] A nonsurgical approach to flexor tendon sheath ganglions is both cost-effective and successful. [3] (10.1053/jhsu.2002.34318)
- [L4] The ultrasound-guided excision of flexor tendon sheath ganglion, using a 2-mm portal, under local anaesthesia was reliable and efficient, without specific morbidity. [4] (10.1016/j.hansur.2018.10.116)
- [L4] Percutaneous puncture is a practical option for managing flexor tendon sheath ganglions given its low cost, lack of downtime, and low recurrence rate, with no recurrences observed after a second puncture in this cohort. [5] (10.1177/17531934221115983)
- [L5] [6] (10.1016/0266-7681(94)90139-2)
- [L4] Pediatric ganglions are more commonly found on the volar surface of the hand and wrist and more commonly have tendon sheath origin compared to adults. [7] (10.1007/s11552-008-9122-2)
- [L5] [8] (10.1016/0266-7681(91)90138-e)
- [Paper] Endoscopic ganglionectomy via flexor carpi radialis tendoscopy is a minimally invasive approach that offers better cosmesis, less soft tissue trauma, and the ability to manage concomitant FCR tendon pathology, though it carries risks of recurrence and nerve or vessel injury. [9] (10.1016/j.eats.2017.06.002)
- [L4] [13] (10.1016/j.jhsa.2021.12.015)
- [L5] [16] (10.1016/j.hcl.2004.03.015)
- [L4] [17] (10.1016/j.jhsa.2015.05.025)
- [L4] In a child with a wrist ganglion, if the cyst ultimately resolved, it usually did so within 18 months. [20] (10.1016/j.jhsa.2019.10.032)
- [L4] The study concludes that routinely performing wrist radiography is not cost-effective in the evaluation and treatment decision-making process for patients with a wrist ganglion due to a low prevalence of therapeutically significant findings. [21] (10.1007/s11552-007-9032-8)
- [L4] There is no consensus within the literature regarding the best management of pediatric wrist ganglia, and no single treatment modality confers a particular advantage or disadvantage over another. [22] (10.1177/1558944720966716)
- [L1] At 12 months follow-up, the rates of recurrence with arthroscopic dorsal ganglion excision are comparable with and not superior to those of open excision. [24] (10.1016/j.jhsa.2008.01.009)
- [L5] Current best evidence suggests that about 40% of lesions decrease over the first 6 years after evaluation by a hand surgeon, that most ganglions recur after aspiration, and that surgical intervention has about a 10% recurrence rate, leaves scars, and has some risk for adverse events. [25] (10.1016/j.jhsa.2010.11.048)
- [L3] This study suggests that, in patients with the clinical diagnosis of wrist ganglion cyst, quality of care would not be compromised by abandoning the practice of routinely submitting surgical specimens for pathological examination after excision of the ganglion cyst. [27] (10.1016/j.jhsa.2010.03.021)
- [L4] Arthroscopy allows for the simultaneous treatment of ganglions and other pathologies. [29] (10.1016/j.jhsa.2012.04.042)
- [L4] In patients with the clinical diagnosis of wrist ganglion cyst, the quality of care would not be compromised by abandoning the practice of routine submission of surgical specimens for pathological examination after excision of the ganglion cyst. [31] (10.1016/s0363-5023(10)60107-4)
- [L4] MRI is an excellent diagnostic modality to evaluate rapidly growing upper extremity masses and distinguish ganglions from malignant processes. [33] (10.1007/s11552-007-9083-x)
- [L3] Routine midcarpal joint exploration during arthroscopic excision of dorsal wrist ganglions appeared to reduce recurrence at 1 year without negatively impacting patient outcomes. [35] (10.1177/17531934251405730)
- [L5] The importance of sheath closure at the time of tendon suture is based in part on the evidence that diffusion is a significant nutrient pathway to the flexor tendon. [36] (10.1016/0266-7681(88)90077-0)
- [L5] The importance of sheath closure at the time of tendon suture is based in part on the evidence that diffusion is a significant nutrient pathway to the flexor tendon. [37] (10.1016/0266-7681_88_90077-0)
- [L4] Ganglion cysts also have a high association with certain interosseous laxities, and recurrent ganglion cysts originating from the midcarpal joint are not contraindications for arthroscopic resection. [38] (10.1016/j.jhsa.2008.11.025)
- [L5] At half the total tendon excursion, the force required to flex the digit through half its range is always less than a third of the force required to flex the digit fully. [46] (10.1016/0266-7681(90)90086-j)
- [L2] Ganglions in pediatric populations, which most commonly affect the dorsal wrist, demonstrate a female predilection. [47] (10.1016/j.jhsa.2021.02.026)
- [L3] MRI scans provide relatively good reliability in establishing the diagnosis of an occult dorsal wrist ganglion, with a sensitivity of 83% when using intra-operative findings as the standard. [48] (10.1177/1753193408092041)
- [Case_report] [50] (10.1007/s12593-014-0117-7)
- [L4] There was no impairment of wrist motion and function in all patients. [51] (10.1016/j.main.2006.07.028)
- [L4] Pediatric ganglions of the hand have a greater rate of resolution than ganglions of the wrist. [52] (10.1016/j.jhsa.2023.07.002)
- [L4] Ganglion aspiration should be considered as a first-line intervention, with surgical excision remaining an effective option for symptomatic cases. [55] (10.1177/1753193411434376)
- [L5] The architecture and relationship of the FDS to FDP within the flexor sheath is accurately defined using a non-invasive imaging technique and the pulley system can be clearly imaged in cross-section. [58] (10.1016/j.jhsb.2005.08.001)
- [L3] The operation-related complications after arthroscopic volar wrist ganglionectomy are associated with its anatomical location: distal to the bifurcation of the radial artery and concurrently penetrated up to the superficial fascia layer. [60] (10.1186/s12891-025-08766-x)
- [L5] Anatomical studies have identified two annular and one oblique pulley in the thumb. [91] (10.1016/s0363-5023(77)80101-9)
- [L5] The force required to fully flex the digit decreased with more extensive A1 pulley release, becoming significant when more than 50% of the pulley was released. [97] (10.1016/s0266-7681(98)80217-9)
- [L5] This illustrates another post-traumatic mechanical cause for triggering of the finger. [98] (10.1016/0363-5023(93)90059-c)
- [L2] [113] (10.1177/17531934231153029)
- [L4] [116] (10.1055/s-0040-1716509)
- [L4] Arthroscopic resection is an effective treatment strategy for intra-articular synovial ganglions refractory to conservative measures, providing complete resolution of symptoms and functional recovery with minimal soft tissue damage. [119] (10.1016/j.jhsg.2024.05.007)
- [L4] Arthroscopic ganglionectomy through an intrafocal cystic portal is a safe and efficacious option for the treatment of painful wrist ganglia. [120] (10.1016/j.arthro.2009.08.021)
- [L4] [122] (10.1016/s0749-0712(21)00020-2)
- [L2] [123] (10.1016/j.jhsa.2015.01.015)
- [L4] Sonography-guided wrist arthroscopy provides several advantages for surgeons, including visualization of the ganglions and ganglion stalk, as well as of the arthroscopic shaver and adjacent structures such as nerves, vessels, and tendons to perform surgery safely. [124] (10.1016/j.jhsa.2012.04.012)
- [L4] Nonsurgical treatment is largely ineffective in treating ganglion cysts, though it may be considered for symptomatic relief in patients who do not want surgery. [125] (10.1155/2013/940615)
- [Paper] Sonography-assisted arthroscopy allows clear visualization of ganglia, vessels, nerves, and tendons, enabling safe guidance of the arthroscopic shaver to the lesion without blind resection. [126] (10.1016/j.eats.2011.12.007)
- [L1] Open surgical excision offers significantly lower chance of recurrence compared with aspiration in the treatment of wrist ganglions. [135] (10.1016/j.jhsa.2014.12.014)
- [L3] Radiologists are less likely to identify occult dorsal ganglion cysts on MRI if the cyst is smaller or if the requisition form does not mention a cyst. [138] (10.1055/s-0039-1683847)
- [L4] Arthroscopic ganglionectomy is a safe and reliable alternative to open resection. [140] (10.1016/j.jhsa.2003.10.018)
- [L4] [141] (10.2106/00004623-197254070-00009)
References
[1] Treatment of flexor tendon sheath ganglions using ultrasound imaging. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(97)80043-3
[2] Flexor Tendon Sheath Ganglions: Results of Surgical Excision. HAND. 2007. DOI: 10.1007/s11552-007-9028-4
[3] Management of flexor tendon sheath ganglions: A cost analysis. The Journal of Hand Surgery. 2002. DOI: 10.1053/jhsu.2002.34318
[4] Flexor tendon sheath ganglions — A new procedure to perform excision under ultrasound-guidance. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.10.116
[5] Percutaneous puncture of flexor sheath ganglions: an assessment of recurrence. Journal of Hand Surgery (European Volume). 2022. DOI: 10.1177/17531934221115983
[6] Extensor Tendon Sheath Stenosis Resulting in Triggering of the Little Finger. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90139-2
[7] Pediatric Ganglion Cysts of the Hand and Wrist: An Epidemiologic Analysis. HAND. 2008. DOI: 10.1007/s11552-008-9122-2
[8] Anatomical Demonstration of the Nerve-Supply to the Flexor Tendon. Journal of Hand Surgery. 1991. DOI: 10.1016/0266-7681(91)90138-e
[9] Endoscopic Ganglionectomy of Palmar Ganglion via Flexor Carpi Radialis Tendoscopy. Arthroscopy Techniques. 2017. DOI: 10.1016/j.eats.2017.06.002
[13] Pediatric Ganglions of the Hand and Wrist: A Review of Current Literature. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2021.12.015
[16] Ganglion cysts and other tumor related conditions of the hand and wrist. Hand Clinics. 2004. DOI: 10.1016/j.hcl.2004.03.015
[17] Intraneural Ganglions of the Hand and Wrist. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.05.025
[20] Wrist Ganglia in Children: Nonsurgical Versus Surgical Treatment. The Journal of Hand Surgery. 2020. DOI: 10.1016/j.jhsa.2019.10.032
[21] The Use of Routine Wrist Radiography is Not Useful in the Evaluation of Patients with a Ganglion Cyst of the Wrist. HAND. 2007. DOI: 10.1007/s11552-007-9032-8
[22] Wrist Ganglion Cysts in Children: An Update and Review of the Literature. HAND. 2022. DOI: 10.1177/1558944720966716
[24] Arthroscopic Versus Open Dorsal Ganglion Excision: A Prospective, Randomized Comparison of Rates of Recurrence and of Residual Pain. The Journal of Hand Surgery. 2008. DOI: 10.1016/j.jhsa.2008.01.009
[25] Wrist Ganglions. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2010.11.048
[27] Necessity of Routine Pathological Examination After Surgical Excision of Wrist Ganglions. The Journal of Hand Surgery. 2010. DOI: 10.1016/j.jhsa.2010.03.021
[29] Ganglions of the Wrist and Associated Triangular Fibrocartilage Lesions: A Prospective Study in Arthroscopically-treated Patients. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.04.042
[31] Necessity of Routine Pathological Examination following Surgical Excision of Wrist Ganglions. The Journal of Hand Surgery. 2010. DOI: 10.1016/s0363-5023(10)60107-4
[33] Compression Neuropathy of the Radial Nerve Due to Ganglion Cysts. HAND. 2008. DOI: 10.1007/s11552-007-9083-x
[35] Arthroscopic resection of dorsal wrist ganglions with or without midcarpal exploration. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934251405730
[36] Flexor tendon healing. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90077-0
[37] Flexor Tendon Healing. Journal of Hand Surgery. 1988. DOI: 10.1016/0266-7681_88_90077-0
[38] Prospective Outcomes and Associations of Wrist Ganglion Cysts Resected Arthroscopically. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2008.11.025
[46] The Mechanical Effect of Partial Resection of the Digital Fibrous Flexor Sheath. Journal of Hand Surgery. 1990. DOI: 10.1016/0266-7681(90)90086-j
[47] Clinical Presentation and Characteristics of Hand and Wrist Ganglion Cysts in Children. The Journal of Hand Surgery. 2021. DOI: 10.1016/j.jhsa.2021.02.026
[48] Magnetic Resonance Imaging in the Diagnosis of Occult Dorsal Wrist Ganglions. Journal of Hand Surgery (European Volume). 2008. DOI: 10.1177/1753193408092041
[50] Intraneural Ganglion of Digital Nerve of Thumb: A Case Report and Review of Literature. Journal of Hand and Microsurgery. 2015. DOI: 10.1007/s12593-014-0117-7
[51] Résection des kystes synoviaux palmaires par arthroscopie. Chirurgie de la Main. 2006. DOI: 10.1016/j.main.2006.07.028
[52] Natural History of Pediatric Hand and Wrist Ganglion Cysts: Longitudinal Follow-Up of a Prospective, Dual-Center Cohort. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.07.002
[55] Patient outcomes following wrist ganglion excision surgery. Journal of Hand Surgery (European Volume). 2012. DOI: 10.1177/1753193411434376
[58] Mri ‘Magic Angle’ Imaging of Finger Tendons. Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsb.2005.08.001
[60] Anatomical location of volar wrist ganglion in preoperative MRI is a risk factor for operation-related complications after arthroscopic ganglionectomy. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08766-x
[75] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > FLEXOR TENDON INJURY.
[76] Exam Of The Hand Wrist 2Ed. 1.3 MOVEMENTS OF THE HAND AND WRIST > Gliding mechanisms.
[91] Anatomy of the flexor tendon sheath and pulleys of the thumb. The Journal of Hand Surgery. 1977. DOI: 10.1016/s0363-5023(77)80101-9
[97] The Effect of the Extent of A1 Pulley Release on the Force Required to Flex the Digits. Journal of Hand Surgery. 1998. DOI: 10.1016/s0266-7681(98)80217-9
[98] Triggering of the finger secondary to partial flexor tendon tear after closed direct injury. The Journal of Hand Surgery. 1993. DOI: 10.1016/0363-5023(93)90059-c
[113] Factors associated with self-reported pain and hand function following dorsal wrist ganglion excision. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231153029
[116] Patient-Related Outcomes of Arthroscopic Resection of Ganglion Cysts of the Wrist. Journal of Wrist Surgery. 2020. DOI: 10.1055/s-0040-1716509
[119] Intra-articular Synovial Ganglion of the Wrist. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2024.05.007
[120] Arthroscopic Ganglionectomy Through an Intrafocal Cystic Portal for Wrist Ganglia. Arthroscopy. 2010. DOI: 10.1016/j.arthro.2009.08.021
[122] ARTHROSCOPIC RESECTION OF DORSAL GANGLION OF THE WRIST. Hand Clinics. 1995. DOI: 10.1016/s0749-0712(21)00020-2
[123] Visualization of the Wrist Ganglion Capsule by Methylene Blue Staining as an Aid for Complete Resection in Children. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.01.015
[124] Sonography-guided Arthroscopy for Wrist Ganglion. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.04.012
[125] Treatment of Ganglion Cysts. ISRN Orthopedics. 2013. DOI: 10.1155/2013/940615
[126] Sonography‐Assisted Arthroscopic Resection of Volar Wrist Ganglia: A New Technique. Arthroscopy Techniques. 2012. DOI: 10.1016/j.eats.2011.12.007
[135] Wrist Ganglion Treatment: Systematic Review and Meta-Analysis. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.12.014
[138] Radiologist Identification of Occult Dorsal Wrist Ganglion Cysts on MRI. Journal of Wrist Surgery. 2019. DOI: 10.1055/s-0039-1683847
[140] Arthroscopic resection in the management of dorsal wrist ganglions: results with a minimum 2-year follow-up period. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2003.10.018
[141] Ganglions of the Wrist and Hand. The Journal of Bone & Joint Surgery. 1972. DOI: 10.2106/00004623-197254070-00009