Patients › Rehabilitation
Giải phóng đường hầm thần kinh quay
Post-operative exercises and precautions after radial tunnel release, including radial nerve glides.
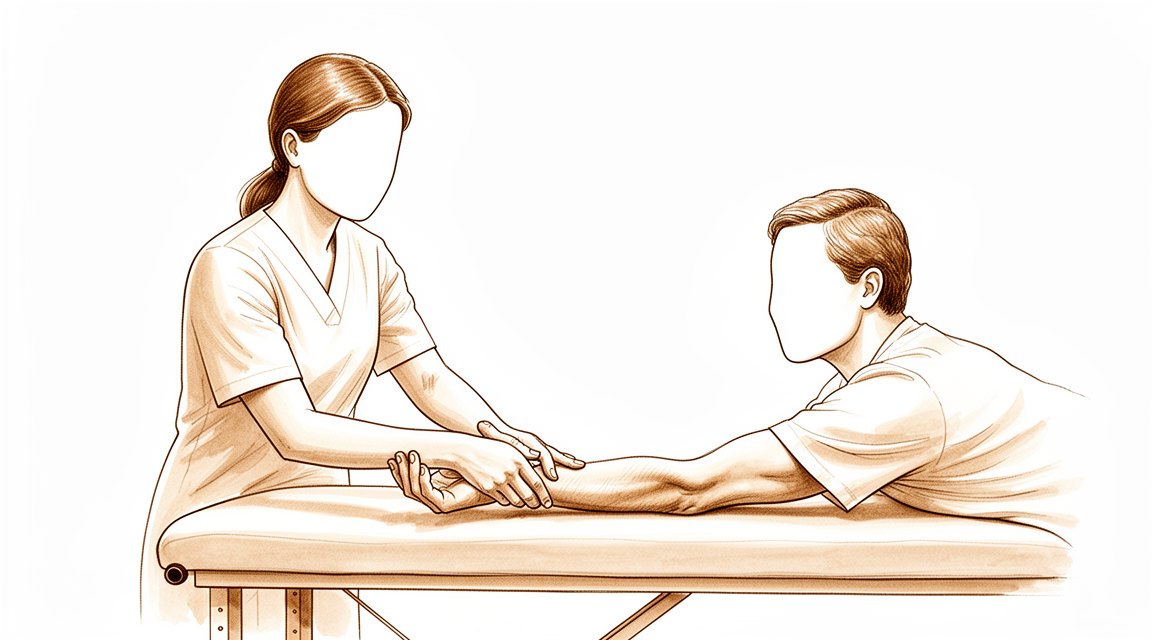
Quy trình này hướng dẫn quá trình hồi phục của bạn sau ca phẫu thuật giải phóng ống cẳng tay do bác sĩ Kieran Hirpara thực hiện tại Bệnh viện tư nhân Mater Rockhampton. Quy trình này mô tả những gì bạn có thể mong đợi trong những tuần sau phẫu thuật và nêu rõ chương trình tập luyện được ghi trong tờ hướng dẫn hậu phẫu dành cho bạn. Hãy mang theo trang này hoặc bản PDF tương ứng trong lần trị liệu vật lý trị liệu hoặc trị liệu tay đầu tiên để quá trình phục hồi được thực hiện một cách nhất quán. Chuyên viên trị liệu có thể điều chỉnh kế hoạch tập luyện tùy theo tiến độ hồi phục của bạn.
Nếu bạn có bất kỳ thắc mắc nào về vết thương sau phẫu thuật, vui lòng liên hệ với phòng khám. Việc chụp ảnh vết thương rồi gửi qua email để được đánh giá cũng là một cách hữu ích.
Những điều bạn có thể mong đợi
Cách chăm sóc vết thương đã được hướng dẫn chi tiết trong tài liệu hướng dẫn chăm sóc vết thương của phòng khám. Trong quá trình lành vết thương, dây thần kinh được giải phóng có thể dính vào các mô xung quanh; vì vậy các bài tập giúp dây thần kinh di chuyển dưới đây rất quan trọng để giúp nó vận động tự do và tránh bị dính cố định.
Đôi khi vết thương có thể trở nên nhạy cảm. Điều này là bình thường, và có thể được ngăn ngừa hoặc giảm thiểu bằng cách thực hiện các bài tập giảm nhạy cảm hàng ngày: nhẹ nhàng vỗ và xoa lên vết thương (hoặc lớp băng gạc), bắt đầu ngay sau khi phẫu thuật. Loại “phản hồi cảm giác” này giúp dây thần kinh dần thích nghi với các kích thích về xúc giác và kết cấu.
Khi vết thương đã lành hoàn toàn, hãy bắt đầu mát-xa vùng sẹo: dùng tay xoay tròn mạnh lên vùng vết mổ. Hãy tham khảo tài liệu hướng dẫn chăm sóc vết thương để biết thêm thông tin về cách quản lý sẹo.
Việc có những kỳ vọng thực tế về quá trình hồi phục là rất quan trọng. Dây thần kinh quay phải di chuyển và giãn ra một khoảng nhất định trong các động tác thông thường của cánh tay; vì vậy việc vận động sớm sẽ giúp tránh tình trạng dây thần kinh dính vào các mô đang lành [1]. Tuy nhiên, cơn đau thường giảm dần sau phẫu thuật giải phóng dây thần kinh quay chứ không biến mất ngay lập tức; đối với một số người, mức độ giảm đau cũng chỉ ở mức vừa phải. Thực tế, ca phẫu thuật này ít có tính dự đoán hơn so với các thủ thuật giải phóng dây thần kinh khác: hội chứng ống thần kinh quay khó chẩn đoán chính xác và thường chồng chéo với chứng viêm mỏm khuỷu tay, đó là lý do khiến kết quả điều trị có sự khác biệt. Các nghiên cứu dài hạn cho thấy khoảng hai phần ba bệnh nhân đạt được kết quả tốt; những người chỉ gặp triệu chứng liên quan đến ống thần kinh quay lại có kết quả tốt nhất [2][3]. Quá trình hồi phục thường chậm hơn và không triệt để nếu bệnh nhân còn mắc chứng viêm mỏm khuỷu tay (viêm mỏm khuỷu ngoài), có nhiều hơn một chỗ chèn ép dây thần kinh ở cùng một cánh tay, hoặc đang trong quá trình yêu cầu bồi thường tai nạn lao động [2][4]. Chương trình vận động dây thần kinh và các bài tập giảm nhạy cảm có mức độ là những yếu tố trong quá trình phục hồi nằm trong tầm kiểm soát của bạn; việc thực hành đều đặn mỗi ngày sẽ giúp dây thần kinh hồi phục tốt nhất.
Các biện pháp phòng ngừa và hạn chế
Bạn nên sử dụng bàn tay một cách nhẹ nhàng cho các hoạt động sinh hoạt hàng ngày như chăm sóc bản thân, ăn uống, mặc quần áo, viết lách và đánh máy. Ngoài ra, các hạn chế cụ thể như sau: không được nâng vật nặng, nắm chặt, chịu tải trọng hoặc sử dụng các thiết bị tạo rung động (ví dụ: dụng cụ điện, máy cắt cỏ) trong vòng 6 tuần sau phẫu thuật; việc lái xe cũng bị hạn chế trong 3 tuần đầu tiên 2–3.
Dành cho chuyên viên vật lý trị liệu:
Mục tiêu
- Ngăn ngừa tình trạng dây thần kinh bị dính vào vết thương đang hồi phục (thực hiện chương trình trượt dây thần kinh)
- Giảm độ nhạy cảm của vết thương thông qua phương pháp khử nhạy dần dần
- Duy trì biên độ vận động của cổ tay, cẳng tay và khuỷu tay
- Hỗ trợ việc sử dụng bàn tay một cách nhẹ nhàng cho các hoạt động sinh hoạt hàng ngày
Cách thực hiện
- Khử nhạy vết thương hàng ngày: nhẹ nhàng vỗ hoặc xoa lên vùng vết thương (vùng băng gạc), bắt đầu ngay sau phẫu thuật
- Massage vết sẹo (xoa tròn mạnh lên vết mổ) sau khi vết thương đã lành hoàn toàn
- Thực hiện các bài tập tại nhà theo hướng dẫn trên các thẻ dưới đây: các bài giãn cổ tay gập/duỗi; các bài giãn cổ tay xoay ngoài/xoay trong; các bài tập gập/duỗi khuỷu tay; các bài tập trượt dây thần kinh quay
- Nên ưu tiên các kỹ thuật trượt dây thần kinh nhẹ nhàng thay vì kéo căng quá mức ở các vị trí cực hạn: các kỹ thuật trượt giúp dây thần kinh di chuyển xa hơn đáng kể mà không gây căng thẳng quá mức, điều này rất có lợi đối với dây thần kinh vừa được giải ép [1][5]
- Có thể cân nhắc thêm các bài tập vận động dây thần kinh như phương pháp hỗ trợ; hiện có nhiều bằng chứng ủng hộ việc vận động dây thần kinh trong các bệnh lý liên quan đến dây thần kinh, tuy nhiên mức độ tin cậy còn khác nhau; vì vậy việc tiến triển các bài tập cần dựa trên triệu chứng của bệnh nhân [6]
Các lưu ý phòng ngừa
- Chỉ được sử dụng bàn tay một cách nhẹ nhàng (chăm sóc bản thân, ăn uống, mặc quần áo, viết lách, đánh máy)
- Không được nâng vật nặng, nắm chặt, chịu tải trọng hoặc sử dụng các thiết bị tạo rung động (ví dụ: dụng cụ điện, máy cắt cỏ) trong vòng 6 tuần sau phẫu thuật
- Việc lái xe bị hạn chế trong 2–3 tuần đầu tiên
- Các bài tập trượt dây thần kinh và giãn cơ phải thực hiện một cách nhẹ nhàng, không gây đau đớn; tuyệt đối không cố gắng kéo căng đến mức gây tái phát cơn đau dây thần kinh như trước phẫu thuật
Đây là các bài tập được ghi trong tờ hướng dẫn sau phẫu thuật; bạn cần thực hiện chúng tại nhà theo hướng dẫn của chuyên viên vật lý trị liệu hoặc chuyên gia trị liệu bàn tay. Số lần lặp lại, thời gian giữ tư thế và tần suất thực hiện đều được ghi rõ trên từng thẻ hướng dẫn.
Các bài tập của bạn

Kieran Hirpara 4.0
Bài tập kéo giãn cổ tay: gập và duỗi cổ tay
Đặt khuỷu tay lên bàn và nhẹ nhàng đung đưa cổ tay qua lại (hoặc đặt cổ tay lên mép bàn hoặc tay vịn ghế như trong hình). Khi đã cảm thấy thoải mái hơn, dùng tay kia đặt lên lòng bàn tay và đẩy cổ tay ra phía sau rồi lại về phía trước, đồng thời giữ các ngón tay thả lỏng. Giữ nguyên tư thế kéo giãn trong 15 giây; lặp lại 5 lần theo mỗi hướng.
10 lần lặp lại, 4–5 lần mỗi ngày.
Kieran Hirpara 4.0
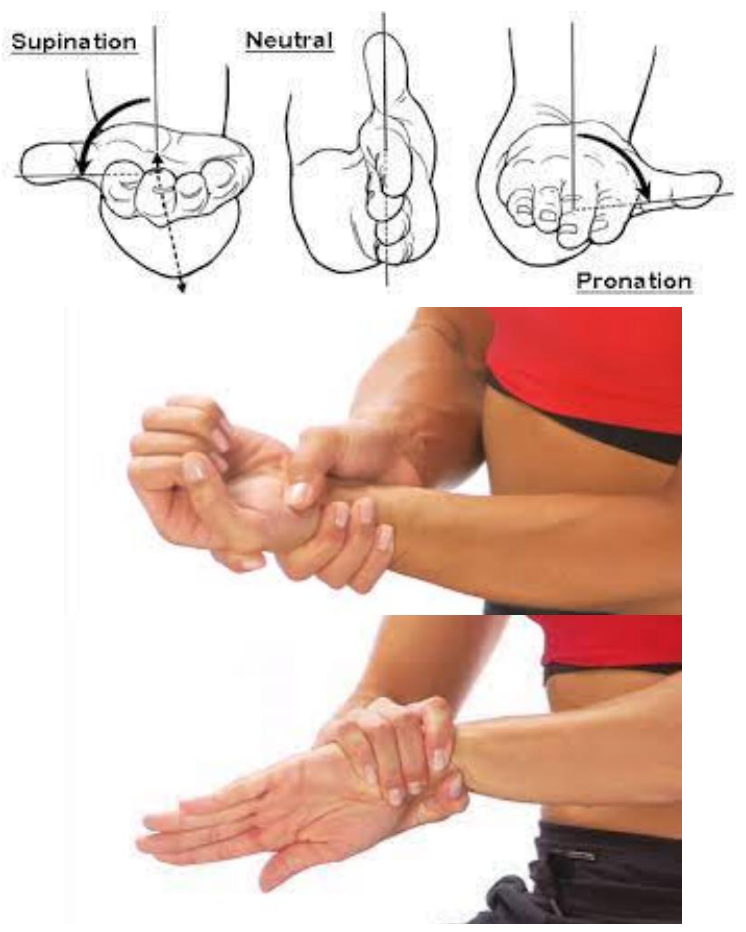
Bài tập kéo giãn xoay ngửa / xoay sấp cẳng tay
Gập khuỷu tay sát bên thân, lòng bàn tay hướng lên trần nhà. Sau đó xoay lòng bàn tay hướng lên trên và giữ trong 15 giây; tiếp tục xoay lòng bàn tay hướng xuống dưới và giữ trong 15 giây; thực hiện tổng cộng 5 lần. Khi cảm thấy thoải mái hơn, hãy dùng tay còn lại — đặt tay lên CỔ TAY chứ không phải lòng bàn tay — để nhẹ nhàng đẩy cổ tay xoay sâu hơn vào mỗi vị trí cho đến khi cảm nhận được sự giãn cơ.
5 lần lặp lại, 4 lần mỗi ngày, 5–7 ngày mỗi tuần.

Kieran Hirpara 4.0
Gập và duỗi khuỷu tay
Hãy để cánh tay thả tự do bên hông, sau đó từ từ duỗi thẳng cẳng tay và khuỷu tay hết mức có thể. Giữ nguyên tư thế giãn cơ ở biên độ tối đa này trong 3–5 giây. Tiếp theo, thực hiện tương tự theo hướng ngược lại: gập cẳng tay lên trên và cố gắng chạm tay vào vai.
10 lần lặp lại, 2 lần mỗi ngày, thực hiện hàng ngày.
Kieran Hirpara 4.0
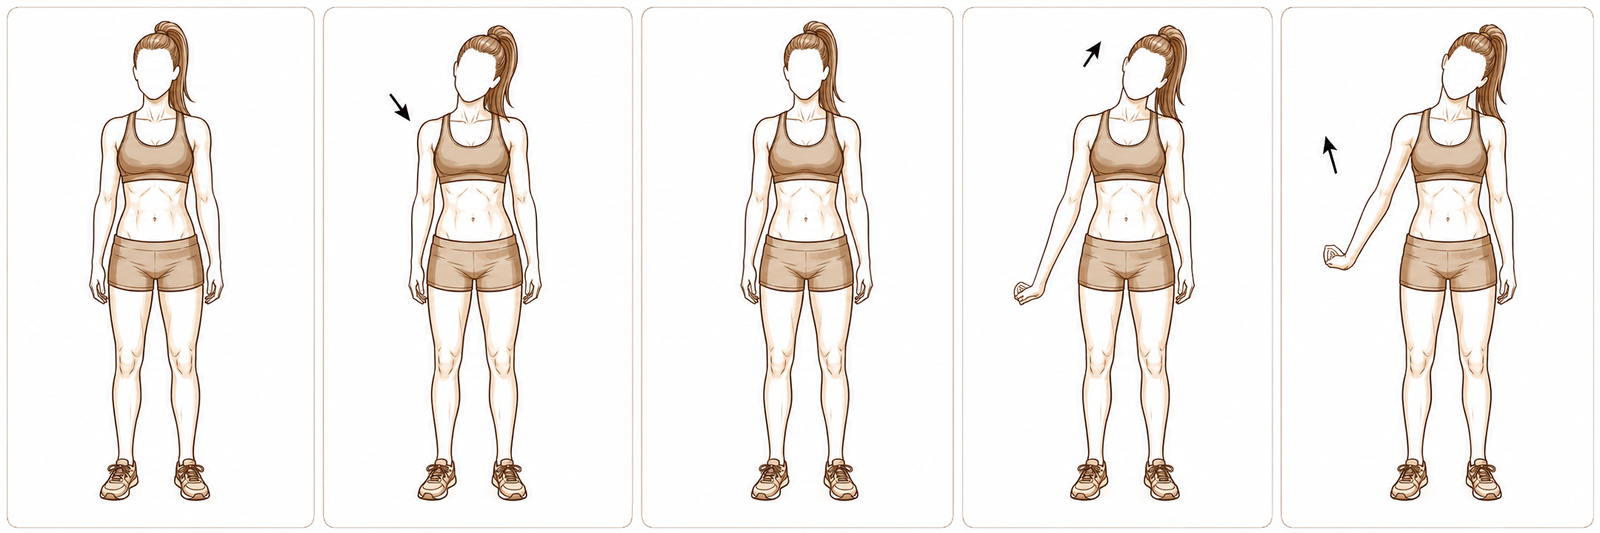
Các bài tập trượt dây thần kinh quay
Đứng thẳng, hai tay thả lỏng dọc theo thân. Hạ vai xuống và vươn các ngón tay về phía sàn nhà. Xoay cánh tay vào trong (ngón tay cái hướng về phía cơ thể) rồi gập cổ tay, lòng bàn tay hướng lên trên. Nhẹ nhàng nghiêng đầu ra xa phía mà bạn đang kéo giãn, sau đó nâng cánh tay lên cao và ra xa khỏi thân. Giữ mỗi tư thế trong khoảng 3 đến 5 giây.
5–8 lần lặp lại, 2–4 lần mỗi ngày, 6–7 ngày mỗi tuần
Chương trình tập luyện này được biên soạn với sự hợp tác của Sarah Farrell, Cử nhân Vật lý trị liệu (BOccThy), Chuyên gia trị liệu tay được chứng nhận (AHT).
Sau khi thực hiện theo quy trình
Quy trình này được sử dụng kết hợp với các hướng dẫn phục hồi chung của phòng khám; vui lòng tham khảo mục xử lý cơn đau sau phẫu thuật, chăm sóc vết thương và những điều cơ bản về vật lý trị liệu cho tay. Để biết thêm thông tin về ca phẫu thuật cũng như tình trạng bệnh được điều trị, hãy xem mục thủ thuật giải phóng ống cánh tay quay và hội chứng ống cánh tay quay.
Tài liệu tham khảo
[1] Wright TW, Glowczewskie F, Cowin D, Wheeler DL. Sự di chuyển và độ căng của dây thần kinh quay tại khuỷu tay và cổ tay khi vận động chi trên. J Hand Surg Am. 2005;30(5):990–996. https://pubmed.ncbi.nlm.nih.gov/16182056/ [2] Lee JT, Azari K, Jones NF. Kết quả điều trị lâu dài sau khi giải phóng đường hầm thần kinh quay – ảnh hưởng của tình trạng viêm gân khuỷu tay, nhiều hội chứng chèn ép thần kinh và các yếu tố liên quan đến bảo hiểm lao động. J Plast Reconstr Aesthet Surg. 2008;61(9):1095–1099. https://www.sciencedirect.com/science/article/abs/pii/S1748681507004044 [3] Sotereanos DG, Varitimidis SE, Giannakopoulos PN, Westkaemper JG. Kết quả điều trị phẫu thuật hội chứng chèn ép đường hầm thần kinh quay. J Hand Surg Am. 1999;24(3):566–570. https://pubmed.ncbi.nlm.nih.gov/10357537/ [4] Naam NH, Nemani S. Hội chứng chèn ép đường hầm thần kinh quay. Orthop Clin North Am. 2012;43(4):529–536. (Hội chứng chèn ép đường hầm thần kinh quay, StatPearls.) https://www.ncbi.nlm.nih.gov/books/NBK555937/ [5] Coppieters MW, Butler DS. Các kỹ thuật vận động thần kinh có thực sự giúp thần kinh di chuyển và giảm độ căng hay không? Phân tích và những lưu ý khi áp dụng các kỹ thuật này. Man Ther. 2008;13(3):213–221. https://pubmed.ncbi.nlm.nih.gov/17398140/ [6] Basson A, Olivier B, Ellis R, Coppieters M, Stewart A, Mudzi W. Hiệu quả của các phương pháp vận động thần kinh trong điều trị các bệnh lý thần kinh – cơ xương: tổng quan có hệ thống và phân tích tổng hợp. J Orthop Sports Phys Ther. 2017;47(9):593–615. https://pubmed.ncbi.nlm.nih.gov/28704626/
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Radial Tunnel Release — Evidence Brief & Post-operative Rehabilitation
Topic scope: post-operative rehabilitation after surgical decompression / neurolysis of the posterior interosseous nerve (deep branch of the radial nerve) in the radial tunnel of the proximal forearm, performed for radial tunnel syndrome (RTS). This is an elbow / proximal-forearm topic — anatomically and clinically distinct from carpal-tunnel and cubital-tunnel decompression. Like other nerve decompressions it is an early-motion pathway (early elbow/forearm/wrist motion, radial-nerve glides, oedema and scar care). The scope deliberately foregrounds the diagnostic controversy and the more variable, lower success rates that distinguish RTS release from the better-validated carpal-tunnel and cubital-tunnel operations.
Defining principle of the rehab here: a decompressed nerve does not create a healing construct that needs months of protection — it needs early, gentle movement to stop it adhering to the operative bed and to restore its glide. So the rehab is an early-motion programme: light functional hand use from day 1, radial-nerve sliders, graded desensitisation and (once healed) scar massage; heavier loading deferred to ~6 weeks. But two honesty caveats sit over the whole topic. First, RTS is a contested diagnosis — there is no confirmatory imaging or electrodiagnostic test, it is a diagnosis of exclusion, and a substantial body of opinion regards it as a variant of recalcitrant lateral epicondylitis. Second, outcomes after release are more variable and on average lower than carpal- or cubital-tunnel release — good results cluster around two-thirds overall, and fall further with co-existing tennis elbow, multiple compression sites, or a workers'-compensation context. Patient expectations should be set accordingly.
A. THE DIAGNOSTIC CONTROVERSY (read first — it frames everything)
RTS is among the most contested entities in upper-limb surgery, and the rehab brief is incomplete without it:
- No confirmatory test. Electromyography and nerve-conduction studies are characteristically normal in RTS (compression is intermittent/dynamic and predominantly of a motor nerve carrying few pain fibres), and MRI is frequently negative — denervation oedema in supinator/extensors is suggestive but inconsistent, and a normal scan does not exclude the diagnosis. RTS is therefore a clinical diagnosis of exclusion, resting on point tenderness ~4 cm distal to the lateral epicondyle (over the radial tunnel rather than the epicondyle), pain on resisted supination / resisted long-finger extension, and — for some surgeons — temporary relief from a diagnostic local-anaesthetic block at the radial tunnel.
- Overlap with lateral epicondylitis (tennis elbow). The two coexist frequently and share the lateral-elbow pain territory. A recognised school of thought holds that "RTS" is often severe, recalcitrant lateral epicondylitis rather than a discrete compression neuropathy. Importantly, routine PIN release added to lateral-epicondylitis surgery has not been shown to improve outcomes, so the diagnosis should be secure before a decompression is planned.
- Practical consequence. Surgery is a last resort after prolonged failed conservative care (activity modification, splinting, anti-inflammatories, sometimes a steroid injection), and is best reserved for patients with proximal-forearm pain and no better explanation. This uncertainty is the single most important reason post-operative expectations must be framed honestly.
B. RELEASE OUTCOMES (variable — and why)
- Headline success ~two-thirds. Across the older long-term series, roughly 67% good, 15% fair, 18% poor after radial tunnel decompression — markedly more variable than carpal- or cubital-tunnel release. A 2008 long-term series (Lee, Azari, Jones) and a 1999 series (Sotereanos et al.) both document this spread; the Sotereanos cohort reported good/excellent results in only ~39% by objective assessment (though ~64% by patient self-rating), underscoring how outcome depends on the metric used.
- Co-existing lateral epicondylitis lowers success. Success falls to roughly 40% when tennis elbow coexists, versus far higher with isolated RTS.
- Multiple compression sites and workers'-compensation context lower success — reported ~58% success in compensation cases vs ~73% without. These are the same modifiers named in the patient protocol.
- 2025 systematic review (Raymond et al., HAND). 11 studies, 401 limbs (381 patients). Outcomes were heterogeneous; a dorsal approach between ECRB and EDC was associated with the most favourable Roles-and-Maudsley scores and satisfaction. The review's central message is that the overall evidence is low-grade (observational), the diagnosis non-standardised, and the effectiveness of conservative treatment essentially untested — a "tendency" toward benefit rather than proof.
- Resorption-style "spontaneous improvement" does not apply here — unlike calcific tendinitis, RTS does not self-resolve through a biological cycle; conservative care manages symptoms rather than curing a deposit.
C. SURGICAL APPROACH (shapes the early rehab)
- What is done. Complete neurolysis of the radial nerve at its bifurcation, decompressing the deep branch (PIN) and superficial sensory branch, releasing the arcade of Frohse (the proximal supinator edge), the leash of Henry (radial recurrent vessels), the ECRB fascial edge, and the distal supinator border. Any constrictive bands or vessels are divided.
- Approaches. Dorsal (Thompson, between ECRB/EDC or the brachioradialis–ECRL interval), volar/anterior (Henry), or transmuscular. Anatomical studies map the trade-offs; the dorsal ECRB–EDC interval performed best in the 2025 review. The superficial radial branch matters — it is a recognised source of post-operative dysaesthesia if irritated.
- Rehab implication. A muscle-splitting/dorsal exposure through the extensor mass means early gentle forearm rotation and wrist motion are encouraged but heavy resisted supination/extension is deferred; the incision sits over a mobile, frequently sensitive area, so desensitisation and scar care carry real weight here.
D. POST-OP THERAPY ROLE (nerve/tendon glides, oedema, scar)
The decompressed nerve must glide, not adhere. The mechanical rationale is well quantified: the radial nerve translates and stretches a measurable amount across the elbow and wrist during ordinary arm motion (Wright et al. 2005), so early motion is what keeps it free of the healing bed.
- Early motion, immediately. Early active elbow, forearm and wrist movement within pain limits from the first post-op days; most protocols use no rigid splinting (or a removable splint for comfort/night only).
- Radial-nerve glides — favour "sliders" over "tensioners". Sliding (slider) neurodynamic techniques achieve substantially greater nerve excursion at much lower nerve strain than end-range tensioners — preferable around a freshly decompressed nerve. Neural-mobilisation evidence across neuromusculoskeletal conditions is supportive but of variable certainty, so progression is symptom-guided and essentially pain-free; mechanism work (e.g., the MONET protocol) is still maturing.
- Oedema and desensitisation. Graded desensitisation (tapping/rubbing over the dressing) from day 1 normalises touch and pre-empts a sensitive scar — particularly relevant given superficial- radial-branch proximity.
- Scar management once healed. Massage, pressure, and silicone are advocated to loosen skin–tissue adhesions and aid remodelling, started once the wound is closed/sutures out.
- Strengthening deferred. Light functional ADL use throughout; resisted strengthening of wrist/ elbow and fine-motor work introduced from ~6 weeks. Heavy work and vibration tools avoided to ~6–8 weeks.
Phased post-op timeline (maps to the patient protocol phases)
| Phase | Window | Splint | Motion / nerve work | Load / strengthening | Notes |
|---|---|---|---|---|---|
| I — Protect & glide | Day 0–2 wk | None, or removable for comfort/night | Early pain-free active elbow/forearm/wrist ROM; radial-nerve sliders; desensitisation from day 1 | Light functional ADL use only (self-care, feeding, dressing, writing, typing) | Stop the nerve adhering; settle the wound. No lifting/gripping/weight-bearing/vibration tools. Driving limited first 1–2 wk |
| II — Restore motion | 2–6 wk | Off | Progress full active + gentle assisted ROM; continue sliders; scar massage once healed | Still no resisted loading; ADL use continues | Sensitivity/dysaesthesia common and usually settles; keep glides gentle |
| III — Strengthen & return | ~6 wk onward | Off | Full ROM goal; sliders as needed | Begin graded wrist/elbow strengthening + fine-motor work from ~6 wk; advance work/heavy tasks thereafter | Vibration tools/heavy work resume ~6–8 wk. Pain relief is often gradual and may be partial — counsel accordingly |
E. COMPLICATIONS / DOWNSIDES
- Incomplete or no pain relief — the dominant "complication," tied directly to diagnostic uncertainty; relief is frequently gradual and sometimes partial.
- Superficial-radial-branch dysaesthesia / scar sensitivity — recognised; desensitisation and careful technique mitigate it.
- Transient PIN weakness (finger/thumb extension) from retraction — usually recovers.
- Adhesion/recurrence of symptoms if early glide is neglected.
- Standard wound risks (infection, haematoma) — uncommon.
F. KEY CONTROVERSIES / EVIDENCE QUALITY
- Does RTS exist as a discrete entity? Genuinely contested. No confirmatory test; substantial opinion equates much of it with recalcitrant lateral epicondylitis. This is the defining controversy and must shape consent and expectation-setting. Unresolved — expert opinion divided.
- Patient selection drives outcome more than technique. Isolated RTS does best; coexisting tennis elbow, multiple compressions, and compensation context predict worse results. Moderate (consistent across cohorts).
- Approach choice. A dorsal ECRB–EDC interval was favoured in the 2025 SR, but the evidence is observational and confounded by diagnostic heterogeneity. Weak–moderate.
- The rehab protocol itself is consensus/expert — drawn from surgeon and hand-therapy guidance (early motion, sliders, desensitisation, scar care), not from a rehab RCT. Phase timings are typical, not trial-derived. Weak / consensus.
- Conservative-treatment efficacy is essentially untested — the 2025 SR notes no usable trials of non-operative care, so "failed conservative management" before surgery rests on practice convention. Weak.
G. EVIDENCE STRENGTH FLAGS (summary)
- STRONG: the mechanical rationale for early nerve glide — quantified radial-nerve excursion/ strain across elbow and wrist (Wright et al. 2005); slider-vs-tensioner excursion/strain physiology.
- MODERATE: patient-selection modifiers of outcome (lateral epicondylitis, multiple compressions, workers' compensation lower success); ~two-thirds overall good-result rate from long-term cohorts; dorsal-approach signal from the 2025 systematic review (low-grade studies).
- WEAK / CONSENSUS: the existence and diagnostic criteria of RTS (no confirmatory test; overlap with lateral epicondylitis); the post-operative rehabilitation protocol (surgeon/ hand-therapy guidance, no rehab RCT); neural-mobilisation certainty (supportive but variable); efficacy of conservative care (essentially untested).
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Posterior Interosseous Nerve Compression in the Forearm, AKA Radial Tunnel Syndrome. HAND. 2022. DOI: 10.1177/15589447221122822
- Radial Tunnel Syndrome: Emphasis on the Superficial Branch of the Radial Nerve. J Hand Surg Eur. 2009. DOI: 10.1177/1753193408099832
- Anatomical Study of the Surgical Approaches to the Radial Tunnel. J Hand Surg Am. 2015. DOI: 10.1016/j.jhsa.2015.03.009
- MR Imaging Features of Radial Tunnel Syndrome: Initial Experience. Radiology. 2006. DOI: 10.1148/radiol.2401050028
- Management of Lateral Epicondylitis: Current Concepts. J Am Acad Orthop Surg (JAAOS). 2008. DOI: 10.5435/00124635-200801000-00004
- Uncommon Nerve Compression Syndromes of the Upper Extremity. J Am Acad Orthop Surg (JAAOS). 1998. DOI: 10.5435/00124635-199811000-00006
- Radial Nerve Excursion and Strain at the Elbow and Wrist Associated With Upper-Extremity Motion. J Hand Surg Am. 2005. DOI: 10.1016/j.jhsa.2005.06.008
- Evidence and Techniques in Rehabilitation Following Nerve Injuries. Hand Clin. 2013. DOI: 10.1016/j.hcl.2013.04.012
- Preventive Strategies, Exercises and Rehabilitation of Hand Compression Neuropathies. J Hand Ther. 2022. DOI: 10.1016/j.jht.2021.11.003
- Mechanisms of Neurodynamic Treatments (MONET): a protocol for a mechanistic study. BMC Musculoskelet Disord. 2024. DOI: 10.1186/s12891-024-07713-6
Radial-tunnel literature (URLs)
- Clinical Outcomes of Operative Management for Radial Tunnel Syndrome According to Surgical Approach: a Systematic Review. HAND. 2025. https://journals.sagepub.com/doi/10.1177/15589447251315761
- The Epidemiology of Radial Tunnel Syndrome and Its Overlap With Lateral Epicondylitis. J Hand Surg Am. 2023. https://www.jhandsurg.org/article/S0363-5023(23)00138-7/abstract
- Lee JT, Azari K, Jones NF. Long-term results of radial tunnel release — the effect of co-existing tennis elbow, multiple compression syndromes and workers' compensation. J Plast Reconstr Aesthet Surg. 2008. https://www.sciencedirect.com/science/article/abs/pii/S1748681507004044
- Sotereanos DG, et al. Results of surgical treatment for radial tunnel syndrome. J Hand Surg Am. 1999. https://pubmed.ncbi.nlm.nih.gov/10357537/
- Interventions for treating the radial tunnel syndrome: a systematic review of observational studies (DARE). https://www.ncbi.nlm.nih.gov/books/NBK75403/
- Radial Tunnel Syndrome (StatPearls). https://www.ncbi.nlm.nih.gov/books/NBK555937/
- Orthopedic Management of Radial Tunnel Syndrome: A Diagnostic and Treatment Dilemma. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC10081130/
- Radial Tunnel Syndrome: Case Report and Comprehensive Critical Review of a Compression Neuropathy Surrounded by Controversy. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC9896270/
Published rehab protocols (patient-guidance — basis for the phase structure)
- Radial Tunnel Release post-op protocol (Santa Barbara Orthopedic / Mencias). https://www.sbortho.com/wp-content/uploads/2023/09/radial-tunnel-release-new.pdf
- Radial Tunnel Syndrome — conservative and post-operative rehabilitation. Physiopedia. https://www.physio-pedia.com/Radial_Tunnel_Syndrome
- Basson A, et al. The effectiveness of neural mobilization for neuromusculoskeletal conditions: a systematic review and meta-analysis. J Orthop Sports Phys Ther. 2017. https://pubmed.ncbi.nlm.nih.gov/28704626/
- Coppieters MW, Butler DS. Do "sliders" slide and "tensioners" tension? Man Ther. 2008. https://pubmed.ncbi.nlm.nih.gov/17398140/