Patients › Hand
Nhiễm trùng vùng bàn tay
Paronychia, deep-space and flexor sheath infections — recognition, antibiotics, drainage.
Những triệu chứng bạn đang gặp phải
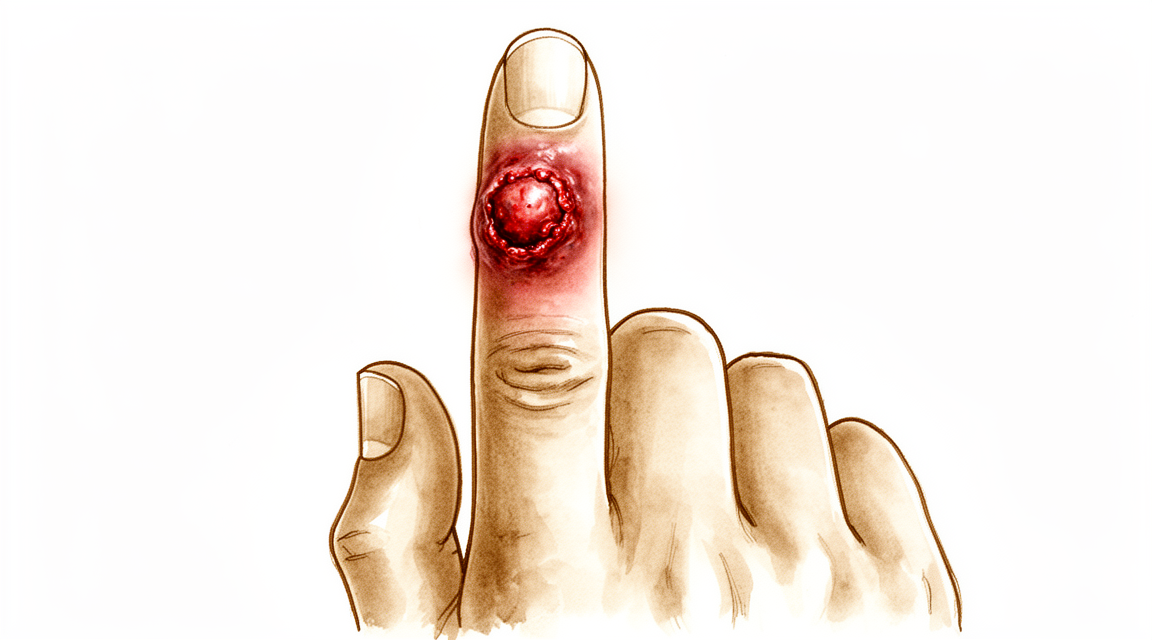
Nhiễm trùng ở tay thường gây đau ở một vị trí cụ thể. Vùng da phía trên chỗ đau có thể đỏ, nóng và sưng lên. Cơn đau thường tăng lên khi bạn cử động ngón tay hoặc nắm chặt vật gì đó. Việc nghỉ ngơi có thể làm giảm đau phần nào, nhưng tình trạng đau nhức sẽ không tự hết.
Các hoạt động hàng ngày trở nên khó khăn: cài cúc áo, xoay chìa khóa, cầm cốc trà hay gõ bàn phím đều gây đau. Nếu nhiễm trùng xảy ra ở bao gân ngón tay (là nơi gân uốn cong ngón tay di chuyển), toàn bộ ngón tay có thể sưng và hơi cong. Việc duỗi thẳng ngón tay gây đau dữ dội; ngay cả khi người khác nhẹ nhàng cố gắng duỗi thẳng nó cũng gây đau. Nếu khớp bị nhiễm trùng, khớp đó sẽ sưng, đau khi chạm vào và nóng; mọi cử động ở khớp đều gây đau nhiều.
Một số trường hợp nhiễm trùng lan rộng dọc theo da dưới dạng những vệt đỏ, sưng và đau; các hạch bạch huyết ở nách cũng có thể bị sưng đau. Tình trạng sưng có thể khiến mu bàn tay trông phù nề; đôi khi rất khó xác định chính xác nơi dịch tích tụ. Vào ban đêm, cảm giác khó chịu tăng lên do dịch tích tụ khi tay ở trạng thái tĩnh.
Hầu hết các nhiễm trùng xuất hiện trong vài giờ hoặc vài ngày chứ không phải vài tuần. Nếu vùng da đỏ, sưng và cơn đau ngày càng tăng thay vì giảm, đó là dấu hiệu của nhiễm trùng chứ không phải chấn thương đơn thuần. Một số tình trạng khác có triệu chứng gần giống nhau như bệnh gút, vết côn trùng cắn, phản ứng với mảnh gỗ găm vào da hoặc cơn đau do viêm khớp; vì vậy nguyên nhân ban đầu đôi khi không dễ xác định.
Hãy thông báo cho bác sĩ phẫu thuật nếu bạn mắc bệnh tiểu đường, bệnh thận hoặc có bệnh lý/đang dùng thuốc làm suy giảm hệ miễn dịch. Những yếu tố này ảnh hưởng đến diễn tiến và cách điều trị nhiễm trùng. Điều tương tự cũng áp dụng cho các trường hợp nhiễm trùng không thuyên giảm sau khi dùng kháng sinh hoặc sau khi vết thương đã được làm sạch; một số nhiễm trùng phát triển chậm cần các xét nghiệm đặc biệt mới xác định được.
Với việc điều trị kịp thời, hầu hết các nhiễm trùng mô mềm ở tay đều khỏi hoàn toàn. Việc chậm trễ trong điều trị có thể dẫn đến cứng khớp, ngón tay bị cong vĩnh viễn hoặc trong những trường hợp nặng có thể dẫn đến mất ngón tay.
Chuyện gì đang xảy ra thực sự
Bàn tay là một không gian chật hẹp. Có tổng cộng 27 chiếc xương nằm sát nhau dưới lớp da mỏng ở mu bàn tay và dính chặt vào lòng bàn tay. Các gân – những “sợi dây” giúp cử động ngón tay – di chuyển qua những đường hầm hẹp. Một trong những đường hầm này là bao gân gập, bao quanh gân chịu trách nhiệm gập ngón tay; bên trong có một lớp màng trơn giúp nuôi dưỡng và bôi trơn gân. Khi vi khuẩn xâm nhập qua vết cắt, mảnh gỗ hay vết thương đâm thủng, không gian kín này khiến chúng không có chỗ nào khác để lan rộng ngoài việc đi dọc theo đường hầm đó.
Tình trạng sưng phù mới là vấn đề nghiêm trọng. Trong những đường hầm như vậy, không còn chỗ cho mô sưng lên, nên áp lực ngày càng tăng. Nếu áp lực tiếp tục tăng, nó có thể chèn ép mạch máu nuôi dưỡng gân, khiến gân bị sẹo dính vào thành đường hầm xung quanh; kết quả là ngón tay bị cứng ngay cả sau khi nhiễm trùng đã khỏi. Đó là lý do tại sao nhiễm trùng bao gân cần được điều trị ngay lập tức chứ không thể chờ vài ngày.
Các vùng khác cũng có những “bẫy” riêng. Mô mỡ ở đầu ngón tay được chia thành nhiều túi nhỏ được ngăn cách bởi các sợi chắc; vì vậy nhiễm trùng tại đây (gọi là áp xe đầu ngón tay) làm áp lực tăng nhanh và có thể lan sang xương hoặc khớp gần đó. Vùng da bên cạnh móng tay cũng có thể là nơi ẩn náu của nhiễm trùng âm ỉ, kéo dài (viêm quanh móng mãn tính), thường do nấm gây ra; độ ẩm thấm qua lớp da móng khiến vùng này luôn bị viêm. Ở một số người, các đường hầm gân của ngón cái và ngón út lại nối với nhau, nên nhiễm trùng có thể lan từ một phía lòng bàn tay sang phía còn lại.
Hầu hết các nhiễm trùng ở tay đều do vi khuẩn vốn sống trên da xâm nhập qua vết thương hở. Một số trường hợp xuất phát từ vết cắn của người hoặc động vật. Tiểu đường, việc dùng thuốc steroid hoặc hệ miễn dịch suy yếu khiến vi khuẩn dễ dàng xâm nhập và lan sâu tới các cấu trúc như gân, xương hay khớp. Vì vậy bác sĩ phẫu thuật sẽ hỏi kỹ về tiền sử sức khỏe của bạn; việc điều trị sớm là vô cùng quan trọng: nếu được chăm sóc kịp thời, hầu hết các nhiễm trùng mô mềm đều khỏi hoàn toàn; ngược lại, việc trì hoãn điều trị có thể dẫn đến tình trạng cứng khớp kéo dài.
Những gì chúng tôi có thể làm
Bác sĩ Kieran Hirpara, bác sĩ phẫu thuật chi trên tại Bệnh viện tư nhân Mater Rockhampton, điều trị các nhiễm trùng ở tay bằng cách hành động nhanh chóng; bởi sự chậm trễ mới là nguyên nhân gây ra những tổn thương lâu dài. Thông thường, bệnh nhân được bác sĩ đa khoa giới thiệu đến phòng khám chúng tôi; nếu nhà vật lý trị liệu khuyên bạn nên đến gặp chúng tôi, bạn vẫn cần có giấy giới thiệu từ bác sĩ đa khoa để được hưởng mức hoàn trả từ Medicare. Trong lần khám đó, chúng tôi sẽ hỏi bệnh sử, khám tay bạn và chỉ định các xét nghiệm cần thiết nhằm xác định loại vi khuẩn gây bệnh và mức độ lan rộng của nhiễm trùng.
Đối với nhiều trường hợp nhiễm trùng giai đoạn sớm, bước đầu tiên là điều trị không phẫu thuật. Nếu nhiễm trùng màng gân được phát hiện trong vòng 48 giờ kể từ khi các triệu chứng xuất hiện, việc dùng kháng sinh và đeo nẹp có thể ngăn chặn sự lan rộng của bệnh. Sau đó, bệnh nhân sẽ được theo dõi sát sao; nếu tình trạng không cải thiện nhanh chóng, chúng tôi sẽ tiến hành phẫu thuật thay vì chờ đợi. Sau mọi hình thức điều trị, việc đeo nẹp giữ tay ở tư thế bảo vệ và vận động các ngón tay sớm sẽ giúp ngăn ngừa cứng khớp. Phục hồi chức năng đóng vai trò quan trọng: nếu tay bị nhiễm trùng không được vận động, nó sẽ dễ bị cứng lại; vì vậy vật lý trị liệu là một phần không thể thiếu trong kế hoạch điều trị, chứ không phải là yếu tố tùy chọn.
Kháng sinh là thành phần y tế quan trọng thứ hai trong điều trị. Loại kháng sinh đầu tiên được kê đơn nhằm bao phủ các loại vi khuẩn có khả năng gây nhiễm trùng ở bạn; sau khi kết quả xét nghiệm cho biết chính xác loại vi khuẩn gây bệnh, chúng tôi sẽ chuyển sang dùng loại kháng sinh phù hợp hơn. Một số trường hợp nhiễm trùng cần dùng kháng sinh qua đường truyền tĩnh mạch thay vì uống dưới dạng viên; đối với các nhiễm trùng nghiêm trọng, liệu trình điều trị có thể kéo dài từ 4 đến 6 tuần. Nếu hệ miễn dịch của bạn bị suy yếu do bệnh tật hoặc do dùng các loại thuốc như steroid, chúng tôi sẽ điều trị nhanh hơn và mạnh mẽ hơn, vì những nhiễm trùng này có thể trở nên nghiêm trọng rất nhanh. Các vết cắn từ người hoặc động vật thường cũng cần dùng kháng sinh phòng ngừa.
Phẫu thuật được cân nhắc khi có mủ cần dẫn lưu hoặc khi nhiễm trùng đã lan đến gân, xương hoặc khớp. Áp xe hoặc khối dịch tích tụ dưới da cần được dẫn lưu để giảm áp lực; vết thương thường được băng bó bằng gạc để tiếp tục dẫn lưu. Nhiễm trùng đầu ngón tay (gọi là felon) hoặc nhiễm trùng quanh móng (paronychia) được dẫn lưu qua một vết rạch nhỏ; đôi khi phải cắt bỏ một phần móng. Nhiễm trùng màng gân cần được rửa sạch khoang màng gân; còn nhiễm trùng xương (viêm tủy xương) thì cần loại bỏ mô chết cùng với việc dùng kháng sinh trong thời gian dài. Có một ngoại lệ quan trọng: nếu mụn nước trên ngón tay thực chất là nhiễm trùng do virus (viêm mụn nước do herpes), chúng tôi không dùng phẫu thuật; việc mổ mở vết mụn nước có thể khiến tình trạng tệ hơn.
Những điều bạn có thể mong đợi
Hầu hết các nhiễm trùng ở tay được phát hiện sớm đều khỏi hoàn toàn sau khi điều trị. Nếu được chăm sóc kịp thời, phần lớn các nhiễm trùng mô mềm sẽ biến mất hoàn toàn và bàn tay sẽ trở lại trạng thái bình thường. Việc đến khám càng sớm thì cơ hội tránh được tình trạng cứng khớp hoặc tổn thương lâu dài càng cao.
Thời gian hồi phục phụ thuộc vào mức độ lan sâu của nhiễm trùng. Các nhiễm trùng ở da hoặc móng có thể khỏi chỉ sau vài ngày nhờ dẫn lưu mủ hoặc dùng kháng sinh. Trong khi đó, nhiễm trùng bao gân, nhiễm trùng xương hoặc nhiễm trùng khớp cần thời gian hồi phục lâu hơn; một số trường hợp phải dùng kháng sinh trong nhiều tuần. Ngay cả khi nhiễm trùng đã khỏi, ngón tay vẫn có thể bị cứng trong một thời gian. Việc vận động ngón tay sớm, khi bác sĩ phẫu thuật cho phép, sẽ giúp ngăn ngừa tình trạng cứng khớp trở thành vĩnh viễn.
Nếu điều trị bị trì hoãn, tiên lượng sẽ kém chắc chắn hơn. Nhiễm trùng bao gân kéo dài vài ngày có thể gây sẹo ở gân, khiến ngón tay bị cứng ngay cả sau khi nhiễm trùng đã khỏi. Những nhiễm trùng nghiêm trọng thậm chí có thể dẫn đến mất chức năng vĩnh viễn hoặc, trong một số trường hợp, phải cắt bỏ ngón tay dù đã được điều trị tích cực và kịp thời. Vì vậy, các nhiễm trùng này luôn được xem là tình trạng cấp cứu chứ không thể chỉ theo dõi vài ngày.
Một số loại nhiễm trùng có diễn tiến khác. Ở những người mắc bệnh đái tháo đường hoặc có hệ miễn dịch suy yếu, nhiễm trùng có thể lan nhanh và ảnh hưởng đến các cấu trúc sâu hơn; vì vậy cần điều trị mạnh mẽ hơn và đôi khi phải phẫu thuật nhiều lần. Những nhiễm trùng phát triển chậm, chẳng hạn do vi khuẩn mycobacteria (nhóm vi khuẩn liên quan đến vi khuẩn gây bệnh lao), cần dùng kháng sinh trong thời gian dài kết hợp với phẫu thuật để loại bỏ hoàn toàn; thời gian hồi phục có thể kéo dài hàng tháng thay vì vài ngày.
Sau điều trị, bạn thường sẽ được khám lại để kiểm tra xem nhiễm trùng đã khỏi chưa và khả năng vận động của bàn tay có tốt không. Hãy tuân thủ các lịch hẹn khám này ngay cả khi cảm thấy đã khỏe hơn, vì một số biến chứng chỉ xuất hiện khi tình trạng sưng giảm đi. Nếu cơn đau, vùng da đỏ hoặc sưng tấy tái phát sau khi nhiễm trùng dường như đã khỏi, hãy liên hệ ngay với bác sĩ phẫu thuật thay vì chờ đợi.
Khi nào nên đi khám bác sĩ
Các nhiễm trùng ở tay cần được xử lý ngay lập tức. Việc chậm trễ có thể gây tổn thương nhanh chóng; vì vậy đừng chờ đợi xem tình trạng có tự khỏi hay không.
Hãy đến phòng cấp cứu nếu trên tay hoặc cánh tay xuất hiện các vệt đỏ lan rộng, nếu toàn bộ ngón tay bị sưng, cong lại và đau đến mức không thể duỗi thẳng, hoặc nếu da chuyển màu nhanh chóng, xuất hiện mụn nước hoặc bị rách. Điều tương tự cũng áp dụng nếu bạn bị sốt và cảm thấy mệt mỏi kèm theo các triệu chứng ở tay; hoặc nếu tay vừa bị chấn thương và hiện đang sưng to, căng cứng. Những dấu hiệu này có thể cho thấy nhiễm trùng đang lan rộng hoặc ở sâu bên trong, cần được đánh giá và điều trị ngay trong ngày.
Hãy yêu cầu được khám ngay trong ngày nếu cơn đau dữ dội và ngày càng tăng, nếu khớp ngón tay nóng, sưng và đau đến mức không thể cử động, hoặc nếu thấy mủ tích tụ dưới da hoặc gần móng tay. Những trường hợp nhiễm trùng không thuyên giảm sau một hoặc hai ngày dùng kháng sinh cũng cần được đánh giá lại thay vì chỉ chờ hết thời hạn dùng thuốc.
Dù là nhiễm trùng nhỏ ở tay, bạn cũng nên đến gặp bác sĩ đa khoa càng sớm càng tốt. Điều này đặc biệt quan trọng nếu bạn mắc bệnh đái tháo đường, bệnh thận, hoặc có bệnh lý/đang dùng thuốc làm suy giảm hệ miễn dịch; vì trong những trường hợp này, nhiễm trùng có thể lan rộng và đi sâu vào cơ thể nhanh hơn. Hãy thông báo cho bác sĩ về bất kỳ vết cắn từ động vật hay người, vết thương do vật nhọn gây ra, cũng như lịch sử làm việc hoặc đi du lịch có thể liên quan đến các loại vi khuẩn đặc biệt.
Nếu nhiễm trùng tái phát nhiều lần hoặc không hề thuyên giảm dù đã điều trị, hãy yêu cầu được khám bởi chuyên gia, vì một số nhiễm trùng phát triển chậm cần các xét nghiệm đặc hiệu để xác định nguyên nhân.
Phân tích chi tiết hơn
Advanced reading: the deeper science (optional)
Phần này đi sâu hơn mức cần thiết để bạn tự đưa ra quyết định điều trị. Các bệnh nhiễm trùng ở tay rất đáng để tìm hiểu thêm; bởi vì các loại kháng sinh thường được kê đơn đầu tiên cho hầu hết mọi người trong trường hợp này lại không phù hợp, và bởi vì một số trường hợp nhiễm trùng tay là tình trạng cấp cứu ngoại khoa thường bị nhầm lẫn là bệnh nhẹ.
Vi khuẩn phổ biến nhất lại kháng lại các loại thuốc kháng sinh thường dùng nhất
Một nghiên cứu kéo dài 10 năm trên 815 ca nhiễm trùng vùng tay ở khu vực thành thị cho thấy, mặc dù tỷ lệ mắc MRSA hàng năm có xu hướng giảm, nhưng vi khuẩn này vẫn là tác nhân gây bệnh phổ biến nhất; đồng thời tình trạng kháng thuốc clindamycin và levofloxacin liên tục gia tăng. Các tác giả đưa ra kết luận cụ thể: trong điều trị nhiễm trùng vùng tay, phác đồ kháng sinh nên tránh sử dụng penicillin, các thuốc nhóm beta-lactam, clindamycin và levofloxacin [1].
Danh sách các loại thuốc cần tránh này dài hơn nhiều so với dự đoán của hầu hết mọi người; nó bao gồm hầu hết các loại thuốc thường được kê đơn để điều trị nhiễm trùng da ở những vùng khác trên cơ thể. Điều này có nghĩa là việc nhiễm trùng vùng tay không thuyên giảm dù đã dùng thuốc kháng sinh đầu tay là hiện tượng phổ biến và dễ dự đoán; vì vậy bệnh nhân nên đi khám lại thay vì tiếp tục điều trị đơn độc.
Tình trạng kháng thuốc ở từng địa phương có thể khác nhau; do đó đây là một nguyên tắc chung chứ không phải phác đồ cố định. Tuy nhiên, nguyên tắc này giúp giải thích tại sao các ca nhiễm trùng vùng tay thường cần được điều trị mạnh hơn so với mức cần thiết dựa trên mức độ nghiêm trọng của bệnh.
Nhiễm trùng bao gân gập: những chi tiết quyết định kết quả điều trị
Viêm màng bao gân gập do vi khuẩn, tức là tình trạng nhiễm trùng xảy ra trong không gian kín nơi gân gập đi qua, có diễn tiến khác biệt so với các dạng nhiễm trùng ở tay khác. Bao gân là một không gian hạn chế và có nguồn cung cấp máu kém; vì vậy mủ tích tụ dưới áp lực bên trong có thể phá hủy bề mặt trơn tru giúp gân di chuyển chỉ trong vài ngày.
Trên 763 bệnh nhân, có hai yếu tố giúp cải thiện phạm vi vận động: việc sử dụng kháng sinh như một phần của phác đồ điều trị, và thực hiện rửa bao gân bằng ống thông thay vì rửa mở. Các bằng chứng lâm sàng ủng hộ cả việc điều trị sớm lẫn việc dùng kháng sinh toàn thân [2].
Cần lưu ý rằng chỉ số đánh giá kết quả điều trị ở đây là phạm vi vận động của ngón tay, chứ không phải việc loại trừ hoàn toàn vi khuẩn gây bệnh. Có thể chữa khỏi nhiễm trùng nhưng ngón tay vẫn bị cứng khớp; đó mới là hậu quả nghiêm trọng do việc trì hoãn điều trị. Bốn dấu hiệu điển hình gồm: ngón tay sưng phù giống hình “xúc xích”, hơi cong, đau khi sờ dọc toàn bộ bao gân, và đau dữ dội khi cố gắng duỗi thẳng ngón tay – cần được nhận biết rõ ràng, vì sự kết hợp này đòi hỏi phải thăm khám ngay trong ngày thay vì chỉ dùng thuốc uống.
Trường hợp thực sự là tình trạng cấp cứu
Viêm mô tế bào hoại tử khởi phát từ bàn tay là tình trạng hiếm gặp nhưng có khả năng phá hủy mô rất nhanh. Cuộc tổng quan hệ thống về 161 ca bệnh cho thấy việc chẩn đoán sớm là điều vô cùng quan trọng, và cần thực hiện can thiệp phẫu thuật sớm, quyết đoán với ngưỡng can thiệp thấp, đặc biệt là ở những bệnh nhân có các yếu tố nguy cơ [3].
Cụm từ “ngưỡng can thiệp thấp” được sử dụng một cách có chủ đích. Đây là tình trạng mà việc chần chừ để xác nhận chẩn đoán có thể dẫn đến mất chi. Những đặc điểm giúp phân biệt tình trạng này với viêm mô tế bào thông thường là cơn đau không tương xứng với mức độ tổn thương trên da, tiến triển nhanh trong vài giờ thay vì vài ngày, kèm theo các triệu chứng toàn thân như sốt, lú lẫn, cảm giác mệt mỏi cực độ; bên cạnh đó là vùng da đỏ có diện tích tương đối nhỏ.
Tại sao một vết thương nhỏ lại có thể gây hiểu lầm?
Có hai cơ chế dẫn đến tình trạng nhiễm trùng xảy ra sâu hơn nhiều so với mức độ mà vết thương bên ngoài cho thấy. Vết cắn vào vùng khớp ngón tay khi va chạm với miệng sẽ khiến các vi khuẩn từ khoang miệng xâm nhập qua da, gân duỗi và màng khớp chỉ trong một động tác; sau đó da lại khép lại che phủ vùng bị nhiễm trùng. Một vết đâm vào lòng bàn tay cũng có thể khiến vi khuẩn xâm nhập vào bao gân gập thông qua lỗ đâm, và vết thương này sẽ tự liền lại trong vòng một ngày.
Trong cả hai trường hợp, vết thương bên ngoài không thể phản ánh chính xác mức độ nghiêm trọng của vấn đề. Các dấu hiệu đau đớn – đặc biệt là cơn đau khi cử động ngón tay thay vì cơn đau tại chính vết thương – mới là những chỉ dẫn hữu ích hơn so với diện mạo của vùng da bị tổn thương.
Tài liệu tham khảo
[1] Kistler JM, Thoder JJ, Ilyas AM. Tỷ lệ mắc MRSA và xu hướng sử dụng kháng sinh trong các nhiễm trùng vùng bàn tay ở khu vực đô thị: Nghiên cứu dọc kéo dài 10 năm. Hand (N Y). 2018;14(4):449-54. https://doi.org/10.1177/1558944717750921
[2] Giladi AM, Malay S, Chung KC. Tổng quan có hệ thống về phương pháp điều trị viêm màng gân duỗi cấp tính do nhiễm khuẩn. J Hand Surg Eur Vol. 2015;40(7):720-8. https://doi.org/10.1177/1753193415570248
[3] Christopoulos G, Khoury A, Johnson M, Sergentanis TN. Viêm mô tế bào hoại tử khởi phát từ vùng bàn tay: Tổng quan có hệ thống và phân tích tổng hợp. Hand (N Y). 2022;19(4):568-74. https://doi.org/10.1177/15589447221141486
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Treatment of acute hand infections requires a combination of surgical intervention (incision and drainage) and appropriate antibiotic therapy tailored to the organism and infection severity [1].
- Fungal infections of the hand are most commonly cutaneous infections involving the skin and nails [2].
- Cutaneous fungal infections of the hand can be treated with topical or local therapy [2].
- Mycobacterium tuberculosis must be maintained in the differential diagnosis for subacute presentations of flexor tenosynovitis or carpal tunnel syndrome of the hand [3].
- Mycobacterium tuberculosis must be considered in the differential diagnosis of subacute flexor tenosynovitis or carpal tunnel syndrome even in nonendemic areas and in the absence of past tuberculosis infection or exposure [3].
- Stiffness and contracture are the most common sequela of pyogenic flexor tenosynovitis [4].
- Stiffness and contracture resulting from pyogenic flexor tenosynovitis benefit from early motion and hand therapy [4].
- Tuberculous tenosynovitis can be overlooked as a cause of chronic tenosynovitis [5].
- Tuberculous tenosynovitis is particularly easily overlooked in immunocompetent young people lacking risk factors [5].
- The majority of patients with fungal tenosynovitis of the hand and upper extremity were successfully treated with surgical debridement and antimicrobial therapy [6].
- Fungal tenosynovitis of the hand and upper extremity has a recurrence rate of 30% [6].
- A recurrence rate of 30% in fungal tenosynovitis highlights the need for close post-treatment follow-up [6].
- Management of fungal osteomyelitis and fungal septic arthritis is challenging, especially in immunocompromised patients [7].
- Outcomes for fungal osteomyelitis and fungal septic arthritis have historically been poor due to a lack of evidence-based treatment guidelines [7].
- Invasive infections may require a combination of serial surgical debridement and a multidrug antibiotic regimen [8].
Anatomy & Pathophysiology
General Principles & Diagnosis
- Chronic hand infections can be caused by viruses, bacteria, mycobacteria, fungi, Prototheca, protozoa, parasites, and insects [14].
- Hand infections may be superficial (skin or nails), subcutaneous, or deep (nerves, tendons/tenosynovium, joints/synovium, bone, and rarely muscles) [14].
- Chronic lesions of the hand have a nonspecific presentation, and early biopsy and cultures facilitate diagnosis [14].
- Infection must be included in the differential diagnosis for any chronic lesion of the hand, particularly in immunocompromised patients [14].
- An infection that does not respond to antibiotics, incision, drainage, or debridement is suspect for a chronic or atypical etiology [14].
- The adage "culture a tumor and biopsy an infection" is recommended when an unusual lesion is encountered to avoid diagnostic delay [14].
- Nontuberculous mycobacterial (NTM) infections of the hand are now more common than Mycobacterium tuberculosis infections [14].
- Tenosynovial infections are far more common than joint and bone infections in mycobacterial hand disease [14].
- Hansen disease is the most common chronic infection affecting the hand in developing countries and infects peripheral nerves [14].
- High suspicion for Hansen disease is warranted when peripheral neuropathy of the ulnar nerve, with or without nerve enlargement, is seen in an immigrant [14].
- Consultation with an infectious disease specialist, microbiology personnel, and a pathologist improves diagnostic accuracy for chronic hand infections where organisms are scarce or slow-growing [14].
Bacterial Pathophysiology
- Paronychia contains polymicrobial aerobic and anaerobic flora, with mixed aerobic/anaerobic flora isolated in half of the patients [9].
- Human bite injuries to the hand involve 42 different bacterial species identified in normal human mouth flora [48].
- The mechanism for introducing anaerobic bacteria into the joint during a clenched-fist injury involves the lacerated tendon gliding proximally when the finger is extended, creating a closed, anaerobic environment [48].
- Actinomycosis is caused by endogenous human flora, most commonly Actinomyces israelii, which is a normal inhabitant of the oral cavity [32].
- Actinomycosis spreads contiguously in a slow but progressive manner, ignoring tissue planes [32].
- The identification of "yellow sulfur granules" from a draining sinus or pus is diagnostic for actinomycosis [32].
- Actinomycosis cultures are positive in only 25% of cases, often because specimens were not sent in anaerobic media [32].
- Mycetoma presents with a clinical triad of tumification, draining sinuses, and granules in the discharging pus [33].
- Mycetoma grains are 0.2 to 5.0 mm in diameter and may be black, white, yellow, pink, or red depending on the causal organism [33].
- Mycetoma infection begins in the skin and subcutaneous tissues and tends to follow fascial planes as it spreads proximally and mediolaterally [33].
- With increasing depth, mycetoma progressively infects and destroys all connective tissues and eventually bone [33].
Fungal Pathophysiology
- Cutaneous fungal infections are caused by fungi that infect and metabolize keratin, preventing invasion beneath the skin [29].
- Candida albicans and dermatophytes (Trichophyton, Microsporum, and Epidermophyton) cause the majority of chronic cutaneous and nail infections [29].
- Chronic cutaneous C. albicans infection occurs in the moist palms and webs of a "clenched fist" in patients with spasticity [29].
- C. albicans involvement in chronic paronychia is characterized by mycelium in the outer epidermis with no involvement of the dermis [10].
- Fungal tenosynovitis has a recurrence rate of 30% despite treatment with surgical debridement and antimicrobial therapy [6].
- Management of fungal osteomyelitis and fungal septic arthritis is challenging, especially in immunocompromised patients, with historically poor outcomes due to a lack of evidence-based treatment guidelines [7].
Mycobacterial Pathophysiology
- Mycobacterium tuberculosis must be maintained in the differential diagnosis for subacute flexor tenosynovitis or carpal tunnel syndrome, even in nonendemic areas and without past exposure [3].
- Tuberculous tenosynovitis can be overlooked as a cause of chronic tenosynovitis, particularly in immunocompetent young people lacking risk factors [5].
- Extrapulmonary TB accounts for almost 20% of all TB cases in the general population and 72% of all cases in U.S. AIDS patients [30].
- Skeletal TB represents 1% of all TB and 10% of all extrapulmonary TB in the United States [30].
- Of skeletal TB cases, 10% occur in the upper extremity, with 4% specifically in the hand and fingers and an additional 3% in the hand accompanied by multifocal sites elsewhere [30].
- Tuberculous osteomyelitis of the hand typically occurs in the phalanges (tuberculous dactylitis) and metacarpals [30].
Anatomical Structures & Compartments
- The hand consists of 19 bones, 17 articulations, and 19 muscles situated entirely within the hand, plus approximately the same number of tendons activated by forearm muscles [11].
- The skeleton of the hand and wrist consists of 27 bones, of which 19 are long bones [19].
- The thumb ray is the shortest, composed of a metacarpal and two phalanges, and is more mobile and proximal than the other rays [19].
- The trapezium is angled out in front of the carpal plane, allowing the first metacarpal to make an angle of about 45 degrees with the second metacarpal in the sagittal plane [19].
- The transverse axis of the palm is oblique, forming an acute angle of approximately 75 degrees with the longitudinal axis [19].
- The extrinsic extensors run through six different fibroosseous retinacular compartments at the wrist level [18].
- The first extensor compartment contains the abductor pollicis longus and the extensor pollicis brevis [18].
- The second extensor compartment contains the extensor carpi radialis longus and the extensor carpi radialis brevis [18].
- The third extensor compartment contains the extensor pollicis longus, which turns abruptly radialward about Lister tubercle [18].
- The fourth extensor compartment contains the extensor indicis proprius lying deep to the four tendons of the extensor digitorum communis [18].
- The fifth extensor compartment contains the extensor digiti quinti [18].
- The sixth extensor compartment contains the extensor carpi ulnaris [18].
- The sagittal bands stabilize the digital extensor tendons over the midline of the metacarpophalangeal joint and transmit proximal extrinsic extensor tension to the proximal phalanx [18].
- Rupture or attenuation of the sagittal band fibers allows the extrinsic extensor tendon to sublux to the ulnar side of the metacarpal head, causing ulnar deviation of the finger [18].
- The flexor digitorum profundus inserts on the proximal volar aspect of the distal phalanx and flexes the distal, proximal interphalangeal, and metacarpophalangeal joints [18].
- The flexor digitorum superficialis inserts via radial and ulnar slips into the proximal metaphysis of the middle phalanx and primarily flexes the proximal interphalangeal joint [18].
- The tenosynovial sheath of the flexor pollicis longus is continuous with the radial bursa, and the sheath to the little finger is continuous with the ulnar digital bursa [28].
- In some patients, the radial and ulnar bursae communicate, allowing a horseshoe abscess to spread between the thumb and little finger if infection occurs in either flexor tendon sheath [28].
- The fibroosseous tunnel of the digital flexor sheath consists of annular pulleys for mechanical stability and cruciate pulleys for flexibility [28].
- The A2 and A4 annular pulleys are the most essential in maintaining the mechanical advantage of the flexor tendons [28].
- The tenosynovium lining the fibroosseous tunnel supplies nutrition and lubrication to the poorly vascularized flexor tendons [28].
- Within the flexor tendon sheath, tendon vascularity is supplied via the vincula system, specifically the vinculum longus and brevis [28].
- There are seven interosseous muscles in the hand: four dorsal and three volar [24].
- The dorsal interossei are abductors, while the volar interossei are adductors [24].
- The middle finger has two dorsal interossei (abductors) and no volar interossei (adductors) because the central axis of the hand lies within it [24].
- The deep head of each dorsal interosseous muscle forms a lateral band that flexes and weakly abducts the proximal phalanx while extending the middle and distal phalanges [24].
- The volar interossei form the ulnar lateral band of the index finger and the radial lateral band of the ring and little fingers [24].
- The abductor digiti quinti and flexor digiti quinti brevis are structurally and functionally similar to the superficial and deep heads of the dorsal interossei, respectively [24].
- The opponens digiti quinti arises from the pisohamate ligament and the hook of the hamate and inserts onto the ulnar side of the diaphysis of the fifth metacarpal [24].
- The flexor retinaculum maintains and restrains the tendons of the extrinsic flexors within the carpal canal, keeping them close to the axis of flexion–extension of the wrist [26].
- The metacarpal arch is adaptable due to the mobility of the peripheral metacarpals, which can deepen the palmar concavity as they approach each other [26].
- The index metacarpal is the most firmly fixed, while the fifth metacarpal is semi-independent with a range of flexion–extension of approximately 20 degrees [26].
- The metacarpophalangeal joints are the keystones of the longitudinal arches and are stabilized by collateral ligaments and the thick volar articular capsule (volar plate) [26].
- The volar plates are interconnected by the transverse interglenoid ligament, which ties together the anterior glenoid ligaments of the metacarpophalangeal articulations [26].
- The palmar skin is subdivided into two zones by the oppositional crease of the thumb: a radial mobile portion and an ulnar/distal fixed portion [23].
- The central triangular part of the palm has fixed, poorly vascularized skin covering almost directly the superficial palmar aponeurosis [23].
- Incisions made along the sides of the diamond-shaped cutaneous contact zones in flexed digits present a minimal chance of retraction [23].
- The dorsal slope of the web spaces has supple, non-adherent skin, while the palmar surface is flat and densely adherent to the commissural skeleton [23].
- The "princeps pollicis" artery is the terminal branch of the radial artery that crosses the first intermetacarpal space and runs along the ulnar side of the first metacarpal [27].
- Only 15% of anatomical dissections of the thumb palmar arteries fall into the classical "typical" category [27].
- In the second segment of the thumb, the ulnar collateral artery is often easier to dissect and larger than the radial collateral artery [27].
- The dorsal arteries of the thumb originate from palmar arteries (princeps, commissural, or anastomoses) at the level of the first metacarpal and head distally along the sides of the distal phalanges [27].
Classification
Flexor Tenosynovitis
- Kanavel identified four cardinal signs of suppurative flexor tenosynovitis: tenderness over the involved sheath, rigid positioning of the finger in flexion, pain on attempts to hyperextend the fingers, and swelling of the involved part [16].
- Of the four cardinal signs of suppurative flexor tenosynovitis, tenderness over the flexor sheath is considered the most significant [16].
- The Michon classification categorizes flexor tenosynovitis into three intraoperative stages based on characteristic findings [16].
- Michon stage I flexor tenosynovitis is characterized by increased fluid in the sheath, primarily serous exudate [16].
- Michon stage II flexor tenosynovitis is characterized by cloudy or purulent fluid and granulomatous synovium [16].
- Michon stage III flexor tenosynovitis is characterized by septic necrosis of the tendon, pulleys, or tendon sheath [16].
- The Michon classification has not been validated [16].
- Direct inoculation is the most common cause of infectious flexor tenosynovitis [16].
- Adjacent spread from a local infection or hematogenous spread are possible causes of infectious flexor tenosynovitis [16].
- While the flexor sheath is usually involved in infectious tenosynovitis, the radial and ulnar bursae may also be involved [16].
Subcutaneous Fungal Infections
- There are three major subcutaneous fungal infections of the hand: chronic paronychia, sporotrichosis, and phaeomycotic cysts [44].
- Chronic paronychia is usually initially misdiagnosed as a bacterial infection [44].
- A phaeomycotic cyst is a deep dermal or subcutaneous infection resulting from the traumatic implantation of a dematiaceous (pigmented) fungus such as Exophiala or Phialophora [44].
Mycetoma
- Mycetoma of the hand and upper extremity has been graded into five stages [47].
- Mycetoma stage I is the nodular stage, characterized by a small, firm, painless subcutaneous nodule or nodules under the skin [47].
- The duration of mycetoma stage I is 2 to 3 months [47].
- Mycetoma stage II is the sinusoidal stage, where nodules become abscesses and drain granules through sinuses to the surface of the skin or to the surface of an ulcerated nodule [47].
- The duration of mycetoma stage II is 4 to 12 months [47].
- Mycetoma stage III is the skeletal stage, where the infection progresses to osteomyelitis [47].
- Mycetoma stage IV is the skeletal stage, where limb deformity occurs over the course of a year or more [47].
- Mycetoma stage V is the metastatic stage, where lesions of the hand may metastasize to the axilla and the chest wall [47].
- Radiographic signs of mycetoma include thinning of the metacarpal, bone erosions and cavities, sclerosis, and periosteal reaction [47].
- A network of connected sinuses is present in the soft tissues from the bone to the skin in mycetoma [47].
- Constitutional symptoms are absent in mycetoma unless there is superimposed bacterial infection [47].
- Pain is not a predominant symptom in mycetoma [47].
- In 80% of cases, patients postpone seeking medical care for mycetoma until the second or third stage is reached due to lack of pain [47].
Clinical Presentation
General Principles and Diagnostic Approach
- Chronic lesions of the hand, both superficial and deep, have a nonspecific presentation [14].
- Early biopsy and cultures facilitate diagnosis of chronic hand infections [14].
- Infection must be included in the differential diagnosis for any chronic lesion of the hand [14].
- In an immunocompromised patient, infection must always be included in the differential diagnosis [14].
- An infection that does not respond to antibiotics, incision, drainage, or debridement is suspect [14].
- "Culture a tumor and biopsy an infection" is a useful adage when an unusual lesion is encountered [14].
- With a careful history and physical examination, the location of the infection, the extent of spread, and the presence of swelling, lymphangitis, lymphadenitis, and joint involvement can be determined [38].
- Fluctuance can be difficult to identify in the hand [38].
- Radiographs are helpful in revealing bone injury [38].
- Radionuclide scanning may show bone infection [38].
- MRI and ultrasound may localize an abscess [38].
- The specificity of all inflammation markers (WBC, C-reactive protein, ESR) was inadequate for diagnosis of finger infections [38].
- If any fluid or tissue is obtained, it is sent to the laboratory for Gram stain, crystals, culture, and antibiotic sensitivity determinations [38].
- Specific requests are usually made of the laboratory to culture for aerobic and anaerobic bacteria, mycobacteria, and fungi [38].
Specific Infection Types
- Tuberculous tenosynovitis can easily be overlooked as a cause of chronic tenosynovitis, particularly in immunocompetent young people lacking risk factors [5].
- M tuberculosis should be maintained in the differential diagnosis of a subacute presentation of flexor tenosynovitis or carpal tunnel syndrome of the hand, even in nonendemic areas and in the absence of past tuberculosis infection or exposure [3].
- In chronic paronychia lesions studied, C. albicans involvement was present with mycelium in the outer epidermis but no involvement of the dermis [10].
- Finger joint infections usually result from the spread of infection in adjacent structures, direct penetration of the joint, and less commonly, hematogenous spread [34].
- The involved joints in finger joint infections are usually swollen, tender, and warm, and the finger is usually held in slight flexion [34].
- Careful inspection and palpation may reveal a fluctuant joint effusion in finger joint infections [34].
- Active and passive motions are usually quite painful in finger joint infections [34].
- Fluid obtained from a septic joint is usually turbid, opaque, or grossly purulent [34].
- The joint fluid WBC is usually greater than 50,000/mm³ in septic joints [34].
- Lowering the cell count threshold to 17,500 increases the sensitivity of the diagnosis of septic arthritis to 83% [34].
- The polymorphonuclear count is usually greater than 75% in septic joint fluid [34].
- The synovial fluid glucose is 40 mg or less in septic joints [34].
- Blue nails and clubbing are both a sign of HIV infection [21].
- Red fingers syndrome has been reported in patients with HIV and hepatitis C infection [21].
- Fingers of patients with AIDS may be red with painless erythema and periungual telangiectasia [21].
- Nails in patients with AIDS may be blue with painless clubbing [21].
- Diagnosis of AIDS should be considered when there is an unusual hand infection [21].
- Diagnosis of AIDS should be taken into consideration for any patient who needs a repeat drainage or debridement procedure [21].
Differential Diagnosis Considerations
- Conditions that can be confused with hand infections include gout, acute calcium deposition, pseudogout, pyogenic granuloma, insect bites, pyoderma gangrenosum, foreign bodies, factitious lesions, herpetic gangrenes, metastatic lesions, silicone synovitis, granuloma annulare, rheumatoid arthritis, nonspecific tenosynovitis, reactions to intravenous medications (e.g., chemotherapeutic agents), and Sweet syndrome [38].
Investigations
- MRI, CT, and 3-phase bone scans may add to the radiographic diagnosis made on plain radiographs for hand osteomyelitis [42].
- MRI, CT, and 3-phase bone scans have poor sensitivity and specificity for the diagnosis of hand osteomyelitis [42].
- Deep tissue cultures are the most accurate method of diagnosis for hand osteomyelitis [42].
- The presence of an indolent course in hand osteomyelitis suggests a fungal or mycobacterial cause [42].
- Incisional biopsy is indicated for patients with lytic destructive lesions of the bones of the hand [46].
- Biopsy must be strongly considered before the initiation of treatment for presumed deep infection because misdiagnosis is the most common error in diagnosis [46].
- MRI is particularly useful in delineating the extent of bone and soft tissue involvement in Ewing’s sarcoma that may not be apparent on plain radiographs [46].
Treatment
General Principles
- Early suspicion, biopsy, and diagnosis of a chronic infection is the mainstay of all ensuing treatment principles [14].
- Pharmacologic treatment of a chronic hand infection requires close monitoring for serious side effects and drug resistance [14].
- Consultation with an infectious disease specialist, microbiology personnel, and a pathologist improves the accuracy of a diagnosis when organisms are scarce, slow to grow, and require special media and temperature to grow [14].
Fingertip Infections
- Early-stage paronychia can be managed with warm soaks and antistaphylococcal antibiotics [35].
- When paronychia has progressed to abscess formation, drainage, with or without removal of the involved portion of the nail plate from the fold, is required [35].
- Following drainage of paronychia, cultures should be taken whenever possible, and antibiotics as well as warm soapy soaks should be recommended [35].
- Routine oral antibiotics usually are not effective for chronic paronychia [35].
- Nail plate removal and eponychial marsupialization is the recommended treatment for chronic paronychia [35].
- The “Swiss roll” technique has also been described to treat chronic paronychia [35].
- Surgical drainage is the mainstay of treatment for felon [35].
- Drainage of a felon should be accomplished without violating the flexor sheath or DIP joint [35].
- A midaxial incision along the non–pressure-bearing side of the digit or a longitudinal incision over the volar pulp skin is preferred for felon drainage [35].
- The wound from a felon drainage is left open, and warm soapy soaks are initiated to allow drainage [35].
- Surgical drainage or débridement of herpetic whitlow lesions is contraindicated [35].
- When administered early, oral acyclovir may lessen symptom severity in herpetic whitlow [35].
- In children with herpetic whitlow, a 10-day course of a penicillinase-resistant oral antibiotic is required if cultures from blistering dactylitis reveal growth [35].
Cellulitis and Abscesses
- Empiric coverage for CA-MRSA should be provided if local prevalence rates exceed 10% to 15% [15].
- Ultrasonography has a 78.4% positive predictive value of identifying an abscess and a negative predictive value of 90% to rule out an abscess [15].
- Early antibiotic administration has not been shown to greatly reduce bacterial culture growth from hand abscess so long as decompression is performed within 24 hours [15].
- After surgical decompression, débridement, and irrigation of the abscess, packing is often used, at least initially, to allow for continued drainage [15].
- No difference has been shown between different soaks and daily dressing changes in clearing the infection postoperatively [15].
- Infections in immunosuppressed patients are more likely to involve deeper structures such as joints, bone, tendons, and muscle [15].
- Immunosuppressed patients with hand infections should be treated rapidly and aggressively as their potential for increased morbidity is high [15].
Flexor Tenosynovitis
- When early tenosynovitis is suspected, immediate treatment with antibiotics and splinting may abort the spread of infection if the patient’s symptoms have been present for less than 48 hours [16].
- If nonsurgical treatment is selected for early tenosynovitis, patients should be followed closely with a low threshold for hospital admission [16].
- Good results have been reported in patients with pyogenic flexor tenosynovitis treated with surgical drainage, followed by outpatient management with intravenous antibiotics, wound care, and rehabilitation [16].
- If gross pus is obtained from the aspiration of the digital flexor sheath, surgical drainage usually is indicated [16].
- Vancomycin is effective for infections caused by gram-positive bacteria [16].
- Ciprofloxacin is most effective for gram-negative organisms, including Pseudomonas [16].
- The Michon classification recommends minimally invasive drainage and catheter irrigation for stage I or II flexor tenosynovitis [16].
- The Michon classification recommends extensile open debridement and possible amputation for stage III flexor tenosynovitis [16].
- The use of a continuous postoperative irrigation catheter has not been shown to improve outcomes, but rather increases postoperative pain and adds difficulty to postoperative care [16].
- Stiffness and contracture are the most common sequela of pyogenic flexor tenosynovitis and benefit from early motion and hand therapy [4].
- Invasive infections may require a combination of a serial surgical debridement and a multidrug antibiotic regimen [8].
Fungal Infections
- Fungal infections of the hand are most commonly cutaneous infections involving the skin and nails and can be treated with topical or local therapy [2].
- Although the majority of patients with fungal tenosynovitis were successfully treated with surgical debridement and antimicrobial therapy, a recurrence rate of 30% highlights the need for close post-treatment follow-up [6].
- Fluconazole and AmB are the drugs of choice for use in patients with deep candidiasis [20].
- For periprosthetic fungal infection, radical synovectomy, tenosynovectomy, and removal of the implant are recommended in addition to chemotherapy combination of amphotericin B and 5-fluorouracil [20].
Mycobacterial Infections
- The case highlights the importance of maintaining M tuberculosis in the differential diagnosis of a subacute presentation of flexor tenosynovitis or carpal tunnel syndrome of the hand, even in nonendemic areas and in the absence of past tuberculosis infection or exposure [3].
Complications
Flexor Tenosynovitis
- Persistent tenosynovial infection can cause pressures within the flexor sheath to exceed 30 mm Hg, rendering tendons ischemic [16].
- Delay in treatment of flexor tenosynovitis may lead to damage to the flexor tendon, resulting in adhesion, loss of excursion, finger stiffness, and impaired function [16].
- The prognosis for function is poor if a flexor tenosynovitis infection produces pus that must be drained [16].
- If an open technique is used for flexor tenosynovitis drainage, healing and rehabilitation are prolonged and full motion may not be regained [16].
- Patients presenting with ischemic changes in flexor tenosynovitis had amputation rates of 59% [16].
- Patients presenting with subcutaneous purulence in flexor tenosynovitis had amputation rates of 8% [16].
- The use of a continuous postoperative irrigation catheter for flexor tenosynovitis has not been shown to improve outcomes, but rather increases postoperative pain and adds difficulty to postoperative care [16].
Fungal Infections
- Fungal infections following organ transplantation can have an associated mortality as high as 76% [40].
- Histoplasmosis necrotizing myofasciitis in severe burns of the upper extremity can result in fatality [40].
- Cutaneous histoplasmosis in a renal transplant patient with hand and forearm necrotizing myofasciitis required below-elbow amputation [40].
- Recurrent histoplasmosis infection after multiple antifungal medications and debridements may require above-elbow amputation to save the patient's life [40].
General Infection Complications
- Hand involvement is an independent risk factor for hospital admission for patients presenting to the emergency department with cellulitis [15].
- Patients with immunosuppression are at a higher risk for atypical infections [15].
- Patients with immunosuppression have a high potential for increased morbidity from hand infections [15].
- M tuberculosis must be maintained in the differential diagnosis of subacute flexor tenosynovitis or carpal tunnel syndrome, even in nonendemic areas and in the absence of past tuberculosis infection or exposure [3].
Recovery
- Stiffness and contracture following pyogenic flexor tenosynovitis benefit from early motion and hand therapy [4].
- A recurrence rate of 30% was observed in patients treated for fungal tenosynovitis of the hand and upper extremity [6].
- The 30% recurrence rate in fungal tenosynovitis highlights the need for close post-treatment follow-up [6].
- After surgical decompression, débridement, and irrigation of a hand abscess, packing is often used initially to allow for continued drainage [17].
- No difference has been shown between different soaks and daily dressing changes in clearing the infection postoperatively after hand abscess drainage [17].
- In a matched cohort study of upper extremity infections, the most frequent immunosuppressive medication was glucocorticoids [17].
- Infections in immunosuppressed patients were more likely to involve deeper structures such as joints, bone, tendons, and muscle [17].
- In a review of 74 HIV-seropositive patients treated for upper extremity infections, 26 infections (29%) required more than one operation [21].
- In a review of 74 HIV-seropositive patients treated for upper extremity infections, 11 infections (12%) resulted in amputation [21].
- Among 14 AIDS patients with hand infections, almost one-third needed multiple debridements and resulted in amputation of a finger or hand [21].
Key Evidence
- [L5] Treatment requires a combination of surgical intervention (incision and drainage) and appropriate antibiotic therapy tailored to the organism and infection severity. [1] (10.1016/j.jhsa.2014.03.031)
- [L5] Fungal infections of the hand are most commonly cutaneous infections involving the skin and nails and can be treated with topical or local therapy. [2] (10.1016/j.hcl.2020.03.009)
- [L5] The case highlights the importance of maintaining M tuberculosis in the differential diagnosis of a subacute presentation of flexor tenosynovitis or carpal tunnel syndrome of the hand, even in nonendemic areas and in the absence of past tuberculosis infection or exposure. [3] (10.5435/jaaosglobal-d-17-00083)
- [L5] Stiffness and contracture are the most common sequela and benefit from early motion and hand therapy. [4] (10.2106/jbjs.rvw.26.00015)
- [L5] Tuberculous tenosynovitis can easily be overlooked as a cause of chronic tenosynovitis, particularly in immunocompetent young people lacking risk factors. [5] (10.1007/s00402-012-1527-2)
- [L4] Although the majority of patients were successfully treated with surgical debridement and antimicrobial therapy, a recurrence rate of 30% highlights the need for close post-treatment follow-up. [6] (10.1016/j.jhsa.2016.11.014)
- [L5] Management of fungal osteomyelitis and fungal septic arthritis is challenging, especially in immunocompromised patients, and historically outcomes have been poor due to a lack of evidence-based treatment guidelines. [7] (10.5435/jaaos-22-06-390)
- [L5] Invasive infections may require a combination of a serial surgical debridement and a multidrug antibiotic regimen. [8] (10.5435/jaaosglobal-d-19-00024)
- [L4] Paronychia contains polymicrobial aerobic and anaerobic flora, with mixed aerobic/anaerobic flora isolated in half of the patients. [9] (10.1016/0266-7681(93)90063-l)
- [L4] Each lesion studied had C. albicans involvement with mycelium in the outer epidermis but no involvement of the dermis. [10] (10.1001/archderm.1962.01590090066015)
References
[1] Acute Hand Infections. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.03.031
[2] Fungal Infections of the Hand. Hand Clinics. 2020. DOI: 10.1016/j.hcl.2020.03.009
[3] Flexor Tenosynovitis of the Hand Caused by Mycobacterium tuberculosis. JAAOS: Global Research and Reviews. 2018. DOI: 10.5435/jaaosglobal-d-17-00083
[4] Management of Pyogenic Flexor Tenosynovitis. JBJS Reviews. 2026. DOI: 10.2106/jbjs.rvw.26.00015
[5] Tuberculous extensor tenosynovitis of the hand. Archives of Orthopaedic and Trauma Surgery. 2012. DOI: 10.1007/s00402-012-1527-2
[6] A Rare Diagnosis: Recognizing and Managing Fungal Tenosynovitis of the Hand and Upper Extremity. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2016.11.014
[7] Fungal Osteomyelitis and Septic Arthritis. Journal of the American Academy of Orthopaedic Surgeons. 2014. DOI: 10.5435/jaaos-22-06-390
[8] Finger Flexor Tenosynovitis From Stonefish Envenomation Injury. JAAOS: Global Research and Reviews. 2019. DOI: 10.5435/jaaosglobal-d-19-00024
[9] Paronychia: a Mixed Infection. Journal of Hand Surgery. 1993. DOI: 10.1016/0266-7681(93)90063-l
[10] Chronic Paronychia. Archives of Dermatology. 1962. DOI: 10.1001/archderm.1962.01590090066015
[11] Exam Of The Hand Wrist 2Ed. INTRODUCTION.
[14] Green S Operative Hand Surgery. GENERAL PRINCIPLES.
[15] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Bone and Soft-Tissue Infections of the Hand and Wrist > Soft-Tissue Infections > Hand Cellulitis and Abscesses.
[16] Campbell S Operative Orthopaedics 4 Volume Set. TUMORS AND TUMOROUS CONDITIONS OF THE HAND > TENOSYNOVITIS.
[17] Exam Of The Hand Wrist 2Ed. REFERENCES.
[18] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > Image DISORDERS OF THE MUSCULATURE OF THE HAND.
[19] Exam Of The Hand Wrist 2Ed. 1.1 SKELETON OF THE HAND > The osseous skeleton.
[20] Green S Operative Hand Surgery. Candidiasis.
[21] Green S Operative Hand Surgery. Clinical Manifestations of AIDS Infection in the Hands.
[23] Exam Of The Hand Wrist 2Ed. Functional cutaneous units.
[24] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[26] Exam Of The Hand Wrist 2Ed. The arches of the hand > The metacarpal arch.
[27] Exam Of The Hand Wrist 2Ed. Techniques of investigation of the arterial supply by J P Melki > Vascularization of the thumb > Palmar aspect.
[28] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > FLEXOR TENDON INJURY.
[29] Green S Operative Hand Surgery. Cutaneous Fungal Infections > Etiology and Epidemiology.
[30] Green S Operative Hand Surgery. Mycobacterial Osteomyelitis.
[32] Green S Operative Hand Surgery. CHRONIC BACTERIAL INFECTIONS > Actinomycosis.
[33] Green S Operative Hand Surgery. Clinical Findings.
[34] Campbell S Operative Orthopaedics 4 Volume Set. TUMORS AND TUMOROUS CONDITIONS OF THE HAND > SEPTIC ARTHRITIS.
[35] Aaos Comprehensive Orthopaedic Review 3. Infections of the Hand* > I Fingertip Infections.
[38] Campbell S Operative Orthopaedics 4 Volume Set. TUMORS AND TUMOROUS CONDITIONS OF THE HAND > GENERAL APPROACH TO HAND INFECTIONS.
[40] Green S Operative Hand Surgery. Histoplasmosis.
[42] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Bone and Soft-Tissue Infections of the Hand and Wrist > Bone Infections.
[44] Green S Operative Hand Surgery. Subcutaneous Fungal Infections.
[46] Green S Operative Hand Surgery. BOX 59.1 Ganglions of the Hand and Wrist > Ewing's Sarcoma.
[47] Green S Operative Hand Surgery. Staging.
[48] Campbell S Operative Orthopaedics 4 Volume Set. TUMORS AND TUMOROUS CONDITIONS OF THE HAND > HUMAN BITE INJURIES.