Patients › Shoulder
Phẫu thuật chỉnh sửa thay khớp vai
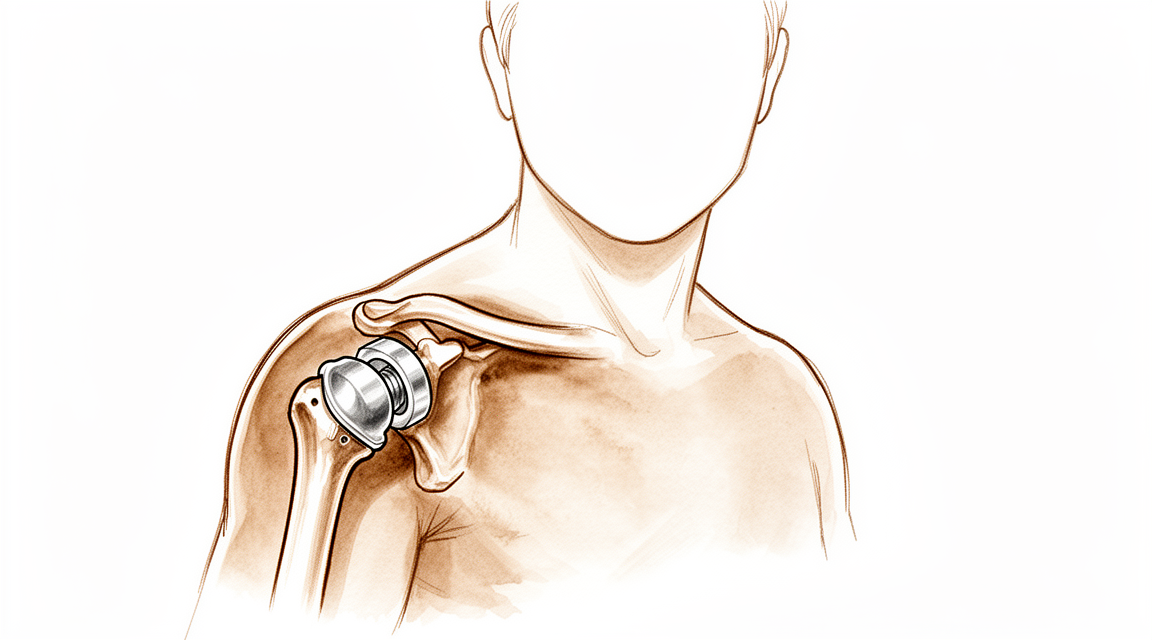
Revision shoulder replacement — addressing failure of prior shoulder replacements with a reverse design.
Lý do phẫu thuật này được đề xuất
Bác sĩ Kieran Hirpara, bác sĩ phẫu thuật chi trên tại Bệnh viện tư nhân Mater Rockhampton, luôn bắt đầu bằng các phương pháp ít xâm lấn nhất phù hợp với tình trạng của bệnh nhân. Thông thường, bệnh nhân được bác sĩ đa khoa giới thiệu đến phòng khám chúng tôi; nếu nhà vật lý trị liệu khuyên bạn nên đến gặp chúng tôi, bạn vẫn cần có giấy giới thiệu từ bác sĩ đa khoa để được hưởng mức hoàn trả từ chương trình Medicare. Trong lần khám đầu tiên, chúng tôi sẽ hỏi bệnh sử, khám vai và chỉ định chụp hình ảnh nếu cần thiết. Đối với các vấn đề đã kéo dài lâu năm, chúng tôi thường thử các phương pháp điều trị không phẫu thuật trước, chẳng hạn như thay đổi hoạt động sinh hoạt, vật lý trị liệu hoặc đeo nẹp; chỉ khi các phương pháp này không mang lại hiệu quả đáng kể thì chúng tôi mới cân nhắc phẫu thuật.
Phẫu thuật thay khớp vai lần thứ hai là ca mổ nhằm thay thế một phần hoặc toàn bộ các bộ phận của ca thay khớp vai trước đó. Chúng tôi đề xuất phương pháp này khi ca thay khớp ban đầu không còn hoạt động tốt nữa; nguyên nhân thường là do các bộ phận bị lỏng ra, khớp trở nên không ổn định hoặc ổ khớp bị mòn. Cơn đau dữ dội và tình trạng cứng khớp là những lý do chính khiến bệnh nhân tìm đến chúng tôi để thực hiện ca phẫu thuật này. Mục tiêu là giảm đau, cải thiện khả năng vận động và giúp vai ổn định hơn. Tỷ lệ sống sót của các bộ phận cấy ghép trong phẫu thuật thay khớp vai ngược lần thứ hai đạt 85% sau mười năm. Chúng tôi sẽ trao đổi với bạn về những lợi ích cũng như hạn chế của ca phẫu thuật này, rồi cùng nhau quyết định xem nó có phù hợp với bạn hay không.
Trước khi phẫu thuật
Vai của bạn sẽ cần được chụp hình để chúng tôi lên kế hoạch phẫu thuật. Thông thường, các phim X-quang thông thường chụp từ vài góc độ là đủ. Đôi khi chúng tôi cũng yêu cầu chụp MRI (phương pháp chụp hình cho thấy các mô mềm) hoặc siêu âm. Trước ngày phẫu thuật, bạn sẽ nhận được những hướng dẫn rõ ràng từ đội ngũ y tế của chúng tôi. Bạn cần nhịn ăn và uống trong vòng bảy giờ trước phẫu thuật. Chúng tôi yêu cầu thời gian nhịn ăn là bảy giờ thay vì sáu giờ như thông thường để có thể sắp xếp ca phẫu thuật sớm hơn nếu danh sách các ca phẫu thuật được lên trước. Hãy mang theo danh sách các loại thuốc mà bạn đang dùng; một số loại có thể cần phải ngưng sử dụng. Hãy sắp xếp người đưa đón bạn về nhà. Mặc quần áo rộng rãi và thoải mái. Nếu bạn mắc các bệnh lý khác, có thể bạn sẽ cần làm xét nghiệm máu hoặc được bác sĩ gây mê (chuyên gia phụ trách việc gây mê) thăm khám lại.
Vào ngày phẫu thuật
Bạn sẽ đến khu vực tiếp nhận bệnh nhân phẫu thuật của bệnh viện, nơi bạn sẽ được làm thủ tục nhập viện và chuẩn bị cho ca mổ. Sau đó, bạn sẽ gặp bác sĩ gây mê. Ca phẫu thuật này được thực hiện dưới gây mê toàn thân kết hợp với phong bế thần kinh vùng. Bác sĩ gây mê sẽ gặp bạn trước khi mổ và giải thích chi tiết về cả hai phương pháp gây mê này.
Tiếp theo, bạn sẽ được đưa vào phòng mổ để tiến hành ca phẫu thuật. Khi ca mổ hoàn tất, bạn sẽ tỉnh dậy tại khu vực hồi sức. Các điều dưỡng sẽ theo dõi tình trạng sức khỏe của bạn trong lúc thuốc mê dần hết tác dụng. Sau khi sức khỏe ổn định, bạn sẽ được chuyển sang phòng bệnh.
Quy trình phẫu thuật
Phẫu thuật thay khớp vai lần thứ hai là ca mổ mở được thực hiện qua một đường rạch duy nhất tại vùng cần phẫu thuật. Bác sĩ phẫu thuật sẽ tiến hành can thiệp qua đường rạch này để tiếp cận khớp vai.
Các bước thực hiện cụ thể phụ thuộc vào nguyên nhân khiến ca thay khớp lần đầu thất bại. Bác sĩ có thể loại bỏ một phần hoặc toàn bộ các bộ phận đã bị mòn hoặc lỏng lẻo, rồi thay thế bằng các bề mặt kim loại và nhựa mới. Nếu xương ổ khớp bị mòn nhiều, người ta có thể ghép một mảnh xương nhỏ (được lấy từ nơi khác trong cơ thể) để tái tạo lại vùng xương bị mất, từ đó lắp đặt bộ phận ổ khớp mới. Trong mọi trường hợp có thể, bác sĩ sẽ cố gắng lắp đặt lại bộ phận ổ khớp thay vì bỏ trống chỗ đó. Nếu khớp vai bị mất ổn định, bác sĩ có thể thay đổi thiết kế bộ phận thay thế thành loại “ngược”, trong đó vị trí của chỏm và ổ khớp được đảo ngược nhằm tăng độ vững chắc cho khớp. Đôi khi người ta giữ lại lớp xi măng cũ bao quanh phần khớp nối với cánh tay, rồi mới phủ thêm lớp xi măng mới thay vì phải loại bỏ hoàn toàn lớp cũ.
Sau khi các bộ phận mới đã được lắp đặt và kiểm tra xong, vết mổ sẽ được khâu lại. Đầu tiên, một tấm lưới dính mỏng được đặt lên vết mổ đã khâu nhằm giữ hai mép da lại với nhau; sau đó người ta phết một loại keo dán da lên trên tấm lưới này. Chất keo này sẽ đông lại và niêm phong toàn bộ vết mổ. Tấm lưới này sẽ tự bong ra sau khoảng một đến hai tuần, nên không cần phải cắt bỏ.
Sau phẫu thuật
Bạn sẽ tỉnh dậy tại khu vực hồi sức dưới sự chăm sóc của các y tá. Khi đã ổn định, bạn sẽ được chuyển sang phòng bệnh. Hầu hết bệnh nhân sẽ ở lại bệnh viện một hoặc hai đêm sau ca phẫu thuật này. Thuốc giảm đau sẽ được điều chỉnh phù hợp với từng bệnh nhân; hiệu quả gây tê thần kinh từ trong phòng mổ thường giúp giảm đau vùng vai trong những giờ đầu. Cánh tay của bạn sẽ được đặt trong chiếc đai treo đơn giản để tạo cảm giác thoải mái; chiếc đai này sẽ được tháo ra khi bạn tập luyện hoặc vệ sinh. Chúng tôi sẽ giữ băng gạc trên vết mổ khoảng 10 ngày; vui lòng không tự ý tháo ra trước thời hạn đó trừ khi có chỉ định của bác sĩ. Chúng tôi sẽ thay hoặc gỡ băng gạc khi khám lại cho bạn. Một chuyên viên vật lý trị liệu có thể đến để hướng dẫn các động tác vận động nhẹ nhàng. Vui lòng sắp xếp người thân ở bên cạnh bạn trong 24 giờ đầu sau khi về nhà.
Quá trình hồi phục
Những ngày đầu tiên là thời gian để nghỉ ngơi và giảm đau. Vai của bạn sẽ cảm thấy đau nhức và sưng tấy; hiệu ứng gây tê thần kinh sau phẫu thuật thường khiến vai tạm thời không đau. Khi tác dụng này giảm dần, cơn đau sẽ trở nên rõ rệt hơn. Việc dùng thuốc giảm đau phù hợp, nghỉ ngơi và vận động nhẹ nhàng đều có ích cho quá trình hồi phục. Tình trạng sưng sẽ dần thuyên giảm trong vài tuần đầu.
Để tăng cảm giác thoải mái, cánh tay của bạn sẽ được đặt trong chiếc đai treo đơn giản; chiếc đai này sẽ được tháo ra khi bạn thực hiện các bài tập hoặc vệ sinh. Chuyên viên vật lý trị liệu sẽ hướng dẫn bạn những động tác nhẹ nhàng ban đầu, sau đó dần tăng cường độ vận động để cải thiện sức mạnh và phạm vi chuyển động của vai khi tình trạng sức khỏe cho phép. Ban đầu, bạn sẽ cần sự trợ giúp trong các công việc nặng; tuy nhiên việc sử dụng cánh tay cho các hoạt động nhẹ sẽ dần trở lại bình thường. Trong những ngày đầu, việc ngủ ở tư thế ngồi thẳng hoặc tựa vào gối thường giúp cảm thấy dễ chịu hơn.
Quá trình hồi phục diễn ra theo từng giai đoạn chứ không diễn ra ngay lập tức. Khi bác sĩ phẫu thuật cho phép bạn lái xe, thường là sau lần tái khám ở tuần thứ sáu, bạn có thể trở lại lái xe; hãy tham khảo hướng dẫn của chúng tôi về việc lái xe sau phẫu thuật chi trên. Khi khả năng vận động cải thiện, các hoạt động thường ngày như mặc quần áo và nấu ăn cũng trở nên dễ dàng hơn. Khi vai đã đủ khỏe, hầu hết mọi người đều có thể quay lại làm việc; nhiều người thậm chí còn tiếp tục tham gia các môn thể thao hoặc hoạt động yêu thích. Phần lớn bệnh nhân nhận thấy vai của mình vẫn tiếp tục cải thiện trong suốt năm đầu sau phẫu thuật.
Lộ trình hồi phục của bạn có thể khác với người khác. Bác sĩ phẫu thuật và chuyên viên vật lý trị liệu sẽ hướng dẫn bạn trong từng lần tái khám và điều chỉnh kế hoạch điều trị sao cho phù hợp với tiến độ hồi phục của vai bạn.
Những biến chứng có thể xảy ra
Hầu hết bệnh nhân đều hồi phục tốt, nhưng đôi khi vẫn có thể gặp phải các vấn đề. Bác sĩ phẫu thuật và đội ngũ y tế sẽ theo dõi sát sao để phát hiện sớm bất kỳ bất thường nào.
Đôi khi các bộ phận nhân tạo có thể bị lỏng hoặc khớp trở nên không ổn định. Bạn có thể cảm thấy cơn đau trước đây quay trở lại, hoặc xuất hiện cơn đau mới chưa từng có sau phẫu thuật. Một số người còn cảm nhận được tiếng kêu lục cục, tiếng cọ xát, hoặc cảm giác vai bị trượt ra khỏi vị trí bình thường. Nếu gặp tình trạng này, hãy trao đổi với bác sĩ tại lần tái khám tiếp theo; nếu cơn đau ngày càng tăng, hãy gọi ngay cho phòng khám.
Nhiễm trùng là một nguy cơ tiềm ẩn trong mọi ca phẫu thuật thay khớp. Hãy chú ý nếu có cơn đau sâu, âm ỉ không thuyên giảm dù đã dùng thuốc giảm đau thông thường; vùng da quanh vết mổ bị đỏ rộng ra; vai có cảm giác nóng lên; hoặc xuất hiện sốt. Nếu nhận thấy bất kỳ dấu hiệu nào, hãy gọi ngay cho phòng khám. Nếu bạn cảm thấy mệt mỏi kèm sốt hoặc vùng đỏ lan rộng nhanh chóng, hãy đến ngay phòng cấp cứu.
Đôi khi xương xung quanh các bộ phận nhân tạo có thể bị gãy; tình trạng này thường được phát hiện qua các phim X-quang sớm sau phẫu thuật. Bạn sẽ cảm thấy cơn đau dữ dội đột ngột, mức độ nặng hơn nhiều so với cơn đau thông thường sau mổ; đôi khi còn nghe thấy tiếng “rắc” hoặc cảm giác yếu đi ở vùng vai. Nếu gặp phải tình huống này, hãy báo ngay cho bác sĩ phẫu thuật hoặc phòng khám.
Một số bệnh lý và yếu tố nhất định làm tăng nguy cơ gặp biến chứng, bao gồm bệnh Parkinson, tình trạng suy dinh dưỡng trước phẫu thuật, gãy xương do chấn thương nhẹ trước đó, đã từng phẫu thuật vai trước đây, viêm khớp do hệ miễn dịch hoạt động quá mức, phải dùng thuốc chống đông máu sau phẫu thuật, và việc phải phẫu thuật cả hai bên vai trong thời gian gần nhau. Nếu bạn thuộc nhóm này, chúng tôi sẽ tính đến các yếu tố đó khi lập kế hoạch điều trị và theo dõi bạn kỹ lưỡng hơn.
Bảng liệt kê các biến chứng dưới đây nêu rõ tỷ lệ xảy ra các vấn đề thường gặp nếu bạn muốn biết thông tin cụ thể.
Khi nào nên liên hệ với chúng tôi
Hãy gọi cho phòng khám nếu bạn bị sốt, vùng vết thương ngày càng đỏ lên hoặc có dịch tiết ra, hoặc cơn đau ngày càng tăng dần. Hãy đến phòng cấp cứu nếu bạn đột nhiên thấy khó thở, có hiện tượng sưng hoặc đau ở bắp chân, hoặc cơn đau vai xuất hiện đột ngột và dữ dội. Hãy liên hệ ngay với chúng tôi nếu bạn mất cảm giác ở cánh tay hoặc bàn tay, hoặc không thể cử động chúng. Nếu không chắc chắn, hãy gọi cho chúng tôi. Chúng tôi thà nhận được cuộc gọi từ bạn sớm hơn.
Nơi để tìm đọc thêm thông tin về bệnh lý
Trang này chỉ đề cập đến phương pháp phẫu thuật. Các thông tin chi tiết về bệnh lý được điều trị, bao gồm cả những bằng chứng cho thấy khi nào phẫu thuật có ích và khi nào không, đều được trình bày kỹ lưỡng hơn trên trang Viêm khớp vai.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Anatomy & Pathophysiology
Bony Anatomy
- The proximal humerus comprises four main parts: the humeral head, greater tuberosity, lesser tuberosity, and humeral shaft [3].
- The articular head of the proximal humerus is spherical with a diameter of 37 to 57 mm [3].
- The most superior portion of the articular surface of the humeral head averages 8 mm above the greater tuberosity [3].
- Humeral version averages 29.8 degrees, with a range of 10 to 55 degrees [3].
- The humeral head is inclined approximately 130 degrees with respect to the humeral shaft [3].
- The anatomic neck of the proximal humerus is located at the junction of the articular surface and the tuberosities [3].
- The surgical neck represents an indistinct region below the tuberosities but above the humeral shaft [3].
- The greater tuberosity serves as the attachment site for the supraspinatus, infraspinatus, and teres minor tendons [3].
- The lesser tuberosity serves as the attachment site for the subscapularis tendon [3].
- The glenoid is a convex structure of shallow depth shaped like an inverted pear [3].
- The glenoid cavity is a shallow socket, approximately one third the size of the humeral head [4].
- The neck-shaft angle measures an average of 135 degrees [4].
- The humeral head is retroverted an average of 30 degrees [4].
- The scapula is attached to the axial skeleton by the acromioclavicular and sternoclavicular joints [5].
- The glenoid is connected with the flat body of the scapula by the scapular neck [5].
- The coracoid process curves forwards from the superior surface of the scapular neck [5].
- The scapular spine ends in a flattened bony process, the acromion, which curves forwards [5].
- The highest concentration of bony mass in the scapula is located in the glenoid, the scapular neck, and the lateral border of the scapular body [5].
- Two bony pillars transmit compressive forces from the glenoid fossa: the lateral pillar and the spinal pillar [5].
- The lateral pillar connects the inferior border of the glenoid with the inferior angle [5].
- The spinal pillar arises from the central part of the glenoid and continues medially to become part of the base of the scapular spine [5].
- The weakest bone in the scapula is located primarily in the central part of the infraspinous fossa [5].
- The weakest area of the circumference of the biomechanical body of the scapula is the spinomedial angle [5].
- The subchondral bone of the glenoid is relatively flat, with articular concavity augmented by cartilage and a circumferential labrum [6].
- The glenoid averages 5° of retroversion in relation to the axis of the scapular body [6].
- The humeral head averages 19° of retroversion and 41° of inclination (neck-shaft angle) [6].
- The acromion has three ossification centers: the metacromion, mesoacromion, and preacromion [6].
- Failure of fusion of the acromial ossification centers results in os acromiale [6].
Vascular Anatomy
- The proximal humerus receives its blood supply from the anterior and posterior humeral circumflex branches from the third division of the axillary artery [3].
- The posterior humeral circumflex artery travels with the axillary nerve and enters the quadrilateral space posteriorly [3].
- The anterior humeral circumflex artery arises from the axillary artery at the inferior border of the subscapularis [3].
- The anterior humeral circumflex artery provides vascular inflow to the humeral head via its terminal anterolateral branch, known as the artery of Laing or arcuate artery [3].
- The ascending branch of the anterior humeral circumflex artery courses parallel to the lateral aspect of the long head biceps tendon [3].
- The ascending branch of the anterior humeral circumflex artery enters the humeral head at the interface of the bicipital groove and greater tuberosity [3].
- Injury to the arcuate artery may result in osteonecrosis of the humeral head [3].
- Additional extraosseous collateral branches can permit humeral head perfusion despite complete ligation of the arcuate artery [3].
- The major blood supply to the humeral head is through the ascending branch of the anterior humeral circumflex artery, which penetrates the head at the bicipital groove and becomes the arcuate artery [4].
- Fractures of the anatomic neck have a poor prognosis because of complete disruption of the blood supply to the head [4].
- The anterolateral ascending branch of the anterior humeral circumflex artery provides the primary blood supply to the humeral head [6].
- The terminal intraosseous portion of the anterior humeral circumflex artery enters at the proximal aspect of the intertubercular groove as the arcuate artery [6].
Soft Tissue & Ligamentous Anatomy
- The rotator cuff consists of four muscles: the subscapularis, supraspinatus, infraspinatus, and teres minor [4].
- The teres major is not a rotator cuff muscle [4].
- The rotator cuff muscles serve as depressors of the humeral head to allow the deltoid to efficiently abduct the humerus [4].
- The infraspinatus and teres minor are external rotators, while the subscapularis is an internal rotator of the humerus [4].
- The acromion, coracoacromial ligament, and coracoid process form the coracoacromial arch [3].
- The rotator cuff, subacromial bursa, and subdeltoid bursa pass underneath the coracoacromial arch [3].
- The subscapular bursa lies between the subscapularis tendon and the neck of the scapula [7].
- The subscapular bursa communicates with the joint cavity between the superior and middle glenohumeral ligaments [7].
- The subscapular bursa protects the tendon of the subscapularis at the point where it passes under the base of the coracoid process and over the neck of the scapula [7].
- The subscapular bursa often houses loose bodies in the shoulder [7].
- The subscapular bursa is a region in which synovitis of the shoulder may be most intense [7].
- The rotator interval is defined medially by the base of the coracoid, superiorly by the supraspinatus tendon, and inferiorly by the subscapularis tendon [6].
- The rotator interval contains the coracohumeral ligament, the superior glenohumeral ligament, and the intra-articular portion of the long head of the biceps tendon [6].
- Laxity of the rotator interval results in inferior laxity (the sulcus sign) [6].
- Contracture of the rotator interval is seen with adhesive capsulitis [6].
- The coracohumeral ligament restricts external rotation in adduction [6].
- The coracohumeral ligament is a static restraint to inferior and posterior translation in adduction and external rotation [6].
- The superior glenohumeral ligament is a primary static restraint against anterior translation with the arm at the side [6].
- With the coracohumeral ligament, the superior glenohumeral ligament forms a pulley that provides restraint against medial subluxation of the long head of the biceps tendon [6].
- The middle glenohumeral ligament is a primary static restraint against anterior translation with the arm in external rotation and 45° of abduction [6].
- The anterior band of the inferior glenohumeral ligament is a primary static restraint against anterior-inferior dislocation of the glenohumeral joint in 90° of abduction and external rotation [6].
- The posterior band of the inferior glenohumeral ligament is a primary static restraint against posterior-inferior translation in internal rotation and adduction [6].
- The glenoid labrum provides concavity and up to 50% of marginal glenoid socket depth [6].
- The superior transverse scapular ligament arises from the medial base of the coracoid overlying the suprascapular notch [6].
- The suprascapular artery runs superior to the superior transverse scapular ligament, while the nerve runs deep to it [6].
- Entrapment of the suprascapular nerve at the superior transverse scapular ligament causes denervation of both the supraspinatus and the infraspinatus [6].
- The spinoglenoid ligament overlies the suprascapular nerve at the spinoglenoid notch [6].
- Entrapment, traction, or compression of the suprascapular nerve at the spinoglenoid notch causes denervation of the infraspinatus [6].
Pathophysiology & Biomechanics
- Stability and function of the glenohumeral joint are provided by the interaction of structures that promote a near global range of motion and purposeful function [3].
- External loads transferred to the shoulder girdle are initially offset by joint surface anatomy, joint volume, atmospheric pressure, and joint fluid cohesion and adhesion [3].
- Moderate and large loads are counterbalanced by the deltoid and rotator cuff and by the capsulolabral and bone structures, respectively [3].
- Proximal humeral fractures alter complex interactions, resulting in pain, decreased range of motion and stiffness, and disability [3].
- Displacement of proximal humeral fracture fragments is based on the deforming forces created by the tendinous insertions of the pectoralis major, subscapularis, supraspinatus, and infraspinatus [3].
- The subscapularis inserts on the lesser tuberosity and causes medial displacement [3].
- The supraspinatus and infraspinatus insert on the greater tuberosity and cause superior and posterior displacement [3].
- The pectoralis major inserts on the humeral shaft and displaces it medially [3].
- A fracture involving the anatomic neck is prognostically worse than fractures involving other regions of the proximal humerus with respect to the potential disruption of the vascular supply to the humeral head and subsequent development of avascular necrosis [3].
- Displaced proximal humeral fractures can impede normal movement of structures passing under the coracoacromial arch, causing impingement and disruption of normal glenohumeral motion [3].
- In proximal humeral fractures, the subdeltoid and subacromial bursae can become thickened and fibrotic, forming adhesions that limit normal glenohumeral motion [3].
- The malcentering of the joint reaction force on the glenoid leads to posterior instability, posterior glenoid wear, and "rocking horse" loosening of prosthetic glenoid components [2].
- The point of contact of the humeral articular surface on the glenoid articular surface reflects the degree of centering of the net humeral joint reaction force on the glenoid [2].
- Arthritis usually involves the central aspect of the humeral head [2].
- Joint space narrowing is most evident on the axillary view taken with the arm in elevation compared to images made with the arm at the side [2].
- The axillary view taken with the arm in elevation demonstrates posterior subluxation or "functional decentering" that is not evident in images taken with the arm at the side [2].
- Dense scarring from previous operations commonly complicates the surgical approach in revision shoulder arthroplasty [15].
- Exposure in revision shoulder arthroplasty is typically quite difficult, making component implantation less predictable [15].
- Preexisting instability or subscapularis deficiency often is not correctable with an anatomic revision arthroplasty [15].
- The rotator cuff is often deficient in patients with massive (>4 cm) proximal humeral bone loss [15].
Investigations
Plain Radiography
- The purpose of shoulder imaging is to help establish the diagnosis, determine the severity of the pathoanatomy, assist in surgical planning, and enable the surgeon to illustrate the condition of the shoulder to the patient [2].
- Standardized plain films are almost always sufficient to garner the information needed for shoulder care [2].
- The first key radiographic view is the anteroposterior (AP) view taken in the plane of the scapula such that the x-ray beam passes through the glenohumeral joint [2].
- The AP view in the plane of the scapula shows the superoinferior position of the humeral head relative to the glenoid, the presence of osteophytes on the humeral head and glenoid, narrowing of the joint space, and the degree of medial displacement of the humerus in relation to the lateral acromial line [2].
- The AP view in the plane of the scapula also shows the quality of the humeral and glenoid bone, the presence of loose bodies, and whether there is humeral head collapse or deformity [2].
- The second key radiographic view is the axillary view taken with the arm in the functional position of elevation in the plane of the scapula [2].
- The axillary view is oriented so that both the spinoglenoid notch and the scapular neck are visible [2].
- The axillary view demonstrates a different perspective of humeral anatomy, the amount of glenoid bone, the shape of the glenoid, its version in relation to the plane of the scapula, and the relationship of the humeral head to the glenoid fossa [2].
- The axillary view is referred to as the “truth view” because it demonstrates glenohumeral relationships in the functional position of elevation [2].
- CT scans have the disadvantage of being taken with the arm in the adducted position, unlike the axillary truth view which is taken in elevation [2].
- Many axillary views sent for consultation are taken without standardization, making it impossible to determine important features of the glenohumeral joint [2].
- When taken properly, standardized anteroposterior and axillary views indicate the thickness of the cartilage space between the humerus and the glenoid, relative positions of the humeral head and glenoid, presence of osteophytes, degree of osteopenia, and extent of bony deformity and erosion [2].
- Joint space narrowing is most evident on the axillary truth view as opposed to images made with the arm at the side [2].
- The axillary truth view can show posterior subluxation or “functional decentering” that is not evident in images taken with the arm at the side [2].
- The degree of posterior subluxation can be measured as the position of the center of the humeral head in relation to the plane of the scapula [2].
- The degree of posterior subluxation can be measured as the position of the center of the humeral head in relation to the glenoid face [2].
- The degree of posterior subluxation can be measured as the point of contact of the humeral articular surface on the glenoid articular surface [2].
- Malcentering of the joint reaction force leads to posterior instability, posterior glenoid wear, and “rocking horse” loosening of prosthetic glenoid components [2].
- At least two X-ray views should be obtained: an anteroposterior in the plane of the glenoid and an axillary projection with the arm in abduction to show the relationship of the humeral head to the glenoid [11].
Computed Tomography
- CT scans may offer a few degrees of increased precision in the measurement of glenoid version [2].
- The authors are not convinced that the increased precision of CT scans in measuring glenoid version improves the quality of the surgery or the clinical outcome [2].
- There is information that can be gathered from properly taken plain films that cannot be obtained from CT scans [2].
- Three-dimensional reconstructions can reveal fine details of the shoulder anatomy, but this additional information rarely changes the planning or conduct of the arthroplasty [2].
- Computed tomography (CT) is helpful for planning fracture surgery and shoulder joint replacement [11].
Magnetic Resonance Imaging
- Magnetic resonance imaging (MRI) is useful to identify osteonecrosis of the humeral head, or a bone tumour [11].
- MRI can identify labral tears and rotator cuff tears [11].
- The accuracy of MRI for identifying labral tears and rotator cuff tears is enhanced by combining the scan with arthrography [11].
Ultrasonography
- Ultrasonography is a simple and accurate test for identifying rotator cuff tears and calcific tendinitis [11].
- Ultrasonography can be useful in guiding injections or barbotage (aspirating calcific deposits in the rotator cuff) [11].
- The most commonly performed joint examination using ultrasonography is the shoulder examination [9].
- The accuracy of rotator cuff ultrasonography depends on the skill of the scanner operator and an awareness of pitfalls that are encountered [9].
General Imaging Principles
- The diagnosis of a stiff shoulder depends on awareness of the problem, with history and physical examination being paramount and ancillary studies helpful in certain circumstances [1].
- Unless a specific research protocol is in place, the temptation to “overimage” should be resisted, obtaining only the scans or reconstructions that are necessary for the care of the patient [2].
- Proper radiographic technique is as important as proper surgical technique to achieve the desired outcome [2].
- The shoulder is a three-dimensional structure that cannot be represented by a single planar view [13].
- Critical relationships, such as the degree of centering of the humeral head, change with the position of the arm [13].
- Shoulder pathology may be found in a large number of different bones and soft tissues [13].
- Overlying and superimposed structures as well as metallic implants may complicate imaging the structures of interest [13].
- Surgeons need to develop a judicious approach to imaging that yields the information necessary to treat the patient while avoiding the tendency to "over-image" [13].
References
[1] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > SUMMARY.
[2] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Radiographic Evaluation.
[3] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > ANATOMY.
[4] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > SHOULDER AND ARM INJURIES.
[5] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Applied Anatomy Related to Scapular Fractures.
[6] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Shoulder, Arm, and Elbow > I. Shoulder.
[7] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > Bursae.
[9] Orthopaedic Knowledge Update Sports Medicine 6. Diagnostic Ultrasonography and Ultrasonography-Guided Procedures > Annotated References.
[11] Apley And Solomon S Concise System Of Orthopaedics And Trauma. INVESTIGATION.
[13] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > SENIOR EDITOR COMMENTARY.
[15] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTIVE PROCEDURES OF THE SHOULDER AND ELBOW IN ADULTS > REVISION SHOULDER ARTHROPLASTY > INDICATIONS.