Patients › General-Health
Huyết tương giàu tiểu cầu (PRP) và các liệu pháp tiêm
What the evidence shows for platelet-rich plasma and related injection therapies in tendinopathy, osteoarthritis and rotator cuff disease — where they help and where the data is weak.
Định nghĩa
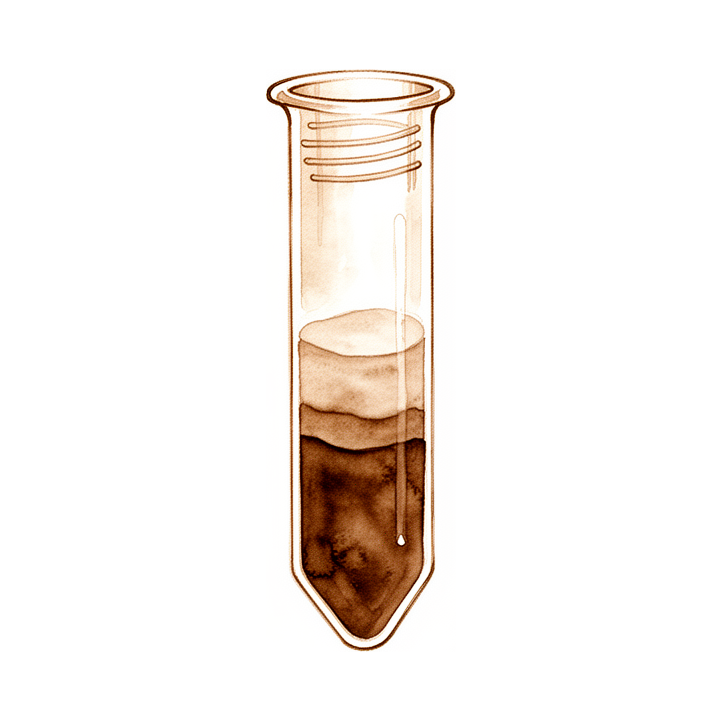
Huyết tương giàu tiểu cầu, thường được viết tắt là PRP, là một phương pháp điều trị được bào chế từ chính máu của bạn. Một mẫu máu nhỏ của bạn được quay trong một chiếc máy để tách riêng và cô đặc tiểu cầu. Tiểu cầu là những thành phần rất nhỏ trong máu giúp máu đông lại, và chúng cũng mang các yếu tố tăng trưởng, là những chất tự nhiên có thể hỗ trợ quá trình lành thương. Sau đó, tiểu cầu đã được cô đặc sẽ được tiêm vào vùng bị đau.
Bác sĩ có thể cân nhắc PRP cho các vấn đề như thoái hóa khớp gối (viêm khớp do hao mòn), các vấn đề về gân ở khuỷu tay, vai hoặc cổ tay, và một số chấn thương cơ trong thể thao. PRP không được dùng cho mọi bệnh lý. Với khuỷu tay quần vợt, bằng chứng chưa thống nhất: một số nghiên cứu cho thấy PRP hiệu quả hơn tiêm steroid về lâu dài [1], trong khi một tổng quan các thử nghiệm lại không ủng hộ PRP so với giả dược [2]. Với thoái hóa khớp gối, thường được khuyến nghị tiêm hai mũi, với tác dụng kéo dài ít nhất 24 tuần [3]. Với hội chứng ống cổ tay, PRP cho thấy lợi ích bền vững hơn so với tiêm steroid ở lần theo dõi sau 6 tháng [4].
Ý tưởng đằng sau PRP là các yếu tố tăng trưởng trong tiểu cầu có thể làm giảm viêm và thúc đẩy quá trình sửa chữa mô. Các nhà nghiên cứu vẫn đang tìm hiểu các chi tiết. Các nghiên cứu cho thấy những cách bào chế khác nhau có tác dụng khác nhau: một loại giàu bạch cầu dường như phù hợp với giai đoạn thoái hóa khớp sớm, trong khi một loại khác có nhiều tiểu cầu hơn và ít bạch cầu hơn có thể phù hợp với các giai đoạn muộn hơn [5]. Một số thử nghiệm cho thấy PRP hiệu quả hơn tiêm thuốc tê đối với các vấn đề về gân ở vai và khuỷu tay, nhưng không hiệu quả hơn châm kim khô hoặc tiêm nước muối [6]. Nhìn chung, bằng chứng khác nhau tùy theo từng bệnh lý, và bác sĩ sẽ trao đổi với bạn về việc PRP có hợp lý cho vấn đề cụ thể của bạn hay không.
Phương pháp này có hiệu quả không?
Câu trả lời thẳng thắn là còn tùy vào bệnh lý, và trong một số trường hợp, các nghiên cứu vẫn chưa theo kịp. Một tổng quan bằng chứng cho thấy PRP là một phương pháp điều trị có tiềm năng đáng quan tâm, nhưng hiện chưa có đủ nghiên cứu chất lượng tốt để ủng hộ việc sử dụng rộng rãi [7]. Các nhà nghiên cứu cũng lưu ý rằng một số bản tóm tắt các thử nghiệm PRP cho thoái hóa khớp gối đã trình bày kết quả theo hướng tích cực quá mức, điều này có thể khiến phương pháp điều trị trông tốt hơn so với những gì bằng chứng thực sự cho thấy [8].
Với một số bệnh lý, kết quả đáng khích lệ hơn. Với các vấn đề về gân, các thử nghiệm cho thấy PRP cải thiện cơn đau và chức năng của bộ phận bị ảnh hưởng, và hiệu quả hơn tiêm steroid trong trung hạn [9]. Với thoái hóa khớp gối, PRP cải thiện chức năng tổng thể, đặc biệt ở những người trẻ tuổi hơn [10]. Kết hợp PRP với axit hyaluronic, một chất bôi trơn có sẵn tự nhiên trong khớp, giúp giảm đau và cải thiện chức năng tốt hơn so với chỉ dùng PRP đơn thuần [11].
Với những bệnh lý khác, bức tranh chưa thống nhất hoặc chưa rõ ràng. Với khuỷu tay quần vợt, một số thử nghiệm cho thấy PRP giảm đau và cải thiện chức năng trong những tháng đầu [12], trong khi các nghiên cứu khác không ủng hộ PRP như một phương pháp điều trị [2]. Với rách chóp xoay, chưa có đủ bằng chứng tốt để kết luận theo hướng nào [13]. Với sụn khớp gối bị tổn thương, bằng chứng hiện chưa ủng hộ việc chỉ tiêm PRP đơn thuần [14].
Điều này có ý nghĩa gì đối với bạn? PRP có thể giúp ích cho một số vấn đề, nhưng không phải là giải pháp đã được chứng minh cho mọi thứ. Bác sĩ sẽ trao đổi với bạn về những gì bằng chứng cho thấy đối với bệnh lý cụ thể của bạn, để hai bên cùng quyết định liệu có đáng thử hay không.
Những rủi ro là gì?
PRP được bào chế từ chính máu của bạn, vì vậy cơ thể bạn ít có khả năng phản ứng xấu với bản thân chế phẩm này. Điều đó không có nghĩa là phương pháp điều trị hoàn toàn không có rủi ro. Bản thân mũi tiêm có thể gây đau, sưng và cứng trong những ngày sau đó, và vùng được điều trị có thể đau nhức trước khi cảm thấy đỡ hơn. Bác sĩ sẽ hướng dẫn bạn cách xử trí tình trạng này.
Nghiên cứu về PRP cho thoái hóa khớp gối vẫn chưa giải đáp dứt khoát được câu hỏi về mức độ hiệu quả của nó, và một số bản tóm tắt đã công bố đã trình bày kết quả theo hướng tích cực quá mức [8]. Điều đó quan trọng khi bạn đang cân nhắc có nên tiến hành hay không, vì một phương pháp điều trị nghe có vẻ hứa hẹn có thể không mang lại mức giảm đau như bạn mong đợi. Với phẫu thuật khâu chóp xoay, việc bổ sung PRP làm tăng tỷ lệ lành nhưng không làm thay đổi khả năng sử dụng vai của bệnh nhân trong sinh hoạt hằng ngày [15]. Với các vấn đề về gân Achilles, các thử nghiệm cho thấy PRP không hiệu quả hơn giả dược [16].
Cơ thể bạn đáp ứng như thế nào cũng có thể phụ thuộc vào hoàn cảnh của bạn. Việc đã từng tiêm corticosteroid trước đó và việc sử dụng thuốc lá dường như làm giảm hiệu quả của PRP đối với viêm lồi cầu trong mạn tính, một vấn đề về gân ở mặt trong khuỷu tay [17]. Nếu bạn hút thuốc hoặc đã từng tiêm steroid vào cùng vùng đó, hãy cho bác sĩ biết trước khi quyết định điều trị.
Một số câu hỏi vẫn còn bỏ ngỏ. Các nhà nghiên cứu lưu ý rằng cần thêm nghiên cứu để xác nhận tác dụng lâu dài của PRP [18]. Các nghiên cứu về PRP cho khuỷu tay quần vợt cho kết quả không thống nhất, với một số thử nghiệm ghi nhận giảm đau và cải thiện chức năng sớm [12] và những thử nghiệm khác không thấy lợi ích rõ ràng so với giả dược [2]. Cũng chưa có đủ bằng chứng tốt để ủng hộ việc chỉ tiêm PRP đơn thuần cho sụn khớp gối bị tổn thương [14].
Nếu bạn nhận thấy tình trạng đau, đỏ hoặc nóng ngày càng tăng quanh vị trí tiêm trong những ngày sau điều trị, hãy liên hệ với phòng khám để chúng tôi kiểm tra. Bác sĩ sẽ trao đổi với bạn về những rủi ro cụ thể đối với bệnh lý của bạn trước khi bạn quyết định có tiến hành hay không.
Liệu phương pháp này có phù hợp với bạn không?
PRP thường phù hợp với một số người hơn so với những người khác. Nếu bạn bị thoái hóa khớp gối, khuyến nghị là tiêm ít nhất hai mũi, với tác dụng kéo dài ít nhất 24 tuần [3]. Nếu bạn chơi thể thao thi đấu, các nhà nghiên cứu đã khuyến nghị áp dụng liệu pháp PRP cho những người chơi thể thao thi đấu [19]. Nếu bạn bị hội chứng ống cổ tay ở cả hai cổ tay, PRP cho thấy lợi ích bền vững hơn so với tiêm steroid ở lần theo dõi sau 6 tháng [4].
Có những trường hợp PRP ít có khả năng là lựa chọn phù hợp. Nếu sụn khớp gối của bạn bị tổn thương, bằng chứng hiện chưa ủng hộ việc chỉ tiêm PRP đơn thuần [14]. Với khuỷu tay quần vợt, bằng chứng chưa thống nhất, vì vậy PRP có thể giúp ích hoặc không giúp ích cho bạn. Nếu bạn hút thuốc hoặc trước đây đã từng tiêm steroid vào cùng vùng đó, PRP có thể kém hiệu quả hơn đối với bạn.
PRP là một trong nhiều lựa chọn. Tiêm steroid là phương pháp thay thế chính cho một số bệnh lý, và trong một số trường hợp PRP đã cho thấy lợi ích kéo dài hơn so với steroid [4]. Một lựa chọn khác là axit hyaluronic, một chất bôi trơn có sẵn tự nhiên trong khớp. Các nghiên cứu so sánh hai phương pháp này vẫn đang ở giai đoạn đầu, vì vậy bác sĩ sẽ giải thích cho bạn những gì đã biết cho đến nay.
Đây nên là quyết định chung giữa bạn và bác sĩ. Hãy suy nghĩ về mục tiêu của bạn, bệnh lý của bạn và những gì bằng chứng cho thấy đối với bệnh lý đó. Bác sĩ sẽ trao đổi với bạn về các lựa chọn, bao gồm cả những rủi ro đã nêu ở phần trên, để hai bên cùng quyết định liệu PRP có hợp lý với bạn hay không.
Tóm lại
PRP đáng để cân nhắc đối với một số vấn đề, nhưng hãy giữ kỳ vọng thực tế. Phương pháp này có thể giúp giảm đau và cải thiện chức năng đối với thoái hóa khớp gối và một số bệnh lý về gân, mặc dù kết quả khác nhau ở mỗi người. Lưu ý quan trọng nhất là các nghiên cứu vẫn chưa theo kịp, và đối với một số bệnh lý, hiện chưa có đủ bằng chứng chất lượng tốt để ủng hộ việc sử dụng rộng rãi [7]. Bác sĩ sẽ giúp bạn cân nhắc liệu phương pháp này có hợp lý cho vấn đề cụ thể của bạn hay không.
Tài liệu tham khảo
[1] A Randomized Controlled Trial of 1-Year Clinical Outcomes of a Single Platelet-Rich Plasma Injection Versus Corticosteroid for the Treatment of Lateral Elbow Tendinopathy. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671251386862
[2] Platelet-Rich Plasma Does Not Improve Pain or Function in Patients With Lateral Epicondylitis as Compared With Placebo: A Meta-analysis of Randomized Clinical Trials. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251383039
[3] Efficacy of multiple autologous apheresis platelet-rich plasma injections for treating knee osteoarthritis and its influencing factors: a retrospective cohort study. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05756-6
[4] Comparison of the effectiveness of platelet-rich plasma (PRP) injection and steroid injection in patients with bilateral moderate carpal tunnel syndrome: a prospective randomized controlled trial. Injury. 2026. DOI: 10.1016/j.injury.2026.113018
[5] The efficacy of platelet-rich plasma preparation protocols in the treatment of osteoarthritis: a network meta-analysis of randomized controlled trials. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06026-1
[6] Update on Platelet-rich Plasma for Shoulder and Elbow Tendinopathy. Techniques in Shoulder & Elbow Surgery. 2017. DOI: 10.1097/bte.0000000000000118
[7] Platelet-Rich Plasma for Chronic Tennis Elbow: Letters to the Editor. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546513512784
[8] Statistically Significant Results Favored in Abstracts of Platelet Rich Plasma Treatment of Knee Osteoarthritis: A Systematic Review and Spin Analysis. Arthroscopy. 2026. DOI: 10.1002/arj.70027
[9] Platelet-rich plasma and corticosteroid injection for tendinopathy: a systematic review and meta-analysis. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08566-3
[10] Investigating the therapeutic impact of platelet-rich plasma on knee, hip, and traumatic osteoarthritis: a meta-analysis and systematic review. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09486-6
[11] RETRACTED ARTICLE: A meta-analysis and systematic review of the clinical efficacy and safety of platelet-rich plasma combined with hyaluronic acid (PRP + HA) versus PRP monotherapy for knee osteoarthritis (KOA). Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-024-05429-w
[12] Poster 58: Decreased Pain After Platelet-Rich Plasma Injection in Lateral Epicondylitis Patients in the Early Follow-up Period. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/2325967125s00169
[13] Use of Platelet-Rich Plasma for the Improvement of Pain and Function in Rotator Cuff Tears: Response. The American Journal of Sports Medicine. 2020. DOI: 10.1177/0363546520918190
[14] Orthobiologic Injections Adjunctive to Cartilage‐Preserving Surgery May Improve Outcomes for Focal Knee Chondral Defects: A Systematic Review of Randomized Controlled Trials With Subgroup Meta‐analyses. Arthroscopy. 2026. DOI: 10.1002/arj.70548
[15] Injection of Leukocyte‐Poor Platelet‐Rich Plasma During Rotator Cuff Repair Can Increase Healing Rate but Does Not Affect Clinical Outcomes: A Systematic Review and Meta‐analysis of Randomized Controlled Trials. Arthroscopy. 2026. DOI: 10.1002/arj.70537
[16] Editor’s Spotlight/Take 5: Is Platelet-rich Plasma Effective in Treating Achilles Tendinopathy? A Meta-analysis of Randomized Clinical Trials. Clinical Orthopaedics & Related Research. 2025. DOI: 10.1097/corr.0000000000003478
[17] Efficacy of platelet-rich plasma injections for chronic medial epicondylitis. Journal of Hand Surgery (European Volume). 2015. DOI: 10.1177/1753193414567012
[18] Overview of Available Treatments and Their Limitations for Hypertrophic Facet Joints—A Systematic Review of the Literature. JAAOS: Global Research and Reviews. 2025. DOI: 10.5435/jaaosglobal-d-24-00140
[19] Platelet-rich plasma treatment for large joint osteoarthritis: retrospective study highlighting a possible treatment protocol with long-lasting stimulation of the joint with an adequate dose of platelets. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08663-3
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- PRP remains a potentially interesting intervention for chronic tennis elbow but currently lacks sufficient high-quality evidence of effectiveness to warrant widespread use [1].
- At least two PRP injections are recommended for treating knee osteoarthritis, with effects lasting for at least 24 weeks [2].
- The conclusions of the study on PRP for knee osteoarthritis do not provide a conclusive statement but aim to stimulate further research and shed light on factors influencing efficacy in clinical practice [3].
- There is no definitive evidence regarding the effectiveness of PRP treatment when the literature is evaluated [4].
- Further studies are needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the future [5].
- Conclusions regarding the clinical utility of PRP should be interpreted with caution due to major methodological concerns, including lack of PRP characterization and short-term follow-up [6].
- Future studies should prioritize long-term outcomes to guide clinical decision-making more effectively [6].
- Both leukocyte-rich (L-PRP) and leukocyte-poor (LP-PRP) are effective treatment options with comparable efficacy based on current evidence [7].
- PRP was superior to anesthetics in 2 studies for shoulder and elbow tendinopathy [8].
- PRP showed no clinical efficacy compared with dry needling or saline injections in 3 studies for shoulder and elbow tendinopathy [8].
- Interventions employing PRP, MSCs, and exosomes are considered in the context of degenerative osteoarthritis as a reversible chronic disease [9].
- Findings from a randomized controlled trial refute claims of PRP equivalence to placebo and support its efficacy over placebo in chronic tenosynovitis [10].
- The authors recommend systematically offering PRP therapy for competition sports practitioners [11].
- PRP provides a greater clinical improvement at 12 weeks than a single corticosteroid injection for gluteal tendinopathy [12].
- The authors argue that they fulfilled the reporting requirements for the injected PRP product as defined by MIBO [13].
- PRP demonstrated some indications of more sustained benefits, particularly at the 6-month follow-up, compared to steroid injection in bilateral moderate carpal tunnel syndrome [14].
- Rigorous basic, translational, and clinical research remains fundamental to realize the promise of PRP treatment for musculoskeletal disease [15].
- There is insufficient evidence to recommend for or against the use of PRP for rotator cuff tears given the heterogeneity of the literature and the inability of effect sizes to reach MCID values even when significant [16].
- Current evidence supports the selective use of PRP in sports settings for acute muscle injuries, though standardization in protocols and outcomes is needed [18].
- Studies evaluating the outcomes and procedures of the use of PRP in the setting of lateral epicondylitis have poor adherence to MIBO guidelines [22].
- The statement regarding the standard of care for knee osteoarthritis was intended to reflect frequent clinical use of hyaluronic acid and platelet-rich plasma rather than formal guideline recommendations [24].
- Findings from a meta-analysis of randomized clinical trials do not support PRP as a recommended treatment for lateral epicondylitis as compared with placebo [27].
- It is recommended to wait for at least one month before considering another injection or alternative treatments for first presentation trigger digits [28].
- The authors do not support the routine use of PRP for the treatment of greater trochanteric pain syndrome [29].
How It Works
Tendinopathy and Soft Tissue
- PRP was superior to anesthetics in 2 studies but showed no clinical efficacy compared with dry needling or saline injections in 3 studies for shoulder and elbow tendinopathy [8].
- A direct, linear relationship was observed between the concentration factor of PRP used and the magnitude of patient-reported symptom relief after PRP injection for lateral epicondylitis [23].
- High-dose PRP showed significant efficacy over alternative treatment strategies for lateral epicondylitis [23].
- Corticosteroids resulted in greater short-term improvement, while PRP demonstrated superior longer-term outcomes at 6 and 12 months for lateral elbow tendinopathy [20].
- PRP is no more effective than placebo for treating Achilles tendinopathy [21].
- Previous corticosteroid injections and tobacco seem to unfavourably affect the response to PRP for chronic medial epicondylitis [35].
- Time-dependent growth factor kinetics and platelet concentration influence clinical response following PRP versus saline in chronic tenosynovitis [10].
- Findings from a randomized controlled trial refute claims of PRP equivalence to placebo and support its efficacy over placebo for chronic tenosynovitis [10].
- PRP enhances anabolic gene expression patterns in flexor digitorum superficialis tendons [34].
- An innovative biological approach to the treatment of muscle injuries is the application of Plasma Rich in Growth Factors (PRGF) in intramuscular infiltrations [32].
Osteoarthritis
- At least two PRP injections are recommended for knee osteoarthritis, with effects lasting for at least 24 weeks [2].
- Both leukocyte-rich PRP (L-PRP) and leukocyte-poor PRP (LP-PRP) are effective treatment options with comparable efficacy for knee osteoarthritis based on current evidence [7].
- Optimizing osteoarthritis treatment involves tailoring PRP protocols to disease stage, with low platelet, high leukocyte PRP recommended for early OA due to its anti-inflammatory effects [36].
- High platelet, low leukocyte PRP is preferred for advanced osteoarthritis to promote tissue repair and regeneration [36].
- The improvement from PRP injections for knee osteoarthritis is clinically significant and influenced by platelet concentration [3].
- PRP demonstrated some indications of more sustained benefits, particularly at the 6-month follow-up, compared to steroid injection for bilateral moderate carpal tunnel syndrome [14].
- The study compared the efficacy of intra-articular injections of platelet-rich plasma (PRP) and viscosupplementation (hyaluronic acid [HA]) for the treatment of knee degenerative cartilage lesions and osteoarthritis [19].
- The authors recommend systematically offering PRP therapy for competition sports practitioners with large joint osteoarthritis [11].
- Further studies will be needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the future for hypertrophic facet joints [5].
Fracture Healing and Nonunion
- The effectiveness rate for excellent and good limb function was 85.19% in the combined group (PRP plus extracorporeal shock wave) versus 60.71% in the PRP group for long diaphysis aseptic nonunion [25].
- At final follow-up, all patients in the PRP-enhanced group healed, while 80.49% of the non-PRP group healed for aseptic femoral shaft nonunion (p = 0.049) [37].
- Although PRP has been reported in literature to be a biological treatment which increases healing, adequate healing was not determined in the patient group of a specific study on delayed union or non-union [31].
Rotator Cuff Repair
- LP-PRP augmentation increases healing rates but does not affect clinically meaningful functional outcomes for rotator cuff repair [40].
- The authors state that the significant difference in the retear rate, even in an underpowered study, has further confirmed the positive effect of platelet-rich plasma (PRP) for arthroscopic repair of medium to large rotator cuff tears [26].
General Mechanisms and Evidence Status
- PRP remains a potentially interesting intervention but is currently lacking sufficient high-quality evidence of effectiveness to warrant widespread use for chronic tennis elbow [1].
- The authors' conclusions regarding the clinical utility of PRP should be interpreted with caution due to major methodological concerns, including lack of PRP characterization and short-term follow-up [6].
- Future studies should prioritize long-term outcomes to guide clinical decision-making more effectively for PRP [6].
- The goal of a specific study was to discern key molecular mediators between leukocyte-rich PRP (LR-PRP) and leukocyte-poor PRP (LP-PRP) derived from the same patient with equivalent platelet concentrations [33].
- The authors agree that results from an in vitro study should be interpreted with caution and mention a subsequent prospective randomized double-blind clinical trial comparing autogenous PRP to HA for the treatment of OA [17].
- The PRP used in a specific study came from healthy donors, which may encourage research toward the use of allogeneic healthy PRP [38].
What the Evidence Shows
Tendinopathy and Soft Tissue Injuries
- A meta-analysis of randomized clinical trials found that PRP is no more effective than placebo for treating Achilles tendinopathy and should not be used for this indication until new, large, high-quality RCTs upend current knowledge [21].
- A meta-analysis of randomized clinical trials found that PRP does not improve pain or function in patients with lateral epicondylitis as compared with placebo and does not support PRP as a recommended treatment for this condition [27].
- A direct, linear relationship was observed between the concentration factor of PRP used and the magnitude of patient-reported symptom relief after PRP injection for lateral epicondylitis, with high-dose PRP showing significant efficacy over alternative treatment strategies [23].
- PRP injections are a safe and effective conservative treatment method for reducing pain symptoms and increasing functionality in patients with lateral epicondylitis in the early follow-up period [45].
- After autologous blood injection therapy, 22 patients (79%) in whom nonsurgical modalities had failed were relieved completely of pain even during strenuous activity for refractory lateral epicondylitis [47].
- PRP can effectively improve pain and functional impairment in patients with tendinopathy, and its midterm efficacy is superior to that of corticosteroids [43].
- PRP demonstrated some indications of more sustained benefits, particularly at the 6-month follow-up, compared to steroid injection in patients with bilateral moderate carpal tunnel syndrome [14].
Osteoarthritis
- A double-blind randomized controlled trial demonstrated that leukocytes did not affect the safety and efficacy of intra-articular PRP injections for the treatment of patients with knee osteoarthritis [41].
- Intra-articular PRP injection is an effective treatment for improving overall function in patients with primary osteoarthritis, particularly in younger individuals [46].
- For patients with knee osteoarthritis, PRP combined with hyaluronic acid (HA) therapy is safe and yields better outcomes in pain relief and functional improvement compared to PRP monotherapy [44].
- The combination of PRP with non-crosslinked HA in mono-injection was found to be non-inferior to crosslinked HA, with regards to the percentage of responders over 6 months (WOMAC pain) for knee osteoarthritis [49].
- Spin bias is highly prevalent in the abstracts of systematic reviews and meta-analyses of intra-articular PRP to treat knee osteoarthritis, with identified spin tending to favor the use of PRP [48].
- Further studies will be needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the treatment of hypertrophic facet joints [5].
Rotator Cuff and Shoulder
- Among level 1 RCTs reporting VAS pain scores after PRP injection for partial-thickness rotator cuff tears, platelet concentration was not significantly associated with improved pain outcomes [50].
Other Indications and Methodology
- The application of PRP following core decompression results in significant pain relief, improved short-term functional outcomes, and enhanced quality of life compared to core decompression alone for early osteonecrosis of the femoral head [42].
- Current evidence is insufficient to support orthobiologic injections adjunctive to cartilage-preserving surgery as standalone procedures for focal knee chondral defects [30].
Practical Considerations
General Evidence Status and Research Needs
- PRP remains a potentially interesting intervention but is currently lacking sufficient high-quality evidence of effectiveness to warrant widespread use [1].
- There is no definitive evidence regarding the effectiveness of PRP treatment [4].
- Further studies will be needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the future [5].
- Current evidence supports the selective use of PRP in sports settings, though standardization in protocols and outcomes is needed [18].
Dosing, Protocol, and Preparation
- At least two PRP injections are recommended, with effects lasting for at least 24 weeks [2].
- Both L-PRP and LP-PRP are effective treatment options with comparable efficacy based on current evidence [7].
Indication-Specific Outcomes and Comparisons
- These findings refute claims of PRP equivalence to placebo and support its efficacy over placebo in chronic tenosynovitis [10].
- PRP is no more effective than placebo for treating Achilles tendinopathy and should not be used for this indication until new, large, high-quality RCTs upend current knowledge [21].
- There is insufficient evidence to recommend for or against the use of PRP given the heterogeneity of the literature and the inability of effect sizes to reach MCID values even when significant for rotator cuff tears [16].
- The economic value of LP-PRP is conditional rather than uniform and depends on revision probability and preparation cost after arthroscopic rotator cuff repair [39].
- Current evidence is insufficient to support orthobiologic injections as standalone procedures for focal knee chondral defects [30].
Methodological and Interpretive Caveats
- The conclusions of a study on intra-articular PRP injections for knee osteoarthritis do not intend to provide a conclusive statement but rather to stimulate further research [3].
- The authors clarify that their statement regarding the standard of care for knee osteoarthritis was intended to reflect frequent clinical use of hyaluronic acid and platelet-rich plasma rather than formal guideline recommendations [24].
Key Evidence
- [L5] The authors conclude that PRP remains a potentially interesting intervention but is currently lacking sufficient high-quality evidence of effectiveness to warrant widespread use. [1] (10.1177/0363546513512784)
- [L3] At least two PRP injections are recommended, with effects lasting for at least 24 weeks. [2] (10.1186/s13018-025-05756-6)
- [Paper] The conclusions of this study do not intend to provide a conclusive statement but rather to stimulate further research in this complex field and contribute to shedding light on the several aspects influencing the efficacy of intra-articular platelet-rich plasma (PRP) injections for knee osteoarthritis (OA) in clinical practice. [3] (10.1177/03635465251387701)
- [L5] When the literature is evaluated, it is understood that there is no definitive evidence regarding the effectiveness of PRP treatment. [4] (10.1177/23259671241255700)
- [L4] Further studies will be needed to evaluate PRP’s long-term efficacy and cost-effectiveness for practical patient use in the future. [5] (10.5435/jaaosglobal-d-24-00140)
- [L5] The authors' conclusions regarding the clinical utility of PRP should be interpreted with caution due to major methodological concerns, including lack of PRP characterization and short-term follow-up; future studies should prioritize long-term outcomes to guide clinical decision-making more effectively. [6] (10.1016/j.arth.2025.05.007)
- [L1] Both L-PRP and LP-PRP are effective treatment options with comparable efficacy based on current evidence. [7] (10.1186/s13018-026-06689-4)
- [L1] PRP was superior to anesthetics in 2 studies but showed no clinical efficacy compared with dry needling or saline injections in 3 studies. [8] (10.1097/bte.0000000000000118)
- [L5] Interventions employing PRP, MSCs and exosomes are considered in this article. [9] (10.1016/j.reth.2020.07.007)
- [L1] These findings refute claims of PRP equivalence to placebo and support its efficacy over placebo. [10] (10.1186/s12891-025-09339-8)
- [L4] The authors recommend systematically offering PRP therapy for competition sports practitioners. [11] (10.1186/s12891-025-08663-3)
- [L5] The authors state that the conclusion of the referenced randomized controlled trial is that PRP provides a greater clinical improvement at 12 weeks than a single corticosteroid injection. [12] (10.1177/0363546518773719)
- [Paper] The authors argue that they fulfilled the reporting requirements for the injected PRP product as defined by MIBO. [13] (10.1177/03635465231203202)
- [L1] PRP demonstrated some indications of more sustained benefits, particularly at the 6-month follow-up. [14] (10.1016/j.injury.2026.113018)
- [Paper] Rigorous basic, translational, and clinical research remains fundamental to realize the promise of PRP treatment for musculoskeletal disease. [15] (10.1177/03635465251395284)
- [L5] There is insufficient evidence to recommend for or against the use of PRP given the heterogeneity of the literature and the inability of effect sizes to reach MCID values even when significant. [16] (10.1177/0363546520918190)
- [L5] The authors agree that results from an in vitro study should be interpreted with caution and mention a subsequent prospective randomized double-blind clinical trial comparing autogenous PRP to HA for the treatment of OA. [17] (10.1177/0363546514537991)
- [L2] Current evidence supports the selective use of PRP in sports settings, though standardization in protocols and outcomes is needed. [18] (10.1177/23259671251399907)
- [L1] Corticosteroids resulted in greater short-term improvement, while PRP demonstrated superior longer-term outcomes at 6 and 12 months. [20] (10.1177/23259671251386862)
- [L1] PRP is no more effective than placebo for treating Achilles tendinopathy and should not be used for this indication until new, large, high-quality RCTs upend current knowledge. [21] (10.1097/corr.0000000000003478)
- [L2] This review demonstrated that studies evaluating the outcomes and procedures of the use of PRP in the setting of LE have poor adherence to MIBO guidelines. [22] (10.5397/cise.2024.01060)
- [L1] A direct, linear relationship was observed between the concentration factor of PRP used and the magnitude of patient-reported symptom relief after PRP injection, with high-dose PRP showing significant efficacy over alternative treatment strategies. [23] (10.1016/j.jisako.2025.100442)
- [L5] The authors clarify that their statement regarding the standard of care for knee osteoarthritis was intended to reflect frequent clinical use of hyaluronic acid and platelet-rich plasma rather than formal guideline recommendations. [24] (10.1177/0363546517703364)
- [L1] The effectiveness rate for excellent and good limb function was 85.19% in the combined group versus 60.71% in the PRP group. [25] (10.1016/j.otsr.2022.103417)
- [L5] The authors state that the significant difference in the retear rate, even in this underpowered study, has further confirmed the positive effect of platelet-rich plasma (PRP). [26] (10.1177/0363546515625958)
- [L1] These findings do not support PRP as a recommended treatment for this condition. [27] (10.1177/03635465251383039)
- [L3] It is recommended to wait for at least one month before considering another injection or alternative treatments. [28] (10.1142/s2424835520500253)
- [L1] As a result, we do not support the routine use of PRP for the treatment of this condition. [29] (10.2106/jbjs.24.00763)
- [L2] Current evidence is insufficient to support such injections as standalone procedures. [30] (10.1002/arj.70548)
- [L4] Although PRP has been reported in literature to be a biological treatment which increases healing, adequate healing was not determined in the patient group of the current study. [31] (10.1016/s0020-1383(13)70158-x)
- [L5] An innovative biological approach to the treatment of muscle injuries is the application of Plasma Rich in Growth Factors (PRGF) in intramuscular infiltrations. [32] (10.1016/s0020-1383(14)70004-x)
- [L5] The goal of the study was to discern key molecular mediators between leukocyte-rich PRP (LR-PRP) and leukocyte-poor PRP (LP-PRP) derived from the same patient with equivalent platelet concentrations. [33] (10.1177/03635465231206930)
- [Paper] These findings support in vivo investigation of PRP as an autogenous, patient-side treatment for tendonitis. [34] (10.1002/jor.20278)
- [L4] Previous corticosteroid injections and tobacco seem to unfavourably affect the response to PRP. [35] (10.1177/1753193414567012)
- [L1] Optimizing OA treatment involves tailoring PRP protocols to disease stage, with low platelet, high leukocyte PRP recommended for early OA due to its anti-inflammatory effects and high platelet, low leukocyte PRP preferred for advanced OA to promote tissue repair and regeneration. [36] (10.1186/s13018-025-06026-1)
- [L3] At final follow-up, all patients in Group 1 (PRP-enhanced) healed, while 80.49% of Group 2 (non-PRP) healed (p = 0.049). [37] (10.1016/j.injury.2025.112325)
- [L5] The authors also highlight that the PRP used in the study came from healthy donors, which may encourage research toward the use of allogeneic healthy PRP. [38] (10.1177/0363546514537996)
- [L1] The economic value of LP-PRP is conditional rather than uniform and depends on revision probability and preparation cost. [39] (10.1016/j.jse.2026.02.018)
- [L1] Consequently, LP-PRP augmentation increases healing rates but does not affect clinically meaningful functional outcomes. [40] (10.1002/arj.70537)
- [L1] This double-blind randomized controlled trial demonstrated that leukocytes did not affect the safety and efficacy of intra-articular PRP injections for the treatment of patients with knee OA. [41] (10.1177/03635465241283500)
- [L3] The application of PRP following CD results in significant pain relief, improved short-term functional outcomes, and enhanced quality of life compared to CD alone. [42] (10.1186/s12891-024-08243-x)
- [L1] PRP can effectively improve pain and functional impairment in patients with tendinopathy, and its midterm efficacy is superior to that of corticosteroids. [43] (10.1186/s12891-025-08566-3)
- [L1] This meta-analysis reveals that, for patients with KOA, PRP + HA therapy is safe and yields better outcomes in pain relief and functional improvement compared to PRP monotherapy. [44] (10.1186/s13018-024-05429-w)
- [L4] PRP injections are a safe and effective conservative treatment method for reducing pain symptoms and increasing functionality in patients with lateral epicondylitis. [45] (10.1177/2325967125s00169)
- [L1] Intra-articular PRP injection is an effective treatment for improving overall function in patients with primary OA, particularly in younger individuals. [46] (10.1186/s12891-026-09486-6)
- [L4] After autologous blood injection therapy 22 patients (79%) in whom nonsurgical modalities had failed were relieved completely of pain even during strenuous activity. [47] (10.1053/jhsu.2003.50041)
- [L1] Spin bias is highly prevalent in the abstracts of systematic reviews and meta-analyses of intra-articular PRP to treat knee osteoarthritis, with identified spin tending to favor the use of PRP. [48] (10.1002/arj.70027)
- [L1] The combination of PRP with non-crosslinked HA in mono-injection was found to be non-inferior to crosslinked HA, with regards to the percentage of responders over 6 months (WOMAC pain). [49] (10.1186/s12891-026-09625-z)
- [L1] Among level 1 RCTs reporting VAS pain scores after PRP injection for partial-thickness rotator cuff tears, platelet concentration was not significantly associated with improved pain outcomes. [50] (10.1177/23259671261480483)
References
[1] Platelet-Rich Plasma for Chronic Tennis Elbow: Letters to the Editor. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546513512784
[2] Efficacy of multiple autologous apheresis platelet-rich plasma injections for treating knee osteoarthritis and its influencing factors: a retrospective cohort study. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05756-6
[3] PRP Injections for the Treatment of Knee Osteoarthritis: The Improvement Is Clinically Significant and Influenced by Platelet Concentration: Response. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251387701
[4] Comparison of Conventional Dose Versus Superdose Platelet-Rich Plasma for Knee Osteoarthritis: Letter to the Editor. Orthopaedic Journal of Sports Medicine. 2024. DOI: 10.1177/23259671241255700
[5] Overview of Available Treatments and Their Limitations for Hypertrophic Facet Joints—A Systematic Review of the Literature. JAAOS: Global Research and Reviews. 2025. DOI: 10.5435/jaaosglobal-d-24-00140
[6] Letter Regarding “Platelet-Rich Plasma Injections are Inferior to Corticosteroid Injections for Short-Term Pain Relief: A Prospective, Double-Blinded, Randomized Controlled Trial”. The Journal of Arthroplasty. 2025. DOI: 10.1016/j.arth.2025.05.007
[7] Leukocyte-rich versus leukocyte-poor platelet-rich plasma and hyaluronic acid for knee osteoarthritis: a systematic review and network meta-analysis. Journal of Orthopaedic Surgery and Research. 2026. DOI: 10.1186/s13018-026-06689-4
[8] Update on Platelet-rich Plasma for Shoulder and Elbow Tendinopathy. Techniques in Shoulder & Elbow Surgery. 2017. DOI: 10.1097/bte.0000000000000118
[9] Degenerative osteoarthritis a reversible chronic disease. Regenerative Therapy. 2020. DOI: 10.1016/j.reth.2020.07.007
[10] Time-dependent growth factor kinetics, platelet concentration, and clinical response following platelet-rich plasma versus saline in chronic tenosynovitis: a randomized controlled trial. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-09339-8
[11] Platelet-rich plasma treatment for large joint osteoarthritis: retrospective study highlighting a possible treatment protocol with long-lasting stimulation of the joint with an adequate dose of platelets. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08663-3
[12] The Effectiveness of Platelet-Rich Plasma Injections in Gluteal Tendinopathy: Response. The American Journal of Sports Medicine. 2018. DOI: 10.1177/0363546518773719
[13] Improving Injectable Orthobiologics Reporting Guidelines Adherence: Response. The American Journal of Sports Medicine. 2023. DOI: 10.1177/03635465231203202
[14] Comparison of the effectiveness of platelet-rich plasma (PRP) injection and steroid injection in patients with bilateral moderate carpal tunnel syndrome: a prospective randomized controlled trial. Injury. 2026. DOI: 10.1016/j.injury.2026.113018
[15] Platelet-Rich Plasma in the Treatment of Musculoskeletal Disease in 2025 and Beyond. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251395284
[16] Use of Platelet-Rich Plasma for the Improvement of Pain and Function in Rotator Cuff Tears: Response. The American Journal of Sports Medicine. 2020. DOI: 10.1177/0363546520918190
[17] The Anti-inflammatory and Matrix Restorative Mechanisms of Platelet-Rich Plasma in Osteoarthritis: Response to Patel and Dhillon. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546514537991
[18] Platelet-Rich Plasma in Acute Muscle Injuries: An Umbrella Review and Meta-analysis of Return to Sport and Reinjury Outcomes. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671251399907
[19] Platelet-Rich_Plasma_Versus_Hyaluronic_Acid_S0749806312015812. 2015.
[20] A Randomized Controlled Trial of 1-Year Clinical Outcomes of a Single Platelet-Rich Plasma Injection Versus Corticosteroid for the Treatment of Lateral Elbow Tendinopathy. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671251386862
[21] Editor’s Spotlight/Take 5: Is Platelet-rich Plasma Effective in Treating Achilles Tendinopathy? A Meta-analysis of Randomized Clinical Trials. Clinical Orthopaedics & Related Research. 2025. DOI: 10.1097/corr.0000000000003478
[22] Adherence rates to the Minimum Information for Studies Evaluating Biologics in Orthopedics guidelines for clinical studies on platelet-rich plasma for the treatment of lateral epicondylitis: a systematic review. Clinics in Shoulder and Elbow. 2026. DOI: 10.5397/cise.2024.01060
[23] Platelet Concentration Factor Explains Variability in Outcomes of Platelet-rich Plasma for Lateral Epicondylitis: High Dose Critical for Positive Response. Journal of ISAKOS. 2025. DOI: 10.1016/j.jisako.2025.100442
[24] Hyaluronic Acid Versus Platelet-rich Plasma: Response. The American Journal of Sports Medicine. 2017. DOI: 10.1177/0363546517703364
[25] Synergistic effects of autologous platelet-rich plasma combined with an extracorporeal shock wave in treatment of long diaphysis aseptic nonunion. Orthopaedics & Traumatology: Surgery & Research. 2024. DOI: 10.1016/j.otsr.2022.103417
[26] PRP for Arthroscopic Repair of Medium to Large Rotator Cuff Tears: Response. The American Journal of Sports Medicine. 2016. DOI: 10.1177/0363546515625958
[27] Platelet-Rich Plasma Does Not Improve Pain or Function in Patients With Lateral Epicondylitis as Compared With Placebo: A Meta-analysis of Randomized Clinical Trials. The American Journal of Sports Medicine. 2026. DOI: 10.1177/03635465251383039
[28] Time to Resolution of Triggering after Steroid Injection for First Presentation Trigger Digits. The Journal of Hand Surgery (Asian-Pacific Volume). 2020. DOI: 10.1142/s2424835520500253
[29] Efficacy of Platelet-Rich Plasma Versus Placebo for the Treatment of Greater Trochanteric Pain Syndrome. Journal of Bone and Joint Surgery. 2025. DOI: 10.2106/jbjs.24.00763
[30] Orthobiologic Injections Adjunctive to Cartilage‐Preserving Surgery May Improve Outcomes for Focal Knee Chondral Defects: A Systematic Review of Randomized Controlled Trials With Subgroup Meta‐analyses. Arthroscopy. 2026. DOI: 10.1002/arj.70548
[31] PS9 Is platelet-rich plasma injection an effective choice in cases of delayed union or non-union?. Injury. 2013. DOI: 10.1016/s0020-1383(13)70158-x
[32] Muscle repair: platelet-rich plasma derivates as a bridge from spontaneity to intervention. Injury. 2014. DOI: 10.1016/s0020-1383(14)70004-x
[33] The Accurate Characterization of Platelet-Rich Plasma Enables Its Classification and Comparison: Response. The American Journal of Sports Medicine. 2023. DOI: 10.1177/03635465231206930
[34] Platelet rich plasma (PRP) enhances anabolic gene expression patterns in flexor digitorum superficialis tendons. Journal of Orthopaedic Research. 2006. DOI: 10.1002/jor.20278
[35] Efficacy of platelet-rich plasma injections for chronic medial epicondylitis. Journal of Hand Surgery (European Volume). 2015. DOI: 10.1177/1753193414567012
[36] The efficacy of platelet-rich plasma preparation protocols in the treatment of osteoarthritis: a network meta-analysis of randomized controlled trials. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06026-1
[37] Based on the diamond concept, application of platelet-rich plasma in the treatment of aseptic femoral shaft nonunion: A retrospective controlled study on 66 patients. Injury. 2025. DOI: 10.1016/j.injury.2025.112325
[38] Anti-inflammatory and Matrix Restorative Mechanisms of Platelet-Rich Plasma in Osteoarthritis: Response to Andia and Maffulli. The American Journal of Sports Medicine. 2014. DOI: 10.1177/0363546514537996
[39] Leukocyte-poor platelet-rich plasma reduces retear risk after arthroscopic rotator cuff repair: a meta-analysis with mechanistic and economic evaluation. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2026.02.018
[40] Injection of Leukocyte‐Poor Platelet‐Rich Plasma During Rotator Cuff Repair Can Increase Healing Rate but Does Not Affect Clinical Outcomes: A Systematic Review and Meta‐analysis of Randomized Controlled Trials. Arthroscopy. 2026. DOI: 10.1002/arj.70537
[41] Leukocytes Do Not Influence the Safety and Efficacy of Platelet-Rich Plasma Injections for the Treatment of Knee Osteoarthritis: A Double-Blind Randomized Controlled Trial. The American Journal of Sports Medicine. 2024. DOI: 10.1177/03635465241283500
[42] Efficacy of small-diameter core decompression with platelet-rich plasma in early osteonecrosis of the femoral head: a retrospective study. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-024-08243-x
[43] Platelet-rich plasma and corticosteroid injection for tendinopathy: a systematic review and meta-analysis. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08566-3
[44] RETRACTED ARTICLE: A meta-analysis and systematic review of the clinical efficacy and safety of platelet-rich plasma combined with hyaluronic acid (PRP + HA) versus PRP monotherapy for knee osteoarthritis (KOA). Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-024-05429-w
[45] Poster 58: Decreased Pain After Platelet-Rich Plasma Injection in Lateral Epicondylitis Patients in the Early Follow-up Period. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/2325967125s00169
[46] Investigating the therapeutic impact of platelet-rich plasma on knee, hip, and traumatic osteoarthritis: a meta-analysis and systematic review. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09486-6
[47] Autologous blood injections for refractory lateral epicondylitis. The Journal of Hand Surgery. 2003. DOI: 10.1053/jhsu.2003.50041
[48] Statistically Significant Results Favored in Abstracts of Platelet Rich Plasma Treatment of Knee Osteoarthritis: A Systematic Review and Spin Analysis. Arthroscopy. 2026. DOI: 10.1002/arj.70027
[49] Efficacy and safety of a combination of platelet-rich plasma with non-crosslinked hyaluronic acid versus a crosslinked hyaluronic acid, in single-injection for knee osteoarthritis. Randomized, controlled, multicenter, non-inferiority trial. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09625-z
[50] Platelet Concentration Is Not Associated With Improved Pain for Partial-Thickness Rotator Cuff Tears Treated With Platelet-Rich Plasma: A Systematic Review and Meta-analysis With Meta-regression of Level 1 Randomized Controlled Trials. Orthopaedic Journal of Sports Medicine. 2026. DOI: 10.1177/23259671261480483