Patients › Rehabilitation
Tình trạng không ổn định khớp khuỷu tay
Phục hồi chức năng sau phẫu thuật điều trị tình trạng không ổn định khớp khuỷu, bao gồm cả các chấn thương vùng bên (hội chứng “terrible triad”/chấn thương dây chằng bên ngoài) và các chấn thương liên quan đến hoạt động ném (chấn thương dây chằng UCL vùng trong). Phương pháp này chú trọng việc vận động sớm một cách có kiểm soát thay vì việc cố định khớp.
Quy trình này hướng dẫn quá trình hồi phục của bạn sau phẫu thuật chứng không ổn định khớp khuỷu tay do bác sĩ Kieran Hirpara thực hiện tại Bệnh viện tư nhân Mater Rockhampton. Quy trình này đề cập đến hai dạng không ổn định khác nhau; bác sĩ phẫu thuật sẽ cho bạn biết dạng nào phù hợp với trường hợp của mình:
- (A) Chấn thương ở mặt ngoài khớp khuỷu: ví dụ như chấn thương “tam giác kinh hoàng”, tình trạng gãy xương kèm trật khớp, hoặc phẫu thuật sửa chữa dây chằng bên ngoài (LCL). Các chấn thương này được xử lý nhằm giúp khớp khuỷu không còn bị trượt hay xoay ra khỏi vị trí bình thường.
- (B) Chấn thương ở mặt trong khớp khuỷu: là phẫu thuật sửa chữa hoặc tái tạo dây chằng quay – trụ (UCL), thường áp dụng cho các vận động viên thường thực hiện các động tác ném vật.
Toàn bộ quy trình này dựa trên một nguyên tắc cốt lõi: cho phép vận động sớm một cách có kiểm soát, thay vì cố định khớp. Việc đeo nẹp hoặc bó bột trong thời gian dài là nguyên nhân chính dẫn đến tình trạng khuỷu tay bị cứng vĩnh viễn; vì vậy mục tiêu là bắt đầu vận động một cách an toàn càng sớm càng tốt. Hãy mang theo trang này hoặc bản PDF tương ứng đến buổi trị liệu đầu tiên để quá trình phục hồi được thực hiện đồng bộ. Chuyên viên trị liệu có thể điều chỉnh quy trình tùy theo tiến triển hồi phục của bạn.
Nếu bạn có bất kỳ thắc mắc nào về vết thương sau phẫu thuật, hãy liên hệ với phòng khám. Việc chụp ảnh vết thương rồi gửi qua email để các bác sĩ xem xét thường rất hữu ích.
Những điều bạn có thể mong đợi
Khớp khuỷu tay được giữ vững nhờ các dây chằng ở mặt trong và mặt ngoài khớp. Khi các dây chằng này bị tổn thương (do trật khớp, gãy kèm trật khớp hoặc do việc ném đi ném lại nhiều lần), khớp có thể trở nên không ổn định. Phẫu thuật giúp sửa chữa hoặc tái tạo các cấu trúc bị hư hỏng để khớp trở lại trạng thái bình thường.
Phương pháp của bác sĩ Hirpara giúp tránh việc phải sử dụng nẹp khớp ngoài có bản lề cồng kềnh. Nếu sau khi phẫu thuật, khớp vẫn giữ được độ ổn định trong toàn bộ vòng chuyển động, bạn chỉ cần đeo một chiếc đai đỡ nhẹ để cảm thấy thoải mái và có thể bắt đầu vận động khuỷu tay sớm, trong các tư thế an toàn. Nếu cần bảo vệ thêm độ ổn định, bác sĩ có thể lắp đặt thiết bị ổn định khớp nội bộ trong lúc phẫu thuật: đó là một bản lề nhỏ đặt bên trong cơ thể, giúp giữ khuỷu tay ở vị trí đúng mà vẫn cho phép bạn gập và duỗi tay sớm. Nhờ thiết bị này nằm bên trong, bạn vẫn không cần phải đeo nẹp hạn chế chuyển động bên ngoài. Thông thường, thiết bị này sẽ được tháo ra sau khoảng bốn đến sáu tháng, khi các dây chằng đã lành hẳn.
Để quản lý vết thương, sưng và sẹo, vui lòng tham khảo hướng dẫn chăm sóc vết thương của phòng khám.
Thói quen quan trọng nhất trong quá trình hồi phục là tiếp tục vận động trong phạm vi an toàn, đồng thời tránh những tư thế mà bác sĩ phẫu thuật yêu cầu không thực hiện. Các bài tập dưới đây sẽ là điểm khởi đầu cho bạn.
Các biện pháp phòng ngừa và hạn chế
Các tư thế cần tránh hoặc nên thực hiện phụ thuộc vào loại chấn thương mà bạn gặp phải. Bác sĩ phẫu thuật và chuyên viên trị liệu sẽ xác định cụ thể cho trường hợp của bạn.
Đối với chấn thương ở phía ngoài cánh tay (bộ ba chấn thương nghiêm trọng / dây chằng bên ngoài – LCL):
- Nên giữ cẳng tay ở tư thế lòng bàn tay hướng xuống dưới (tư thế xoay trong) khi vận động; điều này giúp khớp ổn định và bảo vệ vùng được phẫu thuật.
- Nên tập luyện khi cánh tay đặt phía trước cơ thể, hoặc nằm xuống và giơ tay lên trần nhà nếu được hướng dẫn; trọng lực sẽ hỗ trợ giữ khớp ổn định.
- Không được để cánh tay rơi sang bên hông (tránh tư thế dạng vai) hoặc chịu tải trọng sớm; trọng lực sẽ làm vết khâu bị tách ra.
- Không được kết hợp tư thế duỗi thẳng khuỷu tay với cẳng tay ở tư thế lòng bàn tay hướng lên trên (tư thế xoay ngoài) cho đến khi bác sĩ phẫu thuật cho phép (khoảng tuần thứ 16); đây là tư thế có nguy cơ khiến khớp bị trượt trở lại.
- Không được dùng lực đẩy hoặc kéo khuỷu tay đến mức gây đau; trong vài tháng đầu, cần tránh các hoạt động chịu tải trọng và va chạm mạnh.
Đối với chấn thương ở phía trong cánh tay do ném vật (dây chằng UCL):
- Nên giữ cẳng tay ở tư thế lòng bàn tay hướng lên trên (tư thế xoay ngoài) hoặc tư thế trung tính, theo hướng dẫn của bác sĩ.
- Không được tạo áp lực lên vai ở tư thế xoay ngoài sớm; điều này sẽ gây căng thẳng cho vùng được phẫu thuật. Thông thường, cần tránh tư thế này cho đến khoảng tuần thứ 6.
Các bài tập của bạn

Kieran Hirpara 4.0
Các động tác gập khuỷu tay chủ động
Hãy nhẹ nhàng gập khuỷu tay đến mức bạn cảm thấy thoải mái, sau đó duỗi thẳng lại đến mức mà bác sĩ phẫu thuật và chuyên viên trị liệu cho phép. Hãy giữ cẳng tay xoay theo tư thế đã được hướng dẫn — đối với chấn thương phía ngoài (bên) khuỷu tay, điều này thường có nghĩa là lòng bàn tay úp xuống (tư thế sấp cẳng tay). Chỉ dùng sức cơ của chính mình để vận động; không ép khớp.
10–15 lần, vài lần mỗi ngày
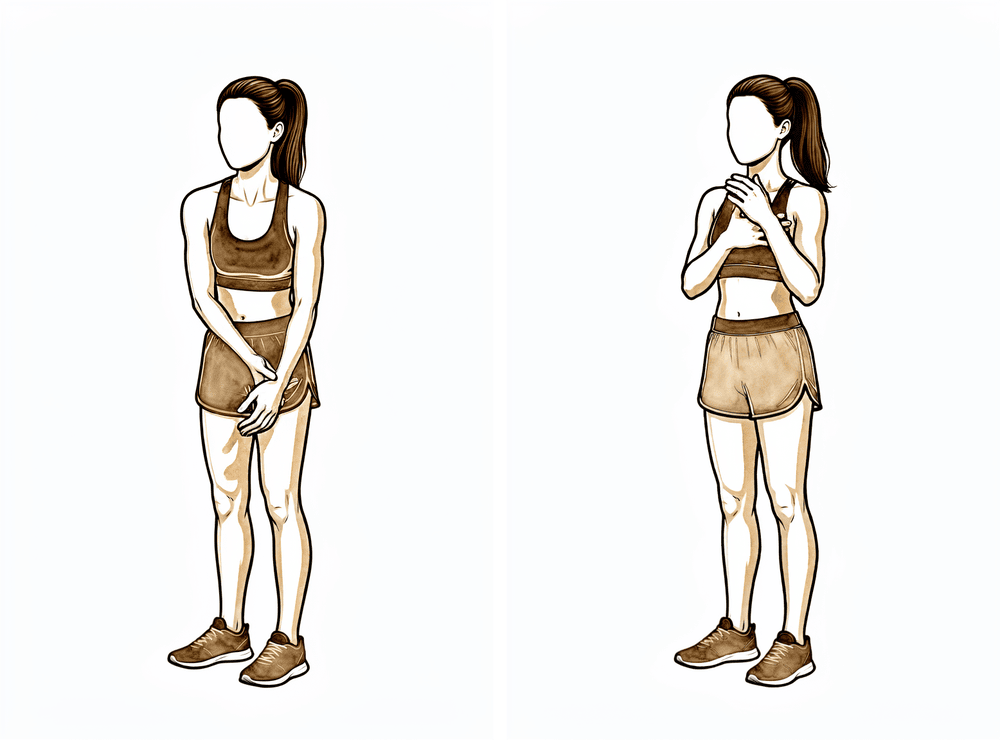
Kieran Hirpara 4.0
Hỗ trợ gập khuỷu tay
Khi được chuyên viên trị liệu cho phép, hãy dùng tay còn lại nhẹ nhàng hỗ trợ khuỷu tay gập thêm một chút so với mức tự nhiên. Chỉ nên kéo căng đến mức cảm thấy thoải mái — tuyệt đối không được gây đau đớn — rồi từ từ thả ra.
Giữ trong 10–15 giây, thực hiện 5–10 lần theo hướng dẫn.
Kieran Hirpara 4.0
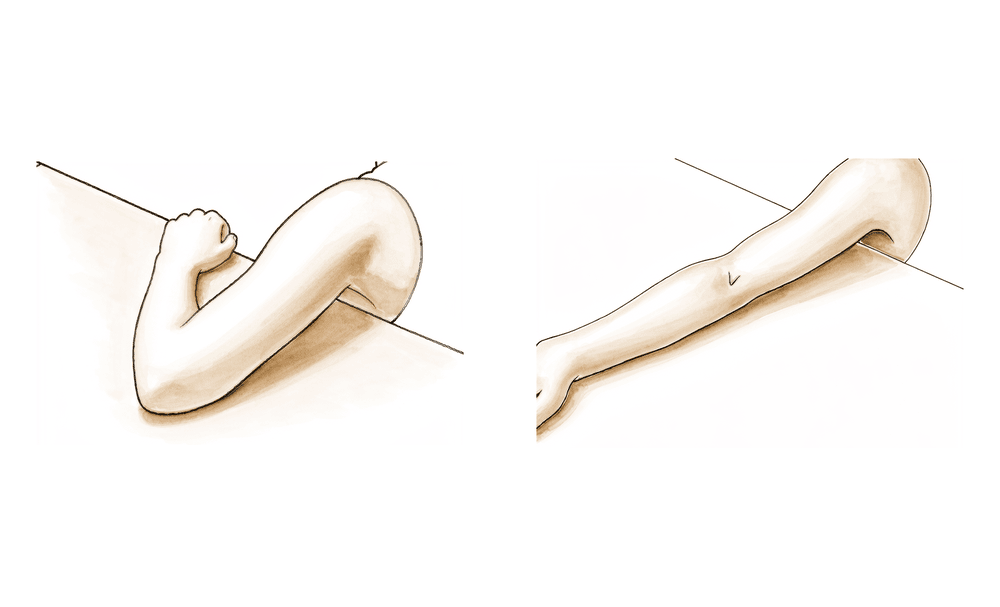
Duỗi thẳng khuỷu tay (duỗi ra đến mức thoải mái)
Hãy duỗi thẳng khuỷu tay đến mức bạn cảm thấy thoải mái trong phạm vi mà bác sĩ phẫu thuật đã xác định. Trong trường hợp chấn thương ở mặt ngoài cánh tay, hãy giữ lòng bàn tay hướng xuống dưới khi duỗi thẳng khuỷu tay. Đừng cố gắng duỗi thẳng hoàn toàn khuỷu tay kết hợp với việc xoay lòng bàn tay hướng lên trên cho đến khi bác sĩ phẫu thuật cho phép.
10–15 lần, vài lần mỗi ngày

Kieran Hirpara 4.0
Chuyển động xoay cẳng tay (lòng bàn tay hướng lên / lòng bàn tay hướng xuống)
Khi khuỷu tay áp sát vào thân mình và gập khoảng 90°, hãy nhẹ nhàng xoay lòng bàn tay hướng lên trên rồi lại hướng xuống dưới, trong phạm vi mà bác sĩ đã chỉ định. Hướng vận động an toàn phụ thuộc vào chấn thương của bạn: nếu bị chấn thương ở mặt ngoài cánh tay thì nên xoay lòng bàn tay xuống dưới (tư thế pronation); còn nếu bị chấn thương ở mặt trong do vận động ném thì nên xoay lòng bàn tay hướng lên trên (tư thế supination). Hãy tuân theo hướng dẫn của bác sĩ phẫu thuật và chuyên viên trị liệu.
Mỗi hướng được thực hiện 10 lần, nhiều lần trong ngày.

Kieran Hirpara 4.0
Giữ co cơ khuỷu tay — duỗi (đẳng tích)
Giữ khuỷu tay yên bất động, nhẹ nhàng ấn như thể muốn duỗi thẳng khuỷu tay chống lại tay kia hoặc một bề mặt cố định. Khuỷu tay không được thực sự cử động. Cách này giúp đánh thức các cơ mà không gây tải lên các dây chằng đang lành.
Giữ nguyên trong 5 giây, thực hiện 10 lần, mỗi ngày một hoặc hai lần — chỉ khi được bác sĩ cho phép.
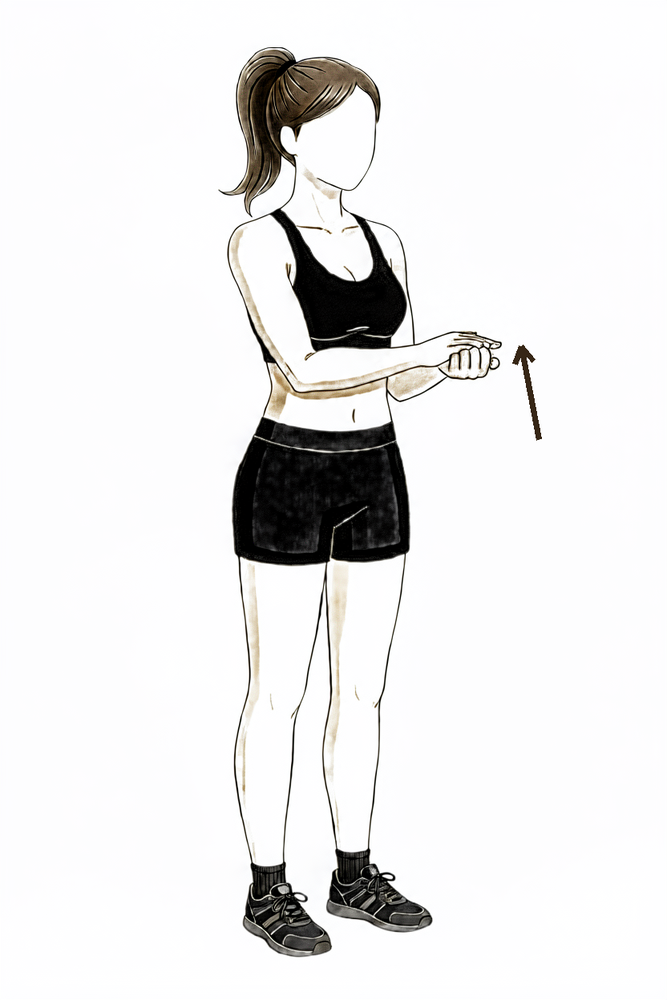
Kieran Hirpara 4.0
Giữ co cơ khuỷu tay — gập (đẳng tích)
Giữ khuỷu tay yên bất động, nhẹ nhàng ấn như thể muốn gập khuỷu tay chống lại tay kia. Khuỷu tay không được cử động. Giữ lực ở mức thoải mái — đây là kích hoạt cơ, không phải một buổi tập luyện.
Giữ nguyên trong 5 giây, thực hiện 10 lần, mỗi ngày một hoặc hai lần — chỉ khi được bác sĩ cho phép.

Kieran Hirpara 4.0
Tăng cường sức mạnh nắm tay
Hãy nắm chặt một quả bóng mềm hoặc đất nặn trị liệu trong tay, giữ nguyên trong chốc lát rồi thả ra. Cách này giúp duy trì sức mạnh cho tay và cẳng tay trong khi bảo vệ khuỷu tay của bạn.
10–15 lần bóp, 2–3 lần mỗi ngày
Đây là những bài tập trong tài liệu hướng dẫn dành cho bạn, nhằm giúp phục hồi khả năng vận động an toàn và duy trì chức năng của tay, cẳng tay và vai trong lúc khuỷu tay đang được bảo vệ. Chỉ thực hiện và tăng dần độ khó của các bài tập này theo hướng dẫn của Bác sĩ Hirpara và chuyên viên trị liệu; vị trí cũng như biên độ vận động an toàn của cẳng tay phụ thuộc vào chấn thương cụ thể của bạn.
Quy trình điều trị lâm sàng của bạn
Phần còn lại của trang này là quy trình điều trị dành cho chuyên viên vật lý trị liệu hoặc chuyên gia trị liệu tay của bạn. Quy trình được trình bày theo hai phần riêng biệt vì hai loại chấn thương này cần được xử lý khác nhau. Mỗi giai đoạn đều có các tiêu chí cụ thể; bạn chỉ được tiến sang giai đoạn tiếp theo khi đã đáp ứng đầy đủ các tiêu chí đó, chứ không phải chỉ dựa vào thời gian.
Trước khi bắt đầu điều trị, hãy kiểm tra phim X-quang, báo cáo phẫu thuật và tiền sử bệnh của bệnh nhân. Đồng thời trao đổi với bác sĩ phẫu thuật về mức độ ổn định sau phẫu thuật, phạm vi chuyển động an toàn của khớp và cẳng tay, cũng như việc có cấy ghép thiết bị cố định khớp nội bộ hay không. Bác sĩ Hirpara không sử dụng nẹp khớp ngoài; đối với các ca phục hồi ổn định trong toàn bộ phạm vi chuyển động, bệnh nhân chỉ cần đeo đai treo đơn giản và bắt đầu vận động sớm để giảm đau. Trong những trường hợp cần bảo vệ thêm độ ổn định, thiết bị cố định khớp nội bộ sẽ giữ cho khớp ở vị trí đúng trong khi vẫn cho phép bệnh nhân duỗi thẳng tay để giảm khó chịu.
Nhóm A — Phục hồi tam giác thương tổn nghiêm trọng / gãy xương kèm trật khớp / sửa chữa dây chằng bên ngoài khuỷu tay (LUCL)
Mục tiêu: Đạt được khớp khuỷu tay ổn định, được nắn chỉnh đúng vị trí và có thể vận động sớm; ngăn ngừa tình trạng trật khớp vùng sau ngoài tái phát.
Các lưu ý quan trọng trong giai đoạn đầu:
- Đối với các chấn thương chỉ ở vùng bên ngoài, hãy giữ cẳng tay ở tư thế xoay lòng bàn tay vào trong (giúp căng các cấu trúc bên ngoài và giúp khớp quay-củ tay nằm đúng vị trí). Nếu cả hai cột xương đều đã được phục hồi, hãy giữ cẳng tay ở tư thế trung tính; chỉ được phép xoay lòng bàn tay ra ngoài khi khuỷu tay gập khoảng 90°.
- Tránh tác động lực vào phía trong khớp và tránh giơ tay lên cao: trọng lực sẽ gây áp lực vào vùng sửa chữa bên ngoài. Thực hiện các động tác vận động chủ động khi tay đặt phía trước cơ thể, hoặc nằm ngửa và giơ tay lên trên đầu (giảm tác động của trọng lực) nếu vùng sửa chữa còn yếu.
- Không được duỗi thẳng khuỷu tay kèm xoay lòng bàn tay ra ngoài cho đến khoảng tuần thứ 16 (động tác này có thể gây hiện tượng dịch chuyển trục khớp).
- Không được chịu tải trọng hay thực hiện các động tác vận động với chuỗi khớp khép kín trong 8–16 tuần.
Tuần 0–2: Vận động sớm. Sử dụng máng treo đơn giản để giảm đau. Ngay lập tức bắt đầu các động tác vận động chủ động cho các ngón tay, cổ tay và vai. Từ ngày 2–3, bắt đầu các động tác vận động chủ động và hỗ trợ cho khớp khuỷu tay tới mức cảm thấy thoải mái, với cẳng tay vẫn giữ tư thế xoay lòng bàn tay vào trong, tay được nâng đỡ phía trước cơ thể (hoặc giơ lên trên đầu khi nằm ngửa nếu vùng sửa chữa còn yếu, nhằm giảm tác động của trọng lực lên khớp). Trong trường hợp đã đặt thiết bị ổn định nội khớp, có thể sớm đạt mức duỗi thẳng khuỷu tay hoàn toàn mà không gây đau; thiết bị này giúp bảo vệ vị trí nắn chỉnh, vì vậy không cần dùng nẹp ngoài.
Tuần 2–6: Phục hồi phạm vi vận động. Tiếp tục thực hiện các động tác gập và duỗi khuỷu tay tới mức cảm thấy thoải mái (duỗi thẳng hoàn toàn cũng được phép nếu có thiết bị ổn định nội khớp). Tiếp tục giữ thói quen xoay lòng bàn tay vào trong; tuyệt đối tránh tạo áp lực vào phía trong khớp. Tiêu chí để chuyển sang giai đoạn tiếp theo: phạm vi vận động thụ động đã phục hồi hoàn toàn, không có dấu hiệu trật khớp tái phát khi khám lâm sàng hoặc chụp X-quang, mức độ đau ≤3/10.
Tuần 6–12: Tăng cường sức mạnh. Khi đã có dấu hiệu lành thương rõ rệt trên lâm sàng và X-quang (khoảng tuần thứ 6), bắt đầu các bài tập tăng cường sức mạnh dần dần; nếu xuất hiện tình trạng co rút khớp, hãy sử dụng nẹp cố định tiến triển. Vẫn tiếp tục tránh tạo áp lực vào phía trong khớp. Nếu đã sử dụng thiết bị ổn định nội khớp, thường vẫn giữ lại cho đến khi dây chằng lành hoàn toàn.
Từ tuần 12–20 trở đi: Các bài tập nâng cao và trở lại sinh hoạt. Tiến hành các bài tập chống lực tiến triển; có thể trở lại làm việc nặng. Có thể tham gia các môn thể thao có va chạm và yêu cầu giơ tay lên cao sau khoảng 6–9 tháng (và sau khi đã tháo thiết bị ổn định nội khớp). Vẫn tiếp tục tránh các bài tập tăng cường sức mạnh tạo áp lực vào phía trong khớp.
Lộ trình B — Phục hồi/tái tạo dây chằng UCL phía trong (liên quan đến động tác ném)
Đây là tình trạng tổn thương dây chằng do quá tải lâu ngày. Bác sĩ Hirpara ưu tiên không sử dụng nẹp khớp ngoài: việc gia cố bằng băng khâu nội bộ hoặc sử dụng mảnh ghép gân để tái tạo dây chằng sẽ đảm bảo sự ổn định cần thiết; chương trình phục hồi chức năng cũng được thiết kế riêng cho các vận động viên ném bóng. Cẳng tay thường được giữ ở tư thế xoay ra ngoài/trung tính; các bài tập xoay vai ra ngoài có sức cản sẽ không được thực hiện cho đến khoảng tuần thứ 6, vì chúng tạo áp lực gây biến dạng dây chằng.
Phương pháp phục hồi có gia cố bằng băng khâu nội bộ (tiến trình nhanh, tương tự phương pháp không dùng nẹp ngoài):
- Vận động có kiểm soát ngay từ đầu để đảm bảo thoải mái; đạt biên độ chuyển động đầy đủ vào khoảng tuần 0–4 (khoảng tuần thứ 6).
- Bắt đầu chương trình tập luyện Thrower’s Ten từ tuần thứ 3; các bài tập tăng cường sức mạnh từ tuần thứ 6.
- Bắt đầu tập ném theo chương trình giãn cách từ tuần thứ 11; có thể trở lại thi đấu sau khoảng 5–7 tháng.
Lộ trình tái tạo dây chằng bằng mảnh ghép (diễn tiến chậm hơn):
- Đạt biên độ chuyển động đầy đủ vào khoảng tuần thứ 6; bắt đầu tập ném theo chương trình giãn cách vào tuần 14–16; không được ném từ vị trí ném chuẩn cho đến 6 tháng sau; thời điểm trở lại thi đấu thường là khoảng 9–16 tháng.
Trở lại làm việc và các hoạt động thường ngày
Tốc độ hồi phục của bạn phụ thuộc vào loại chấn thương và yêu cầu công việc hoặc môn thể thao mà bạn tham gia.
- Chấn thương vùng bên ngoài khuỷu tay (bộ ba chấn thương nghiêm trọng / tổn thương dây chằng bên ngoài): Bạn có thể bắt đầu thực hiện các công việc văn phòng nhẹ nhàng và các hoạt động chăm sóc bản thân sớm, miễn là vẫn giữ khuỷu tay ở các tư thế an toàn. Việc tăng cường sức mạnh cơ bắp thường bắt đầu vào khoảng tuần thứ 6, khi khuỷu tay đã lành lặn về mặt lâm sàng và trên phim X-quang. Các môn thể thao có va chạm hoặc yêu cầu vung tay lên cao thường phải hoãn lại khoảng 6–9 tháng, sau khi đã tháo bộ cố định khớp nếu có đặt vào trước đó. Trước khi được bác sĩ phẫu thuật cho phép, tuyệt đối không chịu tải trọng lên cánh tay hoặc vận động cánh tay sang hai bên.
- Chấn thương dây chằng UCL do ném vật: Trong trường hợp phẫu thuật sử dụng nẹp nội bộ để hỗ trợ, chương trình luyện tập ném có cấu trúc thường bắt đầu vào khoảng tuần thứ 11, và người bệnh có thể trở lại thi đấu sau khoảng 5–7 tháng. Đối với ca phẫu thuật tái tạo dây chằng, thời gian trở lại thi đấu sẽ lâu hơn, thường mất khoảng 9–16 tháng.
Bạn có thể lái xe khi đã kiểm soát được cánh tay một cách dễ dàng và an toàn sau khi tháo nẹp, và khi bác sĩ phẫu thuật xác nhận rằng việc lái xe là phù hợp trong buổi tái khám. Chuyên viên trị liệu sẽ hướng dẫn bạn thực hiện các bài tập tăng cường sức mạnh cũng như các bài tập chuyên biệt phù hợp với công việc hoặc môn thể thao, nhằm giúp bạn đạt được mục tiêu cá nhân.
Sau khi thực hiện theo quy trình này
Quy trình này được áp dụng song song với các hướng dẫn phục hồi chung của phòng khám; vui lòng tham khảo mục xử lý cơn đau sau phẫu thuật và chăm sóc vết thương. Quá trình phục hồi của bạn sẽ được điều chỉnh riêng biệt bởi chuyên viên vật lý trị liệu hoặc chuyên gia trị liệu tay, dựa trên tiến triển của khuỷu tay và loại chấn thương mà bạn gặp phải. Bản tóm tắt các bằng chứng lâm sàng liên quan đến quy trình này dành cho các bác sĩ cũng được lưu kèm với trang này.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Elbow Instability — Rehabilitation Evidence (Lateral / Terrible Triad / LCL and Throwing / UCL)
Topic scope: Post-operative rehabilitation after surgery for elbow instability, in two distinct tracks: (A) complex lateral instability — "terrible triad" / fracture-dislocation and lateral (ulnar) collateral ligament [LCL/LUCL] repair & reconstruction for posterolateral rotatory instability (PLRI); and (B) overhead-throwing ulnar (medial) collateral ligament [UCL] reconstruction & repair ("Tommy John").
Defining principle: the crux of every track is protected motion, not immobilisation. Restore enough stability to permit early range of motion (within ~1 week), because prolonged immobilisation is the dominant cause of disabling flexion contracture and stiffness. Dr Hirpara's stance: he does not use an external hinged brace. A repair that is stable through-range at surgery is managed with a simple sling for comfort plus early motion to comfort within positional precautions. Where stability needs protecting, he implants an internal joint stabiliser (an internal hinge) that holds the elbow reduced from the inside while permitting full flexion and extension to comfort — so the patient still moves early without an external arc-limiting brace. The device is typically removed once the ligaments have healed (~4–6 months). The published external-hinged-brace extension-block arcs below are retained as reference for what they represent biomechanically, not as Dr Hirpara's management.
(A) Terrible triad / complex fracture-dislocation / LCL (LUCL) repair & reconstruction
Forearm-rotation rule (the key precaution)
- Lateral-sided (LCL/LUCL) injury → keep the forearm PRONATED. Pronation tightens the lateral structures and seats the radiocapitellar joint, protecting the lateral repair. Terminal extension is performed pronated; supination near full extension reproduces the pivot-shift and is avoided.
- Medial-sided (MCL/UCL) injury → keep the forearm SUPINATED (Rockwood & Green; Green's Operative Hand Surgery).
- If both columns are repaired (many terrible triads), the forearm is held neutral.
- Early supination, when allowed, is done only with the elbow flexed to ~90° (flexion stabilises the ulnohumeral joint and protects the lateral reconstruction).
Phased timeline
- Week 0–2 — Immediate post-op / early motion. Posterior splint at ~90° flexion in injury-appropriate forearm rotation for 7–14 days in the published protocols; the practical aim is early motion. Begin digit/wrist/shoulder AROM immediately and gentle elbow AROM/AAROM in the surgeon-defined stable arc within days (Brigham fracture-dislocation guideline starts elbow/forearm AROM at day 2–3). A supine/overhead protocol is an option where the lateral repair is tenuous — gravity compresses and stabilises the ulnohumeral joint (Green's; Lee 2013).
- Week 2–6 — Protected motion / restore the arc. Published external-hinged-brace protocols open an extension block ~10°/week, forearm pronated (Denver/Eichinger: 30° at wk2 → 20° wk3 → 10° wk4 → 0° wk5), reaching full extension by ~week 5–6. Dr Hirpara replaces this external brace with a simple sling (through-range stable repair) or an internal joint stabiliser permitting extension to comfort. Precautions: avoid varus stress and shoulder abduction; avoid combined full-extension-with-supination for up to ~16 weeks; no weight-bearing/closed-chain for 8–16 weeks.
- Week 6–12 — Intermediate / strengthening. Full PROM, joint mobilisations. Strengthening starts ~week 6 once clinical and radiographic healing is confirmed (Brigham PRE 6–8 wk; Rockwood & Green). Static-progressive splinting if a contracture is developing (Müller 2013).
- Week 12–20+ — Advanced / return. Progressive resistance; avoid varus-loaded strengthening. Contact/overhead sport often delayed to ~6–9 months for reconstruction (Green's: unrestricted use ≥6 months for graft incorporation; Eichinger: up to 9 months).
Nonoperative (stable terrible triad) caveat: if the joint is concentrically reduced with a stable arc to ≥30° of extension (no radial-head block, small coronoid), nonoperative early-motion management is reasonable (Rockwood & Green / Chan criteria; Najd Mazhar 2017).
(B) UCL reconstruction / repair — throwing athlete ("Tommy John")
Rehabilitation is uniformly described in 4 phases (Brotzman-Wilk lineage; ASMI/Andrews; Mass General). The forearm is biased toward supination/neutral (medial-sided injury); no shoulder external-rotation loading early (it valgus-loads the graft).
- Phase I — Week 0–3. Posterior splint at 90° week 1, then progressive ROM. Wrist AROM, gripping, submax shoulder isometrics (no ER), submax biceps isometrics from week 1–2.
- Phase II — Week 4–6/8. Progress to full ROM by ~week 6. Light wrist/forearm strengthening, rotator-cuff isotonics; resisted shoulder ER avoided until ~week 6 to protect the graft.
- Phase III — Week 6/9–12/13. Progressive elbow/forearm strengthening, eccentrics from ~wk9, Thrower's Ten, plyometrics ~wk9 if appropriate.
- Phase IV — Week 14–26+. Interval throwing program ~week 14–16; long-toss ramp 45→60 ft, +30 ft increments to 180 ft; mound throwing ≥6 months; return to competitive throwing ~6 months for return-to-throw, but full competitive RTS typically 9–16 months (≥12 months a common criterion). ~83–97% RTS in throwers.
Internal-brace–augmented UCL REPAIR (accelerated track) — the recent shift
For acute/avulsion tears with good tissue, UCL repair with internal brace allows a markedly accelerated protocol (Dugas/ASMI; SLU/JOSPT 2019):
- Mobilise early to comfort; full/unrestricted ROM by ~wk4, brace off by wk6.
- Thrower's Ten from ~wk3; plyometrics from ~wk6.
- Interval throwing as early as ~wk11; return to sport ~5–7 months (vs ≥9–12+ for reconstruction). Dugas 2025 (AJSM) head-to-head: repair ~2–3 weeks accelerated for ROM/strengthening and ~5–9 weeks accelerated for starting the interval throwing program, with comparable outcomes in appropriately selected athletes.
Phased-timeline summary
| Phase / window | Track A — lateral (terrible triad / LCL) | Track B — throwing (UCL, internal-brace repair) |
|---|---|---|
| Weeks 0–2 | Sling for comfort; elbow AROM/AAROM to comfort from day 2–3, forearm pronated, arm supported in front / supine-overhead | Early protected motion to comfort; submax shoulder (no ER) + biceps isometrics; grip/wrist work |
| Weeks 2–6 | Restore full comfortable arc; extension to comfort (internal stabiliser permits); maintain pronation, avoid varus | Progress to full arc by ~wk6; Thrower's Ten from ~wk3 |
| Weeks 6–12 | Strengthening once healed (~wk6); static-progressive splint if contracture | Plyometrics from ~wk6; progressive strengthening |
| Weeks 12–20+ | Progressive resistance; contact/overhead sport ~6–9 mo | Interval throwing ~wk11; RTS ~5–7 mo (reconstruction: 9–16 mo) |
Key controversies
- Early vs protected motion (complex instability). Strong consensus favours early motion (≤7 days), BUT the two 2024 systematic reviews (Ahmed Kamel, JSES; Larwa, Shoulder & Elbow) found no RCT and high heterogeneity (immobilisation 1–76 days, weighted mean ~42–47). "Early" is biomechanically favoured, not Level-I proven; over-aggressive motion risks re-subluxation in a marginally stable repair.
- Brace necessity & utility. A hinged orthosis is the published standard, but Manocha/King (JHS 2018) showed it adds little stability with the arm overhead (gravity already compresses the joint), supporting overhead/supine rehab over brace reliance for lateral injuries (Lee 2013). This underpins Dr Hirpara's no-external-brace approach.
- Forearm-rotation dogma. Pronation-for-lateral / supination-for-medial is biomechanically grounded and widely taught, but Selley 2025 found forearm rotation at graft tensioning did not change postoperative medial gapping — questioning how rigidly rotation must be controlled in UCL cases.
- Accelerated vs conservative UCL return-to-throw. Time-to-RTS varies 4–16 months with no consensus threshold; Erickson 2017 found earlier RTS did not raise revision risk in MLB pitchers, undercutting strict "wait ≥12 months" dogma.
- Internal brace enabling faster rehab. The biggest recent shift: suture-tape/internal-brace augmentation gives superior time-zero biomechanics and supports repair (not reconstruction) in selected throwers with a 5–9-week-faster throwing timeline. Durability in elite pitchers and mid-substance tears is still maturing (Level III–IV).
Evidence strength flags
- (A) Complex instability / LCL: LOW–MODERATE. No RCTs; guidance is biomechanical + expert-consensus + Level III/IV case series and two 2024 systematic reviews. Internal-joint-stabiliser data (Orbay/Mighell lineage; Dunning/Morrey biomechanics) are device-specific case series — Consensus / Moderate.
- (B) UCL throwing: MODERATE. Large case series, multiple systematic reviews, and concordant institution-standard protocols (Brigham/Brotzman-Wilk, Mass General, ASMI/Andrews) for the phased arc and interval-throwing timeline. Internal-brace augmentation is newer (Level III–IV, growing).
- Rehabilitation protocols themselves: CONSENSUS / WEAK — phase timings derive from published institutional protocols, not rehab RCTs.
Citations
RAG corpus (180,000+ Orthopaedic articles)
- Szekeres M, Chinchalkar SJ, King GJ. Optimizing Elbow Rehabilitation After Instability. Hand Clin. 2008.
- Wilk KE, Arrigo CA. Rehabilitation of Elbow Injuries. Clin Sports Med. 2020.
- Ahmed Kamel S, Shepherd J, Al-Shahwani A, et al. Postoperative mobilization after terrible triad injury: systematic review and single-arm meta-analysis. J Shoulder Elbow Surg. 2024;33(3):e116–e125.
- Larwa J, Buchanan TR, Janke RL, et al. Characteristics of rehabilitation protocols following operative treatment of terrible triad elbow injuries and the influence of early motion: systematic review and meta-analysis. Shoulder Elbow. 2024.
- Najd Mazhar F, Jafari D, Mirzaei A. Evaluation of functional outcome after nonsurgical management of terrible triad injuries of the elbow. J Shoulder Elbow Surg. 2017;26(8):1342–1347.
- Manocha RH, King GJ, Johnson JA. In Vitro Kinematic Assessment of a Hinged Elbow Orthosis Following Lateral Collateral Ligament Injury. J Hand Surg Am. 2018.
- Lee AT, Schrumpf MA, Choi D, et al. The influence of gravity on the unstable elbow. J Shoulder Elbow Surg. 2013;22(1).
- Dunning CE, et al. (Morrey lineage). Ligamentous Repair and Reconstruction for Posterolateral Rotatory Instability of the Elbow. 2006. (LCL/LUCL stabiliser biomechanics.)
- Müller AM, Sadoghi P, Lucas R, et al. Effectiveness of bracing in the treatment of nonosseous restriction of elbow mobility: systematic review/meta-analysis of 13 studies. J Shoulder Elbow Surg. 2013. (Static-progressive stretch for stiffness.)
- Selley RS, Lawton CD, Owusu-Akyaw K, et al. Forearm Rotation at the Time of Elbow UCL Reconstruction Graft Tensioning Does Not Affect Postoperative Medial Elbow Joint Gapping. Orthop J Sports Med. 2025.
- Erickson BJ, Cvetanovich GL, Frank RM, et al. Do Clinical Results and RTS Rates After UCL Reconstruction Differ Based on Graft Choice and Surgical Technique? Orthop J Sports Med. 2016.
- Erickson BJ, Chalmers PN, Bach BR, et al. Length of time between surgery and RTS after UCL reconstruction in MLB pitchers does not predict need for revision. J Shoulder Elbow Surg. 2017.
- Kemler BR, Rao S, Willier DP, et al. Rehabilitation and Return to Sport Criteria Following UCL Reconstruction: A Systematic Review. Am J Sports Med. 2021.
- Griffith R, Bolia IK, Fretes N, et al. RTS Criteria After Upper Extremity Surgery, Part 2: UCL of the Elbow. Orthop J Sports Med. 2021.
- Dugas JR, Froom RJ, Mussell EA, et al. Clinical Outcomes of UCL Repair With Internal Brace Versus UCL Reconstruction in Competitive Athletes. Am J Sports Med. 2025.
- Dugas JR, Looze CA, Capogna B, et al. UCL Repair With Collagen-Dipped FiberTape Augmentation in Overhead-Throwing Athletes. Am J Sports Med. 2019;47(5).
- Jackson GR, Opara O, Tuthill T, et al. Suture Augmentation in Orthopaedic Surgery Offers Improved Time-Zero Biomechanics and Promising Short-Term Clinical Outcomes. Arthroscopy. 2023.
- Cain EL, Dugas JR, Wolf RS, et al. Elbow Injuries in Throwing Athletes: A Current Concepts Review. Am J Sports Med. 2003.
- Erickson BJ, Bach BR, Verma NN, et al. Treatment of Ulnar Collateral Ligament Tears of the Elbow. Orthop J Sports Med. 2017.
- Rockwood and Green's Fractures in Adults. 2019. — long-arm splint 7–10 d; lateral injury → forearm pronated, medial → supinated; avoid shoulder abduction/varus for lateral injury; strengthening ~6 wk.
- Green's Operative Hand Surgery. 2021. — supination only with elbow maximally flexed; overhead/supine protocol option; isometric strengthening 8–10 wk; unrestricted use ≥6 mo.
Published protocols (literature URLs)
- Brigham & Women's Hospital — Elbow Fracture/Dislocation Post-Op ORIF Hand Therapy Guideline (2021). https://www.brighamandwomens.org/assets/BWH/patients-and-families/rehabilitation-services/pdfs/elbow-fracture-orif-hand-therapy-protocol.pdf
- Brigham & Women's Hospital — UCL of the Elbow Reconstruction Using Autogenous Graft Protocol (Brotzman-Wilk modification). https://www.brighamandwomens.org/assets/BWH/patients-and-families/rehabilitation-services/pdfs/elbow-ulnar-collateral-ligament-reconstruction-protocol-bwh.pdf
- Massachusetts General Hospital Sports Medicine — Rehabilitation Protocol for UCL Reconstruction (rev. Nov 2018). https://www.massgeneral.org/assets/MGH/pdf/orthopaedics/sports-medicine/physical-therapy/rehabilitation-protocol-for-UCL.pdf
- Saint Louis University Sports Medicine / JOSPT 2019 — Rehabilitation s/p UCL Repair with Internal Brace. https://www.slu.edu/medicine/orthopaedic-surgery/sports-medicine/-pdf/ucl-repair-guidelines-final.pdf
- Eichinger MD — Rehabilitation Guidelines for Elbow Lateral Collateral Ligament Repair (2018). https://www.josefeichingermd.com/pdf/rehab-for-lateral-collateral-ligament-repair-3-4-18.pdf
- Denver Shoulder — Rehabilitation Protocol: Lateral Collateral Ligament Repair (extension block 30°→20°→10°→0° wk2–5, forearm pronated; supination only at 90° flexion). https://www.denvershouldersurgeon.com/pdf/lcl-repair-protocol.pdf
- Orthopaedic Medical Group of Tampa Bay — Elbow Dislocation Rehab Protocol. https://www.omgtb.com/wp-content/uploads/pdfs/elbow-dislocation-rehab.pdf