Patients › Shoulder
Xương mỏm cùng vai không hợp nhất (os acromiale)
Patient-facing topic on os acromiale — failed fusion of an acromial ossification centre that may cause shoulder pain and contribute to subacromial impingement.
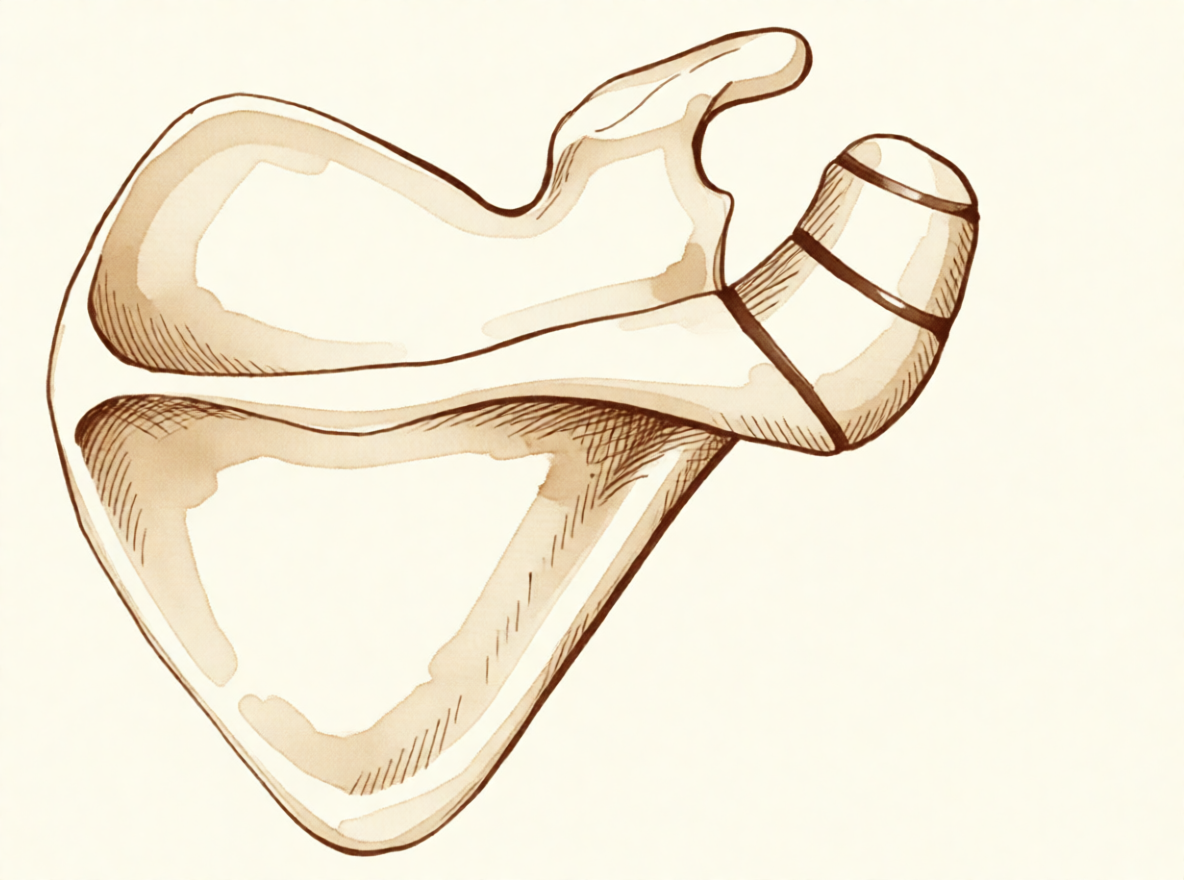
Những cảm giác mà bạn đang trải qua
Với xương mỏm cùng vai không hợp nhất (os acromiale), cơn đau thường nằm ở phía trước và bên ngoài vai, ngay trên phần mái xương của khớp. Các hoạt động đưa tay lên cao làm cơn đau nặng hơn. Với lấy đồ trên kệ cao, phơi quần áo hoặc nâng vật gì đó lên cao hơn tầm vai đều có thể gây đau. Nhiều người cũng bị đau về đêm, và cơn đau có thể khiến bạn thức giấc khi nằm nghiêng về bên vai đó.
Cơn đau xuất phát từ một mảnh xương nhỏ ở đỉnh vai đã không liền vào phần còn lại trong quá trình phát triển. Khi bạn nâng tay, một cơ kéo mảnh xương lỏng lẻo này và nó di chuyển nhẹ, đè lên gân nằm bên dưới. Vị trí tiếp giáp giữa hai mảnh xương cũng có thể đau khi chạm vào, và ấn trực tiếp vào đó có thể gây ra cơn đau.
Trong sinh hoạt hằng ngày, bạn có thể thấy tay yếu khi dang tay sang ngang hoặc xoay tay ra ngoài. Cung đau là hiện tượng phổ biến: vai bị đau ở khoảng giữa động tác khi bạn nâng tay lên, rồi đỡ đau khi nâng cao hơn. Vì các triệu chứng rất giống tình trạng hao mòn ở gân nằm dưới mái vai, bệnh này dễ bị nhầm với một vấn đề về cơ chóp xoay, và nó có thể tiếp tục gây đau ngay cả sau khi đã điều trị vấn đề đó.
Hầu hết những người có dạng xương này không bao giờ cảm thấy gì cả. Tình trạng này thường được phát hiện tình cờ trên phim chụp vì một lý do khác. Khi gây đau, nó thường xuất hiện ở người trưởng thành trẻ tuổi, thường không có chấn thương nào, và nên nghĩ đến tình trạng này nếu cơn đau vai của bạn không thuyên giảm sau vật lý trị liệu, tạm nghỉ chơi thể thao hoặc tiêm thuốc.
Nếu các triệu chứng của bạn không thuyên giảm, ngày càng nặng hơn qua nhiều tuần, khiến bạn thức giấc vào ban đêm, hoặc khiến bạn không thể làm việc hay sử dụng cánh tay, hãy đến gặp bác sĩ đa khoa hoặc đề nghị được bác sĩ chuyên khoa khám.
Chuyện gì đang thực sự xảy ra
Mái xương của vai bạn không hình thành từ một khối xương duy nhất. Nó bắt đầu từ ba trung tâm riêng biệt dần dần liền lại với nhau, bắt đầu vào khoảng 15 tuổi và thường hoàn tất vào khoảng 25 tuổi. Ở khoảng 8% số người, một trong các chỗ nối này không bao giờ khép lại. Khe hở được lấp đầy bằng mô dai giống như sụn thay vì xương, khiến một mảnh nhỏ của mái xương được gắn bằng một mối nối mềm dẻo thay vì xương đặc.
Hãy hình dung như một tấm ván được gắn vào tường bằng một con vít bị lỏng. Tấm ván vẫn được giữ, nhưng hơi xê dịch khi bạn tì vào nó. Cơ nâng tay sang ngang bám vào mái xương này, vì vậy mỗi lần bạn nâng tay, cơ đó kéo mảnh xương lỏng lẻo và nó hơi uốn cong. Chuyển động đó đè xuống gân chạy bên dưới mái xương, và sự cọ xát làm gân bị kích ứng. Đó là lý do các hoạt động đưa tay lên cao gây đau và cơn đau nằm ở phía trước và bên ngoài vai.
Bản thân mối nối mềm dẻo cũng có thể là vấn đề. Nó có thể tự trở nên đau, giống như một khớp bị hao mòn, và ấn vào đó sẽ gây ra cơn đau. Hầu hết những người có dạng xương này không bao giờ cảm thấy gì, và tự bản thân nó dường như không gây đau vai hay làm tăng nguy cơ rách gân. Nhưng khi mảnh xương lỏng lẻo bắt đầu di động nhiều hơn bình thường, do cách nó được hình thành hoặc sau một cú va chạm vào vùng đó, nó có thể đè lên gân mỗi khi bạn nâng tay. Đó là nguyên nhân gây ra cung đau và đau về đêm như đã mô tả ở trên.
Vì mảnh xương lỏng lẻo nằm ngay tại vị trí của gân, hai vấn đề này thường xuất hiện cùng nhau. Nếu vai của bạn đã được điều trị một vấn đề về gân mà cơn đau vẫn không thuyên giảm, nên kiểm tra xem có mảnh xương chưa hợp nhất này hay không, vì chỉ phẫu thuật gân sẽ không làm yên được một mảnh xương di động nằm phía trên nó.
Những biện pháp chúng tôi có thể áp dụng
Bác sĩ Kieran Hirpara, bác sĩ phẫu thuật chi trên tại Bệnh viện tư nhân Mater Rockhampton, sẽ bắt đầu bằng các phương pháp ít xâm lấn nhất phù hợp với tình trạng của bạn. Thông thường, bệnh nhân được bác sĩ đa khoa giới thiệu đến phòng khám chúng tôi; nếu nhà vật lý trị liệu khuyên bạn nên đến gặp chúng tôi, bạn vẫn cần có giấy giới thiệu từ bác sĩ đa khoa để được hưởng mức hoàn trả từ Medicare. Trong lần khám đầu tiên, chúng tôi sẽ hỏi bệnh sử, khám vai và chỉ định chụp hình ảnh nếu cần thiết.
Bước đầu tiên thường là thay đổi cách bạn sử dụng vai và kiên trì tập vật lý trị liệu đúng mức. Vật lý trị liệu nhằm làm dịu tình trạng kích ứng bên dưới mái xương và tăng cường các cơ quanh vai để chúng chịu đựng tốt hơn các công việc phải đưa tay lên cao. Hãy áp dụng biện pháp này trong một thời gian hợp lý trước khi cân nhắc các phương pháp tiếp theo.
Thuốc giảm đau có thể giúp bạn tiếp tục vận động trong thời gian đó. Các thuốc kháng viêm đơn giản, dùng theo hướng dẫn của bác sĩ đa khoa, giúp làm dịu cơn đau để bạn có thể tập các bài tập một cách thoải mái. Nếu cơn đau không thuyên giảm, ngày càng nặng hơn qua nhiều tuần, khiến bạn thức giấc vào ban đêm, hoặc khiến bạn không thể làm việc hay sử dụng cánh tay, hãy đến gặp bác sĩ đa khoa hoặc đề nghị được bác sĩ chuyên khoa khám.
Khi điều trị không phẫu thuật không mang lại đủ cải thiện, chúng tôi sẽ cân nhắc phẫu thuật. Trước đó, chúng tôi xác nhận chẩn đoán bằng phim X-quang thường, gần như luôn đủ để thấy mảnh xương chưa hợp nhất. Một phim chụp từ phía dưới nách cho thấy rõ hình dạng của khớp và phần phía trước của mái xương, và điều này quan trọng vì chấn thương có thể làm tổn thương chỗ tiếp giáp giữa hai mảnh xương. Siêu âm là cách đơn giản và chính xác để kiểm tra gân chạy bên dưới mái xương, và chụp MRI cho hình ảnh đầy đủ hơn về gân đó và các mô mềm xung quanh.
Ca phẫu thuật chúng tôi thường đề xuất nhất là đánh giá khớp qua nội soi (phẫu thuật lỗ khóa) kèm cắt bỏ bao hoạt dịch, nghĩa là loại bỏ mô bị viêm khỏi khoang bên dưới mái xương, sau đó rạch một đường mổ mở nhỏ để ghép xương và cố định, nghĩa là giữ yên mảnh xương lỏng lẻo để nó có thể liền vào phần còn lại của xương. Việc giữ yên giúp hai mảnh xương liền lại với nhau. Nếu mảnh xương lỏng lẻo nhỏ, chúng tôi có thể cắt bỏ nó thay vì cố định. Việc cố định một mảnh xương lớn hơn cần thận trọng, vì cơ nâng tay của bạn liên tục kéo lên nó và mảnh xương thì mỏng. Đôi khi mảnh xương không liền lại sau khi cố định, gọi là không liền xương. Chúng tôi sẽ trao đổi với bạn về phương án phù hợp với vai của bạn và cùng nhau quyết định.
Những điều bạn có thể mong đợi
Hầu hết những người có dạng xương này không bao giờ gặp vấn đề gì và không cần điều trị. Khi nó gây đau, tiên lượng phụ thuộc vào việc mảnh xương lỏng lẻo có ổn định hay không và liệu nó có thực sự là nguồn gốc gây đau của bạn hay không.
Với trường hợp gây đau, việc điều trị thường bắt đầu mà không cần phẫu thuật. Thay đổi cách sử dụng vai, vật lý trị liệu và thuốc giảm đau đơn giản giúp tình trạng ổn định ở nhiều người. Nếu các biện pháp đó không hiệu quả sau một thời gian hợp lý, phẫu thuật có thể giúp giảm đau rõ rệt và cải thiện chức năng vai. Khi mảnh xương lỏng lẻo được giữ yên và liền vào phần còn lại của xương, kết quả trên các thang đo chức năng vai tốt hơn so với khi hai mảnh xương vẫn tách rời. Tuy nhiên, phẫu thuật không phải lúc nào cũng là giải pháp. Ở một số người mắc tình trạng này kèm theo rách gân, kết quả sau phẫu thuật không đồng đều, với 53% đạt kết quả hài lòng nói chung.
Nếu không được điều trị và tình trạng này tiếp tục gây phiền toái, cơn đau thường không tự biến mất. Nó cũng có thể dễ bị bỏ sót: nên nghĩ đến tình trạng này khi cơn đau vai không thuyên giảm sau điều trị, kể cả sau phẫu thuật cho một vấn đề về gân, vì chỉ phẫu thuật gân sẽ không làm yên được một mảnh xương di động nằm phía trên nó.
Quá trình hồi phục sau phẫu thuật diễn ra từ từ. Bạn sẽ tập luyện cùng nhà vật lý trị liệu, phục hồi khả năng cử động trước rồi đến sức mạnh, và khả năng nâng vật lên cao sẽ trở lại dần dần trong nhiều tuần đến nhiều tháng. Mục tiêu là có một bờ vai đáp ứng được sinh hoạt hằng ngày mà không còn cơn đau nhói khi nâng tay như lúc bạn đến khám.
Nếu bạn nhận thấy một ngón tay, bàn tay hoặc cánh tay trở nên nóng, đỏ, sưng và đau, đặc biệt khi kèm theo sốt, hãy đến khoa cấp cứu ngay trong ngày. Bạn không cần giấy giới thiệu của bác sĩ đa khoa.
Khi nào nên gặp bác sĩ
Hầu hết những người có dạng xương này không bao giờ cần điều trị, nhưng hãy đến gặp bác sĩ đa khoa hoặc đề nghị được bác sĩ chuyên khoa khám nếu cơn đau vai không thuyên giảm, ngày càng nặng hơn qua nhiều tuần, khiến bạn thức giấc vào ban đêm, hoặc khiến bạn không thể làm việc hay sử dụng cánh tay. Hãy đề nghị được khám sớm hơn nếu cơn đau nằm ở phía trước và bên ngoài vai, nặng hơn khi đưa tay lên cao, hoặc liên tục khiến bạn thức giấc khi nằm nghiêng về bên vai đó. Cũng nên đi khám nếu điểm đau ở đỉnh vai đau khi ấn vào, nếu tay bạn yếu khi dang sang ngang hoặc xoay ra ngoài, hoặc nếu vai bị đau ở khoảng giữa động tác khi bạn nâng tay lên. Người trưởng thành trẻ tuổi có những triệu chứng này mà không có chấn thương nên được kiểm tra tình trạng này, đặc biệt nếu vật lý trị liệu, tạm nghỉ chơi thể thao hoặc tiêm thuốc không giúp ích. Nếu một ngón tay, bàn tay hoặc cánh tay trở nên nóng, đỏ, sưng và đau, đặc biệt khi kèm theo sốt, hãy đến khoa cấp cứu ngay trong ngày; bạn không cần giấy giới thiệu của bác sĩ đa khoa.
Phân tích chi tiết hơn
Advanced reading: the deeper science (optional)
Phần này đi sâu hơn mức cần thiết để bạn có thể tự đưa ra quyết định điều trị. Cấu trúc xương acromiale là một dạng biến thể giải phẫu bình thường ở một tỷ lệ đáng kể dân số; thường thì nó không gây ra bất kỳ triệu chứng nào, nhưng lại thường bị cho là nguyên nhân gây đau vai dù thực tế không phải vậy. Vì vậy, việc tìm hiểu thêm về nó là hữu ích.
Định nghĩa và mức độ phổ biến
Mỏm cùng vai – phần xương nằm phía trên khớp vai – được hình thành từ nhiều trung tâm ossification riêng biệt; những trung tâm này thường hợp nhất vào cuối tuổi thiếu niên hoặc đầu tuổi hai mươi. Ở một số người, một trong các trung tâm này không hợp nhất, tạo thành một mối nối sợi xơ vĩnh viễn. Đó chính là “os acromiale”, và nó có mặt từ thời niên thiếu chứ không phải là hậu quả của chấn thương hay bệnh lý nào.
Tỷ lệ xuất hiện của os acromiale thay đổi tùy theo dân số. Một nghiên cứu đa trung tâm trên 6.842 bệnh nhân cho thấy os acromiale có liên quan đến các chấn thương gân cơ chóp xoay; tỷ lệ mắc bệnh ở dân số Nhật Bản thấp hơn so với các dân số không phải châu Á; kích thước mảnh xương này thường nhỏ hơn, khoảng [1].
Mối liên hệ giữa os acromiale và tổn thương gân cơ chóp xoay cần được hiểu một cách cẩn thận: nó chỉ chứng minh rằng hai tình trạng này thường xuất hiện cùng nhau nhiều hơn mức ngẫu nhiên, chứ không có nghĩa là os acromiale gây ra vết rách gân. Cơ chế có thể xảy ra theo cả hai hướng: mảnh xương chưa hợp nhất có thể di chuyển nhẹ dưới tác động của cơ delta, gây kích ứng gân phía dưới; hoặc chính cơ chế vận động của vai vốn dễ dẫn đến bệnh lý gân cơ chóp xoay lại khiến mảnh xương không ổn định gây ra triệu chứng.
Liệu nó có phải là nguyên nhân gây đau hay không mới là vấn đề cốt lõi
Do có thể nhìn thấy được, tồn tại vĩnh viễn và có hình dạng bất thường trên hình ảnh chẩn đoán, mảnh xương acromion thường được coi là nguyên nhân gây đau vai. Tuy nhiên, hầu hết các trường hợp đều không gây triệu chứng; phần lớn những người có mảnh xương này thậm chí còn không hề hay biết.
Điểm phân biệt giữa các trường hợp có triệu chứng và không triệu chứng là tình trạng đau nhức khu trú ngay tại vị trí mảnh xương, cơn đau xuất hiện khi ấn vào chỗ đó; nếu tiến hành tiêm chẩn đoán, cơn đau sẽ giảm đi chỉ khi tiêm vào vùng nối giữa các mảnh xương chứ không phải vào khoang dưới acromion. Nếu không có những dấu hiệu này, tốt nhất nên coi việc phát hiện ra mảnh xương này là một phát hiện ngẫu nhiên mà thôi.
Các dạng phụ của tình trạng này thường được phân loại dựa trên vị trí hợp nhất của các mảnh xương [2]; điều này có ý nghĩa quan trọng trong phẫu thuật vì kích thước của mảnh xương di động sẽ quyết định việc có thể cắt bỏ nó hay phải cố định lại.
Tại sao nó gây phức tạp cho các ca phẫu thuật vai khác
Tầm quan trọng thực tế của hiện tượng có mảnh xương acromiale thường không nằm ở các triệu chứng do chính nó gây ra, mà là ở ảnh hưởng của nó đối với các ca phẫu thuật dự định thực hiện cho các vấn đề khác.
Cơ deltoid bám vào mỏm acromion; vì vậy, nếu mảnh xương chưa liền lại thì lực kéo từ cơ này sẽ tác động lên vùng nối còn đang di động. Việc cắt bỏ xương ở mặt dưới mỏm acromion – như trong thủ thuật acromioplasty – sẽ làm mỏng thêm mảnh xương vốn đã không ổn định; điều này có thể biến một dạng biến thể vốn không gây triệu chứng thành dạng gây đau đớn hoặc dẫn đến tình trạng không liền xương. Đây là lý do quan trọng nhất để phát hiện hiện tượng này qua hình ảnh chẩn đoán trước phẫu thuật: không phải để điều trị nó, mà là để tránh làm mất ổn định mảnh xương.
Trong trường hợp thực sự cần điều trị, lựa chọn là cắt bỏ mảnh xương nhỏ hoặc cố định mảnh xương lớn hơn. Việc cố định xương qua vùng nối này được biết là rất khó khăn: mảnh xương mỏng, lực kéo từ cơ deltoid tác động liên tục lên nó, và tỷ lệ không liền xương cũng khá cao. Chính mức độ khó khăn này cũng là lý do để chúng ta phải chắc chắn rằng mảnh xương acromiale thực sự là nguyên nhân gây đau trước khi tiến hành phẫu thuật.
Tài liệu tham khảo
[1] Kozono N, Nishii A, Ishitani E, Mizuki Y, Kimura T, Yamamoto S, và cộng sự. Tỷ lệ mắc và các yếu tố liên quan đến hiện tượng có xương mỏm vai: một nghiên cứu đa trung tâm. JSES Int. 2025;9(5):1541-5. https://doi.org/10.1016/j.jseint.2025.05.015
[2] Boehm TD, Matzer M, Brazda D, Gohlke FE. Điều trị phẫu thuật tình trạng có xương mỏm vai đi kèm với rách gân cơ chóp xoay: tổng quan trên 33 bệnh nhân. J Bone Joint Surg Br. 2003;85(4):545-9. https://doi.org/10.1302/0301-620X.85B4.13634
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- A symptomatic, unstable os acromiale is relatively rare despite the radiographic appearance of an os acromiale being not uncommon in patients presenting with shoulder pain [1].
- An os acromiale should always be suspected in cases of failed rotator cuff surgery or ongoing shoulder pain after failed treatment [2].
- The prevalence of os acromiale was 2.13% in Thai patients with shoulder problems who required MRI evaluation [3].
- Os acromiale is associated with rotator cuff injuries [7].
- The greater the distance of the acromioclavicular joint from the anterior edge of the acromion, the higher the likelihood of an os acromiale [15].
- The authors recommend that the acromion be carefully examined roentgenographically prior to operation in any patient with a rotator cuff tear [10].
- Surgical treatment is usually not indicated for os acromiale in the professional tennis player [9].
- Operative management of a symptomatic os acromiale that has failed initial nonoperative treatment leads to decreased symptoms and improvement in clinical outcomes [4].
- Surgical options for symptomatic os acromiale include arthroscopic sub-total excision, arthroscopic subacromial decompression of stable fragments, and open reduction and internal fixation of unstable fragments [13].
- Patients with a united os acromiale had a significantly better functional outcome as measured by the Constant score (P = .0169) [12].
- The advantages of arthroscopic internal fixation include improved visualization of the undersurface of the acromion, allowing excellent reduction, the possibility of treating concomitant shoulder pathologies, and to avoid increased morbidity of the open approach [14].
- Postoperative local tenderness at the os acromiale can be expected in 1 out of 4 patients but resolves spontaneously over time in the majority of patients [5].
- The presence of os acromiale does not appear to have a negative impact on the clinical outcomes after surgery and rTSA remains a safe and effective treatment option [6].
- The outcome of RTSA does not seem to be negatively affected by the presence of an os acromiale [11].
- Ipsilateral os acromiale may be a relative contraindication to the clavicle hook plate [16].
Anatomy & Pathophysiology
Bony Anatomy
- The acromion has three ossification centers: the metacromion (base), the mesoacromion (middle), and the preacromion (tip) [38].
- Failure of fusion of the acromial ossification centers results in os acromiale [38].
- Os acromiale is defined as incomplete fusion of secondary ossification centers, most commonly between the mesoacromion and meta-acromion [49].
- The unfused segment in os acromiale is most commonly the meso-acromion, a configuration often termed a meso-type os acromiale [22].
- The acromion, coracoacromial ligament, and coracoid process form the coracoacromial arch, a rigid bony-ligamentous structure that imparts stability to the shoulder girdle [35].
- The rotator cuff, subacromial bursa, and subdeltoid bursa pass underneath the coracoacromial arch [35].
- The scapula is attached to the axial skeleton by the acromioclavicular and sternoclavicular joints [37].
- The acromion is a flattened bony process that curves forwards from the scapular spine [37].
Prevalence and Associations
- In Thai patients with shoulder problems who required MRI evaluation, the prevalence of os acromiale was 2.13% [3].
- The radiographic appearance of an os acromiale is not uncommon in patients presenting with shoulder pain [1].
- A symptomatic, unstable os acromiale is relatively rare [1].
Pathophysiology
- Most diagnoses of os acromiale are made incidentally on axillary view radiographs of the shoulder [22].
- Primary shoulder pain is usually unrelated to the unfused os acromiale [22].
- When an os acromiale drives symptoms, the two principal causes are motion at the non-union site or an impingement-type syndrome resulting from flexion of the os fragment during deltoid contraction and arm elevation [22].
- Pain from an os acromiale due to these mechanisms has been reported in a variety of sports, particularly among throwing athletes and swimmers [22].
- Previously stable non-unions can become unstable following an episode of blunt trauma to the region [22].
- The synchondrosis of an os acromiale can be injured following trauma [24].
- Extrinsic impingement occurs when the space available for the rotator cuff is diminished, with examples including acromial fracture or pathologic os acromiale [62].
Epidemiology and Prevalence
- Liberson reviewed 1800 shoulder girdles and identified an incidence of os acromiale of 1.4% [21].
- The lesion was bilateral in 62% of patients in Liberson's review of 1800 shoulder girdles [21].
Associated Pathology and Risk Factors
- The greater the distance of the AC joint from the anterior edge of the acromion, the higher the likelihood of an os acromiale [15].
Diagnostic Considerations
- Awareness of the os acromiale in the young athlete, appropriate clinical examination, and image studies are crucial to confirm diagnosis [19].
- Appropriate radiographic investigation including axillary views is emphasized for the diagnosis of os acromiale injuries [24].
Clinical Presentation
- An os acromiale should always be suspected in cases of failed rotator cuff surgery [2].
- An os acromiale should always be suspected in cases of ongoing shoulder pain after failed treatment [2].
- Postoperative local tenderness at the os acromiale can be expected in 1 out of 4 patients [5].
- Postoperative local tenderness at the os acromiale resolves spontaneously over time in the majority of patients [5].
- The lesion was bilateral in 62% of patients in Liberson's review [21].
- The unfused segment is most commonly the meso-acromion [22].
- Any primary shoulder pain is usually unrelated to the unfused os [22].
- If the os acromiale is driving symptoms, one principle cause is motion at the non-union site [22].
- If the os acromiale is driving symptoms, another principle cause is an impingement-type syndrome resulting from flexion of the os fragment during deltoid contraction and arm elevation [22].
- Pain from an os acromiale by the mechanism of impingement has been reported in a variety of sports [22].
- Pain from an os acromiale by the mechanism of impingement has been reported in particular among throwing athletes and swimmers [22].
- Meta–os acromiale is the rarest subtype of os acromiale [23].
Investigations
Prevalence and Demographics
- Liberson reviewed 1800 shoulder girdles and identified an incidence of os acromiale of 1.4%, with the lesion being bilateral in 62% of patients [21].
- A multicenter study aimed to determine the prevalence of and factors associated with os acromiale in the Japanese population [8].
- The radiographic appearance of an os acromiale is not uncommon in patients presenting with shoulder pain, but a symptomatic, unstable os acromiale is relatively rare [1].
Radiographic Evaluation
- The acromion should be carefully examined roentgenographically prior to operation in any patient with a rotator cuff tear [10].
- Appropriate radiographic investigation for os acromiale includes axillary views [24].
- Awareness of the os acromiale in the young athlete requires appropriate clinical examination and image studies to confirm diagnosis [19].
- The standard shoulder series should include orthogonal views of the shoulder, including a true AP view in the scapular plane, an AP view, an axillary view, and a scapular Y view [60].
- The scapular Y view provides visualization of the coracoacromial arch and can reveal coracoacromial spurs, which have been closely associated with the presence of rotator cuff pathology [60].
- The scapular Y view can also show acromial shape [60].
- At least two X-ray views should be obtained for shoulder imaging: an anteroposterior in the plane of the glenoid and an axillary projection with the arm in abduction to show the relationship of the humeral head to the glenoid [52].
- The purpose of imaging of the shoulder is to help establish the diagnosis, determine the severity of the pathoanatomy, assist in surgical planning, and enable the surgeon to illustrate the condition of the shoulder to the patient [30].
- Standardized plain films are almost always sufficient to garner the information needed for shoulder evaluation [30].
- The first key view for shoulder imaging is the anteroposterior (AP) in the plane of the scapula taken so that the x-ray beam passes through the glenohumeral joint [30].
- The second key view for shoulder imaging is the axillary view taken with the arm in the functional position of elevation in the plane of the scapula and oriented so that both the spinoglenoid notch and the scapular neck are visible [30].
- The axillary view is referred to as the "truth view" because it demonstrates the glenohumeral relationships in the functional position of elevation [30].
- CT scans have the disadvantage of being taken with the arm in the adducted position, unlike the axillary truth view [30].
- The temptation to "overimage" should be resisted, obtaining only the scans or reconstructions that are necessary for the care of the patient [30].
Magnetic Resonance Imaging
- In Thai patients with shoulder problems, os acromiale was identified via Magnetic Resonance Imaging evaluation [3].
- MRI is useful to identify labral tears and rotator cuff tears, although the accuracy for these is enhanced by combining the scan with arthrography [52].
- MRI is the modality of choice for evaluating the rotator cuff, biceps, and subacromial/subdeltoid bursa [59].
- T2-weighted MRI provides better visualization of full thickness rotator cuff tears [59].
- MR arthrography is considered the benchmark for evaluation for labral tears and rarely is indicated for evaluation of rotator cuff pathology [59].
- When MRI or MR arthrography is contraindicated, CT arthrography is indicated [59].
Ultrasonography
- Ultrasonography is a simple and accurate test for identifying rotator cuff tears and calcific tendinitis [52].
- Ultrasonography is a low-cost alternative to MRI and arthrography for evaluating both skeletal and soft-tissue structures of the shoulder [59].
- Ultrasonography can provide immediate, real-time visualization of the rotator cuff, biceps tendon, and calcific deposits [59].
- Ultrasonography can be used to measure the subacromial space and detect atrophy of rotator cuff muscles [59].
- Ultrasonography is highly operator dependent and is not as useful for evaluating labral tears or rotator cuff tears that are very small or larger than 3 cm [59].
- The most commonly performed joint examination using ultrasonography is the shoulder examination, and accuracy depends on the skill of the scanner operator and an awareness of pitfalls that are encountered [50].
Clinical Associations and Diagnostic Implications
- The synchondrosis of an os acromiale can be injured following trauma, though rarely [24].
Treatment
Non-Operative
- A symptomatic os acromiale in a competitive female fastball pitcher was treated successfully with open reduction and internal fixation [27].
Operative
- Symptomatic unstable os acromiale can be effectively treated with autogenous bone-grafting and internal fixation using a rigid tension-band construct and cannulated screws, which results in a high rate of union [65].
- This new arthroscopic technique of fixation of os acromiale with absorbable screws provides promising clinical, cosmetic, and radiologic results with high patient satisfaction [28].
- After 3 to 6 years of follow-up, all 6 shoulders were rated as excellent according to criteria similar to that of the American Shoulder and Elbow Surgeons [18].
- Modified arthroscopic subacromial decompression can provide results similar to standard arthroscopic subacromial decompression for routine impingement [25].
- Meta–os acromiale is the rarest subtype of os acromiale, and special consideration must be given to the type of tension-band construct used to achieve adequate compression and fixation [23].
Complications
Post-operative and Surgical Complications
- Postoperative local tenderness at the os acromiale can be expected in 1 out of 4 patients following reverse total shoulder arthroplasty [5].
Diagnostic and Clinical Implications
Pathophysiology and Mechanisms of Symptom
- Pain from an os acromiale by the mechanism of impingement has been reported in a variety of sports, in particular among throwing athletes and swimmers [22].
Recovery
- After 3 to 6 years of follow-up, all 6 shoulders treated with osteosynthesis of an unstable mesoacromion were rated as excellent according to criteria similar to that of the American Shoulder and Elbow Surgeons [18].
- At a two to five year follow-up, all patients treated for fusion of the unstable mesoacromion had fused [69].
Key Evidence
- [L4] While the radiographic appearance of an os acromiale is not uncommon in patients presenting with shoulder pain, a symptomatic, unstable os acromiale is relatively rare. [1] (10.1097/00132589-200412000-00006)
- [L4] An os acromiale should always be suspected in cases of failed rotator cuff surgery or ongoing shoulder pain after failed treatment. [2] (10.1097/00132589-200609000-00006)
- [L3] In Thai patients with shoulder problems who required MRI evaluation, the prevalence of os acromiale was 2.13%. [3] (10.1177/23259671221078806)
- [L4] Operative management of a symptomatic os acromiale that has failed initial nonoperative treatment leads to decreased symptoms and improvement in clinical outcomes. [4] (10.1016/j.jse.2019.05.047)
- [L3] Postoperative local tenderness at the os acromiale can be expected in 1 out of 4 patients but resolves spontaneously over time in the majority of patients. [5] (10.1177/2325967120965131)
- [L4] The presence of os acromiale does not appear to have a negative impact on the clinical outcomes after surgery and rTSA remains a safe and effective treatment option. [6] (10.1016/j.xrrt.2025.01.002)
- [L3] The study supports previous findings that os acromiale is associated with rotator cuff injuries. [7] (10.1016/j.jseint.2025.05.015)
- [L3] This multicenter study aimed to determine the prevalence of and factors associated with os acromiale in the Japanese population. [8] (10.1016/j.jse.2025.01.008)
- [L4] Surgical treatment is usually not indicated for os acromiale in the professional tennis player. [9] (10.1177/2325967118773723)
- [L4] The authors recommend that the acromion be carefully examined roentgenographically prior to operation in any patient with a rotator cuff tear. [10] (10.2106/00004623-198466080-00029)
- [L4] The outcome of RTSA does not seem to be negatively affected by the presence of an os acromiale. [11] (10.1016/j.jse.2017.02.012)
- [L4] Patients with a united os acromiale had a significantly better functional outcome as measured by the Constant score (P = .0169). [12] (10.1016/s1058-2746(98)90008-8)
- [L5] Surgical options for symptomatic os acromiale include arthroscopic sub-total excision, arthroscopic subacromial decompression of stable fragments, and open reduction and internal fixation of unstable fragments. [13] (10.5435/jaaos-d-17-00011)
- [L5] The advantages of this technique are improved visualization of the undersurface of the acromion, allowing excellent reduction, the possibility of treating concomitant shoulder pathologies, and to avoid increased morbidity of the open approach. [14] (10.1097/bte.0000000000000191)
- [L4] Our data suggest that the greater the distance of the AC joint from the anterior edge of the acromion, the higher the likelihood of an os acromiale. [15] (10.1067/mse.2003.128136)
- [L4] Ipsilateral os acromiale may be a relative contraindication to the clavicle hook plate. [16] (10.1186/s12891-021-04841-1)
- [L4] After 3 to 6 years of follow-up, all 6 shoulders were rated as excellent according to criteria similar to that of the American Shoulder and Elbow Surgeons. [18] (10.1016/s1058-2746(99)90004-6)
- [L4] Awareness of the os acromiale in the young athlete, appropriate clinical examination, and image studies are crucial to confirm diagnosis. [19] (10.1016/j.jseint.2020.02.008)
- [L4] [22] (10.1302/2058-5241.4.180100)
- [L4] Meta–os acromiale is the rarest subtype of os acromiale, and special consideration must be given to the type of tension-band construct used to achieve adequate compression and fixation. [23] (10.1177/03635465211028238)
- [L4] This case highlights that the synchondrosis of an os acromiale can be injured following trauma, though rarely, and emphasizes the need for appropriate radiographic investigation including axillary views and a flexible surgical approach. [24] (10.1016/j.jse.2008.02.012)
- [L5] Increased awareness of the diagnosis and improved techniques have shown that modified arthroscopic subacromial decompression can provide results similar to standard arthroscopic subacromial decompression for routine impingement. [25] (10.1097/00132589-200206000-00003)
- [L4] A symptomatic os acromiale in a competitive female fastball pitcher was treated successfully with open reduction and internal fixation. [27] (10.1177/0363546506288305)
- [L4] This new arthroscopic technique of fixation of os acromiale with absorbable screws provides promising clinical, cosmetic, and radiologic results with high patient satisfaction. [28] (10.1016/j.jse.2011.12.011)
- [L4] Symptomatic unstable os acromiale can be effectively treated with autogenous bone-grafting and internal fixation using a rigid tension-band construct and cannulated screws, which results in a high rate of union. [65] (10.2106/00004623-199809000-00011)
- [L4] At a two to five year followup all had fused. [69] (10.1016/s1058-2746(95)80192-8)
References
[1] Treatment of the Symptomatic Os Acromiale. Techniques in Shoulder and Elbow Surgery. 2004. DOI: 10.1097/00132589-200412000-00006
[2] Management of Os Acromiale. Techniques in Shoulder and Elbow Surgery. 2006. DOI: 10.1097/00132589-200609000-00006
[3] Prevalence of Os Acromiale in Thai Patients With Shoulder Problems: A Magnetic Resonance Imaging Study. Orthopaedic Journal of Sports Medicine. 2022. DOI: 10.1177/23259671221078806
[4] Os acromiale: systematic review of surgical outcomes. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2019.05.047
[5] Os Acromiale in Reverse Total Shoulder Arthroplasty: A Cohort Study. Orthopaedic Journal of Sports Medicine. 2020. DOI: 10.1177/2325967120965131
[6] Clinical implications of reverse total shoulder arthroplasty with an os acromiale: a systematic review. JSES Reviews, Reports, and Techniques. 2025. DOI: 10.1016/j.xrrt.2025.01.002
[7] Prevalence and factors associated with os acromiale: a multicenter study. JSES International. 2025. DOI: 10.1016/j.jseint.2025.05.015
[8] The prevalence and associated factors of os acromiale: a multicenter study. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2025.01.008
[9] Os Acromiale in Professional Tennis Players. Orthopaedic Journal of Sports Medicine. 2018. DOI: 10.1177/2325967118773723
[10] Rotator cuff tears associated with os acromiale.. The Journal of Bone & Joint Surgery. 1984. DOI: 10.2106/00004623-198466080-00029
[11] Reverse shoulder arthroplasty in patients with os acromiale. Journal of Shoulder and Elbow Surgery. 2017. DOI: 10.1016/j.jse.2017.02.012
[12] Transacromial approach to obtain fusion of unstable os acromiale. Journal of Shoulder and Elbow Surgery. 1998. DOI: 10.1016/s1058-2746(98)90008-8
[13] Symptomatic, Unstable Os Acromiale. Journal of the American Academy of Orthopaedic Surgeons. 2018. DOI: 10.5435/jaaos-d-17-00011
[14] Arthroscopic Internal Fixation of Symptomatic Os Acromiale. Techniques in Shoulder & Elbow Surgery. 2020. DOI: 10.1097/bte.0000000000000191
[15] Relationship between os acromiale and acromioclavicular joint anatomic position. Journal of Shoulder and Elbow Surgery. 2003. DOI: 10.1067/mse.2003.128136
[16] Os acromiale may be a contraindication of the clavicle hook plate: case reports and literature review. BMC Musculoskeletal Disorders. 2021. DOI: 10.1186/s12891-021-04841-1
[18] Successful osteosynthesis of an unstable mesoacromion in 6 shoulders: A new technique. Journal of Shoulder and Elbow Surgery. 1999. DOI: 10.1016/s1058-2746(99)90004-6
[19] The unstable os acromiale: a cause of pain in the young athlete. JSES International. 2020. DOI: 10.1016/j.jseint.2020.02.008
[21] Types of os acromiale according to Liberson. 2006.
[22] Os acromiale: a review of its incidence, pathophysiology, and clinical management. EFORT Open Reviews. 2019. DOI: 10.1302/2058-5241.4.180100
[23] Rare Symptomatic Meta–Os Acromiale in an Athlete. The American Journal of Sports Medicine. 2021. DOI: 10.1177/03635465211028238
[24] Fracture of an os acromiale with associated rupture of the coracoclavicular ligaments. Journal of Shoulder and Elbow Surgery. 2008. DOI: 10.1016/j.jse.2008.02.012
[25] Arthroscopic Management of the Mesoacromion. Techniques in Shoulder and Elbow Surgery. 2002. DOI: 10.1097/00132589-200206000-00003
[27] Surgical Stabilization of Os Acromiale in a Fast-Pitch Softball Pitcher. The American Journal of Sports Medicine. 2006. DOI: 10.1177/0363546506288305
[28] Arthroscopically assisted internal fixation of the symptomatic unstable os acromiale with absorbable screws. Journal of Shoulder and Elbow Surgery. 2012. DOI: 10.1016/j.jse.2011.12.011
[30] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Radiographic Evaluation.
[35] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > ANATOMY.
[37] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Applied Anatomy Related to Scapular Fractures.
[38] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Shoulder, Arm, and Elbow > I. Shoulder.
[49] Miller S Review Of Orthopaedics. Genetics of musculoskeletal conditions and abnormalities are summarized in Table 1.27 > UPPER EXTREMITY > SHOULDER.
[50] Orthopaedic Knowledge Update Sports Medicine 6. Diagnostic Ultrasonography and Ultrasonography-Guided Procedures > Annotated References.
[52] Apley And Solomon S Concise System Of Orthopaedics And Trauma. INVESTIGATION.
[59] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Shoulder Anatomy and Biomechanics, Clinical Evaluation, Imaging > Clinical Evaluation > Imaging.
[60] Aaos Comprehensive Orthopaedic Review 3. Imaging of the Shoulder and Elbow > I. Shoulder.
[62] Campbell S Operative Orthopaedics 4 Volume Set. ANTERIOR CRUCIATE LIGAMENT RECONSTRUCTION WITH BONE-PATELLAR TENDON-BONE GRAFT > Developmental Stages of Impingement Syndrome.
[65] The Treatment of Symptomatic Os Acromiale. The Journal of Bone & Joint Surgery*. 1998. DOI: 10.2106/00004623-199809000-00011
[69] Successful fusion of the unstable mesoacromion: Technique and report of five cases. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80192-8