Patients › General-Health
Sức khỏe xương và bệnh loãng xương
How bone strength affects fractures, fixation and recovery — bone density, fragility fractures, and what helps keep bones strong (lifestyle, supplements and medications).
Định nghĩa
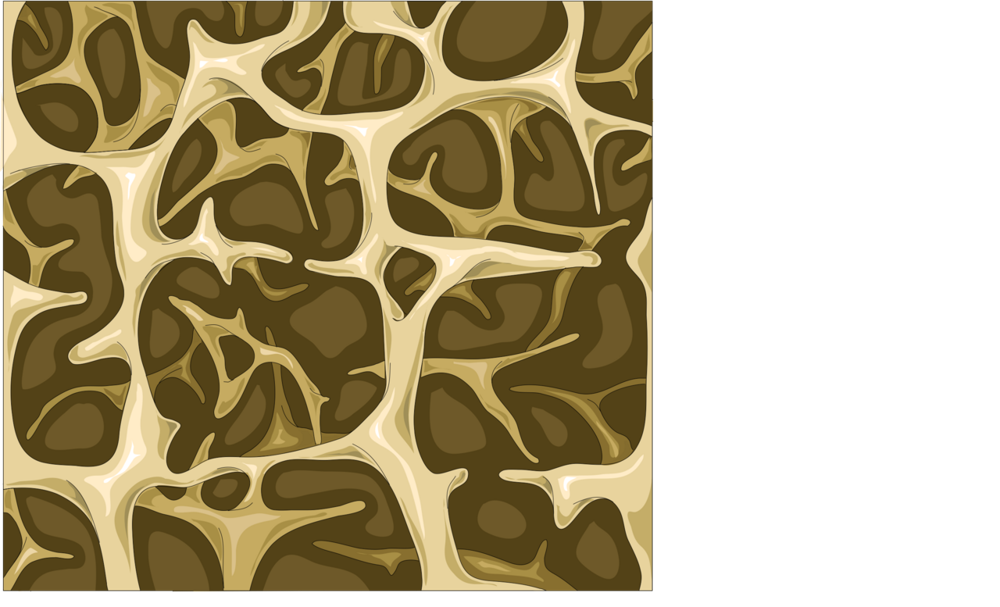
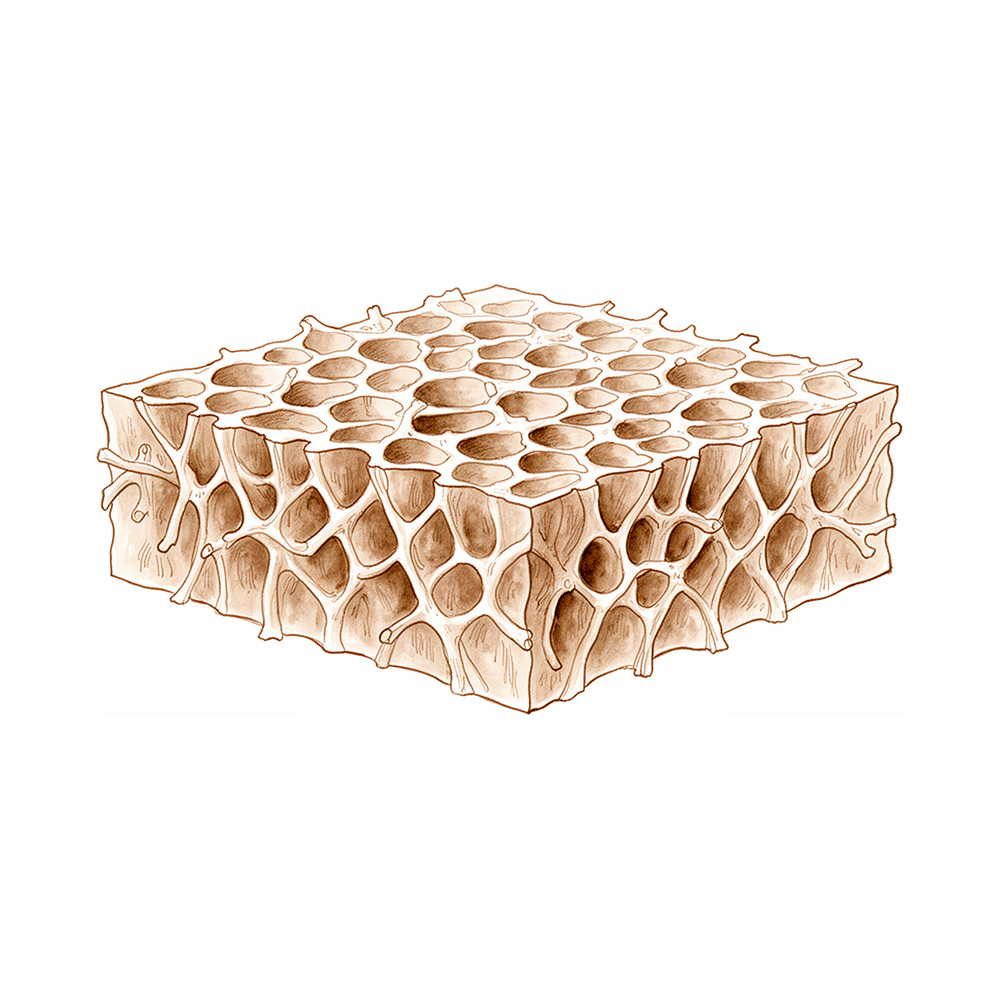
Loãng xương là tình trạng xương của bạn mất dần độ chắc khỏe. Theo thời gian, xương trở nên mỏng và dễ gãy, vì vậy xương có thể bị gãy chỉ sau một cú ngã nhẹ hoặc thậm chí một va chạm nhỏ. Những vị trí gãy xương thường gặp nhất là ở hông, cổ tay và cột sống.
Bạn có thể nghe đến thuật ngữ “gãy xương do xương yếu”. Thuật ngữ này chỉ một chiếc xương bị gãy dễ dàng hơn mức đáng lẽ phải có. Nếu bạn đã từng bị gãy xương kiểu này, đó có thể là dấu hiệu cảnh báo rằng xương của bạn yếu hơn bình thường.
Có một khoảng trống đã được biết đến trong việc chăm sóc ở đây. Nghiên cứu cho thấy những người bị gãy xương theo cách này thường không được kiểm tra loãng xương hoặc không được bắt đầu điều trị [1]. Điều này vẫn xảy ra dù đã có các hướng dẫn điều trị [2]. Điều này quan trọng vì việc điều trị tình trạng xương yếu bên dưới có thể làm giảm khả năng bị gãy xương lần nữa. Các thử nghiệm đã cho thấy điều trị loãng xương sau một lần gãy xương do xương yếu có thể giảm tới 50% nguy cơ gãy xương tiếp theo và giảm tỷ lệ tử vong tới 30% [3].
Xương không phải là thứ cố định, bất biến. Xương là mô sống, liên tục được phân hủy và tái tạo. Loãng xương xuất hiện khi quá trình phân hủy diễn ra nhanh hơn quá trình tái tạo, khiến mật độ xương giảm xuống. Mục tiêu của phòng ngừa là xây dựng bộ xương chắc khỏe nhất có thể, rồi duy trì độ chắc khỏe đó [4]. Mục tiêu của điều trị là ngăn chặn tình trạng mất xương tiếp diễn để lần gãy xương đầu tiên, hoặc một lần gãy xương khác, không bao giờ xảy ra [4].
Một phát hiện đáng biết: một phân tích tổng hợp chín nghiên cứu cho thấy cứ mỗi 1 đơn vị tăng thêm của chỉ số khối cơ thể có liên quan đến nguy cơ loãng xương giảm 9% [5]. Cân nặng cơ thể chỉ là một phần của bức tranh, bên cạnh các yếu tố như tuổi tác, nội tiết tố và sức khỏe tổng thể.
Nếu bạn đã bị gãy xương một cách dễ dàng, hoặc bạn lo lắng về độ chắc khỏe của xương, hãy hỏi về việc kiểm tra mật độ xương. Phát hiện loãng xương sớm giúp bạn có cơ hội tốt nhất để hành động trước khi xảy ra gãy xương.
Phương pháp này có hiệu quả không?
Câu trả lời thẳng thắn là việc điều trị hiệu quả nhất khi được bắt đầu sớm, và cách thực hiện điều đó vẫn còn chỗ cần cải thiện. Nghiên cứu cho thấy những người bị gãy xương cổ tay được kiểm tra loãng xương thường xuyên hơn nhiều khi họ tham gia một chương trình chuyên biệt so với khi được chăm sóc thông thường: 92% so với 23% [6]. Các nghiên cứu khác cho thấy những người bị gãy xương hông hoặc xương cột sống thường hoàn toàn không được bắt đầu điều trị tăng cường sức mạnh xương, mặc dù các hướng dẫn khuyến nghị điều đó [7] [2]. Đó là lý do tại sao việc hỏi về kiểm tra mật độ xương sau bất kỳ lần gãy xương dễ dàng nào lại quan trọng đến vậy.
Khi đã được chẩn đoán loãng xương, có bằng chứng cho thấy điều trị có thể giúp xương lành và giảm khả năng bị gãy xương lần nữa. Trong một thử nghiệm, những người bị gãy xương cổ tay được tiêm một loại hormone kích thích tạo xương đã lành xương sau 7.8 tuần, so với 12.6 tuần ở những người không được điều trị [8]. Tập luyện cũng có vai trò. Người bị loãng xương nên tập các bài tập kháng lực và bài tập chịu tác động để tối đa hóa độ chắc khỏe của xương, cùng với các hoạt động cải thiện sức mạnh và thăng bằng để giảm nguy cơ té ngã, và các bài tập duỗi cột sống để cải thiện tư thế [9].
Một số nghiên cứu mới hơn chưa có kết luận rõ ràng. Các công cụ học máy dự đoán loãng xương từ phim chụp hoặc xét nghiệm máu cho thấy triển vọng, nhưng các tổng quan nhận thấy chúng có nguy cơ sai lệch cao và chưa được kiểm chứng đầy đủ tại các phòng khám [10]. Và một phân tích cho thấy một loại thuốc điều trị tiểu đường từng được cho là có tác dụng bảo vệ xương đã không làm giảm gãy xương cổ tay và cánh tay sau khi tính đến các yếu tố sức khỏe khác [11]. Nếu bạn bị loãng xương và bị gãy xương, việc điều trị bản thân chỗ xương gãy sẽ hiệu quả hơn khi tình trạng xương yếu bên dưới được điều trị cùng lúc [12].
Những rủi ro là gì?
Rủi ro chính của việc không điều trị loãng xương là gãy xương. Nếu bạn đã từng bị một lần gãy xương do xương yếu, xương của bạn dễ bị gãy lần nữa hơn, đặc biệt nếu tình trạng xương yếu bên dưới không được điều trị [7] [2]. Nghiên cứu cho thấy điều trị được bắt đầu sau lần gãy xương đầu tiên làm giảm khả năng bị gãy xương lần nữa, và đây là lý do mạnh mẽ nhất để hành động sớm [3].
Cũng có những rủi ro xung quanh chính thời điểm bị gãy xương. Một nghiên cứu cho thấy những người bị loãng xương gặp nhiều biến chứng nội khoa hơn trong 90 ngày đầu sau phẫu thuật so với những người không bị loãng xương [13]. Xương gãy cũng có thể lành theo cách khác nhau tùy thuộc vào độ chắc khỏe của xương. Trong một nghiên cứu về gãy xương cổ tay di lệch, mức cải thiện biến dạng là 12.5 ở những người bị loãng xương, chưa bằng một nửa mức 25.6 ở những người có chất lượng xương tốt [14]. Một nghiên cứu khác cho thấy riêng tình trạng xương yếu ở người cao tuổi không ngăn cản xương gãy liền lại [15].
Nếu bạn bị loãng xương và cần phẫu thuật khớp hoặc gân, bức tranh rõ ràng hơn. Các tổng quan về phẫu thuật nội soi khâu chóp xoay không tìm thấy mối liên hệ giữa mật độ xương thấp hơn và kết quả sau 2 năm, và tỷ lệ biến chứng thấp [16] [17]. Không nên xem loãng xương là lý do để loại trừ phẫu thuật này [17].
Một số phương pháp điều trị có những điểm chưa chắc chắn riêng. Calcitonin dạng xịt mũi có hiệu quả kém hơn các loại thuốc điều trị xương khác trong việc làm chắc xương và giảm nguy cơ gãy xương [18]. Bằng chứng về châm cứu và các sản phẩm y học cổ truyền Trung Quốc vẫn còn ở giai đoạn đầu, và cần được kiểm chứng thêm [19] [20]. Đối với tiêm hormone tuyến cận giáp, thời điểm dùng thuốc tốt nhất vẫn đang được nghiên cứu trong các thử nghiệm [21].
Khoảng trống thực sự nằm ở việc theo dõi đến cùng. Các nghiên cứu cho thấy nhiều người bị gãy xương hông, cột sống hoặc cổ tay hoàn toàn không bao giờ được bắt đầu điều trị tăng cường sức mạnh xương [7] [2] [22]. Hỏi về việc điều trị sau bất kỳ lần gãy xương dễ dàng nào là bước an toàn nhất bạn có thể thực hiện.
Liệu phương pháp này có phù hợp với bạn không?
Điều trị tăng cường sức mạnh xương là điều đáng cân nhắc nếu bạn đã được cho biết xương của mình yếu, hoặc nếu bạn đã bị gãy xương dễ dàng hơn mức đáng lẽ phải có. Mục tiêu là ngăn chặn tình trạng mất xương tiếp diễn trước khi xảy ra lần gãy xương đầu tiên, hoặc một lần gãy xương khác [4]. Điều trị sau một lần gãy xương do xương yếu cũng quan trọng. Việc này có thể làm giảm khả năng bị gãy xương lần nữa và giảm tỷ lệ tử vong [3]. Nhưng nghiên cứu cho thấy nhiều người bị gãy xương hông, cột sống hoặc cổ tay hoàn toàn không bao giờ được bắt đầu điều trị [7] [2]. Vì vậy, nếu bạn đã từng bị gãy xương dễ dàng, việc hỏi bác sĩ về kiểm tra mật độ xương và liệu điều trị có giúp ích cho bạn hay không là hoàn toàn hợp lý.
Một số người ít có khả năng cần điều trị hơn. Nếu xương của bạn vẫn còn chắc khỏe, trọng tâm là giữ cho xương luôn như vậy: xây dựng bộ xương chắc khỏe nhất có thể, rồi duy trì độ chắc khỏe đó [4]. Tập luyện đóng một vai trò ở đây. Người bị loãng xương nên tập các bài tập kháng lực và bài tập chịu tác động để tối đa hóa độ chắc khỏe của xương [9]. Bác sĩ có thể giúp bạn xác định điều gì là an toàn cho bạn.
Điều trị không phải là một giải pháp áp dụng chung cho tất cả mọi người. Có nhiều loại thuốc điều trị xương khác nhau, và loại phù hợp phụ thuộc vào sức khỏe của bạn, tiền sử gãy xương và những ưu tiên riêng của bạn. Đây nên là quyết định chung giữa bạn và bác sĩ. Hãy hỏi xem mỗi lựa chọn bao gồm những gì, các tác dụng phụ có thể có là gì (được đề cập trong phần rủi ro ở trên), và bạn sẽ cần duy trì điều trị trong bao lâu. Nếu có điều gì chưa rõ, hãy tiếp tục hỏi cho đến khi bạn cảm thấy tự tin với kế hoạch.
Tóm lại
Điều trị loãng xương là điều đáng cân nhắc nếu xương của bạn yếu hoặc bạn đã bị gãy xương một cách dễ dàng. Mục tiêu là ngăn chặn tình trạng mất xương tiếp diễn trước khi xảy ra gãy xương, hoặc một lần gãy xương khác [4]. Hành động sớm rất quan trọng, vì điều trị sau một lần gãy xương do xương yếu có thể làm giảm khả năng bị gãy xương lần nữa và giảm tỷ lệ tử vong [3]. Lưu ý quan trọng nhất là việc theo dõi đến cùng: nhiều người bị gãy xương hông, cột sống hoặc cổ tay hoàn toàn không bao giờ được kiểm tra hay điều trị [7] [2]. Vì vậy, nếu bạn đã từng bị gãy xương dễ dàng, hãy đề nghị kiểm tra mật độ xương và tiếp tục hỏi cho đến khi bạn có một kế hoạch.
Tài liệu tham khảo
[1] The osteoporosis care gap in Canada. BMC Musculoskeletal Disorders. 2004. DOI: 10.1186/1471-2474-5-11
[2] A Missed Opportunity? Osteoporosis Treatment Following Femoral Neck Fractures: Reducing the Risk of Secondary Hip Fracture. The Journal of Arthroplasty. 2026. DOI: 10.1016/j.arth.2025.07.028
[3] Medical management of osteoporosis and the doctor's' role. Injury. 2016. DOI: 10.1016/s0020-1383(16)30014-6
[4] BONE HEALTH AND OSTEOPOROSIS. Clinics in Sports Medicine. 2000. DOI: 10.1016/s0278-5919(05)70201-5
[5] The association between body mass index and osteoporosis, with consideration of sex differences: a systematic review and dose-response meta-analysis. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09675-3
[6] Wristwatch—distal radial fracture as a marker for osteoporosis investigation:. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2004.04.001
[7] The Management of Pelvic and Vertebral Fragility Fractures: An Unmet Care Need. Journal of Bone and Joint Surgery. 2026. DOI: 10.2106/jbjs.26.00966
[8] Use of teriparatide in osteoporotic fracture patients. Injury. 2016. DOI: 10.1016/s0020-1383(16)30009-2
[9] Strong, steady and straight: UK consensus statement on physical activity and exercise for osteoporosis. British Journal of Sports Medicine. 2022. DOI: 10.1136/bjsports-2021-104634
[10] Risk prediction models for postmenopausal osteoporosis: a systematic review and meta-analysis study. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-025-09385-2
[11] Glucagon-like peptide-1 receptor agonist use for type 2 diabetes and risk of upper extremity fragility fracture. Injury. 2026. DOI: 10.1016/j.injury.2026.113456
[12] Continuity and volume of bone cement and anti osteoporosis treatment were guarantee of good clinical outcomes for percutaneous vertebroplasty: a multicenter study. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-024-08153-y
[13] Impact of osteoporosis on post-operative outcomes following rotator cuff repair. JSES Reviews, Reports, and Techniques. 2026. DOI: 10.1016/j.xrrt.2026.100723
[14] Osteoporosis and colles' fractures in the elderly. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90058-1
[15] A89 Osteoporosis is not a risk factor for the development of nonunion: a cohort nested case-control study. Injury. 2011. DOI: 10.1016/s0020-1383(11)70106-1
[16] No difference in 2-year outcomes of arthroscopic rotator cuff repair in patients with osteoporosis. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2025.02.011
[17] Osteoporosis is a risk factor for complications and reoperations at 1 and 3 years after arthroscopic rotator cuff repair. JSES International. 2026. DOI: 10.1016/j.jseint.2026.101678
[18] Revisiting Intranasal Salmon Calcitonin: Historical Osteoporosis Evidence and a Potential Role in Acute Orthopaedic Pain Management. JBJS Reviews. 2026. DOI: 10.2106/jbjs.rvw.26.00021
[19] Efficacy of acupuncture for primary osteoporosis: a systematic review and meta-analysis of randomized controlled trials. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05513-9
[20] Natural traditional Chinese medicine products: emerging therapeutic targets for the treatment of osteoporosis. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05879-w
[21] Timing optimization of teriparatide dosing for postmenopausal osteoporosis: a randomized controlled trial. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06083-6
[22] Incidence of Anti-osteoporosis Diagnosis and Treatment After Distal Radius Fractures. HAND. 2016. DOI: 10.1177/1558944716660555dj
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Fragility fractures represent a major and growing global health concern [15].
- Prevention of osteoporosis is accomplished by maximizing peak bone density and maintaining that bone density [6].
- The goal of osteoporosis treatment is to stop further bone loss to prevent a fracture or any subsequent fragility fractures [6].
- There is evidence of a care gap between the occurrence of a fragility fracture and the diagnosis and treatment of osteoporosis in Canada [12].
- Treatment of the underlying osteoporosis to prevent secondary fractures is rarely initiated following pelvic and vertebral fragility fractures [7].
- Treatments for pelvic and vertebral fragility fractures vary widely and are not always evidence-based [7].
- Wider recognition of common risk factors of osteoporosis and the expansion of screening protocols are necessary to ensure that osteoporosis is properly diagnosed and treated in patients receiving lumbar fusion [3].
- Findings from over one million cases support early, coordinated post-fracture osteoporosis treatment following an initial fragility fracture [4].
- The observational design of the study on recurrent hip fracture risk precludes causal inference [4].
- Each 1-unit increase in body mass index was associated with a 9% reduction in osteoporosis risk based on a dose-response analysis of nine studies [8].
- A bone density based aging model approach may facilitate and support the development of precision medicine strategies in osteoporosis prevention and management [1].
- A nomogram with an online dynamic calculator could facilitate the early prediction, diagnosis, and treatment of osteoporosis, contributing to the bone health of the elderly population and promoting the development of public health [20].
- Patients with osteoporosis may experience a higher incidence of medical complications within the 90-day global period than nonosteoporotic patients following rotator cuff repair [22].
- Overall rates of complication after arthroscopic rotator cuff repair were low, and osteoporosis should not be considered a contraindication to the procedure [33].
- Patients with distal radial fractures in elderly women should be screened for osteoporosis [23].
- The ability of monocytes to fuse declines significantly in patients with osteoporosis [55].
- Intranasal salmon calcitonin is less effective than bisphosphonates and modern anabolic agents for increasing bone mineral density and reducing fracture risk [11].
- The use of intranasal salmon calcitonin is best reserved for patients who cannot take first-line therapies due to contraindications, intolerance, or personal preference [11].
- Sequential anabolic-to-anti-resorptive therapy may inform treatment guidelines for high-risk postmenopausal populations [9].
- Current online health information on osteoporosis often fails to meet basic standards of evidence-based health information, highlighting the urgent need to improve quality to support informed decision-making [5].
- Investigators must select an osteoporotic fracture model that best reflects the clinical problem being studied and the underlying pathophysiology of the osteoporosis in the target patient group [2].
- There is no perfect model for osteoporosis, but a variety of models are appropriate for answering specific questions [10].
How It Works
Pathophysiology and Mechanisms
- Hypothalamic-pituitary disconnection leads to osteoporosis with a reduction in both trabecular and cortical bone caused by a low bone turnover situation, with reduced osteoblast and osteoclast activity [29].
- Evidence of early changes in bone geometry and increased bone turnover could be used to detect osteoporosis before estrogen deficiency has adversely affected bone strength [27].
- MiR-137 promotes TLR4/NF-κB pathway activity through targeting KDM4A, which inhibits osteogenic differentiation of human bone marrow mesenchymal stem cells and aggravates osteoporosis [37].
- The gut microbiota–metabolite–bone network may be involved in the skeletal effects of leptin, providing mechanistic insights for osteoporosis management [36].
- Macrophage polarization-related genes have potential causal roles in osteoporosis, though these findings are exploratory and require validation in bone marrow-specific and functional studies [35].
Risk Factors and Screening
- Each 1-unit increase in BMI was associated with a 9% reduction in osteoporosis risk based on a dose-response analysis of nine studies [8].
- Postmenopausal women with distal radius fractures have diminished bone mass, which might make a bone more likely to break [45].
- Machine learning application to hand radiographs represents a possible step toward more accessible, cost-effective, automated diagnosis and earlier treatment of osteoporosis/osteopenia [19].
- A nomogram with an online dynamic calculator developed based on NHANES data could facilitate the early prediction, diagnosis, and treatment of osteoporosis [20].
- A bone density-based aging model may facilitate the development of precision medicine strategies in osteoporosis prevention and management [1].
- Current online health information on osteoporosis often fails to meet basic standards of evidence-based health information, highlighting the need to improve quality to support informed decision-making [5].
Treatment and Management
- Prevention of osteoporosis can be accomplished by maximizing peak bone density and maintaining that bone density, although the goal of treatment is to stop further bone loss to prevent a fracture or any subsequent fragility fractures [6].
- Randomized controlled trials have demonstrated that treatment of osteoporosis in patients with fragility fractures can reduce the risk of subsequent fractures by up to 50% and mortality rates by up to 30% [18].
- Intranasal salmon calcitonin is less effective than bisphosphonates and modern anabolic agents for increasing BMD and reducing fracture risk, and its use is best reserved for patients who cannot take first-line therapies due to contraindications, intolerance, or personal preference [11].
- The current evidence suggests that the efficacy of acupuncture in improving the symptoms of primary osteoporosis is encouraging for its use in clinical practice as a physical intervention [16].
- Late osteoporosis treatment was associated with no significant further decline in periprosthetic BMD but did not reverse severe proximal bone loss [28].
- Treatment of the underlying osteoporosis to prevent secondary fractures is rarely initiated, and treatments for pelvic and vertebral fragility fractures vary widely and are not always evidence-based [7].
- These findings support early, coordinated post-fracture osteoporosis treatment, although the observational design precludes causal inference [4].
- A program for secondary osteoporotic fracture prevention is needed following distal radius fractures [30].
- Natural traditional Chinese medicine products provide a theoretical and experimental basis for the development of new drugs and the improvement of osteoporosis management [24].
- Findings from studies on long-term hospitalized patients with muscular dystrophy may help inform strategies for osteoporotic treatment and nutritional care in this patient population [17].
Fracture Healing and Repair
- The effect of ovariectomy on fracture repair was to delay healing as evidenced by histological and radiological analysis, and the deleterious effect might be more related to change of structure than to loss of BMD [41].
- In humans, de novo use of bisphosphonate therapy after fracture does not appear to have a significant effect on fracture healing [46].
- Although bone quality may be diminished in the elderly, this does not influence the occurrence of nonunion [47].
- Prior bisphosphonate treatment affects the mineralization pattern of the tissue repair consistently with a reduction in bone turnover, but does not abolish the repair process [26].
- There is some promising experimental and clinical evidence for possible enhancement of the bone repair process via administration of systemic agents [39].
- Fracture healing in SAMP6 mice is not detrimentally affected by impairment of bone marrow stem cell osteogenesis, suggesting that bone marrow-mediated repair processes are dispensable for normal bone healing in this senile osteoporotic fracture model [44].
- Cracks in bone following bisphosphonate treatment were shorter than in control or ovariectomized groups, which may explain why increased damage levels following bisphosphonate treatment have not led to increased fractures [40].
- Bone histomorphometry revealed that bone architecture in the treatment group using a calcitonin release system was improved and results were not different from those observed after calcitonin injection [31].
Clinical Outcomes and Assessment
- There was no relationship between decreased bone mineral density and 2-year clinical outcomes following arthroscopic rotator cuff repair in patients with osteoporosis [21].
- Multiscale biomechanical assessment approaches have potential applications in fracture risk assessment, the design of patient-specific implants, and research into the mechanisms of bone metabolic diseases [38].
- Investigators must select an animal model that best reflects the clinical problem being studied and the underlying pathophysiology of the osteoporosis in the target patient group [2].
What the Evidence Shows
Epidemiology and Risk Factors
- Fragility fractures are a major and growing global health concern [15].
- Each 1-unit increase in body mass index is associated with a 9% reduction in osteoporosis risk [8].
- Type 2 diabetes shows significant associations with femoral neck and total body bone mineral density, while HbA1c shows significant associations with heel bone mineral density [56].
- Osteoporosis is present in long-term hospitalized patients with muscular dystrophy, informing strategies for osteoporotic treatment and nutritional care in this population [17].
Diagnosis and Screening
- There is a care gap between the occurrence of a fragility fracture and the diagnosis and treatment of osteoporosis in Canada [12].
- Osteoporosis screening gaps exist among patients undergoing lumbar fusion surgery, necessitating wider recognition of risk factors and expanded screening protocols [3].
- Patients with distal radial fractures should be screened for osteoporosis [23].
- Intervention programs for distal radius fractures increased the rate of osteoporosis investigation from 26.6% in controls to 87.5% in intervention participants [32].
- Intervention subjects for distal radial fractures were investigated for osteoporosis at a rate of 92%, compared to 23% in the usual-care group [43].
- Machine learning models applied to hand radiographs represent a step toward more accessible, cost-effective, and automated diagnosis of osteoporosis and osteopenia [19].
- A fracture risk prediction model based on routine blood test markers was successfully developed and validated for patients newly diagnosed with osteoporosis [52].
- Current machine learning-based prediction models for postmenopausal osteoporosis without fractures demonstrate good discriminative ability but are characterized by a high risk of bias, lack of calibration performance evaluation, and insufficient validation of clinical utility [58].
- Online health information on osteoporosis often fails to meet basic standards of evidence-based health information [5].
Treatment and Management
- Prevention of osteoporosis can be accomplished by maximizing peak bone density and maintaining that bone density [6].
- Treatment of osteoporosis in patients with fragility fractures can reduce the risk of subsequent fractures by up to 50% and mortality rates by up to 30% [18].
- Early, coordinated post-fracture osteoporosis treatment is supported by findings from over one million cases, though the observational design precludes causal inference [4].
- Treatment of the underlying osteoporosis to prevent secondary fractures is rarely initiated in patients with pelvic and vertebral fragility fractures [7].
- Patients receiving parathyroid hormone (1–84) injections experienced accelerated radiographic and clinical fracture healing at 7.8 weeks compared to 12.6 weeks in untreated patients [48].
- Late osteoporosis treatment was associated with no significant further decline in periprosthetic bone mineral density but did not reverse severe proximal bone loss after cementless total hip arthroplasty [28].
- Continuous bone cement and standardized treatment for osteoporosis were guarantees of good clinical outcomes for percutaneous vertebroplasty [50].
- Injected bone cement greater than 5.5 ml might be a guarantee of good clinical outcomes for percutaneous vertebroplasty [50].
- Prior bisphosphonate treatment affects the mineralization pattern of tissue repair following vertebral fragility fracture, consistent with reduced bone turnover, but does not abolish the repair process [26].
- The efficacy of acupuncture in improving the symptoms of primary osteoporosis is encouraging for its use in clinical practice as a physical intervention [16].
- Key recommendations for people with osteoporosis include undertaking resistance and impact exercise to maximize bone strength [34].
- Key recommendations for people with osteoporosis include activities to improve strength and balance to reduce falls [34].
- Key recommendations for people with osteoporosis include spinal extension exercise to improve posture and potentially reduce the risk of falls and vertebral fractures [34].
Surgical Outcomes and Complications
- There is no relationship between decreased bone mineral density and 2-year clinical outcomes following arthroscopic rotator cuff repair [21].
- Patients with osteoporosis may experience a higher incidence of medical complications within the 90-day global period following rotator cuff repair than nonosteoporotic patients [22].
- In severely displaced distal radial fractures, the final improvement in bony deformity was significantly less in patients with osteoporosis compared to those without [53].
- The initial deformity in severely displaced distal radial fractures was not influenced by osteoporosis [53].
Research Models
- Hypothalamic-pituitary disconnection leads to low turnover osteoporosis in sheep after 12 months, characterized by a reduction in both trabecular and cortical bone with reduced osteoblast and osteoclast activity [29].
Practical Considerations
Screening and Diagnosis
- A bone density-based aging model approach may facilitate the development of precision medicine strategies in osteoporosis prevention and management [1].
- Machine learning application to hand radiographs represents a possible step toward more accessible, cost-effective, automated diagnosis and earlier treatment of osteoporosis or osteopenia [19].
- In a study of wristwatch interventions, seven of the eight remaining intervention participants were investigated for osteoporosis (87.5%), compared to four of the remaining 15 control subjects (26.6%) [32].
- Patients with hand fragility fractures represent a high-risk cohort that is currently underserved by osteoporosis screening pathways [42].
- A cortical bone thickness average below 4.5 mm should prompt DXA referral to improve preoperative bone health assessment without added cost or radiation [49].
Treatment and Management
- Intranasal salmon calcitonin is less effective than bisphosphonates and modern anabolic agents for increasing bone mineral density and reducing fracture risk, and its use is best reserved for patients who cannot take first-line therapies due to contraindications, intolerance, or personal preference [11].
- Findings from a prospective observational study highlight opportunities for systematic primary and secondary fracture prevention and structured medication review prior to femoral fracture [25].
- Findings from a retrospective cross-sectional study may help inform strategies for osteoporotic treatment and nutritional care in long-term hospitalized patients with muscular dystrophy [17].
Surgical Considerations
- Despite previous literature showing the negative effect of osteoporosis on rotator cuff healing, data showed no relationship between decreased bone mineral density and 2-year clinical outcomes following arthroscopic rotator cuff repair [21].
Lifestyle and Prevention
- Key recommendations for people with osteoporosis include undertaking resistance and impact exercise to maximise bone strength [34].
- Key recommendations for people with osteoporosis include spinal extension exercise to improve posture and potentially reduce risk of falls and vertebral fractures [34].
Research Models
Key Evidence
- [L3] This approach may facilitate and support the development of precision medicine strategies in osteoporosis prevention and management. [1] (10.1186/s12891-025-09298-0)
- [L5] Investigators must select a model that best reflects the clinical problem being studied, and the underlying pathophysiology of the osteoporosis in the target patient group. [2] (10.1016/s0020-1383(16)30004-3)
- [Paper] Wider recognition of common risk factors of osteoporosis and the expansion of screening protocols are necessary to ensure that osteoporosis is properly diagnosed and treated in patients receiving lumbar fusion. [3] (10.5435/jaaos-d-26-00335)
- [Paper] These findings support early, coordinated post-fracture osteoporosis treatment; the observational design precludes causal inference. [4] (10.1016/j.injury.2026.113865)
- [Paper] Current OHI on osteoporosis often fails to meet basic standards of EBHI, highlighting the urgent need to improve the quality to support informed decision-making. [5] (10.1186/s12891-026-09711-2)
- [Paper] Prevention of osteoporosis can be accomplished by maximizing peak bone density and maintaining that bone density, although the goal of treatment is to stop further bone loss to prevent a fracture or any subsequent fragility fractures. [6] (10.1016/s0278-5919(05)70201-5)
- [L5] The treatments vary widely and are not always evidence-based and, unfortunately, treatment of the underlying osteoporosis to prevent secondary fractures is rarely initiated. [7] (10.2106/jbjs.26.00966)
- [L1] Based on our dose-response analysis of nine studies, each 1-unit increase in BMI was associated with a 9% reduction in osteoporosis risk. [8] (10.1186/s12891-026-09675-3)
- [L1] This sequential anabolic-to-anti-resorptive therapy may inform treatment guidelines for high-risk postmenopausal populations. [9] (10.1186/s13018-025-06040-3)
- [Paper] However, there is no perfect model for osteoporosis, but a variety of models appropriate for answering specific questions. [10] (10.1016/s0020-1383(16)30002-x)
- [Paper] IN-CAL is less effective than bisphosphonates and modern anabolic agents for increasing BMD and reducing fracture risk; accordingly, its use is best reserved for patients who cannot take first-line therapies due to contraindications, intolerance, or personal preference. [11] (10.2106/jbjs.rvw.26.00021)
- [L4] There is evidence of a care gap between the occurrence of a fragility fracture and the diagnosis and treatment of osteoporosis in Canada. [12] (10.1186/1471-2474-5-11)
- [Paper] Fragility fractures are a major and growing global health concern. [15] (10.1016/j.injury.2026.113902)
- [L1] The current evidence suggests that the efficacy of acupuncture in improving the symptoms of primary osteoporosis is encouraging for its use in clinical practice as a physical intervention. [16] (10.1186/s13018-025-05513-9)
- [L4] These findings may help inform strategies for osteoporotic treatment and nutritional care in this patient population. [17] (10.1186/s12891-026-10045-2)
- [Paper] Randomized controlled trials have demonstrated that treatment of osteoporosis in patients with fragility fractures can reduce the risk of subsequent fractures by up to 50% and mortality rates by up to 30%. [18] (10.1016/s0020-1383(16)30014-6)
- [L2] The findings represent a possible step toward more accessible, cost-effective, automated diagnosis and therefore earlier treatment of osteoporosis/osteopenia. [19] (10.1016/j.jhsa.2024.09.008)
- [L3] Ultimately, this tool could facilitate the early prediction, diagnosis, and treatment of osteoporosis, thus contributing to the bone health of the elderly population and promoting the development of public health. [20] (10.1186/s12891-026-09920-9)
- [L3] Despite previous literature showing the negative effect of osteoporosis on rotator cuff healing, our data showed no relationship between decreased bone mineral density and 2-year clinical outcomes following RCR. [21] (10.1016/j.jse.2025.02.011)
- [L3] In addition, patients with osteoporosis may experience a higher incidence of medical complications within the 90-day global period than nonosteoporotic patient. [22] (10.1016/j.xrrt.2026.100723)
- [L4] It is the authors' opinion that such patients should be screened for osteoporosis. [23] (10.1016/j.jhsb.2004.05.002)
- [L4] This paper summarises recent research progress on natural TCM products in preventing and treating osteoporosis and provides a theoretical and experimental basis for the development of new drugs and the improvement of osteoporosis management. [24] (10.1186/s13018-025-05879-w)
- [L3] These findings highlight important opportunities for systematic primary and secondary fracture prevention and structured medication review. [25] (10.1007/s00402-026-06401-5)
- [L4] Prior bisphosphonate treatment affects the mineralization pattern of the tissue repair consistently with a reduction in bone turnover as found in post-menopausal osteoporotic women, but does not abolish the repair process. [26] (10.1002/jor.22026)
- [Paper] Therefore, evidence of early changes in bone geometry and increased bone turnover could be used to detect osteoporosis before estrogen deficiency has adversely affected bone strength. [27] (10.1002/jor.20961)
- [Paper] Late osteoporosis treatment was associated with no significant further decline in periprosthetic BMD but did not reverse severe proximal bone loss. [28] (10.1007/s00264-026-07068-8)
- [Paper] HPD leads after 12 month to osteoporosis with a reduction in both trabecular and cortical bone caused by a low bone turnover situation, with reduced osteoblast and osteoclast activity, as compared to controls (OVX). [29] (10.1002/jor.22066)
- [L4] The results of our study evidenced the need of a program for secondary osteoporotic fracture prevention; this program has now been developed and is active at our institution. [30] (10.1177/1558944716660555dj)
- [Paper] Bone histomorphometry revealed that bone architecture in the treatment group was improved and results were not different from those observed after calcitonin injection. [31] (10.1016/s0736-0266(01)00074-7)
- [L1] Seven of the eight remaining intervention participants were investigated for osteoporosis (87.5%), compared to four of the remaining 15 control subjects (26.6%). [32] (10.1197/j.jht.2003.10.030)
- [L3] Overall rates of complication were low and osteoporosis should not be considered a contraindication to arthroscopic RCR. [33] (10.1016/j.jseint.2026.101678)
- [L5] Key recommendations are that people with osteoporosis should undertake (1) resistance and impact exercise to maximise bone strength; (2) activities to improve strength and balance to reduce falls; (3) spinal extension exercise to improve posture and potentially reduce risk of falls and vertebral fractures. [34] (10.1136/bjsports-2021-104634)
- [Paper] These findings are exploratory and hypothesis-generating and require validation in bone marrow-specific and functional studies. [35] (10.1186/s13018-026-06905-1)
- [Paper] These findings suggest that the gut microbiota–metabolite–bone network may be involved in the skeletal effects of leptin, providing novel mechanistic insights and potential therapeutic strategies for osteoporosis management. [36] (10.1186/s12891-026-09950-3)
- [Paper] This mechanism inhibits osteogenic differentiation of human bone marrow mesenchymal stem cells and aggravates osteoporosis. [37] (10.1186/s13018-023-03918-y)
- [L5] It explores the potential applications of these multiscale approaches in fracture risk assessment, the design of patient-specific implants, and research into the mechanisms of bone metabolic diseases. [38] (10.1016/j.injury.2026.113659)
- [Paper] There is some promising experimental and clinical evidence for possible enhancement of the bone repair process via administration of systemic agents. [39] (10.1016/s0020-1383(16)30003-1)
- [Paper] However, these cracks were shorter than in control or OVX groups which may provide one explanation as to why increased damage levels following bisphosphonate treatment have not lead to increased fractures. [40] (10.1002/jor.21229)
- [Paper] The effect of OVX on fracture repair was to delay healing as evidenced by histological and radiological analysis, and the evidence suggests that the deleterious effect might be more related to change of structure than to loss of BMD. [41] (10.1002/jor.20505)
- [L3] Patients with hand fragility fractures represent a high-risk cohort that is currently underserved by osteoporosis screening pathways. [42] (10.1016/j.injury.2026.113261)
- [L2] Results indicate that 92% of the intervention subjects were investigated for osteoporosis, compared with the usual-care group, in which only 23% were investigated. [43] (10.1197/j.jht.2004.04.001)
- [Paper] Fracture healing in SAMP6 mice is not detrimentally affected by impairment of BMSC osteogenesis, suggesting that bone marrow-mediated repair processes are dispensable for normal bone healing in this senile osteoporotic fracture model. [44] (10.1002/jor.21041)
- [L4] They also have diminished bone mass, which might make a bone more likely to break. [45] (10.1016/0363-5023(88)90227-4)
- [L4] In humans, de novo use of bisphosphonate therapy after fracture does not appear to have a significant effect on fracture healing. [46] (10.1016/s0020-1383(16)30015-8)
- [L3] Although bone quality may be diminished in the elderly, this does not influence the occurrence of nonunion. [47] (10.1016/s0020-1383(11)70106-1)
- [Paper] Patients who received the PTH (1–84) injections accelerated radiographic and clinical fracture healing (7.8 weeks) when compared to patients who received no treatment (12.6 weeks). [48] (10.1016/s0020-1383(16)30009-2)
- [L4] A CBTavg below 4.5 mm should prompt DXA referral, improving preoperative bone health assessment without added cost or radiation. [49] (10.1177/17585732261491314)
- [L3] Continuous bone cement and standardized treatment for osteoporosis were guarantees of good clinical outcomes for PVP, and injected bone cement >5.5 ml might be a guarantee. [50] (10.1186/s12891-024-08153-y)
- [L3] We successfully developed and validated a fracture risk prediction model for patients newly diagnosed with osteoporosis. [52] (10.1186/s12891-026-09768-z)
- [L3] In severely displaced fractures, the initial deformity was not influenced by osteoporosis, but the final improvement in bony deformity was significantly less in patients with osteoporosis. [53] (10.1016/0266-7681(87)90058-1)
- [L4] It was clearly demonstrated that the ability of monocytes to fuse declines significantly in patients with osteoporosis. [55] (10.1002/jor.1100180215)
- [Paper] The results show varying associations across different BMD sites (femoral neck, lumbar spine, heel, total body) and methods (IVW, MR-Egger, Weighted median), with some significant associations found for T2D on femoral neck and total body BMD, and HbA1c on heel BMD. [56] (10.1186/s12891-024-07430-0)
- [L1] Current machine learning-based prediction models for postmenopausal osteoporosis without fractures demonstrate good discriminative ability but are generally characterized by a high risk of bias, a notable lack of calibration performance evaluation, and insufficient validation of clinical utility. [58] (10.1186/s12891-025-09385-2)
References
[1] Unveiling risk factors and predicting osteoporosis through bone density based aging model: a community-based cohort in Guangdong, China. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-09298-0
[2] Main differences in osteoporotic fracture models: which should I use?. Injury. 2016. DOI: 10.1016/s0020-1383(16)30004-3
[3] Osteoporosis Screening Gaps Among Patients Undergoing Lumbar Fusion Surgery. Journal of the American Academy of Orthopaedic Surgeons. 2026. DOI: 10.5435/jaaos-d-26-00335
[4] Osteoporosis Treatment Gaps and Risk of Recurrent Hip Fracture Following Initial Fragility Fracture: Insights from Over One Million Cases. Injury. 2026. DOI: 10.1016/j.injury.2026.113865
[5] Mapping the quality of information on osteoporosis: a cross-sectional analysis of online health information. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09711-2
[6] BONE HEALTH AND OSTEOPOROSIS. Clinics in Sports Medicine. 2000. DOI: 10.1016/s0278-5919(05)70201-5
[7] The Management of Pelvic and Vertebral Fragility Fractures: An Unmet Care Need. Journal of Bone and Joint Surgery. 2026. DOI: 10.2106/jbjs.26.00966
[8] The association between body mass index and osteoporosis, with consideration of sex differences: a systematic review and dose-response meta-analysis. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09675-3
[9] Effectiveness of anabolic and anti-resorptive agents for preventing postmenopausal osteoporosis fractures: a systematic review and network meta-analysis. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06040-3
[10] Can we induce osteoporosis in animals comparable to the human situation?. Injury. 2016. DOI: 10.1016/s0020-1383(16)30002-x
[11] Revisiting Intranasal Salmon Calcitonin: Historical Osteoporosis Evidence and a Potential Role in Acute Orthopaedic Pain Management. JBJS Reviews. 2026. DOI: 10.2106/jbjs.rvw.26.00021
[12] The osteoporosis care gap in Canada. BMC Musculoskeletal Disorders. 2004. DOI: 10.1186/1471-2474-5-11
[15] Fragility fractures: an increasing issue in the ageing population worldwide. Injury. 2026. DOI: 10.1016/j.injury.2026.113902
[16] Efficacy of acupuncture for primary osteoporosis: a systematic review and meta-analysis of randomized controlled trials. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05513-9
[17] Osteoporosis in long-term hospitalized patients with muscular dystrophy: a retrospective cross-sectional study. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-10045-2
[18] Medical management of osteoporosis and the surgeons' role. Injury. 2016. DOI: 10.1016/s0020-1383(16)30014-6
[19] Application of Machine Learning to Osteoporosis and Osteopenia Screening Using Hand Radiographs. The Journal of Hand Surgery. 2025. DOI: 10.1016/j.jhsa.2024.09.008
[20] A nomogram with online dynamic calculator for predicting osteoporosis: development and validation based on NHANES. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09920-9
[21] No difference in 2-year outcomes of arthroscopic rotator cuff repair in patients with osteoporosis. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2025.02.011
[22] Impact of osteoporosis on post-operative outcomes following rotator cuff repair. JSES Reviews, Reports, and Techniques. 2026. DOI: 10.1016/j.xrrt.2026.100723
[23] The Distal Radial Fracture in Elderly Women and the Bone Mineral Density of the Lumbar Spine and Hip. Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsb.2004.05.002
[24] Natural traditional Chinese medicine products: emerging therapeutic targets for the treatment of osteoporosis. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05879-w
[25] Osteoporosis treatment gap prior to femoral fracture and prevalence of pharmacological risk factors: a prospective observational study. Archives of Orthopaedic and Trauma Surgery. 2026. DOI: 10.1007/s00402-026-06401-5
[26] Mineralization pattern of vertebral bone material following fragility fracture of the spine. Journal of Orthopaedic Research. 2012. DOI: 10.1002/jor.22026
[27] Structural adaptation and intracortical bone turnover in an ovine model of osteoporosis. Journal of Orthopaedic Research. 2009. DOI: 10.1002/jor.20961
[28] Long-term periprosthetic femoral bone loss after cementless total hip arthroplasty: natural history and response to late osteoporosis treatment. International Orthopaedics. 2026. DOI: 10.1007/s00264-026-07068-8
[29] Low turnover osteoporosis in sheep induced by hypothalamic‐pituitary disconnection. Journal of Orthopaedic Research. 2012. DOI: 10.1002/jor.22066
[30] Incidence of Anti-osteoporosis Diagnosis and Treatment After Distal Radius Fractures. HAND. 2016. DOI: 10.1177/1558944716660555dj
[31] Calcitonin release system in the treatment of experimental osteoporosis. Histomorphometric evaluation. Journal of Orthopaedic Research. 2001. DOI: 10.1016/s0736-0266(01)00074-7
[32] Wristwatch: distal radius fractures as a marker for osteoporosis investigation. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2003.10.030
[33] Osteoporosis is a risk factor for complications and reoperations at 1 and 3 years after arthroscopic rotator cuff repair. JSES International. 2026. DOI: 10.1016/j.jseint.2026.101678
[34] Strong, steady and straight: UK consensus statement on physical activity and exercise for osteoporosis. British Journal of Sports Medicine. 2022. DOI: 10.1136/bjsports-2021-104634
[35] Macrophage polarization-related genes with potential causal roles in osteoporosis: a multi-omics Mendelian randomization study. Journal of Orthopaedic Surgery and Research. 2026. DOI: 10.1186/s13018-026-06905-1
[36] Role and mechanism of leptin in improving osteoporosis via the “gut–bone axis”. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09950-3
[37] MiR-137 promotes TLR4/NF-κB pathway activity through targeting KDM4A, inhibits osteogenic differentiation of human bone marrow mesenchymal stem cells and aggravates osteoporosis. Journal of Orthopaedic Surgery and Research. 2023. DOI: 10.1186/s13018-023-03918-y
[38] Progress in Multiscale Biomechanical Assessment of Cancellous Bone: From Bone Density to Multiscale Mechanical Phenotypes. Injury. 2026. DOI: 10.1016/j.injury.2026.113659
[39] Fracture repair: general aspects and influence of osteoporosis and anti-osteoporosis treatment. Injury. 2016. DOI: 10.1016/s0020-1383(16)30003-1
[40] Effects of estrogen deficiency and bisphosphonate therapy on osteocyte viability and microdamage accumulation in an ovine model of osteoporosis. Journal of Orthopaedic Research. 2010. DOI: 10.1002/jor.21229
[41] Effect of osteoporosis on bone mineral density and fracture repair in a rat femoral fracture model. Journal of Orthopaedic Research. 2007. DOI: 10.1002/jor.20505
[42] Hand fragility fractures as a missed opportunity for secondary prevention: A retrospective cohort study and assessment of the Second Metacarpal Cortical Index. Injury. 2026. DOI: 10.1016/j.injury.2026.113261
[43] Wristwatch—distal radial fracture as a marker for osteoporosis investigation:. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2004.04.001
[44] Influence of defective bone marrow osteogenesis on fracture repair in an experimental model of senile osteoporosis. Journal of Orthopaedic Research. 2010. DOI: 10.1002/jor.21041
[45] Postural stability and bone density in postmenopausal women with distal radius fractures. The Journal of Hand Surgery. 1988. DOI: 10.1016/0363-5023(88)90227-4
[46] How do bisphosphonates affect fracture healing?. Injury. 2016. DOI: 10.1016/s0020-1383(16)30015-8
[47] A89 Osteoporosis is not a risk factor for the development of nonunion: a cohort nested case-control study. Injury. 2011. DOI: 10.1016/s0020-1383(11)70106-1
[48] Use of teriparatide in osteoporotic fracture patients. Injury. 2016. DOI: 10.1016/s0020-1383(16)30009-2
[49] Magnetic resonance imaging-based cortical thickness as a predictor of osteoporosis in rotator cuff tears. Shoulder & Elbow. 2026. DOI: 10.1177/17585732261491314
[50] Continuity and volume of bone cement and anti osteoporosis treatment were guarantee of good clinical outcomes for percutaneous vertebroplasty: a multicenter study. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-024-08153-y
[52] SuperLearner approach for predicting imminent risk of fracture in older Chinese patients with newly diagnosed osteoporosis based on their routine blood test markers. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09768-z
[53] Osteoporosis and colles' fractures in the elderly. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90058-1
[55] Ability of osteoclast formation from peripheral monocytes using anti‐fusion regulatory protein‐1/cd98/4f2 monoclonal antibodies in patients with osteoporosis. Journal of Orthopaedic Research. 2000. DOI: 10.1002/jor.1100180215
[56] Diabetes and osteoporosis: a two-sample mendelian randomization study. BMC Musculoskeletal Disorders. 2024. DOI: 10.1186/s12891-024-07430-0
[58] Risk prediction models for postmenopausal osteoporosis: a systematic review and meta-analysis study. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-025-09385-2