Những triệu chứng bạn đang gặp phải
Bệnh lý thần kinh trên vai có nghĩa là dây thần kinh chi phối hai cơ vùng vai của bạn đang bị kéo giãn hoặc bị chèn ép. Tình trạng này thường biểu hiện bằng đau, yếu cơ, hoặc cả hai. Cơn đau thường nằm ở phía sau vai, gần góc trên của xương bả vai, và thường là cảm giác đau âm ỉ chứ không phải cơn đau nhói dữ dội.
Các hoạt động đưa tay lên cao có thể làm tình trạng nặng thêm, nên những việc như với tay lên kệ cao, phơi quần áo hoặc ném bóng cho chó có thể làm các triệu chứng bùng lên. Một số người nhận thấy vai có cảm giác bị vướng, bị kẹt cứng hoặc có tiếng lục cục khi cử động. Đau nhức về đêm làm ảnh hưởng giấc ngủ là điều thường gặp ở các vấn đề về vai nói chung, và nếu cơn đau làm bạn thức giấc vào ban đêm hoặc không dịu đi sau nhiều tuần, hãy đến gặp bác sĩ đa khoa hoặc yêu cầu được bác sĩ chuyên khoa thăm khám.
Khi dây thần kinh bị kích thích trong thời gian dài, các cơ do nó chi phối có thể bị teo đi. Bạn có thể nhận thấy một chỗ hõm hoặc lõm bên dưới gai xương bả vai ở phía sau, hoặc cánh tay nhanh mỏi khi dang ngang sang bên. Yếu cơ khi nâng cánh tay và khi xoay cẳng tay ra ngoài là biểu hiện điển hình. Một số người bị teo cơ như vậy mà rất ít đau, đó là lý do tình trạng này thường không được phát hiện trong một thời gian.
Những công việc hằng ngày cần sức mạnh hoặc cần với tay trở nên khó khăn hơn: nhấc ấm nước, kéo áo len qua đầu, hoặc áp điện thoại lên tai trong thời gian dài. Nếu các triệu chứng nặng dần lên trong nhiều tuần hoặc khiến bạn không thể sử dụng cánh tay, bạn nên đi khám thay vì chờ cho qua.
Có một dấu hiệu khẩn cấp bạn cần biết. Nếu cánh tay, bàn tay hoặc các ngón tay trở nên nóng, đỏ, sưng và đau, đặc biệt khi kèm theo sốt, hãy đến khoa cấp cứu ngay trong ngày.
Điều gì đang thực sự xảy ra
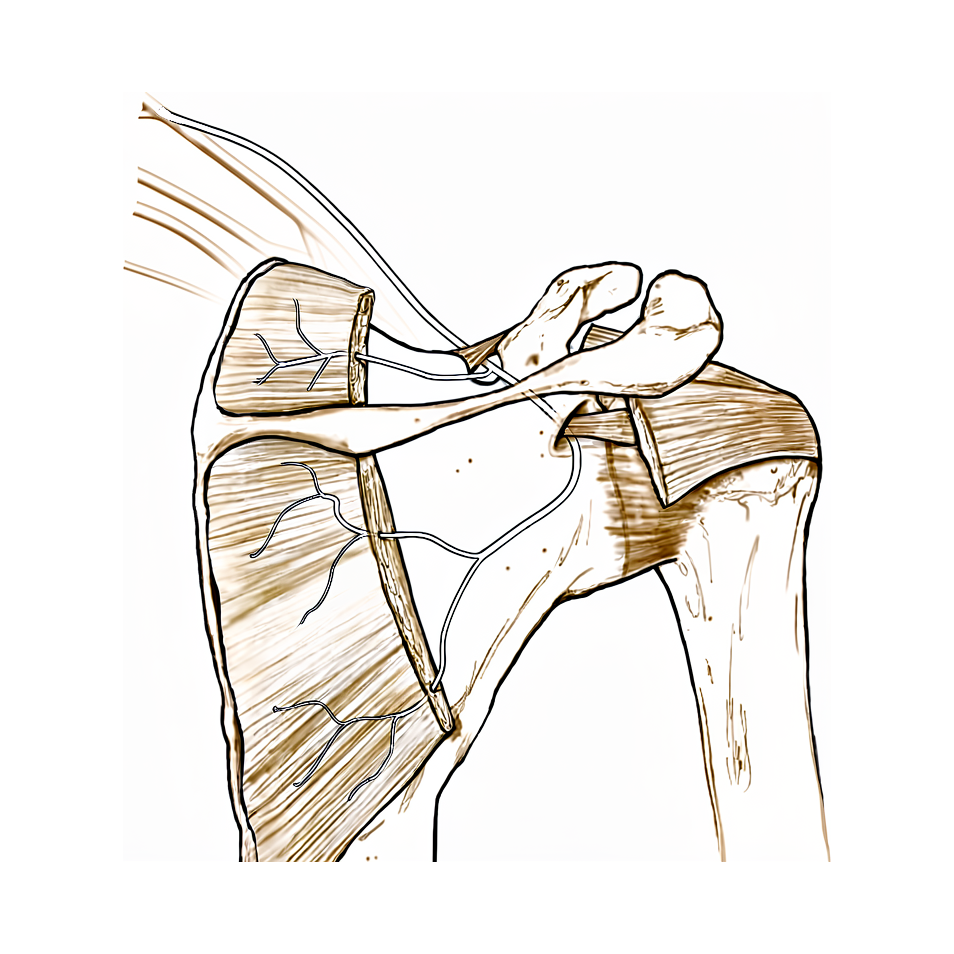
Dây thần kinh trên vai là một dây thần kinh nhỏ chạy ngang qua phía sau xương bả vai và chi phối hai cơ vùng vai của bạn. Dây thần kinh này đi theo một đường quanh co, đi qua hai khe hẹp nơi mô phía trên nó căng chặt, giống như một sợi cáp chạy bên dưới một sợi dây đai. Tại khe thứ nhất, gần phía trên xương bả vai, một dây chằng bắt ngang qua dây thần kinh. Xa hơn dọc theo đường đi, tại khe thứ hai gần nơi vai tiếp giáp với xương bả vai, có một dải mô khác nằm đè lên nó.
Vì dây thần kinh bị ép qua những chỗ hẹp này, bất cứ thứ gì chiếm chỗ trong vùng này đều có thể đè lên nó. Một túi chứa dịch, gọi là nang hạch (ganglion), có thể phát triển từ một vết rách ở vành sụn quanh ổ khớp vai và đè ép dây thần kinh dọc theo đường đi của nó. Dây chằng phía trên khe thứ nhất cũng có thể bị cứng hóa thành xương, hoặc bản thân khe này có thể hẹp bất thường, khiến dây thần kinh có ít chỗ hơn. Một khối máu tụ lớn gần xương bả vai cũng có thể gây ra tình trạng tương tự.
Dây thần kinh cũng có thể bị kéo giãn thay vì bị chèn ép. Việc lặp đi lặp lại các động tác đưa tay lên cao, như giao bóng tennis hoặc đập bóng chuyền, sẽ kéo căng dây thần kinh khi cánh tay đưa lên và ra sau. Một vết rách cơ chóp xoay lâu ngày cũng có thể gây ra tác động tương tự, vì khi gân bị kéo tách ra, cơ sẽ dịch chuyển và giật kéo dây thần kinh tại chỗ nó bị giữ bên dưới sợi dây đai đó. Một chấn thương đột ngột giật mạnh vai ra sau trong khi đầu quay sang hướng ngược lại cũng vậy.
Dù nguyên nhân là gì, kết quả đều giống nhau. Dây thần kinh không còn dẫn truyền tín hiệu đúng cách, nên hai cơ do nó chi phối, vốn giúp nâng cánh tay và xoay cẳng tay ra ngoài, sẽ yếu đi và có thể teo lại. Đó là lý do bạn bị đau ở phía sau vai và yếu cơ như đã mô tả ở phần trên.
Những biện pháp chúng tôi có thể áp dụng
Bác sĩ Kieran Hirpara, bác sĩ phẫu thuật chi trên tại Bệnh viện tư nhân Mater Rockhampton, sẽ bắt đầu bằng các phương pháp ít xâm lấn nhất phù hợp với tình trạng của bạn. Thông thường, bệnh nhân được bác sĩ đa khoa giới thiệu đến phòng khám chúng tôi; nếu vật lý trị liệu viên khuyên bạn nên đến gặp chúng tôi, bạn vẫn cần có giấy giới thiệu từ bác sĩ đa khoa để được hưởng mức hoàn trả từ chương trình Medicare. Trong buổi khám tại phòng khám, chúng tôi sẽ hỏi bệnh sử, khám vai và chỉ định chụp hình ảnh khi cần thiết để xác nhận chẩn đoán.
Hầu hết mọi người bắt đầu bằng điều trị không phẫu thuật. Bạn cho vai nghỉ ngơi và thay đổi những hoạt động làm các triệu chứng bùng lên, chẳng hạn như công việc phải đưa tay lên cao lặp đi lặp lại. Thuốc chống viêm dạng viên có thể giúp giảm đau trong thời gian ngắn. Vật lý trị liệu nhằm giữ cho vai cử động tự do và tăng cường sức mạnh cho các cơ quanh xương bả vai, bao gồm cả các cơ giữ xương bả vai áp vững vào các xương sườn. Thông thường chúng tôi cho phương pháp này một thời gian thử đầy đủ, ít nhất 6 tháng, trước khi nghĩ đến phẫu thuật, trừ khi có một nguyên nhân rõ ràng đang đè lên dây thần kinh hoặc cơ ở phía sau vai đã bắt đầu teo đi; trong trường hợp đó, chúng tôi rút ngắn thời gian thử này, không quá 3 tháng, để dây thần kinh không bị tổn thương vĩnh viễn.
Nếu các bước này chưa giúp bạn đỡ đủ, phẫu thuật có thể được cân nhắc. Ca mổ này giải phóng dải mô căng đang đè lên dây thần kinh, tạo thêm khoảng trống cho dây thần kinh. Ca mổ được thực hiện qua các vết rạch nhỏ với camera nội soi, hoặc đôi khi qua một đường mổ mở nhỏ. Chúng tôi sẽ trao đổi kỹ với bạn về việc phương pháp này có phù hợp với vai của bạn hay không và cùng nhau quyết định.
Sau phẫu thuật, cánh tay của bạn được đặt trong một chiếc đai treo tay đơn giản cho dễ chịu, và các bài tập đung đưa nhẹ nhàng (bài tập con lắc) được bắt đầu ngay lập tức. Bạn sẽ gặp lại chúng tôi sau 1 tuần để kiểm tra sức cơ và bắt đầu vật lý trị liệu với vật lý trị liệu viên của bạn, khởi đầu bằng các cử động có hỗ trợ và các bài tập siết cơ. Các bài tập có kháng lực và hoạt động đưa tay lên cao được bắt đầu trong khoảng từ 4 đến 8 tuần sau ca mổ.
Những điều bạn có thể mong đợi
Với hầu hết mọi người, việc điều trị tình trạng này bắt đầu mà không cần phẫu thuật. Cho vai nghỉ ngơi, thay đổi những hoạt động làm các triệu chứng bùng lên, dùng thuốc chống viêm dạng viên và vật lý trị liệu là những bước đầu tiên thường áp dụng. Với cách tiếp cận này, cơn đau thường dịu đi và vai có thể hoạt động bình thường trở lại.
Nếu dây thần kinh vẫn tiếp tục bị chèn ép, phẫu thuật giải phóng dải mô căng đang đè lên nó có thể giúp giảm đau và giúp vai hoạt động bình thường trở lại. Quá trình hồi phục mất nhiều tháng, không phải vài ngày. Sức mạnh của hai cơ bị ảnh hưởng hồi phục chậm, và các bài tập có hướng dẫn cùng vật lý trị liệu viên giúp bảo vệ vai trong khi vai hồi phục. Ở những trường hợp cơ đã bị teo, chỗ hõm ở phía sau xương bả vai thường cải thiện khi dây thần kinh hồi phục, mặc dù vẫn có thể còn lại một phần teo cơ ngay cả khi đã hết đau.
Nếu có kèm theo một vết rách lớn ở cơ chóp xoay, việc sửa chữa gân bị rách, dù chỉ một phần, có thể giúp giảm lực kéo căng lên dây thần kinh và để dây thần kinh hồi phục cùng với chức năng của vai.
Nếu không được xử lý, một dây thần kinh bị kích thích không phải lúc nào cũng tự dịu đi. Áp lực kéo dài lên một dây thần kinh có thể dẫn đến những thay đổi vĩnh viễn ở các cơ do nó chi phối, vì vậy những triệu chứng không dịu đi sau nhiều tuần nên được thăm khám thay vì chờ cho qua. Nếu các triệu chứng nặng dần lên, làm bạn thức giấc vào ban đêm, hoặc khiến bạn không thể sử dụng cánh tay, hãy đến gặp bác sĩ đa khoa hoặc yêu cầu được bác sĩ chuyên khoa thăm khám.
Khi nào nên đi khám
Hãy đến gặp bác sĩ đa khoa hoặc yêu cầu được bác sĩ chuyên khoa thăm khám nếu bạn bị đau ở phía sau vai không dịu đi sau nhiều tuần, hoặc bị yếu khi nâng cánh tay hay khi xoay cẳng tay ra ngoài. Hãy đi khám sớm hơn nếu chỗ hõm bên dưới xương bả vai đang teo đi thấy rõ, hoặc nếu bạn bị đau âm ỉ kèm cảm giác bị vướng, bị kẹt cứng hoặc có tiếng lục cục ở vai, vì điều này có thể cho thấy có một vết rách ở vành sụn quanh ổ khớp. Một vấn đề dây thần kinh như thế này nên được kiểm tra bằng xét nghiệm thần kinh thay vì chờ cho qua, vì áp lực kéo dài có thể để lại những thay đổi vĩnh viễn ở các cơ. Nếu cánh tay, bàn tay hoặc các ngón tay trở nên nóng, đỏ, sưng và đau, đặc biệt khi kèm theo sốt, hãy đến khoa cấp cứu ngay trong ngày.
Phân tích chi tiết hơn
Advanced reading: the deeper science (optional)
Phần này đi sâu hơn mức cần thiết để bạn có thể tự đưa ra quyết định điều trị. Bệnh lý thần kinh trên vai xứng đáng được nghiên cứu kỹ hơn vì dây thần kinh này đóng hai vai trò hoàn toàn khác nhau: vừa là nguyên nhân gây đau và yếu vùng vai, vừa là mục tiêu để giảm đau. Tuy nhiên, chất lượng các bằng chứng hỗ trợ cho hai vai trò này lại rất khác nhau.
Phương pháp giải ép có hiệu quả, nhưng cần lưu ý về việc xác định nguyên nhân
Khi dây thần kinh bị chèn ép, việc giải ép sẽ mang lại hiệu quả rõ rệt. Trên 730 bệnh nhân, việc giải ép dây thần kinh trên vai cải thiện đáng kể các kết quả được bệnh nhân ghi nhận, không thua kém so với các thủ thuật tương tự được thực hiện mà không có bước giải ép, đồng thời giúp tỷ lệ bệnh nhân trở lại tập luyện thể thao cao và tỷ lệ biến chứng thấp [1].
Yếu tố quan trọng góp phần mang lại hiệu quả này là việc thủ thuật “không thua kém so với các thủ thuật tương tự mà không giải ép”. Thông thường, dây thần kinh này được giải ép trong quá trình phẫu thuật vì các lý do khác, chẳng hạn như sửa chữa cơ vùng vai hoặc loại bỏ u nang hạch ở xương bả vai; vì vậy việc xác định chắc chắn rằng sự cải thiện là do chính việc giải ép gây ra là điều khó khăn. Tuy nhiên, việc giải ép vẫn có lợi và không làm ảnh hưởng tiêu cực đến các thủ thuật đi kèm.
Tại sao mức độ chèn ép lại ảnh hưởng đến biểu hiện lâm sàng?
Dây thần kinh đi qua hai chỗ hẹp khi vòng quanh xương bả vai; chỗ nào bị chèn ép sẽ quyết định các triệu chứng xuất hiện.
Khi bị chèn ép tại rãnh trên xương bả vai (vị trí cao hơn), cả cơ trên gai và cơ dưới gai đều bị ảnh hưởng, gây ra tình trạng yếu sức khi nâng tay và xoay ngoài cánh tay, kèm theo đau. Khi bị chèn ép tại rãnh xương gai – ổ chảo, nằm xa hơn về phía dưới, chỉ có cơ dưới gai bị ảnh hưởng; dẫn đến yếu sức khi xoay ngoài cánh tay và teo cơ rõ rệt ở vùng lõm phía dưới gai bả vai, thường ít gây đau.
Tình trạng teo cơ đơn thuần này thường bị bỏ sót vì hầu như không gây đau. Nguyên nhân phổ biến nhất ở vị trí này là u nang ganglion xuất phát từ vết rách môi khớp; vì vậy việc phát hiện ra kiểu biểu hiện này cần thúc đẩy việc tìm kiếm u nang và vết rách đó, vì điều trị nguyên nhân mới giúp cải thiện tình trạng dây thần kinh.
Về mặt giảm đau, bằng chứng khoa học còn hạn chế so với mức độ sử dụng thực tế
Dây thần kinh này thường được gây tê bằng thuốc gây tê cục bộ để giảm đau vùng vai, cả sau phẫu thuật lẫn trong các trường hợp mạn tính. Qua việc xem xét các tác hại vật lý ở 4,142 bệnh nhân, phương pháp gây tê này có nguy cơ gây hại vật lý thấp. Tuy nhiên, các tác giả cũng chỉ ra sự không đồng nhất trong phương pháp can thiệp cũng như chất lượng bằng chứng còn kém, đồng thời kêu gọi cần đánh giá và báo cáo các tác hại một cách chính xác hơn [2].
“Nguy cơ gây hại thấp dù chất lượng bằng chứng còn kém” là một khẳng định cụ thể và có phạm vi hạn chế. Nó chỉ cho thấy phương pháp gây tê này tương đối an toàn; không phải là lời khẳng định về hiệu quả điều trị, và cũng không nên được hiểu như vậy.
Điểm mấu chốt cần ghi nhớ
Có hai tình trạng cùng mang tên dây thần kinh này nhưng không nên bị nhầm lẫn với nhau. Bệnh thần kinh là tình trạng tổn thương cấu trúc khi dây thần kinh bị chèn ép; tình trạng này thường có thể được giải ép, với các dấu hiệu điển hình là teo cơ và yếu cơ. Việc chặn dây thần kinh chỉ là biện pháp điều trị triệu chứng nhằm ngăn chặn tín hiệu đau từ khớp mà không làm thay đổi bất kỳ yếu tố cấu trúc nào.
Nếu có hiện tượng yếu cơ và teo cơ rõ rệt, đó là dấu hiệu của bệnh thần kinh. Ngược lại, nếu chỉ có đau mà không có các dấu hiệu trên, nguyên nhân đau thường nằm ở nơi khác; việc chặn dây thần kinh giúp giảm đau nhưng không phải là bằng chứng xác nhận chẩn đoán bệnh thần kinh.
Tài liệu tham khảo
[1] Sandler AB, Wells ME, Tran C, Arakawa R, Klahs KJ, Scanaliato JP, và cộng sự. Tỷ lệ cao bệnh nhân trở lại tập luyện sau can thiệp giải ép dây thần kinh trên vai: một phân tích tổng quan có hệ thống. JSES Rev Rep Tech. 2024;4(4):654-61. https://doi.org/10.1016/j.xrrt.2024.05.007
[2] Annison DR, Smith N, Salt E, Noblet T, Rangan A, McDaid C. Những tác hại về thể chất liên quan đến các thủ thuật chặn dây thần kinh trên vai: một phân tích tổng quan có hệ thống. Shoulder Elbow. 2024;17(3):236-53. https://doi.org/10.1177/17585732241255679
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- The exact association and etiology of suprascapular neuropathy in patients with rotator cuff pathology remain unclear [1].
- Entrapment of the suprascapular nerve is frequently overlooked in the differential diagnosis of shoulder pain until profound weakness and denervation atrophy of the spinatus musculature are apparent [2].
- Shoulder surgeons should consider electrophysiologic evaluation of patients with clinical or radiographic signs of suprascapular neuropathy and be cognizant of the parameters that constitute an abnormal study [3].
- Combined injuries of the axillary and the suprascapular nerve cause complete loss of shoulder function [4].
- Suprascapular neuropathy with complete neurogenic fatty replacement has been described in patients with intact rotator cuff tendons in the absence of traction or compression mechanisms [5].
- Preoperative suprascapular nerve injuries do not have a significant clinical impact and do not predispose to an acute postoperative lesion [6].
- In a young, active cohort, suprascapular neuropathy presented with one of two distinct primary presenting complaints: pain or weakness [7].
- Twenty-eight patients with suprascapular nerve entrapment confirmed by electromyographic and nerve conduction studies were identified and treated [8].
- Arthroscopic SSN decompression for suprascapular neuropathy at the suprascapular and/or spinoglenoid notch in the absence of major concomitant glenohumeral pathology results in good functional outcomes with significant improvements from before to after surgery [9].
- In the absence of a well-defined lesion producing mechanical compression of the suprascapular nerve, suprascapular neuropathy should be treated non-operatively [10].
- Initial treatment of isolated suprascapular neuropathy is typically nonoperative, consisting of physical therapy, nonsteroidal anti-inflammatory drugs, and activity modification [11].
- Open or arthroscopic operative intervention is warranted when there is extrinsic nerve compression or progressive pain and/or weakness [11].
- The authors believe that with practice and meticulous technique, arthroscopic release can be mastered and will become the preferred treatment method for suprascapular neuropathy [12].
- No recommendations regarding suprascapular nerve release in conjunction with rotator cuff repair can be made at this time, and further research is necessary to better delineate the indications in the future [13].
- Treatment of choice for suprascapular nerve entrapment at the spinoglenoid notch caused by a ganglion cyst is surgical decompression of the suprascapular nerve by complete excision of the ganglion along with its pedicle [17].
- Full recovery of the nerve may not be expected in each case following surgical decompression for ganglion cysts [17].
- Decompression of the suprascapular nerve at the spinoglenoid notch did not lead to a better functional outcome compared to repair alone in patients with posterosuperior massive rotator cuff tears and suprascapular neuropathy [19].
- Release of the spinoglenoid ligament with resultant suprascapular nerve decompression may result in relief of pain and a return of normal shoulder function [20].
- Operative injury to the suprascapular nerve during cuff mobilization can occur [24].
- Other factors such as inadequate cuff muscle function are more frequently responsible for the poor functional outcomes seen after successful repairs of massive rotator cuff tears than operative injury to the suprascapular nerve [24].
- Combined arthroscopic release of the superior transverse scapular ligament and rotator cuff repair in patients with large/massive RCTs and suprascapular neuropathy did not produce statistically significant improved outcomes compared with repair of the rotator cuff alone [29].
- A host of other factors such as inadequate cuff muscle function may be responsible for poor functional outcomes seen following the repair of massive RCTs [34].
- Arthroscopic release of the suprascapular nerve can be performed safely and effectively, with all patients showing improvement in postoperative electromyographic findings and marked improvement in pain relief and function [48].
- Twelve percent of patients who received RTSA were assessed to be at high risk of iatrogenic suprascapular neuropathy by baseplate screw penetration [95].
Anatomy & Pathophysiology
Nerve Course and Entrapment Sites
- The suprascapular nerve courses from the upper trunk of the brachial plexus to its motor insertion on the supraspinatus and, more distally, the infraspinatus [21].
- The superior transverse scapular ligament arises from the medial base of the coracoid overlying the suprascapular notch [53].
- The suprascapular artery runs superior to the superior transverse scapular ligament, while the nerve runs deep to the ligament [53].
- Entrapment of the suprascapular nerve at the suprascapular notch causes denervation of both the supraspinatus and the infraspinatus [53].
- The spinoglenoid ligament overlies the suprascapular nerve at the spinoglenoid notch [53].
- Entrapment, traction, or compression of the suprascapular nerve at the spinoglenoid notch causes denervation of the infraspinatus [53].
- The inferior transverse scapular ligament was present in 33 shoulders (82.5%) in an anatomical study [32].
- In 52 of 60 shoulders, the suprascapular artery was located on the transverse ligament and positioned superiolaterally [88].
- Anatomical variations at the suprascapular notch, including abnormally oriented subscapularis muscle fibers, anterior coracoscapular ligament, and calcified superior transverse scapular ligament, are predisposing factors for suprascapular nerve entrapment [92].
- The distances from the posterolateral corner of the acromion to the suprascapular and spinoglenoid notches were approximately 43 and 32 mm, respectively, regardless of height and sex [91].
- The suprascapular nerve is furthest away from the posterior edge of the glenoid with the shoulder at 90 degrees of external rotation [40].
- Gender and specific scapular dimensions influence the dimensions of the safe zone for avoiding suprascapular nerve injury during shoulder arthroscopy [98].
Mechanisms of Injury
- Suprascapular nerve injury can occur from either compression or traction [21].
- Nerve traction is theorized to arise from chronic overhead athletics or due to a retracted rotator cuff tear [21].
- Cystic lesions arising from a labral or capsular tear can compress the nerve along its course over the scapula [21].
- During cross-body adduction and internal rotation of the glenohumeral joint, the interaction of the spinoglenoid ligament and the posterior capsule results in a tightening of the spinoglenoid ligament [87].
- Secondary to the spinoglenoid ligament's attachment to the posterior capsule, horizontal adduction and internal rotation of the shoulder creates tension on the ligament that entraps the suprascapular nerve under it in the lateral corner of the tunnel [83].
- The suprascapular nerve can be damaged during muscle advancement in two phases: detachment of the supraspinatus muscle from the supraspinatus fossa and excessive tension applied when shifting the muscle laterally [97].
- Shoulder arthroscopy portals placed according to anatomic studies of the suprascapular nerve may still produce nerve injury in the presence of unknown anatomic variants [30, 31].
- Placement of the superior and posterior screws in the glenoid baseplate during reverse total shoulder arthroplasty risks injury to the suprascapular nerve [94].
Pathophysiology and Clinical Consequences
- Suprascapular neuropathy with complete neurogenic fatty replacement can occur in patients with intact rotator cuff tendons in the absence of traction or compression mechanisms [5].
- Suprascapular nerve injury is an underlying mechanism leading to compromise of the rotator cuff enthesis structure [33].
- In suprascapular nerve palsy, the upward rotation of the glenoid cavity occurred in the early phase of arm elevation, whereas in axillary nerve palsy it occurred in the late phase [16].
- The unexpected humeral head shift following suprascapular nerve entrapment can lead to proprioception disturbance and cause functional instability if the coordinated and conditioned muscles were not functioning very well [80].
- The ubiquitin–proteasome pathway was a major contributor to the atrophy seen following suprascapular nerve denervation, whereas autophagy was a major contributor following tendon transection [89].
- Protein synthesis is up-regulated in rotator cuff muscle atrophy following both tendon transection and suprascapular nerve denervation [89].
Classification
- Suprascapular neuropathy can present secondary to various etiologies including entrapment or compression [21].
- Cystic lesions arising from a labral or capsular tear can compress the suprascapular nerve along its course over the scapula [21].
- Entrapment of the suprascapular nerve usually occurs at the suprascapular or spinoglenoid notch [27].
- Suprascapular neuropathy is frequently overlooked in the differential diagnosis of shoulder pain until profound weakness and denervation atrophy of the spinatus musculature are apparent [2].
- Bilateral suprascapular nerve entrapment syndrome associated with rotator cuff tear is a rare condition [25].
- Suprascapular neuropathy has been described with complete neurogenic fatty replacement in patients with intact rotator cuff tendons in the absence of traction or compression mechanisms [5].
- Chronic rotator cuff tendon tears and suprascapular neuropathy are both associated with fatty infiltration and muscle atrophy of the rotator cuff muscles, but the pattern of fatty infiltration is markedly different in the two situations [22].
- Suprascapular nerve entrapment has been associated with a lipoma at the spinoglenoid notch [14, 15].
- Suprascapular nerve entrapment at the spinoglenoid notch has been caused by a ganglion cyst [17].
- Varicose veins at the spinoglenoidal notch are an unusual cause of suprascapular nerve compression [27].
- Suprascapular nerve injury at the spinoglenoid notch can occur after glenoid neck fracture [30, 31].
- In suprascapular nerve palsy, the upward rotation of the glenoid cavity occurred in the early phase of arm elevation [16].
- In axillary nerve palsy, the upward rotation of the glenoid cavity occurred in the late phase of arm elevation [16].
Clinical Presentation
Symptoms and Pain Characteristics
- Patients with suprascapular entrapment complain primarily of deep burning or aching pain in the posterior and lateral aspect of the shoulder [28].
- Suprascapular nerve neuropathy is a potential source of shoulder pain and functional limitation [21].
- Patients with SSN neuropathy usually complain of a dull, aching pain in the posterior and lateral aspects of the shoulder [79].
- Compression at the spinoglenoid ligament is often insidious at onset with less severe symptoms compared to compression at the suprascapular notch [45].
- Patients often present with a chief complaint of a diffuse ache around the shoulder region with the pain most commonly localized to the region 4 cm medial to the posterolateral corner of acromion as well as the posterior aspect of the glenohumeral joint [45].
- Symptoms may be accompanied by complaints of catching, locking, or clicking, likely the result of a concomitant labral tear [45].
- All shoulder motion may be painful initially, but within a few weeks only external rotation is limited unless a frozen shoulder develops [28].
Physical Examination and Functional Deficits
- Weakness of external rotation and atrophy of the supraspinous and infraspinous muscles follows suprascapular entrapment [28].
- Appreciable physical examination findings may include painful palpation at the spinoglenoid notch [45].
- When the nerve is entrapped at the suprascapular notch, patients present with weakness and atrophy of both the supraspinatus and infraspinatus [79].
- With entrapment at the spinoglenoid notch, symptoms are isolated to the infraspinatus [79].
- Visible atrophy of the infraspinatus is a clinical sign that may warrant minimal nonoperative treatment duration to avoid irreversible damage [45].
Diagnostic Evaluation
- The diagnosis of suprascapular neuropathy is based on a combination of a detailed history, a comprehensive physical examination, imaging, and electrodiagnostic studies [21].
- The key to diagnosis of suprascapular nerve entrapment is electrodiagnostic evaluation [28].
- Electromyography demonstrates denervation of the supraspinous and infraspinous muscles, and there is increased motor latency of the suprascapular nerve across the transverse scapular ligament [28].
- A complete history and physical, careful attention to auxiliary tests, and treatment of multiple diagnoses in the same shoulder avoids missed pathologic features and necessity for revision operations [15].
- Bilateral suprascapular nerve entrapment syndrome associated with rotator cuff tear is a rare condition that can lead to correct early diagnosis through awareness of its clinical presentation [25].
Etiology and Associated Pathology
- Suprascapular nerve neuropathy occurs when the suprascapular nerve is injured along its course from the upper trunk of the brachial plexus to its motor insertion on the supraspinatus and, more distally, the infraspinatus [21].
- Nerve injury can occur from either compression or traction [21].
- Suprascapular neuropathy can present with complete neurogenic fatty replacement in patients with intact rotator cuff tendons in the absence of traction or compression mechanisms [5].
- Forceful shoulder abduction may have caused the sudden onset of suprascapular neuropathy in the loosely compressed suprascapular nerve by the lipoma [14].
- The incidence of compressive neuropathy is quite high in the overhead athletic cohort, but most patients do not show clinically relevant deficiencies in function [21].
Investigations
Electrophysiology
- Electromyography demonstrates denervation of the supraspinatus and infraspinatus muscles in suprascapular nerve entrapment [28].
- Increased motor latency of the suprascapular nerve across the transverse scapular ligament is a finding in suprascapular nerve entrapment [28].
- Electrophysiologic evaluation is recommended for patients with clinical or radiographic signs of suprascapular neuropathy [3].
- Twenty-eight patients with suprascapular nerve entrapment were identified and treated using electromyographic and nerve conduction studies [8].
- Suprascapular neuropathy outcomes in overhead athletes are improved when the nerve is decompressed in the presence of electrodiagnostic evidence of neuropathy [36].
Magnetic Resonance Imaging
- MRI is the modality of choice for evaluating the rotator cuff, biceps, and subacromial/subdeltoid bursa [74].
- T1-weighted MRI can reveal fatty infiltration of the infraspinatus muscle [75].
- High-resolution magnetic resonance imaging is recommended to evaluate complex cases of nerve entrapment [96].
- Suprascapular neuropathy with complete neurogenic fatty replacement can occur in patients with intact rotator cuff tendons [5].
- MRI can identify labral tears and rotator cuff tears, although accuracy for these is enhanced by combining the scan with arthrography [67].
- MR arthrography increases sensitivity and specificity for detecting injuries to the capsulolabral–ligamentous complex compared to traditional MRI [72].
- In a meta-analysis of 6 studies including 4,667 shoulders, MRA had greater diagnostic test accuracy for glenoid labral lesions than MRI, with MRA sensitivity of 88% and specificity of 93% versus MRI sensitivity of 76% and specificity of 87% [72].
- Abduction and external rotation (ABER) positioning during MRA increases the sensitivity for detecting anteroinferior labroligamentous injury [72].
- A comparative analysis found that full routine MRI or MRA examination had similar accuracy as the ABER sequence in evaluating the anteroinferior labral–ligamentous complex [72].
- MRI accuracy in identifying labral and rotator cuff tears ranges from 70% to 100% [72].
- T2-weighted MRI provides better visualization of full-thickness rotator cuff tears [74].
- MR arthrography is considered the benchmark for evaluation of labral tears and is rarely indicated for evaluation of rotator cuff pathology [74].
- CT arthrography is indicated when MRI or MR arthrography is contraindicated, such as in patients with pacemakers or vascular clips [74].
Ultrasonography
- Ultrasonography is a low-cost alternative to MRI and arthrography for evaluating skeletal and soft-tissue structures of the shoulder [74].
- Ultrasonography can provide immediate, real-time visualization of the rotator cuff, biceps tendon, and calcific deposits [74].
- Ultrasonography can be used to detect atrophy of rotator cuff muscles [74].
- Ultrasonography is highly operator-dependent and is not as useful for evaluating labral tears or rotator cuff tears that are very small or larger than 3 cm [74].
- Ultrasonography is a simple and accurate test for identifying rotator cuff tears and calcific tendinitis [67].
- Ultrasonography can be useful in guiding injections or barbotage [67].
- The sensitivity of ultrasonography for the detection of full-thickness rotator cuff tears is 98% [75].
- The specificity of ultrasonography for the detection of full-thickness rotator cuff tears is 80% [75].
- The positive predictive value of ultrasonography for the detection of full-thickness rotator cuff tears is 90% [75].
- The negative predictive value of ultrasonography for the detection of full-thickness rotator cuff tears is 95% [75].
- The accuracy of ultrasonography for the detection of full-thickness rotator cuff tears is 94% [75].
Plain Radiography and CT
- The standard shoulder series should include a true AP view in the scapular plane, an AP view, an axillary view, and a scapular Y view [75].
- The true AP view in the scapular plane visualizes the anterior greater tuberosity in profile and can reveal proximal humeral migration [75].
- The axillary view is necessary for the evaluation of glenohumeral joint instability and enables determination of the humeral head position in the glenoid fossa [75].
- The axillary view may detect occult, locked posterior shoulder dislocation in a patient who exhibits a lack of passive external rotation [75].
- The scapular Y view provides visualization of the coracoacromial arch and can reveal coracoacromial spurs associated with rotator cuff pathology [75].
- The acromiohumeral distance is normally 7 to 14 mm [75].
- The width of the glenohumeral joint space should be symmetric superiorly and inferiorly [75].
- The coracoclavicular distance is normally 1.1 to 1.3 cm [75].
- CT with three-dimensional reconstructions is the advanced imaging study of choice for determining the extent of glenoid bone loss in the setting of shoulder instability [75].
- CT imaging is frequently used to evaluate fractures of the shoulder, assess for bony lesions in recurrent instability cases, or for preoperative templating for shoulder arthritis [74].
- Standardized plain films are almost always sufficient to garner the information needed for surgical planning, and there is information that can be gathered from properly taken plain films that cannot be obtained from CT scans [43].
- The purpose of imaging of the shoulder is to help establish the diagnosis, determine the severity of the pathoanatomy, assist in surgical planning, and enable the surgeon to illustrate the condition of the shoulder to the patient [43].
- Unless a specific research protocol is in place, the temptation to “overimage” should be resisted, obtaining only the scans or reconstructions that are necessary for the care of the patient [43].
- CT scans may offer a few degrees of increased precision in the measurement of glenoid version, but this precision does not necessarily improve the quality of the surgery or the clinical outcome [43].
- Proper radiographic technique is as important as proper surgical technique to achieve the desired outcome [43].
- The axillary view taken with the arm in the functional position of elevation in the plane of the scapula is referred to as the “truth view” because it demonstrates the glenohumeral relationships in the functional position of elevation [43].
- CT scans have the disadvantage of being taken with the arm in the adducted position, whereas the axillary truth view is taken with the arm elevated [43].
- The standardized axillary view enables the measurement of posterior subluxation or “functional decentering” that is not evident in images taken with the arm at the side [43].
- The degree of posterior subluxation can be measured by the position of the center of the humeral head in relation to the plane of the scapula, the position of the center of the humeral head in relation to the glenoid face, or the point of contact of the humeral articular surface on the glenoid articular surface [43].
- The point of contact of the humeral articular surface on the glenoid articular surface reflects the degree of centering of the net humeral joint reaction force on the glenoid [43].
- Malcentering of the joint reaction force leads to posterior instability, posterior glenoid wear, and “rocking horse” loosening of prosthetic glenoid components [43].
- The recommended series of radiographs for proximal humerus fractures is the Neer trauma series, which consists of an AP view, a lateral view in the scapular plane, and a Velpeau modified axillary view [69].
- The combination of the three views in the Neer trauma series allows evaluation of the shoulder joint in three separate perpendicular planes [69].
- The axillary view is important for evaluating the glenoid articular surface and the relationship of the humeral head anteriorly and posteriorly [69].
- On occasion, other studies, including CT scanning for detailing bony anatomy, may be necessary for proximal humerus fractures [69].
- At least two X-ray views should be obtained for shoulder imaging: an anteroposterior in the plane of the glenoid and an axillary projection with the arm in abduction to show the relationship of the humeral head to the glenoid [67].
- CT is helpful for planning fracture surgery and shoulder joint replacement [67].
Treatment
Non-Operative Management
- Initial treatment of isolated suprascapular neuropathy typically consists of physical therapy, nonsteroidal anti-inflammatory drugs, and activity modification [11].
- Nonoperative treatment for arthroscopic decompression indications should include a period of rest and activity modification, antiinflammatory medication, and a supervised physical therapy program [45].
- The focus of physical therapy is to preserve the normal physiologic range of motion of the shoulder and strengthen the shoulder girdle [45].
- Physical therapy exercises include scapular stabilization and resistive strength straining of the trapezius, rhomboids, and serratus musculature [45].
- When a space-occupying lesion is present or there is visible atrophy of the infraspinatus, the course of nonoperative treatment should be minimal (maximum 3 months) to avoid irreversible damage to the infraspinatus [45].
- Surgical release is not routinely recommended unless patients with pain or deficits in strength fail appropriate nonsurgical treatment [21].
- Martin et al. retrospectively reviewed nonoperative treatment in 15 patients with suprascapular neuropathy, with an average duration of follow-up of more than 3 years [35].
- In the series by Martin et al., five patients had excellent results and seven patients had good results [35].
Operative Management
- The primary indications for arthroscopic decompression of the suprascapular nerve and the spinoglenoid notch are a prolonged course of symptoms and a failed minimum 6-month course of nonoperative treatment [45].
- Arthroscopic release of the suprascapular nerve and transverse ligament is a safe and effective treatment for competitive swimmers with suprascapular neuropathy, allowing return to sport with resolution of pain and improvement in function [86].
- Treatment of choice for suprascapular nerve entrapment at the spinoglenoid notch caused by a ganglion cyst is surgical decompression by complete excision of the ganglion along with its pedicle [17].
- Callahan et al. reported that 21 of 23 patients (91%) were pain-free immediately after resection of the transverse scapular ligament by means of an open superior approach [35].
- In the series by Callahan et al., 17 patients remained pain-free, but 3 required reoperation 2 to 4 years after the initial procedure [35].
- Overall, 20 of the 23 patients (87%) in the series by Callahan et al. had long-term relief of pain and resolution of weakness [35].
- Vastamäki and Göransson reported data on 54 patients with suprascapular neuropathy treated with resection of the suprascapular ligament [35].
- In the series by Vastamäki and Göransson, pain disappeared promptly after the procedure in 24 cases (44%) [35].
- A novel technique for endoscopic release of the transverse scapular ligament resulted in a good outcome with pain resolution, clinical improvement in supraspinatus and infraspinatus atrophy, and an increase in active external rotation range of motion to 80 degrees from 40 degrees at 6 months [39].
- Postoperative rehabilitation for isolated suprascapular nerve palsy at the spinoglenoid notch involves placing patients in a simple sling with immediate initiation of pendulum exercises and passive range of motion [78].
- Patients undergoing isolated suprascapular nerve decompression at the spinoglenoid notch are seen again at 1 week after surgery to assess strength and begin physical therapy consisting of passive range-of-motion and isometric exercises [78].
- If significant infraspinatus atrophy is present, electrical stimulation is used during postoperative rehabilitation [78].
- Resistance and overhead exercises start at 4 to 8 weeks postoperatively in cases of isolated suprascapular nerve decompression at the spinoglenoid notch [78].
Concomitant Pathology and Outcomes
- Combined arthroscopic release of the superior transverse scapular ligament and rotator cuff repair in patients with large/massive rotator cuff tears and suprascapular neuropathy did not produce statistically significant improved outcomes compared with repair of the rotator cuff alone [29].
- It appears that operative injury to the suprascapular nerve during cuff mobilization can occur, but a host of other factors such as inadequate cuff muscle function may be responsible for poor functional outcomes seen following the repair of massive rotator cuff tears [34].
- Tsikouris et al. suggested that outcomes are improved when the nerve is decompressed in overhead athletes with electrodiagnostic evidence of suprascapular neuropathy, though further studies are needed to corroborate these findings with more sensitive outcome measures [36].
Complications
Operative Complications
- Operative injury to the suprascapular nerve can occur during cuff mobilization [24].
- Screw out of vault penetration is correlated with suprascapular nerve injury after reverse total shoulder arthroplasty [6].
- Preoperative suprascapular nerve injuries do not predispose to an acute postoperative lesion [6].
Diagnostic and Clinical Complications
- A large size lipoma at the spinoglenoid notch can mimic a traumatic rotator cuff tear [14].
Pathological Complications
- Suprascapular neuropathy can cause complete neurogenic fatty replacement in patients with intact rotator cuff tendons [5].
Recovery
Non-Operative Management
Operative Management
- Full recovery of the nerve may not be expected in each case following surgical decompression for ganglion cysts at the spinoglenoid notch [17].
- A patient treated with endoscopic release of the transverse scapular ligament demonstrated a good outcome with pain resolution, clinical improvement in supraspinatus and infraspinatus atrophy, and an increase in active external rotation range of motion to 80 degrees from 40 degrees at 6 months [39].
- None of the patients had complications after 8 weeks following treatment for a ganglion of the spinoglenoid notch, and the damage to the nerve resolved completely [99].
- Full recovery of shoulder function was achieved in a case report of suprascapular nerve entrapment caused by a large hematoma of the scapula [44].
Outcomes in Concomitant Rotator Cuff Pathology
Key Evidence
- [L3] The exact association and etiology of suprascapular neuropathy in patients with rotator cuff pathology remain unclear. [1] (10.1016/j.jse.2013.06.011)
- [L4] Entrapment of the suprascapular nerve is frequently overlooked in the differential diagnosis of shoulder pain until profound weakness and denervation atrophy of the spinatus musculature are apparent. [2] (10.1016/s1058-2746(95)80144-8)
- [L4] Shoulder surgeons should consider electrophysiologic evaluation of patients with clinical or radiographic signs of suprascapular neuropathy and be cognizant of the parameters that constitute an abnormal study. [3] (10.1016/j.jse.2010.10.039)
- [L4] Combined injuries of the axillary and the suprascapular nerve cause complete loss of shoulder function. [4] (10.1016/s1058-2746(95)80260-6)
- [L4] This is the first description of suprascapular neuropathy with complete neurogenic fatty replacement in patients with intact rotator cuff tendons in the absence of traction or compression mechanisms. [5] (10.1016/j.arthro.2014.01.010)
- [L1] Preoperative suprascapular nerve injuries do not have a significant clinical impact and do not predispose to an acute postoperative lesion. [6] (10.1016/j.jse.2023.06.026)
- [L4] In this young, active cohort, suprascapular neuropathy presented with one of two distinct primary presenting complaints: pain or weakness. [7] (10.1177/2325967123s00003)
- [L4] Twenty-eight patients with suprascapular nerve entrapment confirmed by electromyographic and nerve conduction studies were identified and treated. [8] (10.1016/1058-2746(93)90062-l)
- [L4] Arthroscopic SSN decompression for suprascapular neuropathy at the suprascapular and/or spinoglenoid notch in the absence of major concomitant glenohumeral pathology results in good functional outcomes with significant improvements from before to after surgery. [9] (10.1016/j.arthro.2020.10.020)
- [L4] In the absence of a well-defined lesion producing mechanical compression of the suprascapular nerve, suprascapular neuropathy should be treated non-operatively. [10] (10.2106/00004623-199708000-00007)
- [L5] Initial treatment of isolated suprascapular neuropathy is typically nonoperative, consisting of physical therapy, nonsteroidal anti-inflammatory drugs, and activity modification; however, open or arthroscopic operative intervention is warranted when there is extrinsic nerve compression or progressive pain and/or weakness. [11] (10.2106/jbjs.i.01743)
- [L4] The authors believe that with practice and meticulous technique, this technique can be mastered and will become the preferred treatment method for suprascapular neuropathy. [12] (10.1097/00132589-200606000-00004)
- [L4] No recommendations regarding suprascapular nerve release in conjunction with rotator cuff repair can be made at this time, and further research is necessary to better delineate the indications in the future. [13] (10.1016/j.jse.2011.11.033)
- [L5] The authors believe that forceful shoulder abduction may have caused the sudden onset of suprascapular neuropathy in the loosely compressed suprascapular nerve by the lipoma. [14] (10.1142/s2424835518720141)
- [L4] A complete history and physical, careful attention to auxiliary tests, and treatment of multiple diagnoses in the same shoulder avoids missed pathologic features and necessity for revision operations. [15] (10.1097/01.blo.0000063791.32430.59)
- [L4] In suprascapular nerve palsy, the upward rotation of the glenoid cavity occurred in the early phase of arm elevation, whereas in axillary nerve palsy it occurred in the late phase. [16] (10.1016/s1058-2746(95)80248-7)
- [L5] Treatment of choice is surgical decompression of the suprascapular nerve by complete excision of the ganglion along with its pedicle, even though full recovery of the nerve may not be expected in each case. [17] (10.1016/s1058-2746(96)80011-5)
- [L3] Decompression of the suprascapular nerve at the spinoglenoid notch did not lead to a better functional outcome compared to repair alone in patients with posterosuperior massive rotator cuff tears and suprascapular neuropathy. [19] (10.1186/s12891-021-04075-1)
- [L4] Release of the spinoglenoid ligament with resultant suprascapular nerve decompression may result in relief of pain and a return of normal shoulder function. [20] (10.1177/03635465990270062101)
- [L5] [21] (10.5435/jaaos-d-19-00526)
- [L4] Chronic rotator cuff tendon tears and suprascapular neuropathy are both associated with fatty infiltration and muscle atrophy of the rotator cuff muscles, but the pattern of fatty infiltration is markedly different in the two situations. [22] (10.1016/j.jse.2013.01.028)
- [L4] It appears that operative injury to the suprascapular nerve during cuff mobilization can occur, but other factors such as inadequate cuff muscle function are more frequently responsible for the poor functional outcomes seen after successful repairs of massive rotator cuff tears. [24] (10.1016/s1058-2746(97)90014-8)
- [L5] Bilateral suprascapular nerve entrapment syndrome associated with rotator cuff tear is a rare condition that can lead to correct early diagnosis through awareness of its clinical presentation. [25] (10.1016/s1058-2746(00)90013-2)
- [L4] Entrapment of the suprascapular nerve usually occurs at the suprascapular or spinoglenoid notch. [27] (10.1016/j.jse.2011.05.022)
- [L5] [28] (10.1016/s0363-5023(82)80015-4)
- [L1] Combined arthroscopic release of the superior transverse scapular ligament and rotator cuff repair in patients with large/massive RCTs and suprascapular neuropathy did not produce statistically significant improved outcomes compared with repair of the rotator cuff alone. [29] (10.1177/03635465211021834)
- [L5] It also demonstrates that shoulder arthroscopy portals placed according to anatomic studies of the suprascapular nerve may still produce nerve injury in the presence of unknown anatomic variants. [30] (10.1067/mse.2000.104093)
- [L5] It also demonstrates that shoulder arthroscopy portals placed according to anatomic studies of the suprascapular nerve may still produce nerve injury in the presence of unknown anatomic variants. [31] (10.1016/s1058-2746(00)90062-4)
- [L5] The inferior transverse scapular ligament was present in 33 shoulders (82.5%). [32] (10.1016/s1058-2746(98)90161-6)
- [L5] This study identifies suprascapular nerve injury as an underlying mechanism leading to compromise of the rotator cuff enthesis structure. [33] (10.1016/j.jse.2019.12.028)
- [L4] It appears that operative injury to the suprascapular nerve during cuff mobilization can occur, but a host of other factors such as inadequate cuff muscle function may be responsible for poor functional outcomes seen following the repair of massive RCTs. [34] (10.1016/s1058-2746(96)80374-0)
- [L5] [35] (10.5435/00124635-199911000-00002)
- [L5] Tsikouris et al. have raised awareness of suprascapular neuropathy and suggested that outcomes are improved when the nerve is decompressed in overhead athletes with electrodiagnostic evidence of suprascapular neuropathy, though further studies are needed to corroborate these findings with more sensitive outcome measures. [36] (10.1016/j.arthro.2018.05.017)
- [L5] The patient demonstrated a good outcome, with pain resolution, clinical improvement in supraspinatus and infraspinatus atrophy, and an increase in active external rotation range of motion to 80 degrees from 40 degrees at 6 months. [39] (10.1097/bte.0000000000000183)
- [L5] The suprascapular nerve is furthest away from the posterior edge of the glenoid with the shoulder at 90 of external rotation. [40] (10.1007/s00167-014-2900-1)
- [Case_report] Full recovery of shoulder function was achieved. [44] (10.1186/s12891-023-06723-0)
- [L4] [45] (10.1016/j.xrrt.2021.04.004)
- [L4] Arthroscopic release of the suprascapular nerve can be performed safely and effectively, with all patients showing improvement in postoperative electromyographic findings and marked improvement in pain relief and function. [48] (10.1016/j.arthro.2006.10.003)
- [L4] [78] (10.1016/j.jse.2013.03.009)
- [L5] [79] (10.1016/j.eats.2024.103051)
- [L5] The unexpected humeral head shift can lead to proprioception disturbance and cause functional instability if the coordinated and conditioned muscles were not functioning very well. [80] (10.1016/s1058-2746(96)80261-8)
- [L5] Secondary to the SGL's attachment to the posterior capsule of the shoulder, as horizontal adduction and internal rotation of the shoulder occurs, tension on the SGL entraps the SSN under it in the lateral corner of the tunnel. [83] (10.1016/s1058-2746(96)80481-2)
- [L4] Arthroscopic release of the suprascapular nerve and transverse ligament is a safe and effective treatment for competitive swimmers with suprascapular neuropathy, allowing return to sport with resolution of pain and improvement in function. [86] (10.1177/0363546513477383)
- [L5] During cross-body adduction and internal rotation of the glenohumeral joint, the interaction of the SGL and the posterior capsule resulted in a tightening of the SGL. [87] (10.1016/s1058-2746(98)90051-9)
- [Paper] In fifty two of sixty shoulders, the suprascapular artery was on the transverse ligament and located on superiolaterally. [88] (10.1016/s1058-2746(96)80257-6)
- [Paper] [89] (10.1002/jor.22482)
- [L4] Regardless of height and sex, the distances from the posterolateral corner of the acromion to the suprascapular and spinoglenoid notches were approximately 43 and 32 mm, respectively. [91] (10.1016/j.jseint.2022.04.002)
- [L4] Anatomical variations at the suprascapular notch, including abnormally oriented subscapularis muscle fibers, anterior coracoscapular ligament, and calcified superior transverse scapular ligament, are predisposing factors for suprascapular nerve entrapment. [92] (10.1007/s00167-003-0378-3)
- [L5] Placement of the superior and posterior screws in the glenoid baseplate during rTSA risks injury to the SSN. [94] (10.1016/j.jse.2020.07.008)
- [L3] Twelve percent of patients who received RTSA were assessed to be at high risk of iatrogenic suprascapular neuropathy by baseplate screw penetration. [95] (10.1016/j.jse.2021.10.024)
- [L5] They recommend high-resolution magnetic resonance imaging to evaluate complex cases of nerve entrapment. [96] (10.1007/s11552-014-9652-8)
- [L5] The suprascapular nerve can be damaged during muscle advancement in two phases: detachment of the supraspinatus muscle from the supraspinatus fossa and excessive tension applied when shifting the muscle laterally. [97] (10.1016/s1058-2746(02)00034-4)
- [L5] Knowledge of the safe zone for avoiding suprascapular nerve injury is important; gender and specific scapular dimensions should be evaluated as they influence the dimensions of the safe zone. [98] (10.1016/j.jse.2011.01.033)
- [L4] None of the patients had complications after 8 weeks, and the damage to the nerve resolved completely. [99] (10.1016/s1058-2746(98)90214-2)
References
[1] Association of suprascapular neuropathy with rotator cuff tendon tears and fatty degeneration. Journal of Shoulder and Elbow Surgery. 2014. DOI: 10.1016/j.jse.2013.06.011
[2] Suprascapular nerve entrapment related to sport. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80144-8
[3] Suprascapular neuropathy in a shoulder referral practice. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2010.10.039
[4] Diagnosis of combined injuries of the axillary and the suprascapular nerve. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80260-6
[5] Complete Fatty Infiltration of Intact Rotator Cuffs Caused by Suprascapular Neuropathy. Arthroscopy. 2014. DOI: 10.1016/j.arthro.2014.01.010
[6] Suprascapular nerve injury after reverse total shoulder arthroplasty: correlation with screw out of vault penetration and functional situation: prospective study. Journal of Shoulder and Elbow Surgery. 2023. DOI: 10.1016/j.jse.2023.06.026
[7] Paper 03: Suprascapular Neuropathy: Two Distinct Presentations and Outcomes of Decompression. Orthopaedic Journal of Sports Medicine. 2023. DOI: 10.1177/2325967123s00003
[8] Suprascapular nerve entrapment: Diagnosis and results of treatment. Journal of Shoulder and Elbow Surgery. 1993. DOI: 10.1016/1058-2746(93)90062-l
[9] Clinical Outcomes of Arthroscopic Suprascapular Nerve Decompression for Suprascapular Neuropathy. Arthroscopy. 2020. DOI: 10.1016/j.arthro.2020.10.020
[10] Suprascapular Neuropathy. Results of Non-Operative Treatment. The Journal of Bone & Joint Surgery*. 1997. DOI: 10.2106/00004623-199708000-00007
[11] Suprascapular Neuropathy. Journal of Bone and Joint Surgery. 2010. DOI: 10.2106/jbjs.i.01743
[12] Suprascapular Nerve Entrapment. Techniques in Shoulder and Elbow Surgery. 2006. DOI: 10.1097/00132589-200606000-00004
[13] Suprascapular neuropathy: what does the literature show?. Journal of Shoulder and Elbow Surgery. 2012. DOI: 10.1016/j.jse.2011.11.033
[14] A Large Size Lipoma at Spinoglenoid Notch Mimicked Traumatic Rotator Cuff Tear. The Journal of Hand Surgery (Asian-Pacific Volume). 2018. DOI: 10.1142/s2424835518720141
[15] Suprascapular Nerve Entrapment Secondary to a Lipoma. Clinical Orthopaedics & Related Research. 2003. DOI: 10.1097/01.blo.0000063791.32430.59
[16] Three-dimensional motion analysis of the shoulder in suprascapular and axiliary nerve palsy. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80248-7
[17] Suprascapular nerve entrapment at the spinoglenoid notch caused by a ganglion cyst. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80011-5
[19] Comparison of clinical outcome of decompression of suprascapular nerve at spinoglenoid notch for patients with posterosuperior massive rotator cuff tears and suprascapular neuropathy. BMC Musculoskeletal Disorders. 2021. DOI: 10.1186/s12891-021-04075-1
[20] Suprascapular Nerve Entrapment at the Spinoglenoid Notch in a Professional Baseball Pitcher. The American Journal of Sports Medicine. 1999. DOI: 10.1177/03635465990270062101
[21] The Evaluation and Management of Suprascapular Neuropathy. Journal of the American Academy of Orthopaedic Surgeons. 2020. DOI: 10.5435/jaaos-d-19-00526
[22] A comparative analysis of fatty infiltration and muscle atrophy in patients with chronic rotator cuff tears and suprascapular neuropathy. Journal of Shoulder and Elbow Surgery. 2013. DOI: 10.1016/j.jse.2013.01.028
[24] The low incidence of suprascapular nerve injury after primary repair of massive rotator cuff tears. Journal of Shoulder and Elbow Surgery. 1997. DOI: 10.1016/s1058-2746(97)90014-8
[25] Bilateral suprascapular nerve entrapment syndrome associated with rotator cuff tear. Journal of Shoulder and Elbow Surgery. 2000. DOI: 10.1016/s1058-2746(00)90013-2
[27] Varicose veins at the spinoglenoidal notch: an unusual cause of suprascapular nerve compression. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2011.05.022
[28] Suprascapular nerve entrapment—Case report. The Journal of Hand Surgery. 1982. DOI: 10.1016/s0363-5023(82)80015-4
[29] Outcomes of Arthroscopic Nerve Release in Patients Treated for Large or Massive Rotator Cuff Tears and Associated Suprascapular Neuropathy: A Prospective, Randomized, Double-Blinded Clinical Trial. The American Journal of Sports Medicine. 2021. DOI: 10.1177/03635465211021834
[30] Suprascapular nerve injury at the spinoglenoid notch after glenoid neck fracture. Journal of Shoulder and Elbow Surgery. 2000. DOI: 10.1067/mse.2000.104093
[31] Suprascapular nerve injury at the spinoglenoid notch after glenoid neck fracture. Journal of Shoulder and Elbow Surgery. 2000. DOI: 10.1016/s1058-2746(00)90062-4
[32] 62 Does inferior transverse scapular ligament play a role in suprascapular nerve entrapment neuropathy? — An anatomical study. Journal of Shoulder and Elbow Surgery. 1998. DOI: 10.1016/s1058-2746(98)90161-6
[33] Effect of suprascapular nerve injury on rotator cuff enthesis. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2019.12.028
[34] Suprascapular nerve injury and cuff re-tear after primary repair of massive rotator cuff tears. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80374-0
[35] Suprascapular Neuropathy. Journal of the American Academy of Orthopaedic Surgeons. 1999. DOI: 10.5435/00124635-199911000-00002
[36] Editorial Commentary: Suprascapular Neuropathy in Overhead Athletes: To Release or Not to Release?. Arthroscopy. 2018. DOI: 10.1016/j.arthro.2018.05.017
[39] A Novel Technique for Endoscopic Release of the Transverse Scapular Ligament in the Setting of Suprascapular Neuropathy: Case Report and Technique. Techniques in Shoulder & Elbow Surgery. 2020. DOI: 10.1097/bte.0000000000000183
[40] The safe zone for avoiding suprascapular nerve injury in bone block procedures for shoulder instability. A cadaveric study. Knee Surgery, Sports Traumatology, Arthroscopy. 2014. DOI: 10.1007/s00167-014-2900-1
[43] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Radiographic Evaluation.
[44] Suprascapular nerve entrapment caused by a large hematoma of the scapula: a case report. BMC Musculoskeletal Disorders. 2023. DOI: 10.1186/s12891-023-06723-0
[45] Endoscopic/arthroscopic decompression of the suprascapular nerve at the spinoglenoid notch: indications and surgical technique. JSES Reviews, Reports, and Techniques. 2021. DOI: 10.1016/j.xrrt.2021.04.004
[48] Arthroscopic Release of Suprascapular Nerve Entrapment at the Suprascapular Notch: Technique and Preliminary Results. Arthroscopy. 2007. DOI: 10.1016/j.arthro.2006.10.003
[53] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Shoulder, Arm, and Elbow > I. Shoulder.
[67] Apley And Solomon S Concise System Of Orthopaedics And Trauma. INVESTIGATION.
[69] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > FRACTURES AND DISLOCATIONS AROUND THE SHOULDER.
[72] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Magnetic Resonance Imaging and Arthrography.
[74] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Shoulder Anatomy and Biomechanics, Clinical Evaluation, Imaging > Clinical Evaluation > Imaging.
[75] Aaos Comprehensive Orthopaedic Review 3. Imaging of the Shoulder and Elbow > I. Shoulder.
[78] Suprascapular nerve entrapment isolated to the spinoglenoid notch: surgical technique and results of open decompression. Journal of Shoulder and Elbow Surgery. 2013. DOI: 10.1016/j.jse.2013.03.009
[79] Open Suprascapular Nerve Decompression at the Spinoglenoid Notch. Arthroscopy Techniques. 2024. DOI: 10.1016/j.eats.2024.103051
[80] Glenohumeal performance after suprascapular nerve entrapment in athletes: A biomechanical study. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80261-8
[83] The spinoglenoid ligament, a cause of suprascapular nerve entrapment?. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80481-2
[86] Suprascapular Neuropathy as a Cause of Swimmer’s Shoulder. The American Journal of Sports Medicine. 2013. DOI: 10.1177/0363546513477383
[87] The spinoglenoid ligament and its relationship to the suprascapular nerve. Journal of Shoulder and Elbow Surgery. 1998. DOI: 10.1016/s1058-2746(98)90051-9
[88] Anatomic variations of transverse ligament and foremen suprascapularis; locations of suprascapular artery, vein and nerve. Journal of Shoulder and Elbow Surgery. 1996. DOI: 10.1016/s1058-2746(96)80257-6
[89] Differential ubiquitin–proteasome and autophagy signaling following rotator cuff tears and suprascapular nerve injury. Journal of Orthopaedic Research. 2013. DOI: 10.1002/jor.22482
[91] An anatomical study for the location of suprascapular and spinoglenoid notches using three-dimensional computed tomography images of scapula. JSES International. 2022. DOI: 10.1016/j.jseint.2022.04.002
[92] Variations in anatomy at the suprascapular notch possibly causing suprascapular nerve entrapment: an anatomical study. Knee Surgery, Sports Traumatology, Arthroscopy. 2003. DOI: 10.1007/s00167-003-0378-3
[94] Risk of suprascapular nerve injury during glenoid baseplate fixation for reverse total shoulder arthroplasty: a cadaveric study. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2020.07.008
[95] Three-dimensional analysis of baseplate screw penetration in reverse total shoulder arthroplasty: risk of iatrogenic suprascapular neuropathy by screw violation. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2021.10.024
[96] Subclavius Posticus: An Anomalous Muscle in Association with Suprascapular Nerve Compression in an Athlete. HAND. 2014. DOI: 10.1007/s11552-014-9652-8
[97] The course of the suprascapular nerve in the supraspinatus fossa and its vulnerability in muscle advancement. Journal of Shoulder and Elbow Surgery. 2003. DOI: 10.1016/s1058-2746(02)00034-4
[98] The safe zone for avoiding suprascapular nerve injury during shoulder arthroscopy: an anatomical study on 500 dry scapulae. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2011.01.033
[99] A ganglion of the spinoglenoid notch. Journal of Shoulder and Elbow Surgery. 1998. DOI: 10.1016/s1058-2746(98)90214-2