Patients › Rehabilitation
Phẫu thuật giải phóng ngón tay cò súng
Post-operative exercises and precautions after trigger finger release, including tendon glides and joint blocking exercises.
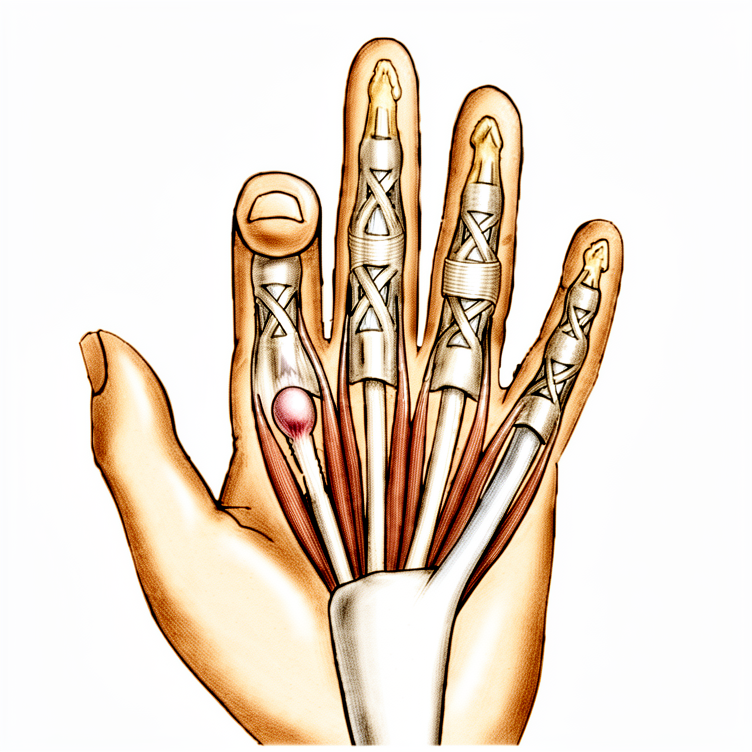
Giao thức này hướng dẫn quá trình hồi phục của bạn sau ca phẫu thuật giải phóng ngón tay cò cứng do Bác sĩ Kieran Hirpara thực hiện tại Bệnh viện tư nhân Mater Rockhampton. Giao thức nêu rõ những điều bạn có thể mong đợi, các biện pháp phòng ngừa cần tuân thủ và chương trình tập luyện hậu phẫu. Vui lòng mang theo trang này hoặc bản PDF tương ứng đến gặp chuyên viên vật lý trị liệu hoặc chuyên gia trị liệu tay để quá trình phục hồi diễn ra một cách đồng bộ.
Nếu bạn có bất kỳ thắc mắc nào về vết thương sau phẫu thuật, hãy liên hệ với phòng khám. Việc chụp ảnh vết thương rồi gửi qua email để được đánh giá cũng là một biện pháp hữu ích.
Những điều bạn có thể mong đợi
Việc chăm sóc vết thương sẽ được hướng dẫn riêng; vui lòng xem trang hướng dẫn chăm sóc vết thương được liên kết ở cuối hướng dẫn này.
Các bài tập dưới đây rất quan trọng nhằm ngăn ngừa tình trạng gân bị dính lại trong quá trình lành vết thương. Sau ca phẫu thuật, các khớp ngón tay đôi khi có thể bị cứng. Việc ngăn ngừa tình trạng này từ sớm là rất cần thiết; vì vậy bạn nên thực hiện các động tác kéo giãn ngón tay một cách mạnh mẽ và kéo dài (bằng tay còn lại), đặc biệt là các động tác duỗi thẳng ngón tay. Hình thức kéo giãn thụ động này hoàn toàn an toàn và không ảnh hưởng đến kết quả phẫu thuật; vì các dây chằng đã được giải phóng trước đó nên không có gì bị ảnh hưởng bởi việc kéo giãn này.
Sau khi vết thương lành hẳn, hãy chườm nóng lên tay trong 20 phút trước khi thực hiện các bài tập. Sau khi tập xong, chườm lạnh có thể giúp giảm viêm.
Đôi khi tay hoặc vết thương có thể trở nên nhạy cảm; điều này là bình thường. Bạn có thể ngăn ngừa hoặc giảm thiểu tình trạng này bằng cách thực hiện các động tác làm giảm độ nhạy cảm hàng ngày: nhẹ nhàng gõ hoặc xoa lên vết thương (khi băng gạc vẫn được dán), ngay sau khi phẫu thuật. Các động tác này giúp da dần thích nghi trở lại với các kích thích xúc giác và kết cấu bề mặt.
Trong 48 giờ đầu, hãy cố gắng giảm sưng: giữ tay ở vị trí cao hơn tim, chườm lạnh, dùng băng ép nếu bác sĩ trị liệu đã hướng dẫn, và nhẹ nhàng co duỗi các ngón tay để giúp dịch thừa lưu thông.
Khi cơn đau cho phép, hãy bắt đầu sử dụng tay để thực hiện các công việc nhẹ nhàng (mặc quần áo, ăn uống, v.v.) và dần dần tăng dần mức độ. Đừng quá sức: nếu cơn đau hoặc sưng tăng lên rõ rệt sau một hoạt động nào đó, hãy giảm bớt mức độ hoạt động cho đến khi tay ổn định trở lại, rồi mới tiếp tục tăng dần.
Khi vết thương đã lành hoàn toàn, hãy bắt đầu mát-xa vùng sẹo: dùng tay xoa tròn mạnh lên vùng vết mổ. Trang hướng dẫn chăm sóc vết thương sẽ cung cấp thêm thông tin về cách quản lý sẹo.
Những gì các bằng chứng khoa học nói về quá trình hồi phục
Phẫu thuật cắt mở rộng vòng xơ A1 là một thủ thuật đã được thiết lập vững chắc, với nhiều kết quả tích cực được ghi nhận trong các tài liệu y khoa. Chính ca phẫu thuật này giúp khắc phục tình trạng dây chằng bị kẹt: sau khi vòng xơ được cắt, gân có thể di chuyển tự do trở lại và tình trạng kẹt gân thường không tái diễn. Trong một nghiên cứu trên gần 1.600 ca phẫu thuật, chỉ dưới 1% bệnh nhân cần phải phẫu thuật lại do tình trạng kẹt gân vẫn tiếp diễn; không có ca nào gặp tổn thương thần kinh hay nhiễm trùng sâu [4]. Một nghiên cứu so sánh kéo dài hơn ba năm cũng cho thấy không có ca nào tái phát sau phẫu thuật cắt mở rộng vòng xơ [5].
Cơn đau ở lòng bàn tay thường giảm đáng kể trong vòng một đến hai tuần đầu sau phẫu thuật. Trong một nghiên cứu so sánh, thời gian trung bình để cơn đau giảm đáng kể sau ca phẫu thuật là khoảng một tuần [5]. Tuy nhiên, cảm giác đau nhức khi nắm chặt, sưng nhẹ hoặc cứng khớp ngón tay có thể còn kéo dài vài tuần sau đó. Điều này là bình thường và phản ánh quá trình hình thành sẹo, vốn mất khoảng ba tháng mới hoàn tất [3]; chương trình xoa dịu cảm giác đau, mát-xa sẹo và tập luyện được đề cập trong hướng dẫn này nhằm hỗ trợ quá trình này. Trong nghiên cứu lớn nói trên, chỉ khoảng 1/20 ngón tay gặp vấn đề sau phẫu thuật; phần lớn là tình trạng cứng khớp tạm thời hoặc đau sẹo, và các triệu chứng này đều thuyên giảm sau điều trị; những người mắc bệnh tiểu đường thường hồi phục vận động chậm hơn, vì vậy chương trình tập luyện càng trở nên quan trọng đối với nhóm này [4].
Các hướng dẫn trị liệu tay hiện hành đều khuyến nghị bắt đầu các bài tập vận động chủ động và thụ động cho ngón tay, cũng như các bài tập trượt gân ngay trong những ngày đầu sau phẫu thuật; sau khi vết thương lành, mới tiến hành các biện pháp quản lý sẹo và giảm nhạy cảm; cuối cùng mới tăng dần cường độ các bài tập nắm chặt [2][3] – đó cũng là cách tiếp cận từng bước được áp dụng trong chương trình tập luyện này. Việc bắt đầu tập sớm giúp gân luôn di chuyển trơn tru và các khớp vẫn giữ được độ linh hoạt trong lúc vết thương hồi phục.
Việc trở lại làm việc phụ thuộc vào tính chất công việc của mỗi người. Trong một nghiên cứu so sánh, một nửa số bệnh nhân đã có thể quay lại làm việc sau khoảng hai tuần kể từ ngày phẫu thuật [5]; những người làm công việc nhẹ nhàng hoặc làm việc văn phòng thường hồi phục nhanh hơn, còn những người phải làm việc nặng thì phải đợi đến khi các hạn chế về nâng vật nặng và nắm chặt được dỡ bỏ.
Một thử nghiệm ngẫu nhiên có đối chứng đã so sánh hiệu quả của ba tháng trị liệu có giám sát sau phẫu thuật với chương trình tập luyện tại nhà do bệnh nhân tự thực hiện: sau sáu tháng, chức năng tay, khả năng vận động và mức độ đau giữa hai nhóm là tương đương nhau; tuy nhiên sức mạnh nắm chặt được cải thiện rõ rệt hơn ở nhóm được trị liệu có giám sát. Những bệnh nhân hưởng lợi nhiều nhất từ trị liệu chuyên sâu là những người đã bị tình trạng kẹt gân kéo dài hơn mười hai tháng trước phẫu thuật, hoặc những người phải làm việc nhà hoặc công việc nhẹ [1]. Trên thực tế, nếu thực hiện đúng chương trình tập luyện tại nhà (như hướng dẫn ở đây), phần lớn bệnh nhân đều hồi phục tốt; trị liệu tay chuyên sâu chỉ thực sự cần thiết trong trường hợp ngón tay bị cứng lâu ngày trước phẫu thuật hoặc tiến triển hồi phục chậm.
Các biện pháp phòng ngừa và hạn chế
Bạn nên sử dụng bàn tay một cách nhẹ nhàng cho các hoạt động sinh hoạt hàng ngày như chăm sóc bản thân, ăn uống, mặc quần áo, viết lách và đánh máy. Các hạn chế cần tuân thủ như sau:
- Trong vòng 4 tuần sau phẫu thuật, không được nâng vật nặng, nắm chặt hay chịu lực lên bàn tay.
- Trong tuần đầu sau phẫu thuật, không nên lái xe; chỉ được tiếp tục lái khi cơn đau giảm, bạn có thể nắm tay thành nắm đấm hoàn chỉnh và kiểm soát phương tiện một cách an toàn.
Dành cho chuyên viên vật lý trị liệu của bạn:
Cách xử lý
- Thực hiện chương trình tập luyện tại nhà theo các hướng dẫn dưới đây: các bài giãn cổ tay (gập/giãn cổ tay); các bài tập khóa khớp DIP (khớp ngón tay xa) và PIP (khớp ngón tay gần); các bài trượt gân (Bộ A và B).
- Thực hiện các bài giãn thụ động mạnh và kéo dài cho các ngón tay, đặc biệt là hướng duỗi ngón, nhằm phòng ngừa cứng khớp từ sớm.
- Sau khi vết thương lành, hãy chườm nóng lên bàn tay trong 20 phút trước khi tập; sau khi tập thì chườm lạnh để ngăn ngừa viêm.
- Ngay sau phẫu thuật, hãy tiến hành các bài mát-xa giảm nhạy cảm hàng ngày (gõ nhẹ hoặc xoa nhẹ lên vết thương, trên băng gạc đang dán).
- Trong 48 giờ đầu sau phẫu thuật, kiểm soát sưng bằng cách nâng cao bàn tay, chườm lạnh, băng ép theo chỉ định và các bài vận động nhẹ cho các ngón tay.
- Dần dần khôi phục việc sử dụng bàn tay một cách nhẹ nhàng khi cơn đau cho phép; theo dõi xem có đau hoặc sưng tái phát sau khi vận động hay không.
- Khi vết thương đã lành hoàn toàn, hãy thực hiện mát-xa sẹo (xoa tròn mạnh lên vết mổ).
Các biện pháp phòng ngừa
- Chỉ được sử dụng bàn tay một cách nhẹ nhàng cho các hoạt động sinh hoạt hàng ngày (chăm sóc bản thân, ăn uống, mặc quần áo, viết lách, đánh máy).
- Trong vòng 4 tuần sau phẫu thuật, không được nâng vật nặng, nắm chặt hay chịu lực lên bàn tay.
- Trong tuần đầu sau phẫu thuật, không nên lái xe; chỉ được tiếp tục lái khi cơn đau giảm, bạn có thể nắm tay thành nắm đấm hoàn chỉnh và kiểm soát phương tiện một cách an toàn.
Các mốc tiến triển dự kiến (dựa trên tiêu chí và các hướng dẫn lâm sàng đã công bố [1][2][3])
- Trong vòng 1–2 tuần [5], cơn đau giảm xuống mức chịu đựng được nhờ dùng thuốc giảm đau đơn giản.
- Đến 2–3 tuần [2][3], vết thương lành hẳn; bạn đã thực hiện mát-xa sẹo và các bài mát-xa giảm nhạy cảm đều đặn.
- Khoảng 3 tuần sau phẫu thuật, bạn có thể gập và duỗi các ngón tay hoàn toàn (nắm tay thành nắm đấm và duỗi thẳng tay hoàn chỉnh); các bài tập khóa khớp và trượt gân giúp duy trì khả năng này [2].
- Sau khi hết thời hạn 4 tuần hạn chế nâng/nắm, bắt đầu tăng dần sức mạnh nắm và kẹp ngón tay (ví dụ: dùng đất nặn); dần dần trở lại sử dụng bàn tay cho các hoạt động bình thường.
- Nếu trước phẫu thuật bạn đã bị co cứng bàn tay kéo dài hơn 12 tháng, hoặc công việc đòi hỏi phải dùng tay liên tục với các thao tác tinh tế, hoặc nếu phạm vi vận động/khả năng nắm tay hồi phục chậm, nên cân nhắc tham gia các liệu trình trị liệu bàn tay có giám sát [1].
Đây là các bài tập được ghi trong tờ hướng dẫn dành cho bạn; hãy thực hiện chúng tại nhà theo chỉ dẫn của chuyên viên vật lý trị liệu hoặc chuyên gia trị liệu bàn tay.
Các bài tập của bạn

Kieran Hirpara 4.0
Bài tập kéo giãn cổ tay: gập và duỗi cổ tay
Đặt khuỷu tay lên bàn (hoặc đặt cẳng tay lên mép bàn hoặc tay vịn ghế) rồi nhẹ nhàng đung đưa cổ tay qua lại. Khi đã cảm thấy thoải mái hơn, dùng tay kia nắm lấy lòng bàn tay và đẩy cổ tay ra phía sau (các ngón tay thả lỏng, hướng lên trần nhà) – giữ nguyên tư thế trong 15 giây; sau đó làm ngược lại (các ngón tay thả lỏng, hướng xuống sàn nhà) – giữ nguyên tư thế trong 15 giây. Lặp lại mỗi hướng 5 lần.
10 lần lặp, 4–5 lần mỗi ngày.
Kieran Hirpara 4.0
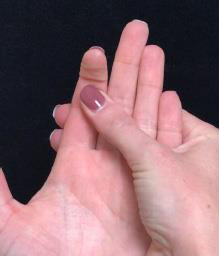
Chặn khớp ngón tay xa
Khớp DIP (khớp liên đốt ngón tay xa) là khớp nằm ở đầu ngón tay. Bắt đầu bằng cách đặt lòng bàn tay hướng lên trên; dùng tay kia nâng đỡ bàn tay đang tập ngay dưới khớp đầu ngón tay. Gập và duỗi thẳng khớp đầu ngón tay, giữ mỗi tư thế trong 3–5 giây. Chỉ cần nâng đỡ khớp giữa ngón tay vừa đủ để nó không bị gập lại. Việc các ngón tay khác di chuyển trong quá trình tập cũng không sao cả.
10 lần lặp lại, 4 lần mỗi ngày, thực hiện hàng ngày.
Kieran Hirpara 4.0
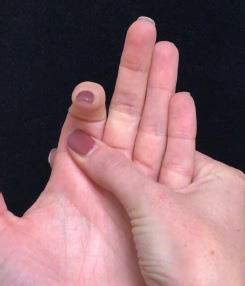
Chặn khớp PIP
Khớp PIP (khớp liên đốt gần) là khớp nằm ở giữa ngón tay. Bắt đầu bằng cách đặt lòng bàn tay hướng lên trên; dùng tay kia nâng đỡ bàn tay đang tập ngay phía dưới khớp thứ hai. Gập và duỗi thẳng ngón tay tại khớp giữa, giữ mỗi tư thế trong 3–5 giây. Việc các ngón tay khác cũng di chuyển là hoàn toàn bình thường.
10 lần lặp, 4 lần mỗi ngày, thực hiện hàng ngày.
Kieran Hirpara 4.0
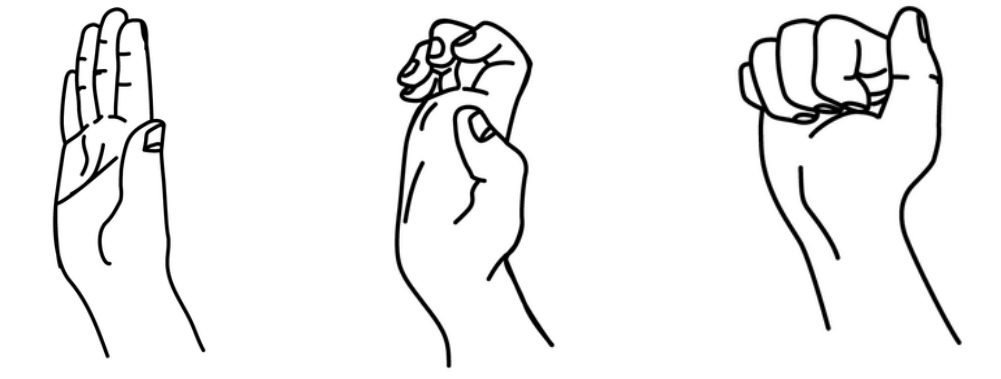
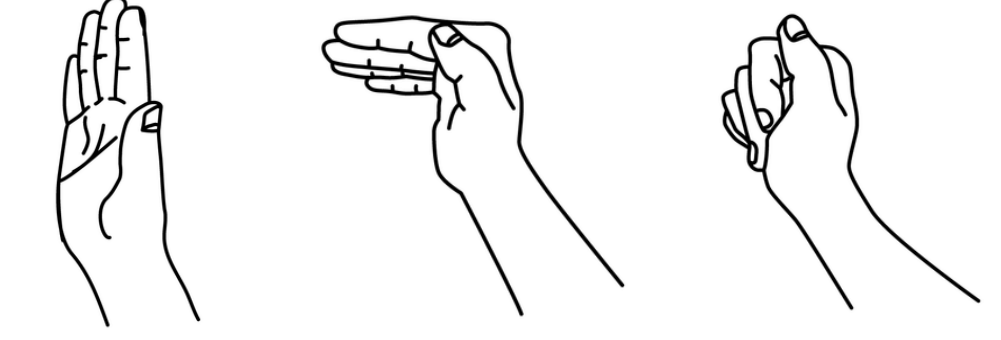
Các bài tập trượt gân — Loạt A
Hãy đặt tay ra trước mặt, giữ cổ tay thẳng; sau đó duỗi thẳng hết các ngón tay — bạn có thể dùng tay kia để đảm bảo các ngón tay được duỗi thẳng hoàn toàn (tư thế 1). Tiếp theo, gập đầu ngón tay lại thành tư thế “móc”, sao cho các khớp ngón hướng lên trên (tư thế 2). Cuối cùng, nắm chặt tay thành nắm đấm, đồng thời đặt ngón tay cái lên trên các ngón còn lại (tư thế 3).
5–10 lần lặp, 2–3 lần mỗi ngày, thực hiện hàng ngày.
Kieran Hirpara 4.0
Các bài tập trượt gân — Loạt B
Hãy đặt tay ra phía trước, giữ cổ tay thẳng; sau đó duỗi thẳng hết các ngón tay — bạn có thể dùng tay kia để đảm bảo các ngón tay được duỗi thẳng hoàn toàn (tư thế 1). Tiếp theo, hãy gập các ngón tay ở khớp gốc ngón tay sao cho tạo thành hình “mặt bàn” trong khi vẫn giữ các ngón thẳng; chú ý không để cổ tay gập về phía trước (tư thế 2). Cuối cùng, gập các ngón tay ở khớp giữa, sao cho đầu ngón tay chạm vào lòng bàn tay (tư thế 3).
5–10 lần lặp, 2–3 lần mỗi ngày, thực hiện hàng ngày.
Kieran Hirpara 4.0
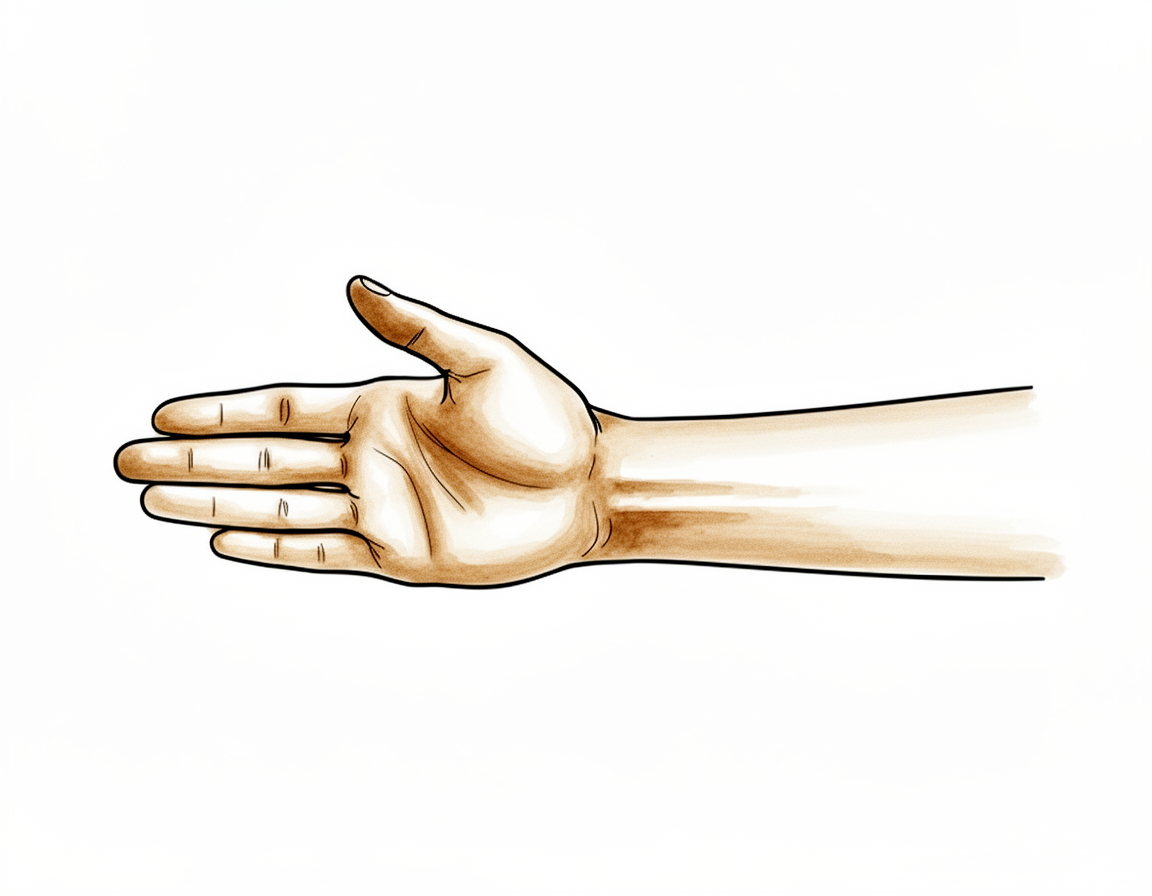
Duỗi phối hợp chủ động
Đặt khuỷu tay lên bàn, duỗi các ngón tay ra hết mức có thể, sau đó dùng tay kia ấn thêm một chút nữa. Đếm đến 5 rồi thả lỏng.
10 lần lặp, 3–4 lần mỗi ngày.
Kieran Hirpara 4.0
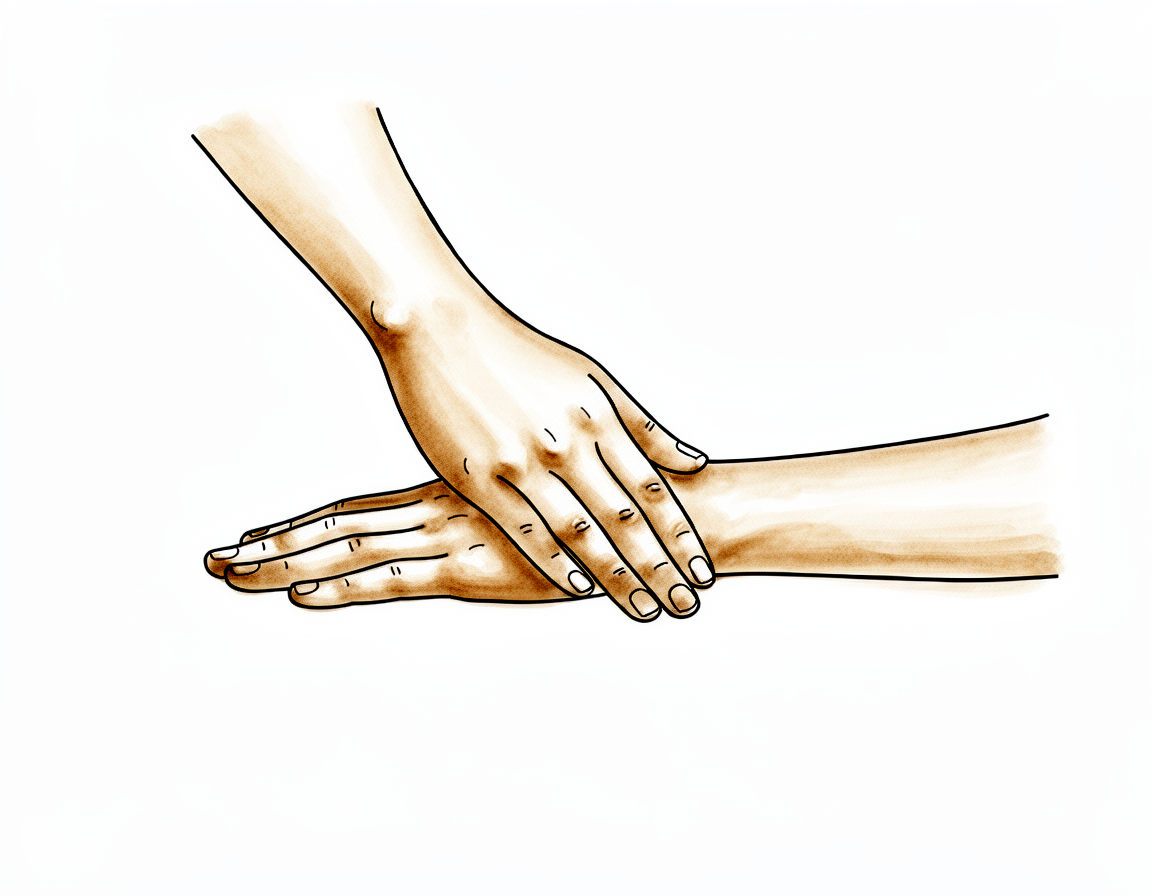
Duỗi phối hợp thụ động
Đặt bàn tay phẳng lên bàn, lòng bàn tay hướng xuống dưới. Dùng tay còn lại ấn nhẹ lên mu bàn tay và “xoa bóp” theo hướng về phía cơ thể. Đếm đến 5 rồi thả lỏng.
10 lần lặp, 3–4 lần mỗi ngày.
Kieran Hirpara 4.0
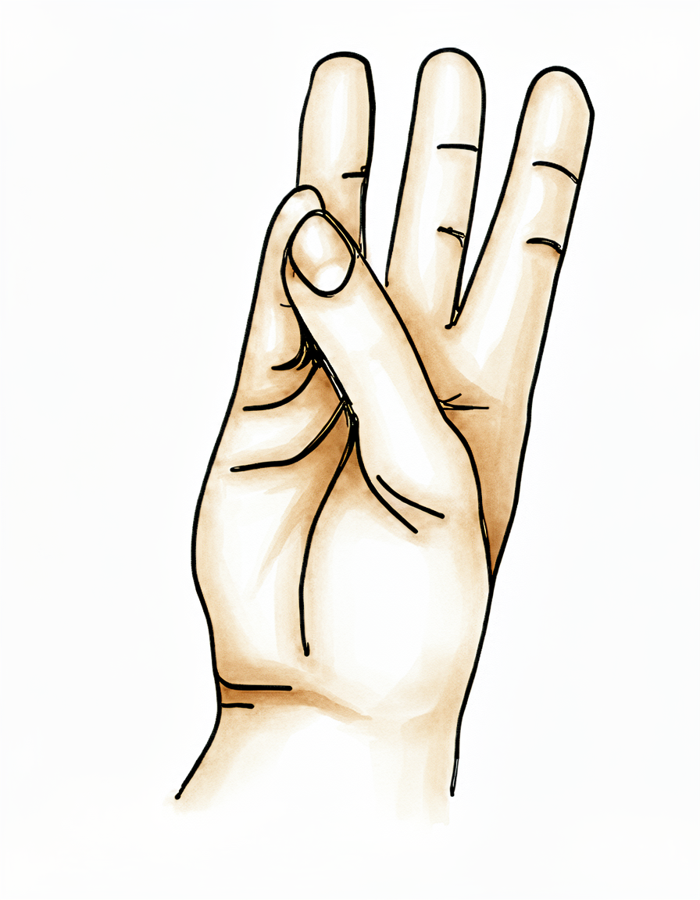
Đối chiếu ngón cái
Hãy bắt đầu với các ngón tay duỗi thẳng và thả lỏng. Chạm đầu ngón tay cái vào đầu ngón trỏ. Giữ nguyên tư thế trong 5 giây, sau đó trở về vị trí ban đầu.
10 lần lặp, 3–4 lần mỗi ngày.
Hãy thực hiện các bài tập dưới đây chỉ khi có sự hướng dẫn từ Bác sĩ Hirpara và chuyên viên trị liệu vận động, đồng thời tuân thủ mọi phạm vi chuyển động và giới hạn đã được chỉ định. Các bài tập trượt gân và các bài tập chặn giúp gân vừa được phục hồi di chuyển trơn tru trong bao gân, tránh tình trạng dính vào mô sẹo đang lành — điều này giúp ngăn ngừa sự tái phát của tình trạng cứng khớp. Các bài tập duỗi thẳng chủ động và thụ động giúp ngón tay duỗi thẳng hoàn toàn; bài tập đối kháng của ngón cái giúp phục hồi khả năng nắm kẹp; bài tập giãn cổ tay giúp ngăn ngừa tình trạng cổ tay cứng lại trong lúc các ngón tay đang được tập luyện. Trong vài tuần đầu, việc cảm thấy đau nhức ngay tại vùng sẹo ở lòng bàn tay là hiện tượng bình thường. Hãy ngừng ngay các bài tập gây ra cơn đau dữ dội.
Sau khi thực hiện theo quy trình
Quy trình này được soạn thảo với sự hợp tác của Sarah Farrell, cử nhân Vật lý trị liệu, chuyên gia trị liệu tay được công nhận; đồng thời tích hợp các hướng dẫn quản lý hậu phẫu mới nhất (tháng 4 năm 2025) từ Ruby Doolan, chuyên gia trị liệu tay được công nhận tại Extend Rehabilitation. Quy trình này bổ sung cho các lời khuyên phục hồi chung của phòng khám: vui lòng tham khảo mục cách kiểm soát cơn đau sau phẫu thuật, chăm sóc vết thương và những điều cơ bản về trị liệu tay. Đối với nội dung liên quan đến ca phẫu thuật, xem mục thủ thuật cắt bỏ gân hạt ngô.
Các mốc thời gian và cách tiếp cận phục hồi cũng được xây dựng dựa trên các quy trình trị liệu sau phẫu thuật cắt bỏ gân hạt ngô đã được công bố, bao gồm cả những quy trình từ Trung tâm Chuyên khoa Tay thuộc Đại học Virginia và Twin Cities Orthopedics; đồng thời dựa trên các nghiên cứu về kết quả điều trị sau phẫu thuật, như thử nghiệm ngẫu nhiên có đối chứng về phục hồi sau phẫu thuật (Saito và cộng sự, Journal of Clinical Medicine, 2023) và nghiên cứu quy mô lớn về các biến chứng có thể xảy ra (Bruijnzeel và cộng sự, Journal of Hand Surgery, 2012).
Tài liệu tham khảo
[1] Saito T, Nakamichi R, Nakahara R, Nishida K, Ozaki T. Hiệu quả của phục hồi chức năng sau phẫu thuật giải phóng mở đối với chứng ngón tay cò: một nghiên cứu tiền cứu, ngẫu nhiên và có đối chứng. J Clin Med. 2023;12(22):7187. https://pmc.ncbi.nlm.nih.gov/articles/PMC10671987/ [2] Trung tâm Phẫu thuật Bàn tay thuộc Đại học Virginia. Hướng dẫn phẫu thuật giải phóng ngón tay cò (quy trình trị liệu sau phẫu thuật). https://med.virginia.edu/orthopaedic-surgery/wp-content/uploads/sites/242/2015/11/Triggerfingerreleaseprotocol.pdf [3] Meletiou SD, Twin Cities Orthopedics. Cách quản lý sau phẫu thuật đối với ca giải phóng ngón tay cò (giải phóng dây chằng A1). https://tcomn.com/wp-content/uploads/2017/10/Trigger-Release-A1.pdf [4] Bruijnzeel H, Neuhaus V, Fostvedt S, Jupiter JB, Mudgal CS, Ring DC. Các biến chứng có thể xảy ra sau phẫu thuật giải phóng dây chằng A1 mở đối với chứng ngón tay cò nguyên phát. J Hand Surg Am. 2012;37(8):1650–1656. https://pubmed.ncbi.nlm.nih.gov/22763058/ [5] Chanthanapodi P, Aodsup S. Kết quả so sánh giữa phương pháp phẫu thuật xuyên da và phẫu thuật mở đối với chứng ngón tay cò: phân tích dựa trên điểm số khuynh hướng. Front Surg. 2025;12:1509292. https://pmc.ncbi.nlm.nih.gov/articles/PMC11922895/
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Trigger Finger Release (A1 Pulley Release) — Surgical Outcomes & Post-operative Rehabilitation
Topic scope: (A) the place of surgery in stenosing tenosynovitis (trigger finger/thumb) after failed conservative care (splinting, corticosteroid injection), and (B) post-operative rehabilitation after surgical division of the A1 pulley — open or percutaneous. This is an early-motion pathway: nothing is reconstructed, the catching is mechanically abolished the moment the pulley is divided, and the rehab exists to keep the now-free tendon gliding and the finger joints supple while the wound heals.
Defining principle of the rehab here: A1 pulley release removes the obstruction; it does not create a construct that needs protecting. Once the pulley is divided the flexor tendon glides freely and triggering does not usually recur. So — unlike a tendon repair, and like a carpal-tunnel decompression — the pathway is immediate active motion: full active finger flexion/extension and tendon glides from the first days, oedema and scar care, early light functional use, and a quick return. Most patients need no formal hand therapy at all; supervised therapy is reserved for the minority with pre-existing joint stiffness, long-standing triggering, or slow recovery. The single branch point is whether the finger was already stiff before surgery (long-standing fixed flexion / PIP contracture) — those patients need active therapy to recover motion the release alone cannot restore.
A. WHERE SURGERY SITS IN THE PATHWAY
Trigger finger is usually managed non-operatively first: activity modification, splinting, and corticosteroid injection, which resolves a substantial proportion of digits without surgery. Surgery (A1 pulley release) is reserved for digits that fail injection, recur, or present with a fixed deformity. The corpus contains the comparative evidence underpinning this stepped approach (percutaneous release vs steroid injection; one- vs two-injection regimens; corticosteroid solution choice) — Moderate (RCT). The rehab protocol on the patient page begins after that decision has been made, so this brief concentrates on the surgical and post-surgical evidence.
B. SURGICAL OUTCOMES & RESOLUTION RATES
Open release of the A1 pulley is one of the most reliable operations in hand surgery. The mechanical problem — a thickened tendon catching under a tight pulley — is solved by dividing the pulley, and the result is durable:
- In a series of 1,598 open releases, fewer than 1% required a second operation for persistent or recurrent triggering, with no nerve injuries and no deep infections [Bruijnzeel 2012]. About one digit in twenty had a documented post-operative problem, almost all minor and self-limiting (transient stiffness, scar tenderness). Strong (large cohort).
- Recovery of motion is slower in patients with diabetes, reinforcing the value of the exercise program in that group [Bruijnzeel 2012]. Moderate.
- A propensity-matched comparison with >3 years follow-up found no recurrences after open release, with median time to significant pain reduction of about one week and roughly half of patients back at work within ~2 weeks [Chanthanapodi 2025]. Moderate.
Take-home for rehab: because the operation itself abolishes the triggering, the rehabilitation is not "earning back" a surgical result — it is preventing the two things that can go wrong during healing: tendon adhesion and joint stiffness. Early glide and early extension are the levers.
C. OPEN vs PERCUTANEOUS RELEASE
Both techniques divide the same structure and converge to the same place.
- A Level I meta-analysis of 8 RCTs (548 patients) found no significant difference between open and percutaneous release in revision, complication, or pain rates — both are appropriate options [Casey 2024, J Hand Surg Am]. Strong (meta-analysis of RCTs).
- Larger RCT syntheses show percutaneous release confers faster early functional recovery — better short/mid-term Q-DASH, ~12 days earlier return to work, and shorter analgesic use — while long-term function, grip, motion and complication/revision rates are equivalent. Strong.
- Percutaneous (including ultrasound-guided/sonographically-controlled) technique is supported by multiple corpus series for efficacy and safety, with the main theoretical risks being incomplete release and digital nerve proximity, mitigated by surface landmarks and imaging [corpus percutaneous series]. Moderate.
Rehab implication: the post-operative program is essentially the same for both approaches — early active motion, glides, oedema and scar care. The patient page applies regardless of whether the release was open or percutaneous; percutaneous patients simply tend to be comfortable and back to activity a little sooner.
D. THE ROLE — AND LIMITS — OF POST-OPERATIVE HAND THERAPY
This is the central evidence point for the protocol, and it is one where "more therapy" is not automatically better.
- A prospective RCT compared 3 months of supervised rehabilitation after open
release against a self-directed home exercise program: at six months,
overall function, motion and pain were similar between groups. Supervised
therapy added further grip-strength recovery, and the patients who clearly
benefited from formal therapy were those whose **triggering had been present
12 months pre-operatively and those in housework/lighter-work roles [Saito 2023, J Clin Med]. Moderate (single RCT).
- Published surgeon and hand-therapy protocols (e.g. University of Virginia Hand Center; Twin Cities Orthopedics) start active and passive finger motion and tendon glides within the first days, add scar massage and desensitisation once the wound is healed, and reintroduce graded grip strengthening later — precisely the staged structure of the patient page. Consensus.
Bottom line: a well-performed home program carries most patients through. Formal hand therapy is reserved, not routine — escalate it for long-standing pre-operative triggering, pre-existing joint stiffness/contracture, manual or fine-use occupational demands, or slow motion/grip recovery.
E. COMPLICATIONS
Serious complications are uncommon (roughly <1–4% across series) and most "complications" are minor, self-limiting healing phenomena:
- Digital nerve injury — the most feared complication, particularly relevant to percutaneous technique (blind division near the radial digital nerve of the thumb and index) and to scar/retraction in open release. Rare in experienced hands; transient paraesthesia is more common than true division [corpus complication series]. Moderate.
- Incomplete release / persistent triggering — failure to fully divide the A1 pulley (or an A2/FDS slip contribution); a recognised cause of revision, more often discussed with percutaneous technique. Moderate.
- Recurrent triggering — uncommon after adequate open release (<1% reoperation in the 1,598-digit series) [Bruijnzeel 2012]. Strong.
- Infection — usually superficial; deep infection rare (none in the large open series) [Bruijnzeel 2012]. Strong.
- Bowstringing — a rare complication from excessive proximal pulley loss (A1 plus encroachment on A2); largely avoided by limiting division to A1 [bowstringing case literature]. Weak (case-level).
- Stiffness / flexion contracture / "flare" — the commonest self-limiting problem; transient PIP stiffness, scar tenderness and a post-operative inflammatory flare that settle with the motion, desensitisation and scar program. Recovery is slower in diabetes. Moderate. This is the category the rehabilitation program actively targets.
F. PHASED POST-OP TIMELINE (matches the patient protocol)
| Phase | Window | Protection | Motion / use | Therapy add-ons | Notes |
|---|---|---|---|---|---|
| I — Immediate active motion & oedema control | Day 0–2 | None beyond dressing | Active finger flexion/extension and finger "pumps" from day 1; tendon glides commenced | Elevation, ice, compression if provided; desensitisation (tap/rub over dressed wound) from day 1 | Nothing reconstructed -> motion is the priority; manage swelling actively |
| II — Glide & joint motion | Week 0–2 | None | Tendon glides (Series A/B), DIP & PIP blocking, composite extension; firm passive stretch into extension | Continue desensitisation | Goal: keep tendon gliding, prevent adhesion & stiffness; pain settles substantially (~1 wk) [Chanthanapodi 2025] |
| III — Scar maturation & function | Week 2–4 | Light functional use only | Full active fist + full composite extension by ~3 wk; build light daily-living use | Scar massage (firm circles) once wound healed; heat before / ice after exercises | No lifting/gripping/weight-bearing to ~4 wk; driving limited ~first week (full fist + safe control) |
| IV — Strengthening & return | Week 4+ | None | Graded grip/pinch (e.g. putty) once 4-wk precaution lifts -> full function | Supervised therapy if indicated (long-standing trigger, stiffness, slow recovery, occupational demand) [Saito 2023] | Manual workers return later than desk/light roles |
Timings are criteria-based and drawn from published surgeon/hand-therapy protocols; they are typical, not trial-mandated.
G. KEY CONTROVERSIES / EVIDENCE QUALITY
- Is routine post-op hand therapy necessary? The best available evidence (Saito 2023 RCT) says no for most — home exercise matches supervised therapy on function/pain/motion at six months, with supervised therapy adding grip strength and benefiting a defined subgroup (long-standing trigger, lighter-work roles). The protocol's "therapy reserved, not routine" stance is evidence-aligned. Moderate.
- Open vs percutaneous. Equivalent long-term outcomes and safety (Casey 2024 meta-analysis); percutaneous offers faster early recovery. The rehab is the same either way. The live debate is technique-side (nerve safety, completeness of release), not rehab-side. Strong on equivalence.
- The rehab protocol structure itself is consensus/expert, built from surgeon patient-guidance documents plus one rehabilitation RCT — there is no large trial dictating exact phase timings.
- Diabetes modifies recovery — slower motion recovery and a lower threshold to involve a hand therapist; not a different protocol, a different pace. Moderate.
H. EVIDENCE STRENGTH FLAGS (summary)
- STRONG (meta-analysis / RCTs / large cohort): open vs percutaneous equivalence in revision/complication/pain (Casey 2024, 8 RCTs); percutaneous faster early functional recovery (RCT syntheses); durability of open release (<1% reoperation, no nerve injury/deep infection in 1,598 digits, Bruijnzeel 2012).
- MODERATE (single RCT / cohorts): home exercise ~ supervised therapy at 6 months with grip-strength edge for supervised therapy (Saito 2023); percutaneous efficacy/safety series; slower recovery in diabetes; injection-vs- surgery comparative data.
- WEAK / CONSENSUS: the post-operative rehabilitation protocol structure and exact phase timings (surgeon/hand-therapy patient-guidance documents); bowstringing risk (case-level).
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Open Versus Percutaneous Fixation of Trigger Finger: Meta-Analysis of Clinical Outcomes. J Hand Surg Am. 2024. DOI: 10.1016/j.jhsa.2024.03.010
- Complications of Open Trigger Finger Release. J Hand Surg Am. 2010. DOI: 10.1016/j.jhsa.2009.12.040
- Differential Pulley Release in Trigger Finger: A Prospective, Randomized Clinical Trial. Hand (N Y). 2021. DOI: 10.1177/1558944721994231
- Percutaneous A1 pulley release vs steroid injection for trigger digit. J Hand Surg Eur. 2010. DOI: 10.1177/1753193410381824
- Comparative Study of A1 Pulley Release and Ulnar Superficialis Slip Resection in Trigger Finger. J Hand Surg Am. 2022. DOI: 10.1016/j.jhsa.2022.04.021
- Risk Factors for Requiring Ulnar Superficialis Slip Resection During Trigger Finger Release. J Hand Surg Am. 2024. DOI: 10.1016/j.jhsa.2024.08.013
- Impact of Flexor Tendon Traction Tenolysis on Clinical Outcomes in Open A1 Pulley Release. J Hand Surg Glob Online. 2024. DOI: 10.1016/j.jhsg.2024.09.010
- Ultrasound-Assisted Percutaneous Trigger Finger Release: Is It Safe? Hand (N Y). 2008. DOI: 10.1007/s11552-008-9137-8
- Evaluation of Percutaneous First Annular Pulley Release: Efficacy and Complications. J Hand Surg Am. 2016. DOI: 10.1016/j.jhsa.2016.04.009
- Sonographically controlled minimally-invasive A1 pulley release using a new guide. BMC Musculoskelet Disord. 2023. DOI: 10.1186/s12891-023-06982-x
- Percutaneous A1 pulley with corticosteroid injection for trigger finger release. J Orthop Surg Res. 2025. DOI: 10.1186/s13018-025-05776-2
- A Cost and Efficiency Analysis of the WALANT Technique for the Management of Trigger Finger. Plast Reconstr Surg Glob Open. 2019. DOI: 10.1097/gox.0000000000002509
- Management of Pediatric Trigger Thumb and Trigger Finger. J Am Acad Orthop Surg. 2012. DOI: 10.5435/jaaos-20-04-206
- What's New in Hand Surgery. J Bone Joint Surg Am. 2024. DOI: 10.2106/jbjs.23.01343
Trigger finger surgical & rehabilitation literature (URLs)
- Saito T, et al. The Effectiveness of Rehabilitation after Open Surgical Release for Trigger Finger: A Prospective, Randomized, Controlled Study. J Clin Med. 2023;12(22):7187. https://pmc.ncbi.nlm.nih.gov/articles/PMC10671987/
- Bruijnzeel H, et al. Adverse Events of Open A1 Pulley Release for Idiopathic Trigger Finger. J Hand Surg Am. 2012;37(8):1650-1656. https://pubmed.ncbi.nlm.nih.gov/22763058/
- Casey JC, et al. Open Versus Percutaneous Fixation of Trigger Finger: Meta-Analysis of Clinical Outcomes. J Hand Surg Am. 2024;49(6):570-575. https://pubmed.ncbi.nlm.nih.gov/38727666/
- Chanthanapodi P, Aodsup S. Comparative results of percutaneous and open surgery for trigger fingers: a propensity score analysis. Front Surg. 2025;12:1509292. https://pmc.ncbi.nlm.nih.gov/articles/PMC11922895/
- Complications of Percutaneous Release of the Trigger Finger. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC6485534/
- Trigger Finger. StatPearls, NCBI Bookshelf. https://www.ncbi.nlm.nih.gov/books/NBK459310/
- Bowstringing as a complication of trigger finger release. J Hand Surg Am. 1988. https://www.jhandsurg.org/article/S0363-5023(88)80097-2/abstract
- Trigger Finger (patient information). British Society for Surgery of the Hand (BSSH). https://www.bssh.ac.uk/patients/conditions/15/trigger_finger
Published rehab protocols (patient-guidance — basis for the phase structure)
- University of Virginia Hand Center. Trigger Finger Release Guidelines (post-operative therapy protocol). https://med.virginia.edu/orthopaedic-surgery/wp-content/uploads/sites/242/2015/11/Triggerfingerreleaseprotocol.pdf
- Meletiou SD, Twin Cities Orthopedics. Post-operative Management of Trigger Release (A1 pulley release). https://tcomn.com/wp-content/uploads/2017/10/Trigger-Release-A1.pdf
- EmergeOrtho. Trigger Finger Release - Post-operative Instructions. https://emergeortho.com/wp-content/uploads/2022/06/Trigger-Finger-Release.pdf