Lý do phẫu thuật này được đề xuất
Bác sĩ Kieran Hirpara, bác sĩ phẫu thuật chi trên tại Bệnh viện tư nhân Mater Rockhampton, sẽ bắt đầu bằng các phương pháp điều trị ít xâm lấn nhất phù hợp với tình trạng của bạn. Thông thường, bệnh nhân được bác sĩ đa khoa giới thiệu đến phòng khám chúng tôi; nếu vật lý trị liệu viên khuyên bạn nên đến gặp chúng tôi, bạn vẫn cần có giấy giới thiệu từ bác sĩ đa khoa để được hưởng mức hoàn trả từ chương trình Medicare. Trong buổi hẹn khám, chúng tôi sẽ hỏi bệnh sử, khám tay và chỉ định chụp hình ảnh nếu cần để xác nhận chẩn đoán.
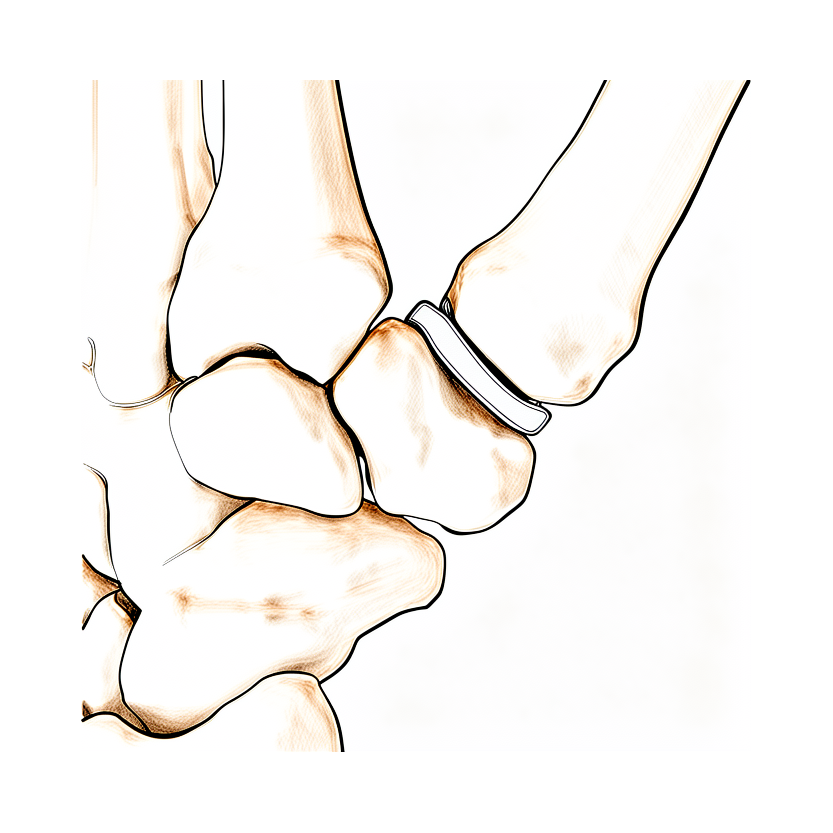
Phẫu thuật này thay thế bề mặt bị mòn của một khớp nhỏ bằng một miếng carbon trơn nhẵn, được tạo hình sẵn. Phẫu thuật thường được đề nghị cho tình trạng viêm khớp lâu năm không thuyên giảm khi đã thay đổi hoạt động, trị liệu bàn tay hoặc đeo nẹp. Chúng tôi thường thử điều trị không phẫu thuật trước và cân nhắc phẫu thuật khi cách đó không mang lại đủ cải thiện. Với một số vấn đề về cấu trúc, phẫu thuật có thể được đề nghị ngay từ đầu.
Ca mổ nhằm giảm đau trong khi vẫn giữ cho khớp cử động được. Ca mổ cũng nhằm giữ chiều cao tự nhiên của ngón cái và duy trì lực kẹp và lực nắm. Với khớp ở gốc ngón cái, 91% mảnh ghép vẫn hoạt động tốt khi theo dõi trung hạn. Chúng tôi sẽ trao đổi với bạn về lựa chọn này và cùng bạn quyết định xem nó có phù hợp với bàn tay và mục tiêu của bạn hay không.
Trước khi phẫu thuật
Trong bảy giờ trước ca phẫu thuật, không được ăn và không được uống bất cứ thứ gì. Chúng tôi yêu cầu bảy giờ thay vì sáu giờ để ca mổ của bạn có thể được đưa lên sớm hơn nếu lịch mổ diễn ra sớm hơn dự kiến. Bác sĩ phẫu thuật sẽ cho bạn biết loại thuốc thường dùng nào cần ngưng và ngưng từ khi nào, và sẽ rất hữu ích nếu bạn mang theo một danh sách ghi lại tất cả các loại thuốc bạn đang dùng. Hãy sắp xếp người lái xe đưa bạn về nhà sau đó, và mặc quần áo rộng rãi, thoải mái. Thường chỉ cần chụp X-quang là đủ để lên kế hoạch cho ca mổ, tuy đôi khi cũng dùng thêm chụp MRI hoặc siêu âm. Nếu bạn mắc các bệnh lý khác, có thể bạn sẽ cần làm xét nghiệm máu hoặc được bác sĩ gây mê, tức là bác sĩ thực hiện gây mê cho bạn, thăm khám trước. Hầu hết bệnh nhân không cần xét nghiệm máu và cũng không cần buổi thăm khám đó.
Vào ngày phẫu thuật
Bạn sẽ đến khu tiếp nhận bệnh nhân phẫu thuật của bệnh viện, nơi bạn được làm thủ tục nhập viện và chuẩn bị cho ca mổ. Bạn sẽ gặp bác sĩ gây mê, tức là bác sĩ phụ trách việc gây mê cho bạn. Ca phẫu thuật này được thực hiện dưới gây mê toàn thân. Bạn sẽ hoàn toàn ngủ say trong suốt ca phẫu thuật. Một số bệnh nhân có thể được tiêm thuốc gây tê vùng để giảm đau sau phẫu thuật; quyết định này do bác sĩ gây mê đưa ra vào ngày mổ, dựa trên tình trạng cụ thể của từng bệnh nhân.
Sau đó, bạn sẽ được đưa vào phòng mổ để tiến hành ca phẫu thuật. Sau ca mổ, bạn tỉnh dậy tại khu hồi sức, nơi các điều dưỡng theo dõi bạn cho đến khi thuốc mê hết tác dụng. Khi đã ổn định, bạn sẽ được chuyển về phòng bệnh hoặc về nhà, tùy thuộc vào loại phẫu thuật và diễn biến hồi phục của bạn.
Quy trình phẫu thuật
Bác sĩ phẫu thuật sẽ rạch một đường duy nhất trên vùng bàn tay được phẫu thuật. Qua đường rạch này, bác sĩ loại bỏ các bề mặt khớp bị mòn, hư tổn. Thay vào chỗ các bề mặt bị mòn đó, bác sĩ đặt một miếng carbon trơn nhẵn, được tạo hình sẵn, nằm giữa các xương. Miếng đệm này đảm nhận vai trò của bề mặt khớp bị mòn, để các xương trượt êm lên nhau thay vì cọ xát vào nhau.
Với khớp ngón cái ở gốc bàn tay, bác sĩ phẫu thuật giữ chiều cao tự nhiên của ngón cái bằng cách đặt miếng đệm vào giữa các xương. Sau đó, khớp được sửa chữa và nâng đỡ để lành ở vị trí tốt. Ngón cái của bạn có thể được giữ cố định ở tư thế thẳng trong khi lành.
Vết mổ được khâu lại bằng chỉ. Một lớp băng gạc được đặt lên vết mổ, và đội ngũ của chúng tôi sẽ hướng dẫn bạn cách chăm sóc vết mổ trong những ngày đầu.
Sau khi phẫu thuật
Hầu hết bệnh nhân sẽ ở lại bệnh viện một đêm sau ca phẫu thuật này, tuy nhiên một số người có thể về nhà ngay trong ngày. Bạn tỉnh dậy tại khu hồi sức, sau đó được chuyển sang phòng bệnh. Các điều dưỡng sẽ giúp bạn cảm thấy dễ chịu và cho bạn dùng thuốc giảm đau nếu bạn cần. Bàn tay của bạn sẽ được băng gạc và đeo nẹp để bảo vệ vùng mổ trong khi lành. Bạn có thể ra khỏi giường và đi lại ngay khi cảm thấy vững. Vui lòng sắp xếp để có người ở cùng bạn trong 24 giờ đầu tiên ở nhà. Chúng tôi sẽ giữ băng gạc trong khoảng 10 ngày; vui lòng đừng tự ý tháo ra trước thời hạn đó trừ khi chúng tôi bảo bạn làm vậy. Chúng tôi sẽ thay hoặc gỡ băng khi khám lại cho bạn.
Quá trình hồi phục
Bạn có thể bị đau và sưng ở bàn tay trong những ngày và tuần đầu tiên. Đây là một phần bình thường của quá trình lành thương và sẽ giảm dần. Kê tay cao khi nghỉ ngơi sẽ giúp ích, và thuốc giảm đau chúng tôi cho bạn sẽ làm dịu cảm giác khó chịu. Hầu hết mọi người thấy giai đoạn đau nhất qua đi sớm, và mức độ dễ chịu cải thiện đều đặn từ đó.
Bàn tay của bạn sẽ được băng gạc và đeo nẹp để bảo vệ khớp trong khi lành. Chúng tôi giữ băng gạc trong khoảng 10 ngày và sẽ thay hoặc gỡ băng khi khám lại cho bạn. Phục hồi chức năng sau phẫu thuật bàn tay là trị liệu bàn tay, không phải vật lý trị liệu. Việc trị liệu bàn tay sau phẫu thuật của bạn sẽ do Ruby Doolan tại Extend Rehabilitation đảm nhận. Ruby là chuyên viên trị liệu bàn tay: cô ấy sẽ hướng dẫn các bài tập của bạn và làm bất kỳ chiếc nẹp nào bạn cần trong quá trình bàn tay hồi phục. Lúc đầu, các bài tập nhẹ nhàng và tập trung vào việc giảm sưng. Khi khả năng cử động trở lại, các bài tập sẽ tăng dần để phục hồi khả năng gập, duỗi và nắm.
Bạn sẽ có thể làm những việc nhẹ nhàng hằng ngày trong nhà trong giới hạn mà nẹp cho phép. Bạn sẽ không thể nắm, kẹp hoặc nâng đồ bằng tay đã mổ trong thời gian tay được giữ cố định. Khi đã tháo nẹp và được bác sĩ phẫu thuật cho phép, bạn có thể bắt đầu sử dụng bàn tay bình thường hơn, và sau đó có thể lái xe. Vui lòng xem trang thông tin về Việc lái xe sau phẫu thuật chi trên để biết chi tiết.
Quá trình hồi phục khác nhau ở mỗi người. Thời gian hồi phục của bạn có thể khác, và bác sĩ phẫu thuật cùng chuyên viên trị liệu sẽ hướng dẫn bạn trong suốt quá trình.
Những biến chứng có thể xảy ra
Hầu hết bệnh nhân đều hồi phục tốt, nhưng đôi khi vẫn có thể gặp phải các vấn đề. Bác sĩ phẫu thuật và đội ngũ y tế sẽ theo dõi sát sao để phát hiện sớm bất kỳ dấu hiệu bất thường nào.
Đôi khi mảnh ghép thay đổi vị trí hoặc lún vào xương. Bạn có thể nhận thấy cơn đau mới ở khớp, cảm giác ngón tay hoặc ngón cái không nằm thẳng, hoặc sự thay đổi trong cách ngón cử động. Nếu bạn nhận thấy bất kỳ điều nào trong số này, hãy nêu ra trong lần tái khám tiếp theo.
Mảnh ghép cũng có thể bị lỏng. Tình trạng này thường biểu hiện bằng cơn đau quay trở lại sau một thời gian dài đã đỡ nhiều, thường nặng hơn khi bạn nắm hoặc kẹp. Hãy báo cho bác sĩ phẫu thuật nếu điều này xảy ra.
Khớp có thể bị cứng. Ngón tay hoặc ngón cái có thể không gập hoặc duỗi được nhiều như trước, và gân ở mặt mu của khớp có thể bị mô sẹo làm dính lại. Hãy nói điều này trong buổi tái khám để chuyên viên trị liệu có thể điều chỉnh các bài tập của bạn.
Khớp có thể trở nên mất ổn định, hoặc biến dạng ban đầu có thể quay trở lại. Bạn có thể thấy ngón tay lại bị lệch ra khỏi trục. Hãy nêu điều này trong cuộc hẹn tiếp theo.
Nhiễm trùng không thường gặp nhưng cần được xử lý nhanh. Hãy gọi cho phòng khám ngay trong ngày nếu bạn bị sốt, có vùng đỏ lan rộng quanh vết mổ, hoặc có dịch hay mủ rỉ ra từ vết mổ. Nếu cơn đau tiếp tục nặng hơn dù đã dùng thuốc giảm đau, bạn cũng cần gọi cho phòng khám ngay trong ngày.
Các cấu trúc ở gần có thể bị kích ứng hoặc tổn thương trong loại phẫu thuật này. Một dây thần kinh gần ngón cái có thể trở nên nhạy cảm, gây cảm giác châm chích hoặc thay đổi cảm giác ở da. Động mạch ở phía ngón cái của cổ tay, hoặc một gân ở mặt trước cổ tay, có thể bị ảnh hưởng. Nếu bạn bị tê hoặc không thể cử động các ngón tay khi thuốc gây tê vùng đã hết tác dụng, vào khoảng 24 giờ, hãy gọi cho phòng khám. Tê và yếu trong 24 giờ đầu sau khi gây tê vùng là điều bình thường.
Đôi khi một xương ở bàn tay có thể bị gãy trong hoặc sau phẫu thuật. Điều này gây đau và sưng đột ngột. Hãy gọi cho phòng khám nếu điều này xảy ra.
Nếu mảnh ghép thất bại và không thể cứu vãn, các ca phẫu thuật khác có thể giúp ích. Mảnh ghép có thể được lấy ra và khớp được điều trị theo cách khác, cách này giúp giảm đau một cách đáng tin cậy. Trong những trường hợp hiếm gặp, khớp có thể được hàn lại, nghĩa là làm cứng khớp vĩnh viễn, hoặc có thể cần phải cắt bỏ ngón tay.
Bảng liệt kê các biến chứng ở trang này cung cấp tỷ lệ xảy ra cụ thể nếu bạn muốn biết thêm chi tiết.
Khi nào nên liên hệ với chúng tôi
Hầu hết các vấn đề xuất hiện sớm, và hành động nhanh sẽ giúp xử lý chúng dễ dàng hơn. Hãy gọi cho phòng khám ngay trong ngày nếu bạn bị sốt, có vùng đỏ lan rộng quanh vết mổ, hoặc có dịch hay mủ rỉ ra từ vết mổ. Cũng hãy gọi cho phòng khám ngay trong ngày nếu cơn đau tiếp tục nặng hơn dù đã dùng thuốc giảm đau. Hãy gọi cho phòng khám nếu bạn bị tê hoặc không thể cử động các ngón tay khi thuốc gây tê vùng đã hết tác dụng, vào khoảng 24 giờ. Tê và yếu trong 24 giờ đầu sau khi gây tê vùng là điều bình thường.
Hãy đến khoa cấp cứu nếu bạn bị sưng hoặc đau bắp chân, hoặc bị khó thở hoặc đau ngực. Đây có thể là dấu hiệu của cục máu đông. Hãy đến khoa cấp cứu nếu các ngón tay, bàn tay hoặc ngón cái của bạn trở nên nhợt nhạt, lạnh, trắng bệch, tím tái hoặc sẫm màu. Đây có thể là một vấn đề về tuần hoàn máu.
Nếu bạn không thể liên lạc với phòng khám, khi ngoài giờ làm việc hoặc vào cuối tuần, hãy đến khoa cấp cứu gần nhất.
Nơi để tìm đọc thêm thông tin về bệnh lý
Trang này nói về chính ca phẫu thuật. Các thông tin liên quan đến bệnh lý được điều trị, bao gồm cả bằng chứng cho thấy khi nào phẫu thuật có ích và khi nào thì không, đều được trình bày chi tiết hơn trên trang Viêm khớp gốc ngón tay cái.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Pyrocarbon interpositional arthroplasty provided pain relief and high patient satisfaction with good implant longevity in a study with minimum 8-year follow-up [1].
- Partial trapeziectomy with pyrocarbon arthroplasty may prove to be a successful option for the treatment of trapeziometacarpal joint osteoarthritis, providing excellent pain relief and high patient satisfaction [2].
- PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis and can provide a stable, mobile, and pain-free joint [3].
- The Pyrocardan implant is not superior to other arthroplasty methods and has a high complication rate [4].
- The Pyrocardan implant appears as a simple alternative to the Dubert procedure for ulnar carpo-metacarpal osteoarthritis, particularly in cases involving the 4th ray [5].
- The PyroDisk implant for treating advanced trapeziometacarpal arthritis did not demonstrate superiority over published outcome data of trapeziectomy with or without ligament reconstruction and tendon interposition [6].
- The good functional and radiographic outcomes, and the absence of surgical complications are evidence that the Pyrocardan resurfacing implant is a valid option for treating STT osteoarthritis [7].
- Arthroplasty is recommended for patients with post-trauma painful PIP joints [8].
- Active patients, under 65 years of age with Eaton-Littler stage III osteoarthritis of the thumb CMC joint who are treated with anatomic pyrolytic carbon resurfacing hemiarthroplasty and stabilisation may achieve sustained improvement in pain and hand function for up to 6.5 years [9].
- The insertion of pyrolytic carbon implants for PIPJ arthroplasty is a technically demanding procedure, but it has the potential to achieve pain relief, stability, satisfactory ROM, and correction of the deformity [10].
- The results of pyrolytic carbon PIPJ arthroplasty in review were unpredictable and may not be superior to those achieved with other methods of arthroplasty [10].
- A study with long-term follow-up after pyrocarbon disc interposition for the treatment of CMC1 osteoarthritis grade 2 to 3 in more than 150 thumbs was conducted [11].
- The PyroDisk interposition arthroplasty confirmed good 5-year clinical results [12, 13].
- PyroDisk interposition has merit in patients with early disease unresponsive to conservative measures, in whom trapeziectomy may be considered too destructive and hemi or total arthroplasty overzealous [14].
- The good results, the simple surgical procedure, the absence of complications, and the lack of a need for any fixation or ligamentoplasty confirm the advantages of this pyrocarbon implant in the treatment of STT arthrosis [15].
- All subjective and objective outcomes were similar following LRTI and pyrolytic interpositional arthroplasty in patients with TMC arthritis, except pinch strength, which was more improved following pyrolytic interpositional arthroplasty [16].
- The encouraging mid-term clinical results of the interposition implant (APSI) in the context of proximal pole scaphoid pseudarthrosis make this technique a proven alternative, without precluding a definitive therapeutic option in case of failure [18].
- The Pyrocardan implant may be contraindicated in patients with symptomatic STT OA who intend to continue high-load activities, particularly those involving wrist extension under load, such as tennis [20].
Anatomy & Pathophysiology
Bony Anatomy
- The skeleton of the hand and wrist consists of 27 bones, of which 19 are long bones [28].
- The radial ray or first ray is the shortest, made up of only three bones: a metacarpal and two phalanges [28].
- The trapezium is clearly angled out in front of the carpal plane so that the first metacarpal makes an angle of about 45 degrees with the second metacarpal in the sagittal plane [28].
- The thumb metacarpal is the shortest, while the index metacarpal is by far the longest [28].
- The epiphyseal plates are located at the proximal ends of the phalanges and the first metacarpal, whereas they are located at the distal ends of the other metacarpals [28].
- The thumb metacarpal is independent and articulates with the trapezium [35].
- The index metacarpal is the most firmly fixed [35].
- The ring metacarpal has about 10 degrees of mobility in flexion and extension [35].
- The fifth metacarpal has a range of flexion–extension of approximately 20 degrees [35].
Soft Tissue & Vascular Anatomy
- The extrinsic extensors run through six different fibroosseous retinacular compartments at the wrist level [27].
- The first (most radial) compartment contains the abductor pollicis longus and the extensor pollicis brevis [27].
- The second extensor compartment contains the extensor carpi radialis longus and the extensor carpi radialis brevis [27].
- The third compartment contains the extensor pollicis longus, which turns abruptly radialward about Lister tubercle [27].
- The fourth extensor compartment contains the extensor indicis proprius lying deep to the four tendons of the extensor digitorum communis [27].
- The fifth compartment contains the extensor digiti quinti [27].
- The sixth compartment contains the extensor carpi ulnaris tendon, which inserts at the base of the little finger metacarpal [27].
- The extrinsic finger flexors are the flexor digitorum profundus and the flexor digitorum superficialis [27].
- The flexor digitorum profundus inserts on the proximal volar aspect of the distal phalanx [27].
- The flexor digitorum superficialis acts as a flexor of the proximal interphalangeal and metacarpophalangeal joints [27].
- There are seven interosseous muscles, four dorsal and three volar [32].
- The dorsal interossei are abductors [32].
- The volar interossei are adductors [32].
- The middle finger has two dorsal interossei (abductors) and no volar interossei (adductors) because the central axis of the hand lies within it [32].
- The "princeps pollicis" artery is the terminal branch of the radial artery and crosses the first intermetacarpal space [36].
- The princeps pollicis runs along the ulnar side of the first metacarpal bone and along the volar surface of the adductor muscle [36].
- The princeps pollicis divides into two terminal rami, namely the collateral palmar arteries of the thumb, at the level of the cutaneous flexion crease of the metacarpophalangeal joint [36].
- An arcade located deep in the flexor tendon joins together the two arteries at the level of the distal metaphysis of the first phalanx [36].
- The dorsal arteries of the thumb originate from the palmar arteries (princeps, commissural or anastomoses of the superficial arcade) at the level of the first metacarpal [36].
Functional Mechanics
- The wrist has three axes of movement, permitting the hand to be positioned in any spatial configuration [28].
- The thumb ray is more mobile, shorter, and more proximal than the other rays, allowing it to project in front of the plane of the palm to oppose itself to the other four rays [28].
- The skeleton of the hand presents a longitudinal and transverse concavity, giving it the shape of a cup with a palmar concavity when the thumb is placed next to the index finger [28].
- The transverse axis of the palm forms an acute angle of approximately 75 degrees with the longitudinal axis [28].
- The metacarpal arch is endowed with a great deal of adaptability because of the mobility of the peripheral metacarpals [35].
- The heads of the second and third metacarpals are fixed [35].
- The mobility of the ulnar metacarpals allows "flexion" of 10 degrees for the fourth metacarpal, and "flexion" of 20 degrees for the fifth metacarpal [35].
- The keystones of the longitudinal arches are the metacarpophalangeal articulations, whose thick anterior glenoid capsules, the volar plates, prevent hyperextension [35].
- The dorsal skin slides distally to allow metacarpophalangeal joint flexion [40].
- Interphalangeal flexion is accomplished by means of a special arrangement of skin folds on the dorsum of each articulation [40].
- The gliding mechanism for tendons in narrow crowded areas is assured by the synovial sheath, which allows a considerable amplitude of movement [40].
- The fibrous sheath assumes the role of a pulley when the tendon changes direction [40].
- The position of each articulation depends on the equilibrium of forces acting at that level, and this equilibrium is subject to the position of the immediately proximal articulation [40].
- Single articular movements around a fixed perpendicular axis simply do not exist in the hand [40].
- Almost all movements in the hand are around oblique and variable axes, resulting in combined movements permitting optimal orientation of the phalanges at the time of prehension [40].
Indications and Disease Staging
- PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis [3].
- The Pyrocardan resurfacing implant is a valid option for treating scaphotrapeziotrapezoid (STT) osteoarthritis [7].
- The pyrocarbon implant is indicated for the treatment of STT arthrosis [15].
- The pyrocarbon interposition implant (APSI) is an alternative for the treatment of proximal pole scaphoid pseudarthrosis [18].
- The Pyrocardan implant may be contraindicated in patients with symptomatic STT osteoarthritis who intend to continue high-load activities, particularly those involving wrist extension under load, such as tennis [20].
Patient Selection and Demographics
- Active patients under 65 years of age with Eaton-Littler stage III osteoarthritis of the thumb CMC joint are candidates for anatomic pyrolytic carbon resurfacing hemiarthroplasty and stabilisation [9].
- Pyrocarbon disc interposition is used for the treatment of CMC1 osteoarthritis grade 2 to 3 [11].
- Total trapezectomy associated with the placement of a NuGrip pyrocarbon implant is a procedure for the replacement of the TMC joint [22].
Comparative Classification and Efficacy
- The insertion of pyrolytic carbon implants for PIPJ arthroplasty has the potential to achieve pain relief, stability, satisfactory ROM, and correction of the deformity; however, the results in this review were unpredictable and may not be superior to those achieved with other methods of arthroplasty [10].
Clinical Presentation
- Pyrocarbon interpositional arthroplasty is indicated for trapeziometacarpal osteoarthritis [1].
- Pyrocarbon interpositional arthroplasty is indicated for trapeziometacarpal joint osteoarthritis [2].
- PyroCarbon implant hemiarthroplasty is a surgical technique for stages II and III trapeziometacarpal arthritis [3].
- The Pyrocardan implant is used for trapeziometacarpal osteoarthritis [4].
- The Pyrocardan implant is used for ulnar carpo-metacarpal osteoarthritis, particularly in cases involving the 4th ray [5].
- The PyroDisk implant is used for advanced trapeziometacarpal arthritis [6].
- The Pyrocardan resurfacing implant is used for scaphotrapeziotrapezoid (STT) osteoarthritis [7].
- Pyrocarbon PIP arthroplasty is used for post-trauma painful joints [8].
- Anatomic pyrolytic carbon resurfacing hemiarthroplasty is used for Eaton-Littler stage III osteoarthritis of the thumb CMC joint in patients under 65 years of age [9].
- Pyrolytic carbon implants are used for proximal interphalangeal joint (PIPJ) arthroplasty [10].
- Pyrocarbon disc interposition is used for CMC1 osteoarthritis grade 2 to 3 [11].
- PyroDisk interposition arthroplasty is used for trapeziometacarpal osteoarthritis [12].
- PyroDisk interposition is indicated for patients with early disease unresponsive to conservative measures, in whom trapeziectomy may be considered too destructive and hemi or total arthroplasty overzealous [14].
- The pyrocarbon implant is used for STT arthrosis [15].
- Pyrolytic interpositional arthroplasty is used for TMC arthritis [16].
- Pi2 pyrocarbon spacer arthroplasty is used for carpometacarpal joint osteoarthritis [17].
- The interposition implant (APSI) is used for pseudarthrosis of the proximal pole of the scaphoid [18].
- A pyrocarbon implant is used for Kienböck disease [19].
- Total trapeziectomy associated with the placement of a pyrocarbon type Nugrip implant is used after replacement of the TMC joint [22].
- The Pyrocardan implant is used for stage 2 trapeziometacarpal osteoarthritis [23].
- The Pi2 pyrocarbon implant is used in total trapeziectomy and suspension ligamentoplasty [24].
- The Pi2 pyrocarbon implant is used in destructions of the capitolunate joint space [25].
Investigations
- Clinical evaluation of the hand and wrist requires combining patient history with a careful physical examination to pinpoint or narrow the scope of possible pathologic processes [26].
- Diagnostic tests such as imaging and serum laboratory studies are useful in determining hand pathology but can be expensive, time-consuming, and often nonspecific [26].
- A systematic method to approaching the physical examination of the hand is essential due to the number of structures in a small space [26].
Treatment
Trapeziometacarpal Joint Osteoarthritis
- Pyrocarbon interpositional arthroplasty provided pain relief and high patient satisfaction with good implant longevity in a minimum 8-year follow-up study [1].
- Partial trapeziectomy with pyrocarbon arthroplasty provides excellent pain relief and high patient satisfaction for trapeziometacarpal joint osteoarthritis [2].
- PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis that can provide a stable, mobile, and pain-free joint [3].
- The Pyrocardan implant is not superior to other arthroplasty methods and has a high complication rate for trapeziometacarpal osteoarthritis [4].
- Long-term follow-up data for pyrocarbon disc interposition for the treatment of CMC1 osteoarthritis grade 2 to 3 is available in a study involving more than 150 thumbs [11].
- Interposition arthroplasty with PyroDisk confirmed good 5-year clinical results [12, 13].
- The modified procedure of partial trapeziectomy and pyrocarbon interpositional arthroplasty improves functional results by increasing active and passive range of movement at the TMCJ, providing joint stability and pain relief comparable to standard techniques, while preserving thumb length and key pinch strength [29].
- Pyrocarbon interposition arthroplasty for trapeziometacarpal osteoarthritis does not preclude subsequent conventional arthroplasty techniques in the event of failure [23].
Scaphotrapeziotrapezoid Joint Osteoarthritis
- The Pyrocardan resurfacing implant is a valid option for treating STT osteoarthritis, evidenced by good functional and radiographic outcomes and the absence of surgical complications [7].
- The good results, simple surgical procedure, absence of complications, and lack of need for fixation or ligamentoplasty confirm the advantages of the pyrocarbon implant in the treatment of STT arthrosis [15].
Other Indications
- Pyrocarbon PIP arthroplasty is recommended for post-trauma painful joints [8].
- The insertion of pyrolytic carbon implants for PIPJ arthroplasty is a technically demanding procedure with the potential to achieve pain relief, stability, satisfactory ROM, and correction of deformity, though results were unpredictable and may not be superior to other methods of arthroplasty [10].
- Range of motion improved after Pi2 pyrocarbon spacer arthroplasty in carpometacarpal joint osteoarthritis, especially in opposition with a mean Kapandji score of 9.60, with no major aggravation of metacarpophalangeal extension [17].
- The interposition implant (APSI) for proximal scaphoid pseudarthrosis provides encouraging mid-term clinical results and serves as a proven alternative without precluding a definitive therapeutic option in case of failure [18].
- There were no changes in range of motion after surgery for Kienböck disease treated with a pyrocarbon implant, and the average grip strength was 76.5% of the contralateral side [19].
Complications
- The Pyrocardan implant has a high complication rate [4].
- The Pyrocardan resurfacing implant for STT osteoarthritis was associated with the absence of surgical complications [7].
- The pyrocarbon implant for STT arthrosis was associated with the absence of complications [15].
Recovery
- Range of motion improved after Pi2 pyrocarbon spacer arthroplasty, especially in opposition, with a mean Kapandji score of 9.60 [17].
- There was no major aggravation of metacarpophalangeal extension following Pi2 pyrocarbon spacer arthroplasty [17].
- The average grip strength was 76.5% of the contralateral side after pyrocarbon implant treatment for Kienböck disease [19].
- There were no changes in range of motion after surgery for Kienböck disease treated with a pyrocarbon implant [19].
Key Evidence
- [L4] Pyrocarbon interpositional arthroplasty provided pain relief and high patient satisfaction with good implant longevity. [1] (10.1177/1753193420906805)
- [L3] Partial trapeziectomy with pyrocarbon arthroplasty may prove to be a successful option for the treatment of trapeziometacarpal joint osteoarthritis, providing excellent pain relief and high patient satisfaction. [2] (10.1177/1753193413519384)
- [L4] PyroCarbon implant hemiarthroplasty is a promising surgical technique for stages II and III trapeziometacarpal arthritis and can provide a stable, mobile, and pain-free joint. [3] (10.1097/bth.0b013e318271aab7)
- [L4] The study concludes that the Pyrocardan implant is not superior to other arthroplasty methods and has a high complication rate. [4] (10.1016/j.hansur.2016.09.004)
- [L4] The Pyrocardan implant appears as a simple alternative to the Dubert procedure for ulnar carpo-metacarpal osteoarthritis, particularly in cases involving the 4th ray. [5] (10.1016/j.hansur.2018.10.044)
- [L4] The PyroDisk implant for treating advanced trapeziometacarpal arthritis did not demonstrate superiority over published outcome data of trapeziectomy with or without ligament reconstruction and tendon interposition. [6] (10.1016/j.jhsa.2014.07.011)
- [L3] The good functional and radiographic outcomes, and the absence of surgical complications are evidence that the Pyrocardan1 resurfacing implant is a valid option for treating STT osteoarthritis. [7] (10.1016/j.hansur.2017.01.003)
- [L4] We recommend arthroplasty for this group of patients. [8] (10.1016/s0363-5023(03)80384-2)
- [L3] Active patients, under 65 years of age with Eaton-Littler stage III osteoarthritis of the thumb CMC joint who are treated with anatomic pyrolytic carbon resurfacing hemiarthroplasty and stabilisation may achieve sustained improvement in pain and hand function for up to 6.5 years. [9] (10.1142/s2424835518500443)
- [L4] The insertion of pyrolytic carbon implants for PIPJ arthroplasty is a technically demanding procedure, but it has the potential to achieve pain relief, stability, satisfactory ROM, and correction of the deformity; however, the results in this review were unpredictable and may not be superior to those achieved with other methods of arthroplasty. [10] (10.1016/j.jhsa.2006.02.018)
- [L4] This is the first study with long-term follow-up after pyrocarbon disc interposition for the treatment of CMC1 osteoarthritis grade 2 to 3 in more than 150 thumbs. [11] (10.1016/j.jhsa.2018.06.086)
- [L4] Our study confirms the good 5-year clinical results of interposition arthroplasty with PyroDisk. [12] (10.1177/1558944716660555n)
- [L4] Our study confirms the good 5-year clinical results of interposition arthroplasty with PyroDisk. [13] (10.1177/1558944716660555m)
- [L4] PyroDisk interposition has merit in patients with early disease unresponsive to conservative measures, in whom trapeziectomy may be considered too destructive and hemi or total arthroplasty overzealous. [14] (10.1177/1753193420981552)
- [L4] The good results, the simple surgical procedure, the absence of complications, and the lack of a need for any fixation or ligamentoplasty confirm the advantages of this pyrocarbon implant in the treatment of STT arthrosis. [15] (10.1016/j.main.2005.04.010)
- [L3] All subjective and objective outcomes were similar following LRTI and pyrolytic interpositional arthroplasty in patients with TMC arthritis, except pinch strength, which was more improved following pyrolytic interpositional arthroplasty. [16] (10.1155/2019/7961507)
- [L3] Range of motion improved, especially in opposition (mean Kapandji score, 9.60), with no major aggravation of metacarpophalangeal extension. [17] (10.1016/j.hansur.2016.05.002)
- [L4] Les résultats cliniques encourageants à moyen terme de l’implant d’interposition (APSI), dans le cadre d’une pseudarthrose du pôle proximal du scaphoïde, font de cette technique une alternative probante, sans interdire une option thérapeutique définitive en cas d’échec. [18] (10.1016/j.main.2011.10.031)
- [L5] There were no changes in range of motion after surgery and the average grip strength was 76.5% of the contralateral side. [19] (10.1016/j.main.2014.09.002)
- [Case_report] The Pyrocardan implant may be contraindicated in patients with symptomatic STT OA who intend to continue high-load activities, particularly those involving wrist extension under load, such as tennis. [20] (10.1016/j.jhsg.2026.100964)
- [L4] La trapézectomie totale associée à la mise en place d'un implant en pyrocarbone type Nugrip après le remplacement de l'articulation TMC semble être une procédure attrayante. [22] (10.1016/j.hansur.2018.10.166)
- [L3] Il ne coupe pas les ponts en cas d'éventuel échec à des techniques d'arthroplastie plus conventionnelles. [23] (10.1016/j.main.2011.10.132)
- [L3] The implant Pi2 seems to contribute keeping trapezial height, without functional advantages and with a risk of dislocation. [24] (10.1016/j.main.2013.04.003)
- [L4] Cette technique a l'avantage de préserver les mobilités médio-carpiennes et les ligaments extrinsèques du poignet. [25] (10.1016/j.hansur.2016.10.125)
- [L4] The modified procedure improves functional results by increasing active and passive range of movement at the TMCJ, providing joint stability and pain relief comparable to standard techniques, while preserving thumb length and key pinch strength. [29] (10.1177/1753193414553368)
References
[1] Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal osteoarthritis: minimum 8-year follow-up. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420906805
[2] Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal joint osteoarthritis: results after minimum 2 years of follow-up. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193413519384
[3] PyroCarbon Implant Hemiarthroplasty for Trapeziometacarpal Arthritis. Techniques in Hand & Upper Extremity Surgery. 2013. DOI: 10.1097/bth.0b013e318271aab7
[4] Early outcomes of Pyrocardan® implants for trapeziometacarpal osteoarthritis. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.09.004
[5] L’implant en Pyrocarbone (Pyrocardan®) dans le traitement de l’arthrose carpo-métacarpienne ulnaire post-traumatique. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.10.044
[6] Pyrocarbon Interposition (PyroDisk) Implant for Trapeziometacarpal Osteoarthritis: Minimum 5-Year Follow-Up. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.07.011
[7] Treatment of scaphotrapeziotrapezoid osteoarthritis with the Pyrocardan® implant: Results with a minimum follow-up of 2 years. Hand Surgery and Rehabilitation. 2017. DOI: 10.1016/j.hansur.2017.01.003
[8] Pyrocarbon PIP arthroplasty for post trauma painful joints. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)80384-2
[9] Anatomic Pyrocarbon Hemiarthroplasty for Thumb Carpometacarpal Osteoarthritis in Patients under 65 Years: Mid Term Results. The Journal of Hand Surgery (Asian-Pacific Volume). 2018. DOI: 10.1142/s2424835518500443
[10] Pyrolytic Carbon Proximal Interphalangeal Joint Resurfacing Arthroplasty. The Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsa.2006.02.018
[11] Long-Term Follow-Up After Pyrocarbon Disc Interposition for Thumb CMC Osteoarthritis. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.06.086
[12] Pyrocarbon Interposition Arthroplasty of the Trapeziometacarpal Joint With the PyroDisk. HAND. 2016. DOI: 10.1177/1558944716660555n
[13] PyroDisk Interposition Implant for Trapeziometacarpal Osteoarthritis. HAND. 2016. DOI: 10.1177/1558944716660555m
[14] Re: Smeraglia F, et al. Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal osteoarthritis: minimum 8-year follow-up. J Hand Surg Eur. 2020, 45: 472–6. Journal of Hand Surgery (European Volume). 2021. DOI: 10.1177/1753193420981552
[15] Traitement de l'arthrose S.T.T. par un Implant en pyrocarbone. Premiers résultats. Chirurgie de la Main. 2005. DOI: 10.1016/j.main.2005.04.010
[16] Tendon versus Pyrocarbon Interpositional Arthroplasty in the Treatment of Trapeziometacarpal Osteoarthritis. BioMed Research International. 2019. DOI: 10.1155/2019/7961507
[17] A ten-year prospective outcome study of Pi2 pyrocarbon spacer arthroplasty in carpometacarpal joint osteoarthritis. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.05.002
[18] Pseudarthrose du scaphoïde : résection proximale et interposition d’un implant en pyrocarbone, à propos de 20 cas. Chirurgie de la Main. 2011. DOI: 10.1016/j.main.2011.10.031
[19] Le traitement de la maladie de Kienböck par un implant en pyrocarbone : fait clinique. Chirurgie de la Main. 2014. DOI: 10.1016/j.main.2014.09.002
[20] Game, Set… Revision! A Case Report of a Tennis Player Who Smashed His Scaphotrapeziotrapezoid-Joint Pyrocardan Implant Twice. Journal of Hand Surgery Global Online. 2026. DOI: 10.1016/j.jhsg.2026.100964
[22] Reprise de prothèses totales trapézo-métacarpiennes par un implant en Pyrocarbone type NuGrip. À propos de 6 cas. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.10.166
[23] L’implant pyrocardan : interposition libre en pyrocarbone trapezometacarpienne pour l’arthrose de stade 2. Chirurgie de la Main. 2011. DOI: 10.1016/j.main.2011.10.132
[24] Trapézectomie totale et ligamentoplastie de suspension : une interposition par un implant Pi2® en pyrocarbone a-t-elle un intérêt ?. Chirurgie de la Main. 2013. DOI: 10.1016/j.main.2013.04.003
[25] Utilisation de l’implant en pyrocarbone de type Pi2 dans les destructions de l’interligne articulaire capito-lunaire. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2016.10.125
[26] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[27] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > Image DISORDERS OF THE MUSCULATURE OF THE HAND.
[28] Exam Of The Hand Wrist 2Ed. 1.1 SKELETON OF THE HAND > The osseous skeleton.
[29] Re: Mariconda et al. Partial trapeziectomy and pyrocarbon interpositional arthroplasty for trapeziometacarpal joint osteoarthritis: results after minimum 2 years of follow-up. J Hand Surg Eur. 2014, 39: 604–610. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193414553368
[32] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[35] Exam Of The Hand Wrist 2Ed. The arches of the hand > The metacarpal arch.
[36] Exam Of The Hand Wrist 2Ed. Techniques of investigation of the arterial supply by J P Melki > Vascularization of the thumb > Palmar aspect.
[40] Exam Of The Hand Wrist 2Ed. 1.3 MOVEMENTS OF THE HAND AND WRIST > Gliding mechanisms.