Patients › General-Health
Xét nghiệm thần kinh và đo dẫn truyền thần kinh
What nerve conduction studies and EMG are, why they are done for carpal tunnel and other nerve problems, what to expect, and how accurate they are.
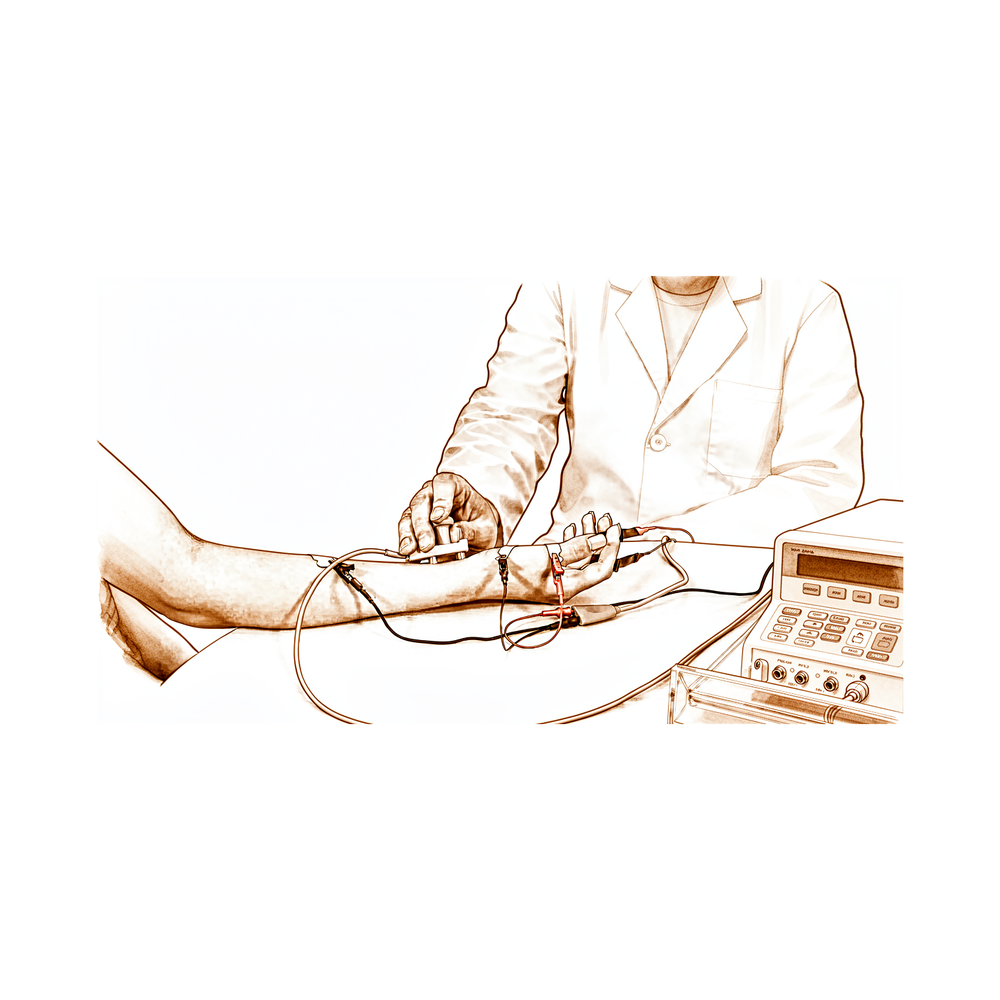
Định nghĩa
Xét nghiệm thần kinh đo khả năng dẫn truyền tín hiệu điện của các dây thần kinh. Có hai phương pháp dùng điện để kiểm tra chức năng thần kinh, và cả hai đều đã được chứng minh là hữu ích trong thực tế [1]. Xét nghiệm chính được gọi là đo dẫn truyền thần kinh. Một thiết bị nhỏ truyền một xung điện rất nhỏ vào dây thần kinh của bạn và ghi lại tốc độ truyền của tín hiệu. Nếu dây thần kinh bị chèn ép hoặc tổn thương, tín hiệu sẽ chậm lại hoặc yếu đi.
Các xét nghiệm này được dùng nhiều nhất cho hội chứng ống cổ tay, khi dây thần kinh ở mặt trước cổ tay bị chèn ép. Các xét nghiệm này được xem là một phần không thể thiếu của việc đánh giá trước khi phẫu thuật cho bệnh lý này [2]. Hầu hết các bác sĩ sẽ không phẫu thuật khi chưa có sự xác nhận này [3]. Các xét nghiệm cũng có thể giúp ích cho các vấn đề thần kinh khác, chẳng hạn như dây thần kinh bị chèn ép ở khuỷu tay (hội chứng ống khuỷu tay) [4].
Bạn thường sẽ được làm thêm một xét nghiệm thứ hai trong cùng buổi khám. Với xét nghiệm này, một cây kim nhỏ được đặt vào một vài cơ. Xét nghiệm này kiểm tra mức độ đáp ứng của các cơ với dây thần kinh chi phối chúng. Gộp lại, các xét nghiệm này được gọi là thăm dò điện chẩn đoán, nghĩa đơn giản là các xét nghiệm dùng điện để khảo sát dây thần kinh và cơ.
Các xét nghiệm này có tác dụng vì dây thần kinh truyền tín hiệu giống như dây điện truyền dòng điện. Một dây thần kinh bị chèn ép hoạt động giống như một sợi cáp bị kẹp, nên tín hiệu truyền dọc theo nó bị chậm lại hoặc giảm đi. Kết quả cho biết mức độ suy giảm chức năng của dây thần kinh, và đây là chỉ dấu tốt nhất hiện có về mức độ nặng tổng thể của bệnh [5]. Giá trị của các xét nghiệm này nằm ở việc chẩn đoán đúng và đánh giá mức độ nặng, chứ không phải ở việc dự đoán bạn sẽ cảm thấy thế nào sau phẫu thuật [6].
Một điểm cần biết: kết quả xét nghiệm bình thường không loại trừ hội chứng ống cổ tay, vì sự chèn ép lên dây thần kinh có thể lúc có lúc không.
Phương pháp này có hiệu quả không?
Câu trả lời thẳng thắn là các xét nghiệm này làm tốt một số việc và còn hạn chế ở những việc khác. Đây là một công cụ bổ sung hữu ích khi kiểm tra hội chứng ống cổ tay, đặc biệt khi các xét nghiệm tiêu chuẩn cho kết quả bình thường [7]. Một nghiên cứu về một xét nghiệm thần kinh đặc biệt cho thấy xét nghiệm này phát hiện được bệnh ở 69% trường hợp, và mọi kết quả dương tính đều chính xác. Khi kết hợp xét nghiệm đó với một cách đo cảm giác khác, xét nghiệm phát hiện được 84% trường hợp [8].
Các xét nghiệm cũng giúp xác nhận chẩn đoán trước phẫu thuật. Khi các dấu hiệu và triệu chứng của bạn cho thấy dây thần kinh bị chèn ép ở mức nhẹ đến trung bình và đang được cân nhắc phẫu thuật, việc làm thêm xét nghiệm có thể tăng khả năng phẫu thuật nhắm đúng vào một vấn đề có thật và điều trị được [9]. Một nghiên cứu cho thấy có khoảng cách lớn giữa số người được chẩn đoán chỉ dựa vào triệu chứng (73%) và số người được xác nhận bằng các xét nghiệm này cùng với siêu âm (51%) [10]. Chính khoảng cách đó là lý do xét nghiệm quan trọng: xét nghiệm giúp phân biệt ai thực sự có vấn đề về thần kinh mà phẫu thuật có thể giúp ích.
Các xét nghiệm này cũng có những hạn chế. Chất lượng xét nghiệm khác nhau giữa các cơ sở thực hiện, và một số báo cáo cung cấp nhiều chi tiết hơn những báo cáo khác [11]. Các tiêu chí để đọc kết quả cũng cần được định nghĩa rõ ràng hơn, để chẩn đoán được chính xác và không thực hiện phẫu thuật khi không cần thiết [12]. Và các xét nghiệm không thể cho bạn biết mọi điều. Xét nghiệm đo dây thần kinh, chứ không đo các triệu chứng của bạn.
Một số kết quả còn chưa thống nhất. Những thay đổi trong kết quả xét nghiệm sau khi tiêm steroid không có ý nghĩa đáng kể ở thời điểm hai năm [13]. Mặt khác, đáp ứng tốt với mũi tiêm là một dấu hiệu hữu ích cho biết phẫu thuật có thể mang lại kết quả thế nào [14]. Một chỉ số từ các xét nghiệm, gọi là thời gian tiềm vận động ngoại vi, nghĩa đơn giản là thời gian tín hiệu cần để đến một cơ, có phần giá trị trong việc dự đoán bạn sẽ hồi phục thế nào sau phẫu thuật [15].
Vì vậy, các xét nghiệm này là một công cụ chẩn đoán tốt. Chúng kém tin cậy hơn khi được dùng như một quả cầu pha lê để đoán trước quá trình hồi phục của bạn.
Những rủi ro là gì?
Xét nghiệm thần kinh an toàn, nhưng bạn nên biết trước những gì sẽ xảy ra. Tác dụng thường gặp nhất là cảm giác khó chịu trong lúc làm xét nghiệm. Các xung điện có cảm giác như những cú gõ nhẹ hoặc những cơn giật nhói nhỏ. Nếu một cây kim nhỏ được đặt vào cơ, bạn sẽ thấy nhói trong chốc lát, và cơ có thể đau nhức trong một hoặc hai ngày sau đó. Phiên bản xét nghiệm đo ở ngón đeo nhẫn thực hiện nhanh và gây rất ít gánh nặng cho bạn [16].
Các xung điện không để lại ảnh hưởng lâu dài nào trên da hay mô của bạn. Các xung điện rất nhỏ và truyền qua da mà không làm tổn thương da. Nếu bạn làm xét nghiệm có dùng kim, các vị trí kim đâm có thể hơi đau khi chạm vào, và có thể xuất hiện một vết bầm nhỏ. Những điều này sẽ tự khỏi.
Các bằng chứng không mô tả ảnh hưởng lên các bộ phận khác của cơ thể, và cũng không mô tả các biến chứng hiếm gặp nhưng nghiêm trọng của các xét nghiệm này. Điều này cần được nói rõ: các nghiên cứu làm cơ sở cho trang này báo cáo về khả năng chẩn đoán và dự đoán của xét nghiệm, chứ không báo cáo về tác hại, vì vậy thông tin ở đây về các rủi ro nghiêm trọng còn hạn chế.
Có một rủi ro không liên quan đến thể chất. Các xét nghiệm có thể được những người thực hiện khác nhau đọc theo cách khác nhau, và một số báo cáo cung cấp nhiều chi tiết hơn những báo cáo khác [11]. Một báo cáo liệt kê những bất thường nhỏ mà không giải thích có thể dẫn đến kết luận sai [17]. Các tiêu chí để đọc kết quả xét nghiệm cũng cần được định nghĩa rõ ràng hơn, để chẩn đoán được chính xác và không thực hiện phẫu thuật khi không cần thiết [12]. Đây là điều chính có thể xảy ra sai sót: không phải bản thân xét nghiệm, mà là một chẩn đoán được đưa ra dựa trên một báo cáo chưa đầy đủ hoặc không rõ ràng.
Nếu bạn đã được tiêm steroid để điều trị hội chứng ống cổ tay, những thay đổi trong kết quả xét nghiệm sau mũi tiêm đó không có ý nghĩa đáng kể ở thời điểm hai năm [13]. Điều đó có nghĩa là mũi tiêm dường như không làm thay đổi những gì xét nghiệm cho thấy về lâu dài, vì vậy làm lại xét nghiệm sau khi tiêm vẫn sẽ phản ánh khá đúng tình trạng dây thần kinh của bạn.
Hãy đề nghị bác sĩ hoặc người thực hiện xét nghiệm giải thích báo cáo cho bạn. Một mô tả rõ ràng về những gì xét nghiệm phát hiện được, và ý nghĩa của những phát hiện đó, là một phần của một kết quả tốt.
Liệu phương pháp này có phù hợp với bạn không?
Nếu các triệu chứng của bạn gợi ý hội chứng ống cổ tay và phẫu thuật đang được tính đến, các xét nghiệm này thường là một phần của kế hoạch. Hầu hết các bác sĩ sẽ không phẫu thuật khi chưa có sự xác nhận này [3]. Việc làm thêm xét nghiệm có thể tăng khả năng phẫu thuật nhắm đúng vào một vấn đề thần kinh có thật và điều trị được [9]. Điều đó quan trọng, vì các xét nghiệm giúp chẩn đoán đúng và cho thấy mức độ chèn ép lên dây thần kinh của bạn nặng đến đâu [6].
Các xét nghiệm có thể ít hữu ích hơn nếu triệu chứng của bạn mơ hồ hoặc lúc có lúc không. Sự chèn ép lên dây thần kinh có thể không được phát hiện vào ngày làm xét nghiệm. Kết quả bình thường không loại trừ hội chứng ống cổ tay. Các xét nghiệm cũng không thể dự đoán bạn sẽ cảm thấy thế nào sau phẫu thuật, vì vậy đây là công cụ để chẩn đoán, chứ không phải một lời hứa về quá trình hồi phục của bạn [6].
Phương pháp thay thế chính là siêu âm, cũng có thể kiểm tra sự chèn ép lên dây thần kinh [9]. Bác sĩ có thể đề xuất một trong hai hoặc cả hai. Mỗi phương pháp có điểm mạnh riêng, và lựa chọn phù hợp phụ thuộc vào triệu chứng và kết quả thăm khám của bạn.
Đây nên là quyết định chung giữa bạn và bác sĩ. Hãy hỏi xem xét nghiệm dự kiến sẽ cho thấy điều gì, và điều gì sẽ xảy ra nếu kết quả bình thường. Nếu bạn có câu hỏi về rủi ro của bản thân xét nghiệm, hãy đọc phần nói về rủi ro ở trên.
Tóm lại
Nếu đang cân nhắc phẫu thuật cho hội chứng ống cổ tay, các xét nghiệm này đáng để thực hiện. Xét nghiệm xác nhận liệu dây thần kinh của bạn có thực sự bị chèn ép hay không và cho thấy mức độ nặng [6]. Việc làm thêm xét nghiệm có thể tăng khả năng phẫu thuật nhắm đúng vào một vấn đề có thật và điều trị được [9]. Hãy có kỳ vọng thực tế: các xét nghiệm làm tốt việc chẩn đoán, nhưng không thể dự đoán bạn sẽ cảm thấy thế nào sau phẫu thuật [6]. Lưu ý quan trọng nhất là kết quả bình thường không loại trừ hội chứng ống cổ tay, vì sự chèn ép lên dây thần kinh có thể lúc có lúc không. Hãy đề nghị được giải thích rõ ràng về báo cáo của bạn trước khi đưa ra bất kỳ quyết định nào.
Tài liệu tham khảo
[1] Sensory threshold and conductance testing in nerve injuries. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1986. DOI: 10.1016/0266-7681(86)90252-4
[2] Correlation of Clinical Signs with Nerve Conduction Tests in the Diagnosis of Carpal Tunnel Syndrome. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90244-5
[3] Current Practice in the Use of Nerve Conduction Studies in Carpal Tunnel Syndrome by Surgeons in the Netherlands. Journal of Hand Surgery (European Volume). 2007. DOI: 10.1016/j.jhse.2007.09.007
[4] Diagnosis of Ulnar Neuropathy at the Elbow Using Ultrasound — A Comparison to Electrophysiologic Studies. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.08.014
[5] Use of nerve conduction studies in carpal tunnel syndrome. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231191685
[6] Electrical studies as a prognostic factor in the surgical treatment of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80384-4
[7] Provocative motor nerve conduction testing in presumptive carpal tunnel syndrome unconfirmed by traditional electrodiagnostic testing. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(97)80045-7
[8] The utility of portable nerve conduction testing for patients with carpal tunnel syndrome: A prospective clinical study. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90117-8
[9] Diagnosis of Mild-to-moderate Idiopathic Median Neuropathy at the Carpal Tunnel Based on Signs and Symptoms is Discordant From Diagnosis Based on Electrodiagnostic Studies and Ultrasound. Clinical Orthopaedics & Related Research. 2023. DOI: 10.1097/corr.0000000000002751
[10] CORR Insights®: Diagnosis of Mild-to-moderate Idiopathic Median Neuropathy at the Carpal Tunnel Based on Signs and Symptoms is Discordant From Diagnosis Based on Electrodiagnostic Studies and Ultrasound. Clinical Orthopaedics & Related Research. 2023. DOI: 10.1097/corr.0000000000002822
[11] Electrodiagnostic reports of median neuropathy at the wrist. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80089-0
[12] Electrodiagnostic testing and carpal tunnel release outcome. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(05)80209-6
[13] Nerve Conduction Studies after Treatment for Carpal Tunnel Syndrome. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90191-4
[14] Diagnostic and therapeutic value of carpal tunnel injection. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80065-9
[15] Carpal Tunnel Syndrome: Neurophysiological Results of Surgery Based on Preoperative Electrodiagnostic Testing. Journal of Hand Surgery. 1997. DOI: 10.1016/s0266-7681(97)80355-5
[16] Relative slowing of the median antidromic sensory nerve conduction velocity to the ring finger in screening for carpal tunnel syndrome. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2004.04.026
[17] Electrodiagnostic testing in hand surgery. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80298-x
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Nerve conduction studies serve as a measure of impaired nerve function and are the best available indicator of overall disease severity with some prognostic value for surgical outcome [1].
- Nerve conduction studies are considered an indispensable part of the pre-operative evaluation for carpal tunnel syndrome [2].
- Provocative nerve conduction testing is a useful and simple addition to the overall evaluation of patients with carpal tunnel syndrome, particularly those with otherwise normal findings on traditional electrodiagnostic studies [3].
- The selection of an appropriate electrical screening test for peripheral nerve injury depends on the prevalence and seriousness of the target disease and the relative consequences of over- and underdiagnosis [4].
- The absence of any real difference in nerve conduction time between a working group with symptoms and a group with diagnosed carpal tunnel syndrome indicates a high probability that many participants with symptoms would have had abnormal findings on standard electrodiagnostic tests [5].
- The value of preoperative nerve conduction studies lies in obtaining the correct diagnosis and determining the severity of the median nerve disease, not in predicting postoperative outcome [6].
- Electrodiagnostic criteria used in some referenced studies were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in carpal tunnel syndrome [7].
- The value of electrodiagnostic testing is not negated by findings that it does not predict postoperative outcome [8].
- When signs and symptoms suggest mild-to-moderate median neuropathy and surgery is being considered, patients and clinicians might consider additional testing, such as electrodiagnostic studies or ultrasound, to increase the probability of actual median neuropathy that can benefit from surgery [9].
- Clinical, electrodiagnostic, and physical examination criteria need better definition to avoid inaccurate diagnoses and unnecessary surgeries [10].
- Highly sensitive tests are required to assess or exclude the diagnosis in one quarter of cases of carpal tunnel syndrome [11].
- Nerve conduction studies were more sensitive than sensibility testing in confirming the diagnosis of carpal tunnel syndrome [13].
- The combination of nerve conduction studies and sensibility testing is more sensitive than either test alone in confirming the diagnosis of carpal tunnel syndrome [13].
- Given specific clinical criteria for establishing the diagnosis of carpal tunnel syndrome, electrodiagnostic testing does not appear to correlate with improved final symptomatic outcome after carpal tunnel release [20].
- Surgical intervention is advocated for patients with symptoms only, even when electrodiagnostic studies are normal, in the context of cubital tunnel syndrome [21].
- The majority of neurosurgeons and orthopaedic surgeons seldom operate without electrodiagnostic confirmation in line with the Dutch consensus guideline on this subject [29].
- When used together, Semmes-Weinstein monofilament mappings and sensory nerve conduction parameters present a clearer picture of the patient's sensory status than either test used alone [31].
- Receiver operating characteristic curves showed distal sensory latency measurement to be a superior diagnostic test for carpal tunnel syndrome, with 3.3 ms as optimal upper limit of normal, giving a sensitivity of 74% and a specificity of 87% [45].
How It Works
Diagnostic Utility and Role
- The clinical, electrodiagnostic, and physical examination criteria need better definition to avoid inaccurate diagnoses and unnecessary surgeries [10].
- Electrodiagnostic studies are used as part of a clinical evaluation process and are considered a reasonable way to practice medicine [12].
Sensitivity and Specificity
- Nerve conduction studies were more sensitive than sensibility testing in confirming the diagnosis of carpal tunnel syndrome, but the combination of the two studies is more sensitive than either test alone [13].
- The sensitivity of the neurometer test alone was 69% and specificity was 100%, increasing to 84% sensitivity when combined with quantitative sensibility testing [28].
- The relative slowing of the antidromic sensory conduction velocity of the median nerve to the ring finger is determined easily and efficiently and imposes minimal strain on the patient [34].
Prognostic Value and Outcomes
- Compound muscle action potential amplitude, but not other conventional electrodiagnostic parameters, was predictive of functional outcomes after in situ decompression of the ulnar nerve [22].
- Suprascapular nerve dysfunction, evidenced by reduced nerve amplitudes and supraspinatus muscle atrophy, significantly predicts poor functional outcomes following shoulder hemiarthroplasty, even when tuberosities are well healed [19].
- This strength recovers gradually as the median nerve heals, but never returns to normal, indicating that this test can be extrapolated to the reinnervation of the abductor pollicies brevis [23].
Technical Considerations and Reporting
- There is variability with respect to the thoroughness of electrodiagnostic studies and in the quality of information in the reports [16].
- Electrodiagnostic reports should specifically indicate abnormalities of latency and conduction and present a clear description of the probable pathophysiologic processes rather than just compiling slight abnormalities [26].
- The conduction velocity of the ulnar nerve after an anterior transposition is determined by both the position of the elbow and the location for the measurement of the skin distance [37].
Physiological Mechanisms and Intraoperative Findings
- When in situ nerve strain reached 8.1 ± 0.5%, the compound muscle action potential was not evoked [33].
- Intraoperative conduction latencies indicated a dramatic and immediate reduction in the conduction latency across the carpal canal in all but seven patients, two of whom had diabetes [36].
- Electrodiagnostic studies revealed an acute median nerve lesion at the wrist with motor and/or sensory conduction blocks in 20/30 women with pregnancy-related carpal tunnel syndrome [18].
Comparative Modalities
- Ultrasound is a valid alternative confirmatory test compared with electrodiagnostic studies in detecting ulnar neuropathy at the elbow [14].
- The study confirms the high diagnostic value of the pre-operative antidromic sensory conduction velocity findings [25].
What the Evidence Shows
Diagnostic Role and Sensitivity
- The absence of any real difference in nerve conduction time between the working group with symptoms and the group with diagnosed carpal tunnel syndrome indicates a high probability that many participants with symptoms would have had abnormal findings on standard electrodiagnostic tests [5].
- There is a severe discordance between the estimated prevalence of mild-to-moderate carpal tunnel syndrome based on clinical signs and symptoms (73%) versus electrodiagnostic studies and ultrasound (51%) [27].
- The authors argue that the electrodiagnostic criteria used in the referenced study were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in carpal tunnel syndrome [7].
- Carpal tunnel injection is a reasonably accurate diagnostic test, as a good response to injection is an excellent diagnostic and prognostic sign for surgical treatment [42].
Prognostic Value and Outcomes
- Upper arm motor nerve conduction velocity might be a useful predictor of poor surgical outcome in cubital tunnel syndrome [32].
- Distal motor latency is a simple test with a predictive value of the postoperative neurophysiological and clinical outcome of carpal tunnel syndrome [39].
- The changes in electrophysiological findings occurring spontaneously in carpal tunnel syndrome and after treatment by injection are not statistically significant at two years [38].
Clinical Application and Reporting
- The author continues to use electrodiagnostic studies as part of a clinical evaluation process and considers this a reasonable way to practice medicine [12].
- The author proposes that the clinical, electrodiagnostic, and physical examination criteria need better definition to avoid inaccurate diagnoses and unnecessary surgeries [10].
- The study confirms the high diagnostic value of the pre-operative antidromic sensory conduction velocity findings in carpal tunnel syndrome [25].
- Surgical intervention is advocated for patients with symptoms only, even when electrodiagnostic studies are normal, in cases of cubital tunnel syndrome [21].
- The incidence of abnormal conduction times was not reliably correlated with either age or duration of paralysis in the paraplegic hand [24].
- In primates, there is no significant difference in the conduction velocity of peripheral nerves repaired in adults and those repaired in early life [15].
- Although there are essential differences between Semmes-Weinstein monofilament mappings and sensory nerve conduction parameters, when used together they present a clearer picture of the patient's sensory status than either test used alone [31].
- The strength of the abductor pollicis brevis recovers gradually as the median nerve heals but never returns to normal, indicating that this test can be extrapolated to the reinnervation of the abductor pollicis brevis [23].
- Chitosan phonophoresis demonstrated significant improvements in nerve conduction, pain reduction, and enhancement of hand function for mild to moderate cubital tunnel syndrome [17].
- All patients had good clinical and electrophysiological recovery at 6 months following single-stage opponensplasty added at the time of release for severe carpal tunnel syndrome [41].
- Three weeks after the operation, 77% of the patients in the tourniquet group had denervation in other than thenar muscles [46].
Practical Considerations
Diagnostic Interpretation and Utility
- Nerve conduction studies serve as a measure of impaired nerve function and the best available indicator of overall disease severity, rather than a test that determines the diagnosis [1].
- The value of preoperative nerve conduction studies lies in obtaining the correct diagnosis and determining the severity of median nerve disease, not in predicting postoperative outcome [6].
- Electrodiagnostic testing does not appear to correlate with improved final symptomatic outcome after carpal tunnel release given specific clinical criteria for establishing the diagnosis [20].
- When signs and symptoms suggest mild-to-moderate median neuropathy and surgery is being considered, patients and clinicians might consider additional testing, such as EDS or US, to increase the probability of actual median neuropathy that can benefit from surgery [9].
- The authors argue that the electrodiagnostic criteria used in the referenced study were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in CTS [7].
- This does not negate the value of electrodiagnostic testing [8].
Testing Variations and Screening
- Provocative nerve conduction testing is a useful and simple addition to the overall evaluation of patients with CTS, particularly those with otherwise normal findings on traditional electrodiagnostic studies [3].
- The absence of any real difference in nerve conduction time between the working group with symptoms and the group with diagnosed CTS indicates a high probability that many of the participants with symptoms would have had abnormal findings on standard electrodiagnostic tests [5].
- There is a significant discrepancy between the practice recommended by the Danish Society of Neurophysiology of performing neurophysiological investigations in all cases of suspected CTS and what is actually done in most surgical departments [35].
Specific Clinical Scenarios
- Upper arm motor nerve conduction velocity (MNCV) might be a useful predictor of poor surgical outcome in cubital tunnel syndrome [32].
- Surgical intervention is advocated for patients with symptoms only, even when electrodiagnostic studies are normal, in cases of electrodiagnostic-negative cubital tunnel syndrome [21].
- SSN dysfunction, evidenced by reduced nerve amplitudes and supraspinatus muscle atrophy, significantly predicts poor functional outcomes following shoulder hemiarthroplasty, even when tuberosities are well healed [19].
- The incidence of abnormal conduction times in the paraplegic hand was not reliably correlated with either age or duration of paralysis [24].
- Intraoperative electrodiagnosis may offer limited value in neonatal brachial plexus palsy surgery, but there is insufficient evidence to reach robust conclusions [44].
- This underscores the need for surgeons to carefully evaluate suprascapular nerve integrity in cases of rotator cuff tear [40].
Methodological and Prognostic Notes
- Only studies with randomization, blinding, and sham injection or sham surgery can address subjective symptoms and satisfaction reliably and accurately [30].
Key Evidence
- [L5] Nerve conduction studies should be understood not as a test that determines the diagnosis but as a measure of impaired nerve function, serving as the best available indicator of overall disease severity with some prognostic value for surgical outcome. [1] (10.1177/17531934231191685)
- [L3] We consider nerve conduction studies to be an indispensable part of the pre-operative evaluation. [2] (10.1016/0266-7681(94)90244-5)
- [L2] Provocative nerve conduction testing is a useful and simple addition to the overall evaluation of patients with CTS, particularly those with otherwise normal findings on traditional electrodiagnostic studies. [3] (10.1016/s0363-5023(97)80045-7)
- [L3] The selection of an appropriate electrical screening test for peripheral nerve injury, such as entrapment neuropathy, depends on the prevalence and seriousness of the target disease and the relative consequences of over- and underdiagnosis. [4] (10.1016/s0363-5023(96)80165-1)
- [L3] The absence of any real difference in nerve conduction time between the working group with symptoms and the group with diagnosed CTS indicates a high probability that many of the participants with symptoms would have had abnormal findings on standard electrodiagnostic tests. [5] (10.1016/0363-5023(92)90116-7)
- [L5] The value of preoperative nerve conduction studies lies in obtaining the correct diagnosis and determining the severity of the median nerve disease, not in predicting postoperative outcome. [6] (10.1016/s0363-5023(96)80384-4)
- [L5] The authors argue that the electrodiagnostic criteria used in the referenced study were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in CTS. [7] (10.1067/jhsu.2000.jjhsu00025a1le01)
- [L5] This does not negate the value of electrodiagnostic testing. [8] (10.1016/s0363-5023(96)80222-x)
- [L3] When signs and symptoms suggest mild-to-moderate median neuropathy and surgery is being considered, patients and clinicians might consider additional testing, such as EDS or US, to increase the probability of actual median neuropathy that can benefit from surgery. [9] (10.1097/corr.0000000000002751)
- [L5] The author proposes that the clinical, electrodiagnostic, and physical examination criteria need better definition to avoid inaccurate diagnoses and unnecessary surgeries. [10] (10.1016/s0363-5023(05)80209-6)
- [L3] Highly sensitive tests are required to assess or exclude the diagnosis in one quarter of cases of carpal tunnel syndrome. [11] (10.1016/0266-7681(94)90245-3)
- [L5] The author continues to use electrodiagnostic studies as part of a clinical evaluation process and considers this a reasonable way to practice medicine. [12] (10.1016/s0363-5023(96)80380-7)
- [L4] The results indicate that nerve conduction studies were more sensitive than sensibility testing in confirming the diagnosis of carpal tunnel syndrome, but the combination of the two studies is more sensitive than either test alone. [13] (10.1016/s0363-5023(82)80176-7)
- [L4] Ultrasound is a valid alternative confirmatory test compared with electrodiagnostic studies in detecting ulnar neuropathy at the elbow. [14] (10.1016/j.jhsa.2023.08.014)
- [L3] The study demonstrates that in primates there is no significant difference in the conduction velocity of peripheral nerves repaired in adults and those repaired in early life. [15] (10.1016/s0363-5023(83)80199-3)
- [L4] There is variability with respect to the thoroughness of electrodiagnostic studies and in the quality of information in the reports. [16] (10.1016/s0363-5023(98)80089-0)
- [L1] This approach demonstrated significant improvements in nerve conduction, pain reduction, and enhancement of hand function. [17] (10.1016/j.jht.2024.02.006)
- [L4] Electrodiagnostic studies revealed an acute median nerve lesion at the wrist with motor and/or sensory conduction blocks in 20/30 women. [18] (10.1016/s0266-7681(98)80232-5)
- [L3] SSN dysfunction, evidenced by reduced nerve amplitudes and supraspinatus muscle atrophy, significantly predicts poor functional outcomes following SHA, even when tuberosities are well healed. [19] (10.1016/j.jse.2025.07.001)
- [L3] Given specific clinical criteria for establishing the diagnosis of carpal tunnel syndrome, electrodiagnostic testing does not appear to correlate with improved final symptomatic outcome after carpal tunnel release. [20] (10.1016/s0363-5023(96)80164-x)
- [L2] We advocate surgical intervention for patients with symptoms only, even when electrodiagnostic studies are normal. [21] (10.1053/jhsu.2001.26327)
- [L2] Compound muscle action potential amplitude, but not other conventional electrodiagnostic parameters, was predictive of functional outcomes after in situ decompression of the ulnar nerve. [22] (10.1016/j.jhsa.2022.10.008)
- [L5] This strength recovers gradually as the median nerve heals, but never returns to normal, indicating that this test can be extrapolated to the reinnervation of the abductor pollicies brevis. [23] (10.1016/s0266-7681(03)00022-6)
- [L4] The incidence of abnormal conduction times was not reliably correlated with either age or duration of paralysis. [24] (10.1016/s0363-5023(88)80132-1)
- [L4] The study confirms the high diagnostic value of the pre-operative antidromic sensory conduction velocity findings. [25] (10.1016/0266-7681(88)90161-1)
- [L5] EDX reports should specifically indicate abnormalities of latency and conduction and present a clear description of the probable pathophysiologic processes rather than just compiling slight abnormalities. [26] (10.1016/s0363-5023(96)80298-x)
- [L5] There is a severe discordance between the estimated prevalence of mild-to-moderate carpal tunnel syndrome based on clinical signs and symptoms (73%) versus electrodiagnostic studies and ultrasound (51%), calling into question whether clinicians can confidently diagnose patients with mild-to-moderate CTS. [27] (10.1097/corr.0000000000002822)
- [L3] The sensitivity of the neurometer test alone was 69% and specificity was 100%, increasing to 84% sensitivity when combined with quantitative sensibility testing. [28] (10.1016/0363-5023(92)90117-8)
- [L4] The majority of neurosurgeons and orthopaedic surgeons seldom operate without electrodiagnostic confirmation in line with the Dutch consensus guideline on this subject. [29] (10.1016/j.jhse.2007.09.007)
- [L4] Although there are essential differences in these two tests, when used together they present a clearer picture of the patient's sensory status than either test used alone. [31] (10.1016/s0894-1130(87)80010-8)
- [L3] Upper arm motor nerve conduction velocity (MNCV) might be a useful predictor of poor surgical outcome. [32] (10.1177/17585732241293360)
- [Paper] The results showed that when the in situ nerve strain reached 8.1 ± 0.5%, the compound muscle action potential was not evoked. [33] (10.1016/s0736-0266(02)00080-3)
- [L3] The relative slowing of the antidromic sensory conduction velocity of the median nerve to the ring finger is determined easily and efficiently and imposes minimal strain on the patient. [34] (10.1016/j.jhsa.2004.04.026)
- [L4] There is a significant discrepancy between the practice recommended by the Danish Society of Neurophysiology of performing neurophysiological investigations (NI) in all cases of suspected CTS and what is actually done in most surgical departments. [35] (10.1016/s0266-7681(97)80443-3)
- [L4] The results of intraoperative conduction latencies indicated a dramatic and immediate reduction in the conduction latency across the carpal canal in all but seven patients, two of whom had diabetes. [36] (10.1016/s0363-5023(78)80119-1)
- [L4] The conduction velocity of the ulnar nerve after an anterior transposition is determined by both the position of the elbow and the location for the measurement of the skin distance. [37] (10.1016/s0363-5023(87)80051-5)
- [L3] The changes in electrophysiological findings occurring spontaneously in carpal tunnel syndrome and after treatment by injection are not statistically significant at two years. [38] (10.1016/0266-7681(92)90191-4)
- [L3] DML is a simple test with a predictive value of the postoperative neurophysiological and clinical outcome of carpal tunnel syndrome. [39] (10.1016/s0266-7681(97)80355-5)
- [L5] This underscores the need for surgeons to carefully evaluate suprascapular nerve integrity in such cases. [40] (10.1186/s12891-025-09195-6)
- [L3] All patients had good clinical and electrophysiological recovery at 6 months. [41] (10.1177/1558944716660555fx)
- [L4] Results suggest that carpal tunnel injection is also a reasonably accurate diagnostic test, as a good response to injection is an excellent diagnostic and prognostic sign for surgical treatment. [42] (10.1016/s0363-5023(84)80065-9)
- [L4] Intraoperative electrodiagnosis may offer limited value in neonatal brachial plexus palsy surgery, but there is insufficient evidence to reach robust conclusions. [44] (10.1177/17531934261478357)
- [L3] Receiver operating characteristic curves showed distal sensory latency measurement to be a superior diagnostic test, with 3.3 ms as optimal upper limit of normal, giving a sensitivity of 74% and a specificity of 87%. [45] (10.1016/s0363-5023(96)80020-7)
- [L1] Three weeks after the operation 77% of the patients in the tourniquet group had denervation in other than thenar muscles. [46] (10.1016/s0363-5023(89)80011-5)
References
[1] Use of nerve conduction studies in carpal tunnel syndrome. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231191685
[2] Correlation of Clinical Signs with Nerve Conduction Tests in the Diagnosis of Carpal Tunnel Syndrome. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90244-5
[3] Provocative motor nerve conduction testing in presumptive carpal tunnel syndrome unconfirmed by traditional electrodiagnostic testing. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(97)80045-7
[4] A comparison of traditional electrodiagnostic studies, electroneurometry, and vibrometry in the diagnosis of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80165-1
[5] Use of motor nerve conduction testing and vibration sensitivity testing as screening tools for carpal tunnel syndrome in industry. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90116-7
[6] Electrical studies as a prognostic factor in the surgical treatment of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80384-4
[7] Diagnostic testing in carpal tunnel syndrome. The Journal of Hand Surgery. 2000. DOI: 10.1067/jhsu.2000.jjhsu00025a1le01
[8] Electrical studies as a prognostic factor in carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80222-x
[9] Diagnosis of Mild-to-moderate Idiopathic Median Neuropathy at the Carpal Tunnel Based on Signs and Symptoms is Discordant From Diagnosis Based on Electrodiagnostic Studies and Ultrasound. Clinical Orthopaedics & Related Research. 2023. DOI: 10.1097/corr.0000000000002751
[10] Electrodiagnostic testing and carpal tunnel release outcome. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(05)80209-6
[11] Sensitivity of the Various Tests for the Diagnosis of Carpal Tunnel Syndrome. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90245-3
[12] Electrical studies as a prognostic factor in the surgical treatment of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80380-7
[13] Nerve conduction studies and sensibility testing in carpal tunnel syndrome. The Journal of Hand Surgery. 1982. DOI: 10.1016/s0363-5023(82)80176-7
[14] Diagnosis of Ulnar Neuropathy at the Elbow Using Ultrasound — A Comparison to Electrophysiologic Studies. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.08.014
[15] Nerve conduction velocity, microscopic, and electron microscopy studies comparing repaired adult and baby monkey median nerves. The Journal of Hand Surgery. 1983. DOI: 10.1016/s0363-5023(83)80199-3
[16] Electrodiagnostic reports of median neuropathy at the wrist. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80089-0
[17] Effectiveness of chitosan phonophoresis on ulnar nerve conduction velocity, pain relief, and functional outcomes for mild to moderate cubital tunnel syndrome: A double-blind randomized controlled trial. Journal of Hand Therapy. 2024. DOI: 10.1016/j.jht.2024.02.006
[18] Pregnancy-Related Carpal Tunnel Syndrome. Journal of Hand Surgery. 1998. DOI: 10.1016/s0266-7681(98)80232-5
[19] Radiological and electrodiagnostic insights into suprascapular nerve dysfunction: a key predictor of poor functional outcomes in shoulder hemiarthroplasty. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2025.07.001
[20] Electrodiagnostic testing and carpal tunnel release outcome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80164-x
[21] The rationale for and efficacy of surgical intervention for electrodiagnostic-negative cubital tunnel syndrome. The Journal of Hand Surgery. 2001. DOI: 10.1053/jhsu.2001.26327
[22] Electrodiagnostic Predictors of Outcomes After In Situ Decompression of the Ulnar Nerve. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2022.10.008
[23] Re. Clinical value of electrodiagnostic testing following repair of peripheral nerve lesions: a prospective study. Th. H.J. Van de Kar, J.B. Jaquet, J. Meulstee, C.B.H. Molenaar, R.J. Schimsheimer, S.E.R. Hovius. Journal of Hand Surgery 2002: 27B(4): 345–349.. Journal of Hand Surgery. 2003. DOI: 10.1016/s0266-7681(03)00022-6
[24] The paraplegic hand: Electrodiagnostic studies and clinical findings. The Journal of Hand Surgery. 1988. DOI: 10.1016/s0363-5023(88)80132-1
[25] Assessment of sensory nerve conduction in carpal tunnel syndrome before, during and after operation. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90161-1
[26] Electrodiagnostic testing in hand surgery. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80298-x
[27] CORR Insights®: Diagnosis of Mild-to-moderate Idiopathic Median Neuropathy at the Carpal Tunnel Based on Signs and Symptoms is Discordant From Diagnosis Based on Electrodiagnostic Studies and Ultrasound. Clinical Orthopaedics & Related Research. 2023. DOI: 10.1097/corr.0000000000002822
[28] The utility of portable nerve conduction testing for patients with carpal tunnel syndrome: A prospective clinical study. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90117-8
[29] Current Practice in the Use of Nerve Conduction Studies in Carpal Tunnel Syndrome by Surgeons in the Netherlands. Journal of Hand Surgery (European Volume). 2007. DOI: 10.1016/j.jhse.2007.09.007
[30] Probability_and_Pathophysiology_S0363502312002821. 2002.
[31] Correlating Semmes-Weinstein monofilament mappings with sensory nerve conduction parameters in Hansen's disease patients: An update. Journal of Hand Therapy. 1987. DOI: 10.1016/s0894-1130(87)80010-8
[32] Clinical significance of upper arm motor nerve conduction velocity in cubital tunnel syndrome. Shoulder & Elbow. 2024. DOI: 10.1177/17585732241293360
[33] In situ strain and stress of nerve conduction blocking in the brachial plexus. Journal of Orthopaedic Research. 2002. DOI: 10.1016/s0736-0266(02)00080-3
[34] Relative slowing of the median antidromic sensory nerve conduction velocity to the ring finger in screening for carpal tunnel syndrome. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2004.04.026
[35] Operative Treatment of Carpal Tunnel Syndrome in Denmark. Journal of Hand Surgery. 1997. DOI: 10.1016/s0266-7681(97)80443-3
[36] Intraoperative changes in motor nerve conduction latency in carpal tunnel syndrome. The Journal of Hand Surgery. 1978. DOI: 10.1016/s0363-5023(78)80119-1
[37] Validity of nerve conduction velocity studies after anterior transposition of the ulnar nerve. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80051-5
[38] Nerve Conduction Studies after Treatment for Carpal Tunnel Syndrome. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90191-4
[39] Carpal Tunnel Syndrome: Neurophysiological Results of Surgery Based on Preoperative Electrodiagnostic Testing. Journal of Hand Surgery. 1997. DOI: 10.1016/s0266-7681(97)80355-5
[40] Electromyography does not show adequate effectiveness in diagnosis of suprascapular nerve lesions caused by rotator cuff tear in rat model. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-09195-6
[41] Should Single-Stage Opponensplasty Be Added at the Time of Release for Severe Carpal Tunnel Syndrome?. HAND. 2016. DOI: 10.1177/1558944716660555fx
[42] Diagnostic and therapeutic value of carpal tunnel injection. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80065-9
[44] Intraoperative electrodiagnostic testing as a decision-making tool for neonatal brachial plexus palsy: a scoping review. Journal of Hand Surgery (European Volume). 2026. DOI: 10.1177/17531934261478357
[45] Evaluation of portable nerve conduction testing in the diagnosis of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80020-7
[46] Upper extremity tourniquet effects in carpal tunnel release. The Journal of Hand Surgery. 1989. DOI: 10.1016/s0363-5023(89)80011-5