Clinicians › Shoulder
Pectoralis Major Rupture
Pectoralis major tendon rupture and repair (corpus-synthesised).
For patients: a plain-language version of this topic is available. See the patient guide.
Overview
Pectoralis major rupture is a condition that likely occurs with greater frequency than current reports indicate [1]. The majority of these injuries occur at the myotendinous junction [5], while full-thickness ruptures of the muscle belly remain rare [7]. Although no previous reports existed for women in the specific age group described in a 2019 case report [4], the incidence among National Football League players has risen drastically, from 10 cases between 2000 and 2010 to 55 cases from 2010 to 2017 [11]. Clinicians should assess for pectoralis major rupture in traumatic first-time dislocations to avoid missed diagnosis [3].
Surgical repair is the treatment of choice for complete acute ruptures of the pectoralis major tendon or muscle in athletes [17], particularly for active patients who require maximum strength in vocational or avocational activities [28]. Complete ruptures should be treated operatively as early as possible to achieve full strength restoration [9], as early anatomic repair yields the best results for total and near-total ruptures [10]. Patients treated operatively for acute or chronic ruptures fared significantly better than those treated nonoperatively [8], with no statistically significant difference in outcomes between acute and chronic operative groups [8]. Surgical repair provides superior outcomes compared to conservative treatment in regaining strength and functional outcome [2], a finding supported by tendon repair studies [16, 25] and Bak criteria assessments in athletes [19].
Surgical repair of pectoralis major tendon ruptures is performed safely with a low re-rupture rate and low risk of complications [18], though the procedure is associated with a 14.21% complication rate [16, 25]. In the largest study to date, 94% of patients returned to full military duty after primary repair, while 5.8% experienced re-rupture [30]. Pectoralis major repair results in a high rate of return to work (97.8%) with a mean time to return of 1.6 months [20]. Early surgical repair of distal tendon ruptures combined with an accelerated rehabilitation protocol provides reliable restoration of shoulder function and strength, allowing an early return to sports and functional activity [31]. Full-thickness ruptures of the muscle belly have been treated surgically with good to excellent results [7], and repair has been successfully performed 13 years after the initial injury [6].
Anatomy & Pathophysiology
Muscle Architecture and Insertion
The pectoralis major is an intrinsic muscle that controls the glenohumeral joint [69]. It consists of an unsegmented clavicular head and upper and lower sternal heads comprising 6 to 7 segments [131]. The tendon forms from anterior and posterior layers that fuse laterally to insert on the lateral ridge of the intertubercular groove of the humerus [131]. The clavicular and upper sternal head segments contribute to the anterior tendon layer, coursing inferolaterally, while the lower sternal head segments form the posterior layer, coursing superolaterally [131]. Although there is no twisting at the muscular or tendinous layers, the contributing segments are wider medially and narrower laterally in a splayed-out orientation [131]. The muscle inserts on the humeral shaft, displacing it medially [56]. Due to its anterior tendinous insertion onto the lateral wall of the bicipital groove, the pectoralis major powers adduction and internal rotation [63]. It also forms the roof of the distal continuation of the bicipital tunnel, a closed space extending proximally to the glenohumeral joint [63]. A soft tissue sheath consistently covers the long head of the biceps tendon to the proximal margin of the pectoralis major tendon, contributing to the roof of this tunnel [60].
Mechanism of Injury and Pathophysiology
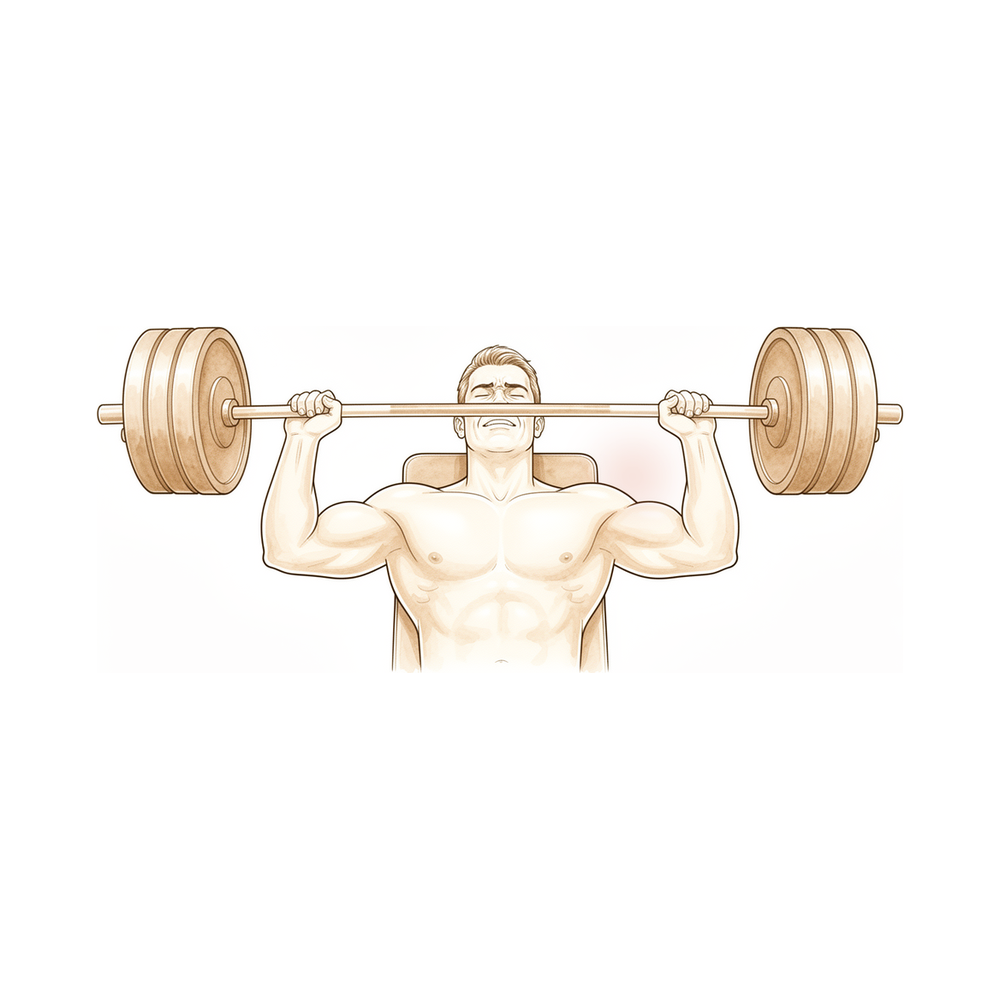
The mechanism of injury is most commonly indirect, involving a sudden forceful overload of a maximally contracted muscle [33]. This typically occurs with the shoulder abducted and externally rotated, such as in the bench press position [23]. In this position, the inferior sternal head fibers are under particular tensile stress [23]. Tears most commonly begin in the lower sternal head, where fibers are shortest and placed in maximal stretch when the shoulder is in abduction, external rotation, and extension [131]. These inferior muscular segments have a mechanical disadvantage at the end of the eccentric phase when maximally stretched, causing them to respond disproportionately and become susceptible to rupture under high loads [23]. Significantly heavy and often eccentric loads can propagate the tear proximally to varying degrees [131]. Propagation to a complete tear can occur with ongoing or excessive load [23]. In most patients, the site of the tear is at either the myotendinous junction or the tendinous insertion [33]. Rupture is presumed to be caused by trauma to a normal tendon, as attrition from rubbing over bone and degeneration preceding rupture do not usually occur [93]. The pectoralis major contributes most to the readily identifiable curved muscle bulk of the anterior axillary contour [23].
Clinical Presentation and Physical Findings
Patients usually present with ecchymosis and swelling about the shoulder, along with pain and weakness in adduction and internal rotation of the arm [33]. Pochini et al described the ‘‘S’’ sign to characterize the defect in the appearance of the axillary fold [23]. Chronic tears may present with ‘‘webbing,’’ an accentuation of the inferior border of the deltoid [23]. Hematoma may fill the gap in the anterior axillary fold, allowing the defect to be visible only when the arm is fully abducted or adducted [23]. In acute tears, hematoma and edema can contribute to the so-called ‘‘dropped nipple,’’ where the ipsilateral nipple sits and points more downward [23]. None of the previously described physical examination features reported with pectoralis major injury are quantifiable, nor are they always reliable [23].
Imaging Findings
Plain radiographs may reveal nonspecific soft-tissue swelling and loss of the pectorals major shadow [26]. Under ultrasonography, normal muscle tissue is hypoechoic with intervening hyperechoic connective tissue [26]. Immediately postinjury hemorrhage is hypoechoic, but with hematoma formation, it becomes heterogeneously echoic [26]. Hematoma formation leads to the formation of a potential space between the deltopectoral groove and coracobrachialis muscle formed by the retracted tendon [26]. Acute pectoralis major rupture results in abnormal T2 signal intensity in a portion of the muscle, musculotendinous junction, or tendon itself with a partial or complete loss of structural continuity [26]. The loss of structural continuity in acute pectoralis major rupture is most often identified on axial MRI sequences [26].
Classification
Contemporary Injury Classification: A contemporary system categorizes pectoralis major tears based on injury timing, injury location, and standardized terminology addressing tear extent [121]. This approach classifies tendon tears as full- or partial-thickness and full- or partial-width, which more accurately characterizes the degree of pathology and helps guide clinical management [27].
Alternate Classification (Tendon Segment Crossing): An alternate classification based on the crossing of tendon segments suggests that lesions Pp-I cannot involve only the inferior part of the posterior layer [32]. Surgical recommendations for this specific classification system are yet to be established [32].
Isolated Sternocostal Head Classification: A new classification has been proposed specifically for isolated tears of the sternocostal head [94].
Other Considerations: The majority of pectoralis major tears occur at the myotendinous junction [5, 22]. In the indirect mechanism of injury, inferior sternal head fibers are under particular tensile stress and are more prone to rupture [23]. The inferior muscular segments have a mechanical disadvantage at the end of the eccentric phase when their fibers are maximally stretched, making them susceptible to rupture under high loads [23]. These segments contribute most to the readily identifiable curved muscle bulk of the anterior axillary contour [23].
Clinical presentation varies by chronicity. The 'S' sign characterizes a defect in the appearance of the axillary fold [23]. Chronic tears may present with 'webbing,' defined as an accentuation of the inferior border of the deltoid [23]. In acute tears, hematoma and edema can contribute to the 'dropped nipple,' where the ipsilateral nipple sits and points more downward [23]. Type IIIC pectoralis major muscle ruptures are repaired using direct suturing of tendon ends [126].
Clinical Presentation
History and Mechanism
The mechanism of injury for pectoralis major rupture is most commonly indirect, occurring with the shoulder abducted and externally rotated, such as in the bench press position [23]. This injury is usually associated with trauma and is commonly secondary to a sudden forceful overload of a maximally contracted muscle [33]. Patients frequently report a sudden pain at the medial aspect of the upper arm associated with a felt "pop" [34]. In athletic populations, pectoralis muscle injuries are most frequently non-contact injuries, most commonly sustained by pitchers [50].
Physical Examination Findings
Physical examination is the most important component of recognizing the tear, as imaging studies are often unclear or variable [46]. Patients typically present with ecchymosis and swelling about the shoulder, along with pain and weakness in adduction and internal rotation of the arm [33]. Loss of the anterior axillary fold with an asymmetric muscle outline that is retracted medially is a useful diagnostic feature [34]. The absence of the anterior axillary fold can be accentuated by abducting the affected arm or with resisted adduction [34].
Specific clinical signs vary by the chronicity of the injury. In acute tears, hematoma and edema can contribute to the "dropped nipple" sign, where the ipsilateral nipple sits and points more downward [23]. Chronic tears may present with "webbing," characterized by an accentuation of the inferior border of the deltoid [23]. The "S" sign characterizes a defect in the appearance of the axillary fold [23]. The Cruciform Test is a simple and reproducible diagnostic tool that has potential as a clinical indicator of both pectoralis major rupture and successful repair [47]. Testing the power of the muscle is helpful for documentation purposes and as a baseline for comparison after any intervention [34].
Anatomical Location of Injury
The inferior sternal head fibers are under particular tensile stress and are more prone to rupture during the mechanism of injury [23].
Complications and Associated Findings
Rupture of the pectoralis major muscle can result in ossification within the muscle, presenting as a tender lump [14]. A haematoma following a partial rupture can become infected, causing problems with diagnosis [15]. Compartment syndrome secondary to acute pectoralis major tendon rupture is a possible complication [39]. Pectoralis major rupture can occur concomitantly with anterior shoulder dislocation and Bankart lesion [3]. Additionally, pectoralis major rupture can occur in combination with posterior labral injury in young athletes who experience high-energy trauma to the shoulder [12].
Investigations
Clinical Examination
Prior to the description of the Pectoralis Major Index, no quantifiable and validated clinical diagnostic test existed for structurally significant pectoralis major ruptures [23]. The Pectoralis Major Index now allows clinicians to accurately and confidently identify such ruptures [23]. Physical examination may reveal the "S" sign, which characterizes a defect in the appearance of the axillary fold associated with pectoralis major injury [23]. In acute tears, hematoma and edema can contribute to the "dropped nipple" sign, where the ipsilateral nipple sits and points more downward [23].
Imaging
Plain radiography: Standardized plain films are almost always sufficient for shoulder evaluation, and the temptation to "overimage" should be resisted [45]. The purpose of imaging is to establish the diagnosis, determine pathoanatomy severity, assist in surgical planning, and illustrate the condition to the patient [45]. At least two views are required: an anteroposterior (AP) view in the plane of the glenoid and an axillary projection with the arm in abduction [73]. The standard shoulder series includes orthogonal views: a true AP view in the scapular plane, an AP view, an axillary view, and a scapular Y view [81]. The true AP view visualizes the anterior greater tuberosity in profile and can reveal proximal humeral migration [81]. The AP view with the arm in internal rotation visualizes the posterior aspect of the greater tuberosity and the lesser tuberosity in profile [81]. The axillary view is necessary for evaluating glenohumeral joint instability and determining humeral head position within the glenoid fossa [81]. The scapular Y view provides visualization of the coracoacromial arch and can reveal coracoacromial spurs [81]. Normal acromiohumeral distance is 7 to 14 mm, and the glenohumeral joint space should be symmetric superiorly and inferiorly [81]. The coracoclavicular distance is normally 1.1 to 1.3 cm [81].
For patients presenting with shoulder instability and dislocations, initial imaging with standard radiographs provides an overview of bony anatomy and assesses for bony Bankart and Hill-Sachs lesions [83]. If the patient can abduct the arm, an axillary view must be obtained to evaluate for anterior or posterior humeral head subluxation or dislocation [83]. If abduction is impossible due to injury acuity, a scapular "Y" view must be obtained to evaluate the relationship of the humeral head to the glenoid [83]. In a systematic review of posterior shoulder dislocations, 73% of patients had a missed initial diagnosis due to the lack of an axillary view, Y view, or computed tomography imaging [83]. Of 150 patients with missed initial diagnoses of posterior dislocation, 98% had only AP or lateral views [83]. When axillary or Y-view radiographs were subsequently obtained in patients with suspected posterior dislocation, the diagnosis was confirmed in 100% of patients [83]. Special radiographic views assist in identifying pathology related to shoulder instability, including the Stryker Notch, West Point, and Bernageau profile views [83]. The Stryker notch view evaluates for Hill-Sachs lesions after dislocation [81]. The West Point view evaluates anterior glenoid bone loss [81]. The Zanca view evaluates the acromioclavicular joint [81]. The apical oblique view evaluates for glenoid rim fracture in instability [81]. The serendipity view evaluates the sternoclavicular joint [81].
The first key view for shoulder imaging is the AP view in the plane of the scapula, taken so the x-ray beam passes through the glenohumeral joint [45]. This view shows the superoinferior position of the humeral head relative to the glenoid, presence of osteophytes, joint space narrowing, degree of medial displacement of the humerus, bone quality, presence of loose bodies, and whether there is humeral head collapse or deformity [45]. The second key view is the axillary view taken with the arm in the functional position of elevation in the plane of the scapula [45]. This view shows a different perspective of humeral anatomy, amount of glenoid bone, shape of the glenoid, its version in relation to the plane of the scapula, and the relationship of the humeral head to the glenoid fossa [45]. The axillary view is referred to as the "truth view" because it demonstrates glenohumeral relationships in the functional position of elevation [45]. Many "axillary views" sent for consultation are taken without standardization, making it impossible to determine important features of the glenohumeral joint [45]. When taken properly, standardized AP and axillary views indicate cartilage space thickness, relative positions of the humeral head and glenoid, presence of osteophytes, degree of osteopenia, and extent of bony deformity and erosion [45]. Joint space narrowing is most evident on the axillary truth view compared to images made with the arm at the side [45]. The axillary truth view can show posterior subluxation or "functional decentering" that is not evident in images taken with the arm at the side [45]. The degree of posterior subluxation can be measured by the position of the center of the humeral head in relation to the plane of the scapula, the position of the center of the humeral head in relation to the glenoid face, or the point of contact of the humeral articular surface on the glenoid articular surface [45]. The point of contact reflects the degree of centering of the net humeral joint reaction force on the glenoid [45]. Malcentering of the joint reaction force leads to posterior instability, posterior glenoid wear, and "rocking horse" loosening of prosthetic glenoid components [45].
The shoulder is a three-dimensional structure that cannot be represented by a single planar view [75]. Critical relationships, such as the degree of centering of the humeral head, change with the position of the arm [75]. Shoulder pathology may be found in a large number of different bones and soft tissues [75]. Overlying and superimposed structures as well as metallic implants may complicate imaging the structures of interest [75]. Surgeons need to develop a judicious approach to imaging that yields necessary information while avoiding the tendency to "over-image" [75]. It is possible to spend a lot of time, money, and radiation dosage on imaging [75]. Initially, all patients are usually asked to have AP and lateral plain radiographs of the shoulder related to their chief report [79]. Plain radiographs are often the only required studies needed for assessing acute shoulder trauma, including fractures or dislocations [79]. Arthritis, calcific tendinitis, and osteolysis of the distal clavicle can be observed on plain radiograph [79].
MRI: MRI is accurate for diagnosing the tear grade and location of pectoralis major tendon ruptures, particularly for acute, tendon-bone, and G3 tears [36]. Axial T2-weighted MRI of the shoulder and chest can show a complete tear of the pectoralis major tendon [81]. Classifying pectoralis tendon tears as full- or partial-thickness and full- or partial-width helps guide the most appropriate clinical management [27]. Discrepancies exist between intraoperative and radiographic assessments of pectoralis major tears [5]. MRI appeared to be less sensitive and specific than previous reports for traumatic pectoralis major tendon injuries in an active duty military cohort [134].
Magnetic resonance imaging is useful to identify osteonecrosis of the humeral head, bone tumours, labral tears, and rotator cuff tears [73]. MRI is the modality of choice for evaluating the rotator cuff, biceps, and subacromial/subdeltoid bursa [79]. T1-weighted MRI can reveal Hill-Sachs lesions and is often used with magnetic resonance arthrograms to provide a more detailed picture of the joint surfaces [79]. T2-weighted MRI provides better visualization of full thickness rotator cuff tears [79]. Magnetic resonance imaging accuracy in identifying labral and rotator cuff tears in the literature ranges from 70% to 100% [77].
MR Arthrography: MR arthrography is considered the benchmark for evaluation for labral tears and rarely is indicated for evaluation of rotator cuff pathology [79]. MR arthrography increases both sensitivity and specificity in detecting injuries to the capsulolabral–ligamentous complex as compared to traditional MRI [77]. In a meta-analysis of 4,667 shoulders, MRA had greater diagnostic test accuracy for glenoid labral lesions than MRI, with MRA sensitivity of 88% and specificity of 93% versus MRI sensitivity of 76% and specificity of 87% [77]. Abduction and external rotation (ABER) of the arm is an alternative position utilized to increase the sensitivity and specificity for detecting anteroinferior labroligamentous injury [77]. Limited range of motion or pain may prohibit patients from performing the ABER provocative maneuver [77]. In a retrospective comparison, full routine MRI or MRA examination had similar accuracy as the ABER sequence in evaluating the anteroinferior labral–ligamentous complex [77]. In a study evaluating the added value of the ABER position, the sensitivity of MRA with the ABER position for detecting anteroinferior labral lesions was significantly higher than that of MRA in neutral position [77]. MRAs can demonstrate a patulous capsule on the coronal, sagittal, and axial imaging in patients with multidirectional instability [77]. The diagnosis of multidirectional instability is a clinical one, and the need for expensive and/or invasive imaging should be weighed against the information that will be gained from these studies [77]. When MRI or MR arthrography is contraindicated, CT arthrography is indicated [79].
CT: Computed tomography is helpful for planning fracture surgery and shoulder joint replacement [73]. CT imaging is frequently used to evaluate fractures of the shoulder, to assess for bony lesions in recurrent instability cases, or for preoperative templating for shoulder arthritis [79]. CT with three-dimensional reconstructions is the advanced imaging study of choice for determining the extent of glenoid bone loss in the setting of shoulder instability [81]. Although CT scans may offer a few degrees of increased precision in the measurement of glenoid version, this precision does not improve the quality of the surgery or the clinical outcome [45]. CT scans have the disadvantage of being taken with the arm in the adducted position [45]. Three-dimensional reconstructions can reveal fine details of the shoulder anatomy, but this additional information rarely changes the planning or conduct of the arthroplasty [45].
Ultrasonography: Ultrasonography is a low-cost alternative to MRI and arthrography for evaluating soft-tissue structures of the shoulder [79]. Ultrasonography can provide immediate, real-time visualization of the rotator cuff, biceps tendon, and calcific deposits [79]. Ultrasonography is a simple and accurate test for identifying rotator cuff tears and calcific tendinitis [73]. Ultrasonography is highly operator dependent and is not as useful for evaluating labral tears or rotator cuff tears that are very small or larger than 3 cm [79]. The most commonly performed joint examination using ultrasonography is the shoulder examination [71]. Accuracy of ultrasonography depends on the skill of the scanner operator and an awareness of pitfalls that are encountered [71]. Ultrasonography can pick up on partial tears that may need treatment but have normal physical examination findings [71]. Dynamic ultrasonographic evaluation is important for zone II partial flexor tendon lacerations due to the ability to move the tendon [71]. Ultrasonography is a dynamic tool for usual and unusual disorders [71]. Ultrasonography of the shoulder with arthroscopic correlation has been described [71]. Pitfalls, limitations, and artifacts in ultrasonography of the rotator cuff have been described [71]. Musculoskeletal sonography is an important complementary or alternative technique to MRI [71]. Ultrasonography-guided biceps tendon sheath injection has a spectrum of preprocedure appearances [71]. Ultrasonography-guided percutaneous treatment of rotator cuff calcific tendonitis has been described [71]. One hundred forty-seven patients with rotator cuff calcific tendinitis were treated with ultrasonography-guided lavage, resulting in significant reduction of symptoms in 70% of shoulders [71]. Patients aged 30 to 40 years had more significant improvement with ultrasonography-guided lavage for rotator cuff calcific tendinitis [71]. Calcifications that were softer and middle-sized (12 to 17 mm) had more significant improvement with ultrasonography-guided lavage for rotator cuff calcific tendinitis [71]. Ultrasonography can be used to measure the subacromial space and detect atrophy of rotator cuff muscles [79]. Ultrasonography can evaluate impingement in various positions and motions due to providing images in real-time [79].
Arthroscopy: Arthroscopy is useful for diagnosing and treating subacromial impingement, intra-articular lesions, detachment of the glenoid labrum, and rotator cuff tears [73].
Other Considerations: Proper radiographic technique is as important as proper surgical technique to achieve the desired outcome [45]. Unless a specific research protocol is in place, the temptation to "overimage" should be resisted, obtaining only the scans or reconstructions that are necessary for the care of the patient [45]. The Multicenter Orthopaedic Outcomes Network (MOON) Shoulder Group was formed to conduct large multicenter studies on conditions of the shoulder [72]. The MOON Shoulder Group is made up of 16 fellowship-trained orthopaedic surgeons and research personnel from nine academic and private practice sites in the United States [72]. The MOON Shoulder Group initially was formed to identify research questions related to treatment of rotator cuff disease but has expanded its scope to include other shoulder pathology [72]. To study rotator cuff disease, the MOON Shoulder Group developed and standardized imaging protocols, assembled validated patient-oriented outcome forms, and conducted validation studies on the classification of rotator cuff tears based on MRI and arthroscopy videotapes as well as radiographic findings associated with rotator cuff disease [72]. After a systematic review to determine the effectiveness of physical therapy for management of rotator cuff disease, a standard physical therapy protocol was developed based on the evidence [72]. This process led to a prospective study of nonsurgical management of atraumatic full-thickness rotator cuff tears in a population of patients with symptoms, fewer than 25% of whom underwent surgery within the next 2 years [72]. Subsequent studies found that duration of symptoms, pain, and activity level were not correlated with the severity of rotator cuff disease in this population [72]. MOON Shoulder Instability is an offshoot of MOON Shoulder, focusing on patients undergoing surgical treatment for shoulder instability [72]. Early studies have described baseline demographics and modifying factors in patients undergoing surgical treatment for shoulder instability [72]. Limited early outcomes have been described in patients undergoing surgical treatment for shoulder instability [72].
Treatment
Non-Operative
Nonsurgical management is recommended only for proximal tears and elderly, sedentary patients [33]. In a patient with the clinical diagnosis of rupture of the pectoralis major, surgical repair will give the best results in terms of regaining strength and functional outcome [2].
Operative
Indications: For all other complete tears, surgery is advocated to return the patient to full strength and function and to reduce cosmetic deformity [33]. Surgical repair of pectoralis major tendon tears resulted in significantly superior outcomes compared with nonoperative treatment [16]. Early surgical repair of distal pectoralis major tendon ruptures allows an early return to sports and functional activity [31].
Surgical Approach / Technique: Pectoralis major tendon repair is an effective treatment that results in a high rate of return to sport and work, pain relief, and improved cosmetic appearance [96]. Acute repair of pectoralis major tendon tears resulted in significantly superior functional outcomes and cosmesis satisfaction compared to delayed repair [42]. Acute repair of pectoralis major tendon tears showed a trend toward a higher proportion of patients who were pain-free [42]. Early surgical repair of distal pectoralis major tendon ruptures and an accelerated rehabilitation protocol provide reliable restoration of shoulder function and strength [31]. Repair of the pectoralis major tendon ruptures using intramedullary suture anchors has high rates of return to duty, patient satisfaction, and patient-reported outcomes [49]. The authors recommend their preferred technique for pectoralis major repair as it provides a reproducible and reliable anatomic repair with positive clinical outcomes [40]. The authors describe a safe and reproducible technique for acute pectoralis major reconstruction with semitendinosus augmentation [106].
Delayed and Salvage Procedures: Delayed surgical repair of pectoralis major ruptures is technically feasible [54]. The use of fascial allograft to augment the repair can successfully treat chronic ruptures without compromising the final result [54]. Full-thickness ruptures of the pectoralis major muscle belly are rare and have been treated surgically with good to excellent results reported [7]. As a salvage procedure, the pectoralis major tendon transfer provides good results in most cases [53]. Pectoralis major transfer results in improvement for patients with an irreparable subscapularis tear with or without an associated reparable supraspinatus tear [51]. Pectoralis major transfer is a reliable treatment option for irreparable anterosuperior rotator cuff injuries with significant improvement in pain and function [114].
Other Considerations: Pectoralis major tendon repair is associated with a significant rate of complication [96].
Complications
Wound complications: A haematoma following a partial pectoralis major rupture can become infected, causing problems with diagnosis [15].
Other Considerations: Surgical repair of pectoralis major tendon ruptures carries a low risk of complications [18].
Recovery
Operative Outcomes: Operative management of pectoralis major tendon ruptures yields significantly superior outcomes compared with nonoperative treatment, with an associated 14.21% complication rate [16]. This superiority in outcomes is consistently observed when comparing operative to nonoperative groups [25]. Patients treated operatively for acute or chronic pectoralis major ruptures fare significantly better than those treated nonoperatively, with no statistically significant difference in outcomes between the acute and chronic operative groups [8]. In the largest study to date, 94% of patients are able to return to full military duty after primary pectoralis major repair, while 5.8% experience re-rupture [30]. Acute repair of pectoralis major tendon tears results in significantly superior functional outcomes and cosmesis satisfaction, with a trend toward a higher proportion of patients who are pain-free [42]. Delayed surgical repair of pectoralis major ruptures is technically feasible, and the use of fascial allograft to augment the repair can successfully treat chronic ruptures without compromising the final result [54]. Prompt recognition and decompression of pectoral/upper arm compartment syndrome, followed by delayed pectoralis major tendon repair, can result in a successful return to normal function [39].
Prognostic Factors: The prognosis is related neither to the age of the patient nor to the location of the rupture [132].
Key Evidence
- [L3] We therefore conclude that, in a patient with the clinical diagnosis of rupture of the pectoralis major, surgical repair will give the best results in terms of regaining strength and functional outcome. [2] (10.1136/bjsm.35.3.202)
- [L4] The authors emphasize that pectoralis major rupture should be assessed in traumatic first-time dislocations to avoid missed diagnosis. [3] (10.1016/j.xrrt.2022.09.002)
- [L5] There have been no previous reports of pectoralis major rupture occurring in women in this age group. [4] (10.5435/jaaosglobal-d-19-00030)
- [L4] The majority of pectoralis major tears occurred at the myotendinous junction. [5] (10.1016/j.jseint.2023.06.019)
- [L4] Repair of a pectoralis major muscle rupture was successfully performed 13 years after the initial injury. [6] (10.1177/03635465000280021901)
- [L4] Full-thickness ruptures of the pectoralis major muscle belly are rare and have been treated surgically with good to excellent results reported. [7] (10.1016/j.jses.2019.10.006)
- [L3] Patients treated operatively for acute or chronic pectoralis major ruptures fared significantly better than those treated nonoperatively, with no statistically significant difference in outcomes between acute and chronic operative groups. [8] (10.1177/03635465000280012701)
- [L3] Complete pectoralis major ruptures should be treated operatively as early as possible to achieve full strength restoration. [9] (10.1055/s-2006-933444)
- [L4] Early surgical treatment by anatomic repair gives the best results in the treatment of total and near-total ruptures of the pectoralis major muscle. [10] (10.1177/0363546503261137)
- [L4] The total number of pectoralis major ruptures has drastically risen from 10 cases between 2000-2010 to 55 cases from 2010-2017. [11] (10.1177/2325967119s00396)
- [L4] This injury combination is rare but can occur in young athletes who experience high-energy trauma to the shoulder. [12] (10.1016/j.eats.2025.103730)
- [L5] Rupture of the pectoralis major muscle can result in ossification within the muscle, presenting as a tender lump. [14] (10.1016/0020-1383(88)90050-2)
- [L5] [15] (10.1007/pl00021233)
- [L1] Pectoralis major tendon repair resulted in significantly superior outcomes compared with nonoperative treatment, with an associated 14.21% complication rate. [16] (10.1177/2325967119900813)
- [L4] In summary, anatomic surgical repair is the treatment of choice for complete acute ruptures of the pectoralis major tendon or muscle in athletes. [17] (10.2147/oajsm.s9066)
- [L4] Surgical repair of pectoralis major tendon ruptures can be performed safely with a low re-rupture rate and low risk of complications. [18] (10.1177/2325967117s00242)
- [L2] Total ruptures of the pectoralis major muscle exhibit better outcomes with surgical treatment than with nonoperative treatment based on the Bak criteria in athletes. [19] (10.1177/0363546513506556)
- [L4] Pectoralis major repair results in a high rate of return to work (97.8%) with a mean time to return of 1.6 months. [20] (10.1177/23259671211045635)
- [L4] The majority of pectoralis major tears occurred at the myotendinous junction, potentially reflecting changes in population-wide physical activities. [22] (10.1177/2325967123s00348)
- [L2] [23] (10.1177/2325967113516729)
- [L1] Pectoralis major tendon repair resulted in significantly superior outcomes as compared to nonoperative treatment with an associated 14.21% complication rate. [25] (10.1177/2325967120s00411)
- [L5] [26] (10.5435/jaaos-d-21-00541)
- [L5] Classifying pectoralis tendon tears as ' full- or partial-thickness ' (i.e., involving both layers or just one) and ' full- or partial-width ' (i.e., involving entire layer or just a portion of the layer) will more accurately characterize the degree of pectoralis tendon pathology and help guide the most appropriate clinical management. [27] (10.1007/s00256-014-1990-7)
- [L4] The authors recommend repair of complete pectoralis muscle ruptures in active patients who require maximum strength in vocational or avocational activities. [28] (10.1177/036354659202000517)
- [L3] In the largest study to date, 94% of patients are able to return to full military duty after primary pectoralis major repair and 5.8% experience re-rupture. [30] (10.1016/j.arthro.2016.03.068)
- [L4] Early surgical repair of distal pectoralis major tendon ruptures and an accelerated rehabilitation protocol provide reliable restoration of shoulder function and strength, allowing an early return to sports and functional activity. [31] (10.1007/s00264-006-0171-2)
- [Letter] The authors propose an alternate classification of pectoralis major tears based on the crossing of tendon segments, suggesting that lesions Pp-I cannot involve only the inferior part of the posterior layer and that surgical recommendations for this classification are yet to be established. [32] (10.1016/j.jse.2012.10.030)
- [L4] [33] (10.5435/00124635-200604000-00008)
- [L5] [34] (10.1016/j.jse.2014.10.024)
- [L3] MRI is accurate for diagnosing the tear grade and location of pectoralis major tendon ruptures, particularly for acute, tendon-bone, and G3 tears. [36] (10.1016/j.jse.2015.08.037)
- [L4] Our case demonstrates that prompt recognition and decompression of pectoral/upper arm compartment syndrome, followed by delayed pectoralis major tendon repair, can result in a successful return to normal function. [39] (10.1016/j.jse.2014.10.023)
- [Paper] The authors recommend their preferred technique for pectoralis major repair as it provides a reproducible and reliable anatomic repair with positive clinical outcomes. [40] (10.1016/j.eats.2017.02.002)
- [L1] Acute repair of pectoralis major tendon tears resulted in significantly superior functional outcomes and cosmesis satisfaction with a trend toward a higher proportion of patients who were pain-free. [42] (10.1177/0363546520904402)
- [L5] [46] (10.1177/0363546509348051)
- [L4] The Cruciform Test is a simple and reproducible diagnostic tool that has potential as a clinical indicator of both pectoralis major rupture and successful repair. [47] (10.1177/17585732211058457)
- [L4] Repair of the pectoralis major tendon ruptures using intramedullary suture anchors has high rates of return to duty, patient satisfaction, and patient-reported outcomes. [49] (10.1016/j.jse.2024.04.029)
- [L4] Pectoralis muscle injuries are most frequently non-contact injuries, most commonly sustained by pitchers. [50] (10.1016/j.jse.2022.01.134)
- [L2] Pectoralis major transfer results in improvement for patients with an irreparable subscapularis tear with or without an associated reparable supraspinatus tear. [51] (10.2106/00004623-200310000-00012)
- [L3] As a salvage procedure, the pectoralis major tendon transfer provides good results in most cases. [53] (10.1016/j.jse.2011.01.023)
- [L4] Delayed surgical repair of pectoralis major ruptures is technically feasible, and the use of fascial allograft to augment the repair can successfully treat chronic ruptures without compromising the final result. [54] (10.1067/mse.2003.128200)
- [L4] The authors propose a new classification of pectoralis major injury and present a biomechanically sound repair technique for isolated tears of the sternocostal head with favorable outcomes. [94] (10.1016/j.jse.2019.11.024)
- [L4] Pectoralis major tendon repair is an effective treatment that results in a high rate of return to sport and work, pain relief, and improved cosmetic appearance, albeit with a significant rate of complication. [96] (10.1177/1941738118818060)
- [L4] The authors describe a safe and reproducible technique for acute pectoralis major reconstruction with semitendinosus augmentation, hoping it provides a treatment rationale for surgeons caring for athletes with favorable outcomes. [106] (10.1016/j.xrrt.2025.06.003)
- [L4] The good results confirm that pectoralis major transfer is a reliable treatment option for irreparable anterosuperior rotator cuff injuries with significant improvement in pain and function. [114] (10.1007/s00264-009-0799-9)
- [L4] A contemporary injury classification system is proposed that includes injury timing, injury location, and standardized terminology addressing tear extent to more accurately reflect the musculotendinous morphology of PM injuries and better inform surgical management, rehabilitation, and research. [121] (10.1016/j.jse.2011.04.035)
- [L4] [126] (10.1177/2325967118824551)
- [L4] [131] (10.1016/j.xrrt.2025.07.019)
- [L1] The prognosis is related neither to the age of the patient nor to the location of the rupture. [132] (10.1007/s001670050197)
- [L3] MRI appeared to be less sensitive and specific than previous reports for traumatic PM tendon injuries. [134] (10.1177/2325967120925019)
See Also
- Pectoralis Major Repair
- Shoulder Instability
- Fractures
- Calcific Tendinitis
- Rotator Cuff
- Shoulder Arthritis
References
[1] Rupture of the Pectoralis Major Muscle: A REPORT OF ELEVEN INJURIES AND REVIEW OF FIFTY-SIX.. The Journal of Bone and Joint Surgery. American Volume. 1972.
[2] Pectoralis major tears: comparison of surgical and conservative treatment. British Journal of Sports Medicine. 2001. DOI: 10.1136/bjsm.35.3.202
[3] Traumatic anterior shoulder dislocation with concomitant pectoralis rupture and Bankart lesion. JSES Reviews, Reports, and Techniques. 2023. DOI: 10.1016/j.xrrt.2022.09.002
[4] Pectoralis Major Rupture in an Active Female. JAAOS: Global Research and Reviews. 2019. DOI: 10.5435/jaaosglobal-d-19-00030
[5] Myotendinous junction tears of the pectoralis major are occurring more frequently and discrepancies exist between intraoperative and radiographic assessments. JSES International. 2023. DOI: 10.1016/j.jseint.2023.06.019
[6] Delayed Repair of a Ruptured Pectoralis Major Muscle. The American Journal of Sports Medicine. 2000. DOI: 10.1177/03635465000280021901
[7] Successful surgical repair of a full-thickness intramuscular muscle belly rupture of pectoralis major. JSES International. 2020. DOI: 10.1016/j.jses.2019.10.006
[8] Rupture of the Pectoralis Major Muscle. The American Journal of Sports Medicine. 2000. DOI: 10.1177/03635465000280012701
[9] Musculus-pectoralis-major-Rupturen: Verletzungsklassifikation und Ergebnisse der operativen Versorgung. Zeitschrift für Orthopädie und ihre Grenzgebiete. 2006. DOI: 10.1055/s-2006-933444
[10] Rupture of the Pectoralis Major Muscle. The American Journal of Sports Medicine. 2004. DOI: 10.1177/0363546503261137
[11] Increasing Incidence of Pectoralis Major Ruptures in NFL Players. Orthopaedic Journal of Sports Medicine. 2019. DOI: 10.1177/2325967119s00396
[12] Open Pectoralis Major Repair Combined With Arthroscopic Posterior Labral Repair. Arthroscopy Techniques. 2025. DOI: 10.1016/j.eats.2025.103730
[14] Rupture of the pectoralis major muscle: a complication. Injury. 1988. DOI: 10.1016/0020-1383(88)90050-2
[15] Traumatic abscess of pectoralis major. Archives of Orthopaedic and Trauma Surgery. 2000. DOI: 10.1007/pl00021233
[16] Treatment of Pectoralis Major Tendon Tears: A Systematic Review and Meta-analysis of Operative and Nonoperative Treatment. Orthopaedic Journal of Sports Medicine. 2020. DOI: 10.1177/2325967119900813
[17] Surgical and nonsurgical treatment of total rupture of the pectoralis major muscle in athletes: update and critical appraisal. Open Access Journal of Sports Medicine. 2010. DOI: 10.2147/oajsm.s9066
[18] Surgical Treatment of Pectoralis Major Tendon Ruptures: A Retrospective Review of 134 Patients Tendon Ruptures. Orthopaedic Journal of Sports Medicine. 2017. DOI: 10.1177/2325967117s00242
[19] Clinical Considerations for the Surgical Treatment of Pectoralis Major Muscle Ruptures Based on 60 Cases. The American Journal of Sports Medicine. 2013. DOI: 10.1177/0363546513506556
[20] Return to Work After Pectoralis Major Repair. Orthopaedic Journal of Sports Medicine. 2021. DOI: 10.1177/23259671211045635
[22] Poster 385: Discrepancies Exist Between Intraoperative and Magnetic Resonance Imaging Assessments of Partial Pectoralis Major Tears. Orthopaedic Journal of Sports Medicine. 2023. DOI: 10.1177/2325967123s00348
[23] Utility of the Pectoralis Major Index in the Diagnosis of Structurally Significant Pectoralis Major Tears. Orthopaedic Journal of Sports Medicine. 2013. DOI: 10.1177/2325967113516729
[25] Treatment of Pectoralis Major Tendon Tears: A Systematic Review and Meta-Analysis of Operative and Nonoperative Treatment. Orthopaedic Journal of Sports Medicine. 2020. DOI: 10.1177/2325967120s00411
[26] Pectoralis Major Rupture: Evaluation and Management. Journal of the American Academy of Orthopaedic Surgeons. 2022. DOI: 10.5435/jaaos-d-21-00541
[27] Pectoralis major tears: anatomy, classification, and diagnosis with ultrasound and MR imaging. Skeletal Radiology. 2014. DOI: 10.1007/s00256-014-1990-7
[28] Ruptures of the pectoralis major muscle. The American Journal of Sports Medicine. 2020. DOI: 10.1177/036354659202000517
[30] Mid‐Term Complications and Re‐operation Rates Following Pectoralis Major Tendon Repair in the Young Active Population. Arthroscopy. 2016. DOI: 10.1016/j.arthro.2016.03.068
[31] Rupture of the pectoralis major muscle: Surgical treatment in athletes. International Orthopaedics. 2006. DOI: 10.1007/s00264-006-0171-2
[32] Regarding “A systematic review and comprehensive classification of pectoralis major tears”. Journal of Shoulder and Elbow Surgery. 2013. DOI: 10.1016/j.jse.2012.10.030
[33] Pectoralis Major Muscle Injuries: Evaluation and Management. Journal of the American Academy of Orthopaedic Surgeons. 2006. DOI: 10.5435/00124635-200604000-00008
[34] Pectoralis major ruptures: a review of current management. Journal of Shoulder and Elbow Surgery. 2015. DOI: 10.1016/j.jse.2014.10.024
[36] Accuracy of magnetic resonance imaging in predicting the intraoperative tear characteristics of pectoralis major ruptures. Journal of Shoulder and Elbow Surgery. 2016. DOI: 10.1016/j.jse.2015.08.037
[39] Compartment syndrome secondary to acute pectoralis major tendon rupture. Journal of Shoulder and Elbow Surgery. 2015. DOI: 10.1016/j.jse.2014.10.023
[40] Pectoralis Major Repair With Unicortical Button Fixation And Suture Tape. Arthroscopy Techniques. 2017. DOI: 10.1016/j.eats.2017.02.002
[42] Treatment of Pectoralis Major Tendon Tears: A Systematic Review and Meta-analysis of Repair Timing and Fixation Methods. The American Journal of Sports Medicine. 2020. DOI: 10.1177/0363546520904402
[45] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Radiographic Evaluation.
[46] Injuries to the Pectoralis Major Muscle. The American Journal of Sports Medicine. 2010. DOI: 10.1177/0363546509348051
[47] The ‘Cruciform Test’: A diagnostic tool to detect pectoralis major rupture. Shoulder & Elbow. 2021. DOI: 10.1177/17585732211058457
[49] Pectoralis major tendon rupture repairs using intramedullary suture anchors shows high patient-reported outcomes in military service members. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2024.04.029
[50] Pectoralis muscle injuries in Major and Minor League Baseball. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2022.01.134
[51] OUTCOME OF PECTORALIS MAJOR TRANSFER FOR THE TREATMENT OF IRREPARABLE SUBSCAPULARIS TEARS. The Journal of Bone and Joint Surgery-American Volume. 2003. DOI: 10.2106/00004623-200310000-00012
[53] Magnetic resonance imaging-controlled results of the pectoralis major tendon transfer for irreparable anterosuperior rotator cuff tears performed with standard and modified fixation techniques. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2011.01.023
[54] Delayed repair of a pectoralis major tendon rupture with allograft: A case report. Journal of Shoulder and Elbow Surgery. 2003. DOI: 10.1067/mse.2003.128200
[56] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > ANATOMY.
[60] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > Bursae.
[63] Rockwood And Matsen S The Shoulder. Fractures, Dislocations, and Acquired Problems of the Shoulder in Children > FRACTURES OF THE PROXIMAL HUMERUS.
[69] Campbell S Operative Orthopaedics 4 Volume Set. ANTERIOR CRUCIATE LIGAMENT RECONSTRUCTION WITH BONE-PATELLAR TENDON-BONE GRAFT > SHOULDER INJURIES > ANATOMY AND BIOMECHANICS.
[71] Orthopaedic Knowledge Update Sports Medicine 6. Diagnostic Ultrasonography and Ultrasonography-Guided Procedures > Annotated References.
[72] Orthopaedic Knowledge Update Sports Medicine 6. Research Studies and Registries in Sports Medicine > Multicenter and Registry-Based Research in Sports Medicine > Shoulder Research.
[73] Apley And Solomon S Concise System Of Orthopaedics And Trauma. INVESTIGATION.
[75] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > SENIOR EDITOR COMMENTARY.
[77] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Magnetic Resonance Imaging and Arthrography.
[79] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Shoulder Anatomy and Biomechanics, Clinical Evaluation, Imaging > Clinical Evaluation > Imaging.
[81] Aaos Comprehensive Orthopaedic Review 3. Imaging of the Shoulder and Elbow > I. Shoulder.
[83] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Radiography.
[93] Pectoralis Major Muscle: Function of Sternal Portion and Mechanism of Rupture of Normal Muscle: Case Reports.. The Journal of Bone and Joint Surgery. American Volume. 1961.
[94] Isolated tears of the sternocostal head of the pectoralis major muscle: surgical technique, clinical outcomes, and a modification of the Tietjen and Bak classification. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2019.11.024
[96] Outcomes and Return to Sport After Pectoralis Major Tendon Repair: A Systematic Review. Sports Health: A Multidisciplinary Approach. 2018. DOI: 10.1177/1941738118818060
[106] Acute pectoralis major tendon tear reconstruction with semitendinosus augmentation: a technique note. JSES Reviews, Reports, and Techniques. 2025. DOI: 10.1016/j.xrrt.2025.06.003
[114] Pectoralis major transfer for the treatment of irreparable anterosuperior rotator cuff tears. International Orthopaedics. 2009. DOI: 10.1007/s00264-009-0799-9
[121] A systematic review and comprehensive classification of pectoralis major tears. Journal of Shoulder and Elbow Surgery. 2012. DOI: 10.1016/j.jse.2011.04.035
[126] Surgical Treatment of Pectoralis Major Muscle Ruptures: A Systematic Review and Meta-analysis. Orthopaedic Journal of Sports Medicine. 2019. DOI: 10.1177/2325967118824551
[131] Technique of reconstruction of chronic pectoralis major tendon rupture with dermal allograft using the anatomic length method. JSES Reviews, Reports, and Techniques. 2025. DOI: 10.1016/j.xrrt.2025.07.019
[132] Rupture of the pectoralis major: a meta‐analysis of 112 cases. Knee Surgery, Sports Traumatology, Arthroscopy. 2000. DOI: 10.1007/s001670050197
[134] Magnetic Resonance Imaging of Pectoralis Major Injuries in an Active Duty Military Cohort: Mechanism Affects Tear Location. Orthopaedic Journal of Sports Medicine. 2020. DOI: 10.1177/2325967120925019