Patients › Elbow
Radial Head Fracture
Radial head fractures — Mason classification, conservative management, and indications for fixation or replacement.
What you're feeling
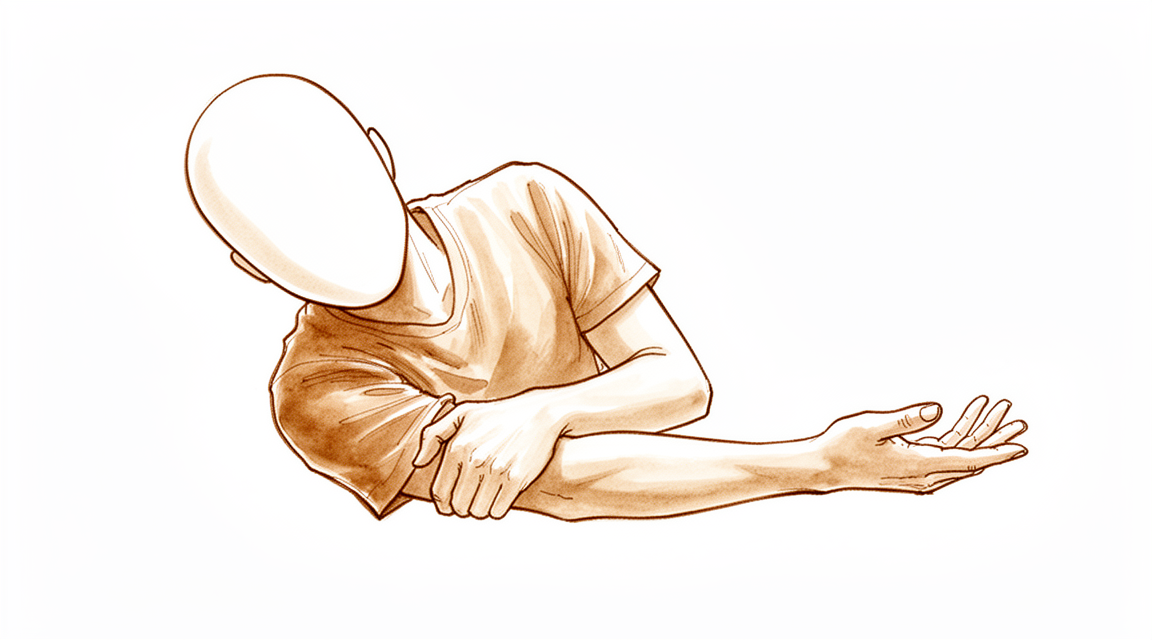
A radial head fracture usually happens when you fall onto an outstretched arm. The force travels up your forearm and into your elbow, breaking the small rounded bone at the top of your forearm, just below your elbow. This bone is called the radial head. These breaks are common. They account for about 20% of all elbow fractures, and they are the most common fracture around the elbow.
Most people feel pain on the outer side of the elbow straight away. The area may be tender to touch, and moving your elbow or turning your forearm can hurt. Swelling often develops over the joint, sometimes with bruising. Your elbow may feel stiff, and you may be reluctant to use the arm at all. Some falls also push the elbow out of joint, which happens with 3% to 14% of these fractures.
In the first days, the pain is often there even when you are resting, and it can disturb your sleep. Simple tasks like lifting a kettle, turning a door handle, pouring a drink, or reaching across your body can be uncomfortable. Turning your palm up or down to hold a phone or a plate may be harder than bending the elbow.
Over the first weeks, the pain usually settles gradually as the bone starts to heal. Movement tends to get easier, though it can take time before your elbow feels normal again.
It is worth knowing that these fractures sometimes come with other injuries in the same arm. The wrist, forearm, or shoulder can also be hurt in the same fall, and the ligaments around the elbow can be strained. Your surgeon will ask about pain elsewhere in your arm and examine those areas carefully, because finding these injuries early matters for how well the elbow works later on.
If your pain is on the outer side of the elbow after a fall, and moving or loading the arm is difficult, that pattern fits this injury. The next sections explain how the fracture is confirmed and what treatment involves.
What's actually happening
The radial head is a small, disk-shaped bone with a shallow cup on top. That cup glides against the end of the arm bone above it, and the side of the disk slots against the other forearm bone. Think of it as a washer sitting between two moving parts: it lets your forearm rotate so you can turn a palm up or down, and it cushions the load travelling up your arm.
It also does a second job. It acts as a brace on one side of the elbow, helping the ligaments keep the joint lined up when you push or straighten the arm. If that brace cracks, the elbow can feel unsteady, especially if a ligament is also torn. The blood supply to this little bone is limited, which is one reason some breaks are slow to knit.
Most of these fractures happen when you fall onto an outstretched arm, and the force drives the radial head hard against the bone above it. Sometimes the same fall strains or tears the ligaments on the inner or outer side of the elbow, or injures the wrist or forearm further along. About 30% of people with a radial head fracture have other injuries in the same arm. When the elbow also comes out of joint, other parts of the elbow can be damaged too, and that combination makes the joint more unstable.
Bone heals by knitting back together, with new bone bridging the break over weeks. If the pieces sit close together and line up well, they can knit in place without surgery. If a piece is pushed apart by 2 to 3 mm or more, or the joint surface is broken into several pieces, the bone may not knit in a usable shape on its own. In those cases, surgery aims to hold the pieces in place, or to replace the damaged radial head with an artificial one so the elbow keeps its brace and its smooth turning surface.
What we can do about it
Dr Kieran Hirpara, an upper-limb surgeon at Mater Private Hospital Rockhampton, matches the treatment to your specific injury. Patients are generally referred to our clinic by their GP; if a physiotherapist has suggested you see us, you will still need a referral from your GP in order to be eligible for the Medicare rebate. At that first visit we take a history, examine your elbow, and arrange imaging where it is needed. X-rays usually show the break. Sometimes a scan is added to check for small pieces of bone or injured ligaments that change the plan.
Many of these fractures are stable and the pieces sit close together. When that is the case, and your elbow can still bend and turn without a block, we usually treat it without surgery. You may wear a sling for comfort, for a week or less, and then start moving the arm. Some people have fluid drawn from the joint with a needle early on, which eases the pain and makes early movement easier. Physiotherapy is staged in as the pain settles. Long-term results after this kind of care are good, and for some fracture patterns surgery and no surgery lead to similar function after a year. The choice here is genuinely shared: non-operative care is reasonable, but the pain and the final position of the arm may not suit everyone.
Surgery is recommended from the outset when the break is pushed apart, when broken pieces jam the joint and stop it turning, when the elbow is unstable, or when other injuries in the same arm need repair. The aim is to hold the pieces in place with small plates or screws, or, when the bone is in too many pieces to rebuild, to replace the radial head with an artificial one. We will talk through which option fits your fracture, your age, your bone quality, and what you need your arm to do.
Whichever path you take, the first weeks are about comfort and protection. Pain relief keeps you moving within the limits we set. The arm is guarded while the bone knits or while the repair settles. Physiotherapy then takes over at the right stage, because early, guided movement is what prevents stiffness. We see you along the way to check healing and adjust the plan as your elbow improves.
What to expect
Most radial head fractures are undisplaced and heal without surgery. Over the first weeks the pain settles and movement gets easier, though the elbow can stay stiff for some months. Turning your palm up and down is often the last thing to feel normal. You can expect to be doing daily tasks like eating and dressing early on, with heavier lifting and work building back over the following weeks. Your surgeon will guide when it is safe to return to work or sport.
If your fracture needs surgery, the bone is held with small plates or screws, or replaced with an artificial radial head when it is in too many pieces to rebuild. Recovery follows the same broad shape: the arm is protected at first, then movement and strength are built back with physiotherapy. Many people regain good function in the arm after surgery for this fracture.
It is honest to say that things can occasionally go wrong. The bone can be slow to knit, or knit in a poorer position than hoped. Stiffness is the most common complaint, which is why guided movement starts early. When a replacement is used, further surgery is sometimes needed in the first year, and over 10 years the implant survival rate with uncemented implants remains high. At 18 years, implant survival is 75.1%, with the highest failure rate in the first year after surgery. Some people who have the radial head removed rather than replaced still do well: 96% report satisfactory function in the long term, even though wear-and-tear changes show on later X-rays.
If other injuries came with the fracture, such as a torn ligament or a dislocated elbow, recovery can take longer and the elbow may feel less steady for a while. Finding and treating these injuries early gives the best chance of a good result, with success rates around 80% when they are picked up in time.
When to see someone
Seek urgent care if your elbow is visibly out of shape, if there is an open wound, if you have numbness or tingling in the arm or hand, or if you cannot use the limb at all. These signs need checking straight away.
Otherwise, start with your GP. Ask for a specialist review if the pain is not settling, or if the swelling, movement, or use of your arm is not improving week on week as the bone heals. Recovery usually moves forward steadily, so a change for the better each week is what you want to see. If that stops happening, it is worth having the elbow looked at again.
In more depth
Advanced reading: the deeper science (optional)
This section goes further than you need for your own treatment decisions. A radial head fracture is worth the extra reading because the bone itself is often the least important part of the injury, what determines your result is usually whether anything else in the elbow was damaged at the same time.
The fracture is a marker, not just an injury
The radial head is a stabiliser. It stops the radius sliding up the forearm and it resists the elbow being pushed sideways. So a force large enough to break it is frequently large enough to damage the ligaments and the coronoid too, the combination known as the terrible triad: radial head fracture, coronoid fracture and elbow dislocation.
That is why an isolated, undisplaced radial head fracture and a radial head fracture as part of a triad are entirely different problems with the same name on the X-ray report. The first usually needs early movement and little else. The second is one of the more demanding reconstructions in upper-limb surgery.
Even the surgical approach for the triad is contested. Pooling 866 patients, a combined lateral plus anteromedial approach appeared to offer a favourable balance between functional outcome and complication risk, while purely anterolateral or anteromedial approaches offered advantages in some postoperative measures [1], a comparison that would not still be open if one route were clearly superior.
Fix it or replace it
Where the head is broken but reconstructable, fixing it preserves your own anatomy. Where it is in too many fragments, replacement is generally preferred over attempting a fixation likely to fail, a failed fixation leaves a stiff, unstable elbow and a harder second operation.
When replacement is chosen, the design debate has been quieter than expected. Comparing monopolar with bipolar radial head prostheses across 591 patients found no significant difference in efficacy or safety, with the authors calling for higher-quality randomised trials [2].
That is a useful thing to know if you are told a particular implant is better. On current evidence the distinction has not been demonstrated.
Why implants get removed — and it is not what you would guess
A meta-analysis of 1,017 radial head arthroplasties found that removal or revision peaked within two years of implantation, and that most removals were performed to manage elbow stiffness and heterotopic ossification rather than loosening of the implant [3].
So the implant usually is not the thing that failed. The elbow around it stiffened, and taking the metal out formed part of treating that. It reframes what "revision surgery" means here, and it explains why the rehabilitation after this operation matters more than the choice of prosthesis.
It also means published revision rates should be read with the follow-up length in mind. A separate review of 1,272 patients concluded the literature does not provide a reliable estimate of the re-operation rate, and recommended a minimum of three years of follow-up with an agreed definition of what counts as a reason for revision [4]. A study reporting twelve months will systematically miss the removals that cluster in the first two years.
The thing to protect is motion
The consistent thread is that the elbow's characteristic failure is stiffness, not instability or implant failure. It is an unforgiving joint: it tolerates immobility badly and loses the last degrees of extension readily. Whatever is done to the bone, the months afterwards are what determine how the arm works.
References for the advanced reading
- Zheng M, Wan W, Liang S. Which is the optimal surgical strategy for the terrible triad of the elbow? A systematic review and meta-analysis. J Orthop Surg Res. 2026;21(1).
- Said E, Ameen M, Sayed AA, Mosallam KH, Ahmed AM, Tammam H. Efficacy and safety of monopolar versus bipolar radial head arthroplasty: a systematic review and meta-analysis. J Shoulder Elbow Surg. 2022;31(3):646-55.
- Kachooei AR, Baradaran A, Ebrahimzadeh MH, van Dijk CN, Chen N. The rate of radial head prosthesis removal or revision: a systematic review and meta-analysis. J Hand Surg Am. 2018;43(1):39-53.e1.
- Laumonerie P, Reina N, Kerezoudis P, Declaux S, Tibbo ME, Bonnevialle N, et al. The minimum follow-up required for radial head arthroplasty. Bone Joint J. 2017;99-B(12):1561-70.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- The purpose of the 2015 World Journal of Orthopedics article was to provide an overview of current concepts in the management of radial head fractures [2].
- There is insufficient evidence to draw definitive conclusions on the optimal treatment of type II–IV radial head fractures [13].
- Recommendations for the surgical treatment of radial head and neck fractures according to the Mason classification can be given with the best available evidence [25].
- The intraoperative decision to fix or replace the radial head is critical to optimize treatment outcomes [81].
- Overall reoperation rates are high in patients undergoing operative treatment of radial head and neck fractures [51].
- The challenge in the coming years will be to perform high-level clinical studies to obtain consensus regarding the most appropriate treatment for comminuted radial head fractures [1].
Operative
- Clinical outcome studies of metallic radial head arthroplasty systems indicate that head replacement is a reasonable option to offer patients with comminuted radial head fractures and complex elbow trauma [14].
- Adequate knowledge of the surgical indications, types of implants, and surgical technique are essential for a satisfactory outcome when a radial head prosthesis is used for the treatment of nonreconstructable radial head fractures [23].
- Radial head replacement is recommended for comminuted fractures with satisfactory medium- and long-term results [29].
- Bipolar-cemented implants show lower revision rates [29].
- Radial head implants offer a reliable treatment for complex Mason type III and IV fractures, with good functional and survival outcomes and a low incidence of complications [4].
- Arthroscopic reduction internal fixation (ARIF) is a safe and viable option for treating displaced radial head fractures [35].
- For radial head arthroplasties, acute trauma is the most common indication [20].
- The Radial Head System is the most commonly used implant for radial head arthroplasties [20].
Anatomy & Pathophysiology
Bony Anatomy
- The radial head is disk-shaped and has a greater diameter than the neck [33].
- The radial head has a shallow cuplike surface that articulates with the capitellum proximally and the radial notch of the ulna medially [33].
- The biceps inserts on the tuberosity of the radial head immediately distal to the neck [33].
- The radial head is seated in the lesser sigmoid notch and has contact axially with the capitellum of the distal humerus [19].
- The radial head has a slightly elliptical cross section and interdigitates precisely with both the lesser sigmoid notch and the lateral lip of the trochlea [60].
- The radial head has a relatively small nonarticular surface [60].
- The nonarticular area of the radial head can be determined as an arc of roughly 90 degrees with its midpoint directly lateral with the arm in neutral position, with a slightly greater margin anteriorly [60].
- The area between the Lister tubercle and the radial styloid on the distal radius has been suggested as a rough guide to the nonarticular safe zone of the radial head [60].
- The proximal radius has a slight angulation with respect to the shaft [60].
- In children, the secondary ossification center of the proximal radius appears as a small sphere between the third and fifth years of life and fuses with the shaft between the ages of 16 and 18 years [33].
- The difference in radiographic height between the tip of the coronoid and anterior radial head in the normal elbow averages 5 mm [53].
Vascular Supply
- The blood supply to the epiphysis of the radial head is supplied through the more distal metaphysis because the entire radial head is covered with articular cartilage [33].
- The vascular supply to the radial head is limited and tenuous [60].
Ligaments and Stability
- The radial head plays an important role as a secondary valgus stabilizer of the elbow [18].
- The radial head is the secondary restraint to valgus stability of the elbow [19].
- The ligaments have the most marked influence on elbow stability, particularly when the upper limb is positioned such that valgus and varus gravity loads are applied [59].
- The radial head is an important secondary stabilizer of the elbow, and excision alone is contraindicated in the presence of extensive damage to primary stabilizers including the medial collateral ligament, coronoid, interosseous membrane, and lateral collateral ligament [18].
Mechanisms of Injury
- Radial head fractures typically result from a fall on an outstretched hand with the forearm in pronation, resulting in an axial load on the elbow [18].
- Radial head fractures are generally caused by longitudinal loading from a fall on an outstretched hand [19].
- Most radial head fractures occur as the result of low-energy mechanisms such as a trip and fall on an outstretched hand [42].
- A valgus load causes impaction of the radial head into the capitellum, commonly with rupture of the medial collateral ligament [42].
- Posterolateral rotatory subluxation of the radial head with respect to the capitellum causes a partial articular shear fracture of the anterior portion of the radial head often with rupture of the lateral collateral ligament [42].
- An axial forearm load causes impaction of the radial head into the capitellum, with more severe trauma producing a fracture of the coronoid or rupture of the interosseous membrane and distal radioulnar joint ligaments [42].
- Dislocation of the elbow is another cause of radial head fractures [19].
- In children, fractures of the radial head or neck usually result from a fall onto an outstretched hand with the elbow in extension and valgus [33].
- In children, fracture of the radial neck may occur as a result of dislocation of the elbow, either at the time of posterior dislocation or at the time of spontaneous reduction [33].
Associated Injuries
- Radial head fractures can occur in isolation; however, they are often associated with more complex injuries such as associated elbow fractures, dislocations, and soft-tissue injuries [18].
- Of patients with radial head fractures, 30% have other soft-tissue and skeletal injuries including carpal fractures, distal radioulnar joint disruption, interosseous membrane disruption, coronoid fractures, Monteggia fracture-dislocations, capitellar fractures, and medial and lateral collateral ligament injuries [18].
- Undisplaced and minimally displaced radial head fractures typically occur as isolated injuries while more displaced and comminuted fractures commonly have associated injuries to the collateral ligaments and may have associated fractures of the coronoid, capitellum, or proximal ulna [42].
- Tears of the lateral collateral ligaments and/or medial collateral ligaments are most commonly associated with radial head fractures [42].
- Dislocations of the elbow and fractures of the coronoid, capitellum, olecranon, and proximal ulna are also frequent associated injuries with radial head fractures [42].
- Rupture of the interosseous membrane while uncommon is best diagnosed and treated early as late reconstruction is challenging and often unsatisfactory [42].
- The incidence of injuries associated with radial head and neck fractures ranges from 11% to 90% [65].
- Increasing patient age, loss of cortical contact, and comminution are related to a higher incidence of associated injuries in radial head fractures [65].
- Posterolateral dislocation of the elbow is seen in 3% to 14% of radial head fractures [65].
- Ulnar fractures occur in 1.2% to 12% of patients with radial head fractures [65].
- Capitellar osteochondral damage occurs from radial head impaction and is seen on MRI 39% to 96% of the time [65].
- Capitellum fractures rarely occur in tandem with radial head fractures with an incidence of 2% [65].
- Scaphoid fractures are identified in 3% of patients with proximal radius fractures [92].
- There is a 10% incidence of concomitant scaphoid and radial head fractures in men aged 18 to 30 years [92].
Epidemiology
- Approximately 20% of all elbow fractures involve the radial head [18].
- Radial head fractures account for 15–25% of all elbow fractures [19].
- Radial head fractures are the most common fractures of the elbow with an estimated incidence of 2.5 to 2.9 per 10,000 people per year [42].
- Radial head fractures are more common in women than in men and most frequently occur between the ages of 20 and 60 years [42].
- Radial head fractures occur at a mean age of 40 years and are seen in a similar ratio between men and women; however, once the age rises above 50, the number of female patients with radial head fractures is significantly larger [65].
- Radial head fractures account for 4% of all fractures and greater than 30% of all fractures involving the elbow [65].
- In children, isolated radial head fractures are rare because the immature radial head is cartilaginous [46].
- In children, most children sustain fractures of the radial neck, which account for approximately 1% of all children’s fractures and 5% of pediatric elbow fractures [46].
- Approximately 50% of radial neck fractures in children are associated with other injuries to the elbow [33].
Classification
- The Mason classification was developed in 1954 based on 100 radial head fractures treated operatively or non-operatively and re-evaluated after more than 2 years [26].
- Mason Type I fractures are defined as non-displaced marginal fissures or fractures [26].
- Mason Type II fractures are defined as displaced marginal fractures with separation or impaction [26].
- Mason Type III fractures are defined as displaced comminuted fractures involving the entire radial head [26].
- Broberg and Morrey added a Type IV to the Mason classification, defined as a radial head fracture combined with elbow dislocation [26].
- Johnston added a fourth type to the Mason classification in 1962 to signify radial head fractures accompanied by dislocation, irrespective of displacement or fragment comminution [34].
- Broberg and Morrey modified the Mason classification in 1987 by suggesting that a partial radial head fracture must be of sufficient size (at least 30% of the articular surface) and displacement (at least 2 mm) to be considered a displaced fracture (Mason type II) [34].
- Hotchkiss modified Mason's classification by adding clinical criteria, defining Type II as a displaced fracture of the radial head or neck combined with mechanical blocking of joint motion or with loss of joint congruity [26].
- Hotchkiss defined Type III fractures as characterized by comminution, which precludes internal fixation and requires either resection or prosthetic replacement of the radial head [26].
- The Mason and modified Mason classifications exhibit limitations, notably moderate inter- and intraobserver reliability and inconsistent guidance regarding treatment or prognostic prediction [34].
- A key weakness of the Mason and Hotchkiss classifications is their failure to consider concomitant lesions, which are present in nearly 80% of multi-fragment fractures, particularly Type III fractures [26].
- The Mayo Clinic classification considers all concomitant lesions and is described as deserving preference over classifications that do not [26].
- In the Mayo Clinic classification, the radial head fracture is described as in Mason's classification, and letters are added to indicate concomitant lesions, with upper case indicating a treated lesion and lower case indicating an untreated lesion [26].
- The first classification of radial head fractures was described by Speed in 1924, who made a distinction between complete and incomplete fractures of the head and neck [75].
- Mason suggested treatment options according to fracture type: Type I was to be treated nonoperatively; Type II might be treated nonoperatively or the radial head could be resected depending on fragment size; and the radial head should be resected in Type III fractures [75].
- The PARMa classification is a computed tomography–based algorithm for the management of radial head and neck fractures [50].
- Radial fractures can be classified by the Mason-Johnston classification [68].
Clinical Presentation
Epidemiology and Mechanism
- Radial head fractures are common and frequently accompanied by associated osseous injuries [6].
- Radial head and neck fractures have distinct epidemiological characteristics, and consideration for osteoporosis in a subset of patients is recommended [16].
- Radial head fractures typically result from a fall on an outstretched hand with the forearm in pronation, which results in an axial load on the elbow [18].
- Radial head fractures are generally caused by longitudinal loading from a fall on an outstretched hand; dislocation of the elbow is another cause [19].
- In children, the cartilaginous radial head is resistant to fracture, and children are more likely to sustain fractures of the radial neck than fractures of the head [33].
- Fractures of the radial head or neck in children may result from a fall onto an outstretched hand with the elbow in extension and valgus [33].
- Fracture of the radial neck in children may occur as a result of dislocation of the elbow, specifically by impact against the inferior aspect of the capitellum at the time of posterior dislocation or spontaneous reduction [33].
Associated Injuries
- Radial head fractures can occur in isolation; however, they often are associated with more complex injuries, such as associated elbow fractures, dislocations, and soft-tissue injuries [18].
- Of patients with radial head fractures, 30% have other soft-tissue and skeletal injuries [18].
- Associated injuries in radial head fractures include carpal fractures, distal radioulnar joint (DRUJ) disruption, interosseous membrane disruption, coronoid fractures, Monteggia fracture-dislocations, capitellar fractures, and medial and lateral collateral ligament injuries [18].
- The incidence of associated, osseous injuries of the upper limb in radial head fractures is high [22].
- Associated injuries must be considered carefully when treating radial head fractures [17].
- When a radial head fracture is present, the wrist should be carefully examined for a scaphoid fracture, and vice versa [40].
- Displaced radial neck fractures in children older than 10 years may be associated with loss of forearm rotation [33].
Physical Examination
- The patient should be questioned carefully about concomitant wrist, forearm, or shoulder pain [18].
- Pain with palpation over the radial head is a clinical finding in radial head fractures [18].
- The surgeon should examine elbow range of motion (ROM) and assess for a block to pronation/supination or flexion/extension [18].
- The surgeon should examine the forearm, wrist, and elbow for tenderness along the course of the interosseous membrane (Essex-Lopresti lesion), instability of the DRUJ, pain at the medial side of the elbow (medial collateral ligament [MCL]), and pain at the lateral side of the elbow (lateral collateral ligament [LCL]) [18].
- Lateral elbow pain and tenderness or limitation in elbow or forearm motion should alert the examiner to the possibility of a radial head fracture [18].
- Aspiration of the intra-articular hematoma and injection of a local anesthetic can be helpful when assessing mechanical blocks to motion [18].
Imaging
- AP and lateral radiographs of the elbow are routinely obtained for radial head fractures [18].
- Nondisplaced fractures of the radial head may not be visible on radiographs; however, they may be diagnosed by elevation of the anterior and posterior fat pads (the sail sign) by an intra-articular hemarthrosis [18].
- The fat pad sign is usually present on the lateral projection in radial head fractures [19].
- The radiocapitellar view is accomplished by positioning the patient as for a lateral view but angling the tube 45° toward the shoulder [18].
- For comminuted fractures, CT can delineate the location, number, and size of the fragments and is rapidly emerging as a standard imaging method for more complicated radial head fractures [18].
- The absence of cortical irregularity in the transition zone of the radial head and neck can be used to correctly identify a non-fractured radial head [12].
- Ultrasound imaging proved to be an effective method for diagnosing occult fractures of the radial head or neck when initial radiograms showed only intraarticular effusion [45].
- Subsequent radiographs during nonoperative treatment of isolated radial head or neck fractures were unhelpful and might contribute to overtreatment [10].
Classification
- The Mason classification of radial head fractures categorizes Type I as a minimally displaced fracture, Type II as a displaced fracture, Type III as a comminuted fracture, and Type IV as a fracture associated with an elbow dislocation [18].
- Mason Type I is a nondisplaced fracture; type II is a fracture that is displaced, usually involving a single large fragment; type III is a comminuted fracture; and type IV is a fracture associated with an elbow dislocation [19].
- In children, O’Brien subdivided radial head and neck fractures into three categories based on the degree of angular displacement of the superior articular surface from the horizontal [33].
- In the O’Brien classification for pediatric radial head and neck fractures, Type I fractures have displacement of 30 degrees or less, Type II fractures have between 31 and 60 degrees of angulation, and Type III fractures have more than 60 degrees of displacement [33].
- Approximately 50% of fractures of the proximal radius in children involve the physis and 50% are completely within the metaphysis [33].
- Proximal radial physeal fractures in children are usually Salter-Harris type II injuries, while younger children may sustain Salter-Harris type I injuries [33].
Investigations
Radiography
- Nondisplaced fractures of the radial head may not be visible on radiographs [18].
- Nondisplaced fractures of the radial head may be diagnosed by elevation of the anterior and posterior fat pads (the sail sign) by an intra-articular hemarthrosis [18].
- The fat pad sign is usually present on the lateral projection of the elbow radiograph [19].
- A positive fat pad sign on a lateral radiograph indicates that fluid is in the elbow joint, which in the acute setting is blood most commonly from a fracture [19].
- In terrible triad injuries, the imaging appearance of radial head fractures has no measurable influence on treatment recommendations [74].
Computed Tomography
- CT can be used for preoperative planning for comminuted fractures of the olecranon if there is an associated radial head or coronoid fracture; however, this is not routinely utilized [21].
Ultrasound
Associated Injury Screening
- Of patients with radial head fractures, 30% have other soft-tissue and skeletal injuries, including carpal fractures, distal radioulnar joint (DRUJ), and interosseous membrane disruption, coronoid fractures, Monteggia fracture-dislocations, capitellar fractures, and medial and lateral collateral ligament injuries [18].
- It is important to determine which structures need to be repaired to avoid complications that could lead to elbow instability [8].
- Patients with a high-energy injury mechanism merit careful evaluation for more complex injury patterns that could potentially be missed [47].
Postoperative Imaging
- There is a positive association between radiographic findings and patient symptoms for postoperative complications after radial head arthroplasty, validating radiography as the preferred postsurgical modality of imaging [82].
- Anatomic radial head replacement has a risk of radiographic technical mistakes that correlate to poorer outcomes [85].
- Significant radiographic differences exist between two frequently used radial head arthroplasty implants [91].
Treatment
Nonoperative Management
- Most radial head fractures are stable and managed non-operatively with good long-term results [11].
- Long-term patient-reported outcomes were excellent following the nonoperative management of isolated stable fractures of the radial head or neck [9].
- Conservative management of isolated Mason II radial head fractures yields favorable therapeutic outcomes with a low incidence of complications [41].
- ORIF and nonoperative treatment of isolated Mason type II radial head fractures provide comparably satisfactory functional outcomes, without significant differences [71].
- Patients with nondisplaced or minimally displaced fractures without any block to forearm rotation should be treated nonoperatively [66].
- Indications for nonoperative treatment include less than 2 mm of displacement, no block to forearm rotation, and involvement of less than 30% of the articular surface [66].
- Relative contraindications for nonoperative treatment include an incarcerated intra-articular fragment, a block to forearm rotation, and fractures with concomitant injuries associated with elbow instability or disruption of the interosseous membrane [66].
- Patients can be initially immobilized based on symptoms for comfort for a short period of time (a week or less) and then active motion is encouraged with the use of a sling as needed [66].
- Treatment of radial head fractures in flexion casts should be avoided, as patients immobilized in a flexion cast had a significantly reduced range of movement compared with patients immobilized in extension [61].
- Immobilization greater than 2 weeks resulted in loss of extension [66].
- The most encountered adverse outcome in nonoperatively treated Mason 1 radial head fractures is elbow stiffness, due to elbow capsular contracture [66].
- Aspiration of a hematoma with or without a local anesthetic can provide immediate pain relief and improve the quality of the physical examination if the patient is unable to tolerate a range of motion examination [66].
- A prospective randomized controlled trial of 180 patients with simple radial head fractures reported that immobilization for 2 days with a sling followed by active mobilization had superior results in motion, strength, and functional outcomes compared with immediate mobilization and immobilization for 8 days [76].
- A fragment displaced more than 4 mm or angulated more than 30° resulted in an impaired outcome in the nonsurgical management of minimally displaced radial head fractures [76].
- There is insufficient evidence to draw definitive conclusions on optimal treatment of type II-IV radial head fractures [13].
Operative Management: General Indications
- Displaced unstable fractures require restoration of radiocapitellar contact via reconstruction or prosthetic replacement to prevent elbow instability [11].
- Patients with displaced radial head fractures with a block to motion, comminuted fragments, associated elbow instability, or retained intra-articular fragments may benefit from operative intervention [47].
- Patients with displaced radial head fractures with a block to motion, those who have concomitant injuries which require surgical intervention such as unstable fracture-dislocations, or those with retained intra-articular loose bodies are best treated surgically [77].
- Surgical treatment is indicated when fragment displacement or malalignment is sufficient to block elbow motion [72].
- The main types of surgical intervention for treating radial head fractures are open reduction and internal fixation (ORIF), resection and radial head replacement [27].
- Recommendations for surgical treatment of radial head and neck fractures according to the Mason classification can now be given with the best available evidence [25].
Operative Management: Fragment Excision
- Fragment excision can be used in patients with a block to forearm motion and a small displaced articular fracture of the radial head (<25% of the articular diameter) [47].
- Fragment excision is indicated in patients with a block to forearm motion by a small (less than 25% of the articular diameter) nonreconstructible displaced articular fracture of the radial head [77].
- The excision of large fragments of the radial head can cause painful clicking and contribute to instability in the setting of concomitant bony and ligament injuries as a consequence of loss of concavity–compression stability of the radiocapitellar joint [77].
- If fragment excision is chosen, the surgeon must ensure that the radial head defect does not engage the proximal radioulnar joint because this can cause pain and promote stiffness [72].
- Displaced fragments can be removed either arthroscopically or using standard open surgical techniques [77].
- ARIF is a safe and viable option for treating displaced radial head fractures [35].
Operative Management: Radial Head Resection
- Complete radial head excision can be considered for isolated displaced multifragmentary radial head fractures that are not amenable to internal fixation [47].
- The radial head should not be excised in the presence of concomitant ligamentous or bony injury, as doing so will lead to loss of radiocapitellar contact forces and precipitate instability [47].
- If excision is to be performed, the push–pull test intraoperatively should have no more than 2 to 4 mm of movement of the radius and a careful fluoroscopic examination should be performed to rule out any signs of instability [47].
- Even in the presence of intact collateral ligaments, excision alone has been shown to alter elbow kinematics and thus is infrequently performed [47].
- Radial head excision may be considered for isolated displaced fractures of the radial head that are not amenable to internal fixation [77].
- If excision is planned, a careful examination under anesthesia is mandatory to evaluate for the presence of elbow or forearm instability [77].
- Even in the presence of intact collateral ligaments, radial head excision has been documented to alter load transfer and kinematics across the elbow [77].
- In the presence of a stable elbow, good long-term outcomes have been reported for excision [72].
- If ligament instability is ignored or underestimated, then radial head excision will potentiate MCL laxity following injury [72].
- Lack of normal radial head-capitellum contact prevents this joint from providing posterolateral rotatory stability in the LUCL-deficient elbow and absorbing and dissipating longitudinal loads along the forearm [72].
- In the absence of this protective function, any interosseous membrane injury is rendered vulnerable to poor or incomplete healing, the consequence of which can be the dreaded proximal migration of the radius, with concomitant ulnar abutment syndrome [72].
- Excision therefore should be avoided when ligamentous instability is present [72].
- A higher incidence of radiographically demonstrated posttraumatic osteoarthritis in the ulnotrochlear joint has been reported after radial head excision [72].
- For the most part, these radiographic arthritic changes do not correlate with clinical symptoms [72].
- RHR is the safest choice to minimize postoperative complications and enable patients to perform all daily life activities [56].
Operative Management: Open Reduction and Internal Fixation (ORIF)
- ORIF with either low-profile plates or screws allows a stable anatomic reduction while preserving soft tissue attachments to fragments [47].
- Clear indications for ORIF include displaced, noncomminuted fractures of the radial head that impede rotation, or those associated with dislocation [47].
- Fractures with greater than 2 mm of displacement and greater than 30% of the articular surface (Mason II fractures) are indications for operative fixation; however, this remains controversial [47].
- The best candidates for ORIF are young patients with three or fewer fragments and good articular cartilage [47].
- Plates and screw fixation is predominantly used; however, malpositioned fixation can impede motion [47].
- Attempted fixation when there are more than three fragments can be fraught with fragment nonunion, osteonecrosis, failure of fixation, and unpredictable forearm motion requiring subsequent hardware removal [47].
- In young patients, the risks of ORIF needs to be weighed against the long-term effects of radial head arthroplasty [47].
- With surgical dissection, care should be taken to preserve all soft tissue attachments if possible [47].
- Reduction can be provisionally held with Kirschner wires and articular impaction and voids can be addressed with bone grafting if needed [47].
- After reduction, plates (either precontoured or mini-fragment plates) should be applied to the anatomic safe zone; however, due to high variability of patient anatomy, even precontoured plates need to be adjusted [47].
- Headless (1.5 to 2.4 mm) screws or countersunk headed screws can be inserted in a tripod configuration and has been shown to have less stiffness and less need for implant removal relative to plates; however, screw fixation may be unstable in the presence of comminution [47].
- Reports of widely displaced fractures devoid of soft tissue attachments reconstructed on the back table and then secured to the remaining head and neck has been described [47].
- The indications for ORIF remain controversial [77].
- Clear indications for ORIF include displaced, noncomminuted fractures of the radial head limit forearm rotation, or radial head fractures fixed as a component of the surgical repair of an elbow fracture-dislocation [77].
- It has been suggested that fractures displaced greater than 2 mm and involving greater than 30% of the articular surface (a type II fracture in the modified Mason classification) might be best treated with surgery; however, this remains unproven [77].
- In one nonrandomized comparative study, the complication rates were higher in patients managed with ORIF relative to nonoperative treatment, while the clinical outcome was better in the patients treated nonoperatively [77].
- The best candidates for internal fixation are younger patients with good-quality bone with three or fewer fragments [77].
- The management of partial articular fractures tends to be more successful than complete fractures of the radial head and neck likely due to both improved stability with partial articular fractures and compromised vascularity with complete fractures of the radial neck [77].
- Low-profile tripod screw fixation has been shown to provide improved results relative to plate fixation; however, screw fixation alone is only indicated for radial neck fractures without comminution [77].
- ORIF of comminuted radial head fractures gained popularity during the 1990s as the need to restore radiocapitellar contact and congruence was recognized [72].
- The use of ORIF has fallen out of favor because of technical difficulties, posterior interosseous nerve injury, osteonecrosis of fracture fragments, and fixation failure, even with the advent of modern, site-specific implants [72].
- A 2002 study showed that the fixation of radial head fractures with more than three fragments, or of those in which fragment diastasis or severe impaction was present, resulted in poor outcomes [72].
- This study suggested that, under such circumstances, radial head arthroplasty was preferred [72].
- A recent meta-analysis of randomized trials of radial head arthroplasty versus ORIF confirmed this conclusion [72].
- Radial head fractures with more than three fragments are often not amenable to open reduction and internal fixation because of small fragment size, comminution, and osteopenia [76].
- In the younger, active population, an initial attempt at fixation is appropriate [76].
- Avoid fixation when greater than three fragments if possible [28].
- Avoid fixation in severely comminuted fractures and in osteoporotic bone [28].
- Stable fixation with low-profile plates and/or screws angling into the neck is recommended for ORIF [28].
- Address all other bony and ligamentous pathology if present to avoid any postoperative elbow instability [28].
- Have a low threshold to use radial head arthroplasty especially in the setting of associated elbow instability [28].
- Early motion is recommended to prevent stiffness after ORIF [28].
- Avoid plate fixation, and only use it in the “safe zone” of radial head/neck to prevent stiffness [28].
- Removal of hardware can help to increase motion after ORIF [28].
- Avoid stripping of articular fragments to prevent avascular necrosis [28].
- Maintain periosteal attachment to prevent avascular necrosis [28].
- Maintain forearm in pronation during approach to prevent posterior interosseous nerve injury [28].
- Avoid anterior and medial aggressive retraction to prevent posterior interosseous nerve injury [28].
- Do not dissect distal to biceps tuberosity to prevent posterior interosseous nerve injury [28].
Operative Management: Radial Head Arthroplasty
- In the setting of an irreconstructable radial head and neck fracture, radial head arthroplasty is an excellent option in restoring radiocapitellar contact and elbow stability [47].
- Prosthetic head and stems have a wide variety of height, size, and offset to best replicate native radial heads [47].
- Radial head arthroplasty is preferred in the setting of unreconstructible comminuted radial head fractures due to the high incidence of associated ligamentous and bony injuries [77].
- Radial head arthroplasty should not be performed in the setting of gross wound contamination, if the radial neck cannot be reconstructed to accept an implant, or if the capitellum is deficient or missing from an associated injury [77].
- The management of acute unreconstructable fractures of the radial head in unstable elbow injuries with radial head replacement has a high risk of reoperation, with the peak risk appearing within 1 year after implantation [7].
- For radial head arthroplasties, acute trauma is the most common indication and Radial Head System the most commonly used implant [20].
- This study suggests that RHA is the best treatment of choice for efficacy and safety in the treatment of comminuted radial head fracture [56].
- Radial head implant arthroplasty has gained more acceptance for more comminuted fractures, or for those associated with elbow or forearm instability, as outcomes from resection arthroplasty and ORIF have demonstrated to be unreliable or unpredictable [72].
- To maximize elbow stability, radial head arthroplasty is an option, which is especially important for complex instability patterns [76].
- A report of 10-year follow-up of 16 patients treated with radial head arthroplasty showed promising midterm results, with no development of instability, loss of range of motion, or increased pain compared with the same cohort at 2-year follow-up [76].
- However, 2 of the 17 patients did develop radiographic osteoarthritis of the ulnohumeral joint [76].
- Implant options include monoblock or bipolar prostheses, smooth stems or porous-coated, and cemented or noncemented fixation [76].
- A prospective study comparing the performance of smooth stems with that of porous-coated, press-fit stems found no difference in functional outcome or range of motion, but found a higher rate of radiographic and symptomatic loosening in press-fit stems [76].
- A recent meta-analysis also found that rigidly fixed stems, with cement fixation or porous-coated press-fit options, had a higher rate of revision and complications [76].
- However, a second meta-analysis found that the lowest rates of implant revision were with cemented stems, compared with porous-coated or smooth stems [76].
- Further studies are needed to determine optimal implant design [76].
- Deliver radial neck atraumatically and avoid forced retractor placement behind the neck to prevent posterior interosseous nerve injury during arthroplasty [28].
- Measure size of radial head diameter and thickness and downsize from measured size to avoid implant size mismatch/overstuffing [28].
- Evaluate radiographically the relationship of the implant to the PRUJ and the coronoid to avoid implant size mismatch/overstuffing [28].
- Fluoroscopic evaluation of the ulnohumeral joint to avoid gapping is recommended during arthroplasty [28].
- Stability examination should be performed with trial as well as final implant during arthroplasty [28].
- Maintain forearm in pronation during approach to prevent posterior interosseous nerve palsy during arthroplasty [28].
- Avoid anterior and medial aggressive retraction to prevent posterior interosseous nerve palsy during arthroplasty [28].
- Do not dissect distal to biceps tuberosity to prevent posterior interosseous nerve palsy during arthroplasty [28].
- Early motion is recommended to prevent stiffness after arthroplasty [28].
- Avoiding overstuffing of the joint is recommended to prevent stiffness after arthroplasty [28].
Pediatric Considerations
- Thirteen percent of patients with radial neck fractures require operative treatment, 21% of which heal with fair or poor outcomes [30].
- Isolated radial head fractures in children are rare because the immature radial head is cartilaginous [46].
- When they do occur, they usually are Salter-Harris type IV injuries in children 10 to 12 years of age [46].
- Patients with true radial head fractures are at increased risk of progressive radial head subluxation, osteonecrosis, and radiocapitellar arthrosis and need to be followed long term [46].
- Most children sustain fractures of the radial neck, which account for approximately
Complications
Associated Injuries
- Radial head fractures are frequently accompanied by associated osseous injuries [6].
- Concomitant lesions are present in nearly 80% of multi-fragment fractures, particularly Type III fractures [26].
Surgical Complications and Reoperation
- Long-term outcomes for radial head arthroplasty are satisfactory; however, there is a high complication and revision rate, resulting in implant survival of 75.1% at 18 years with the highest annual failure rate observed in the first postoperative year [48].
- Although radial head arthroplasty for fractures has a high potential for reoperation within the first year, survival rates with uncemented implants remain high at 10 years [39].
- Overlengthening is a complication of radial head replacement [79].
- The complications of radial head fractures are characteristic to their classification [5].
Implant and Treatment Outcomes
- Radial head replacement is recommended for comminuted fractures with satisfactory medium- and long-term results, though bipolar-cemented implants show lower revision rates [29].
- Midterm outcomes of EVOLVE radial head prosthesis are satisfactory, and associated complication rates are low [49].
- Concomitant elbow fractures or dislocations do not affect the longer term outcomes of patients with unreconstructable radial head fractures requiring radial head arthroplasty [52].
- If impingement symptoms of radial head develop, secondary resection yields good results [24].
Non-Operative and Historical Context
- The fear of causing inferior radio-ulnar subluxation by radial-head excision complicates the treatment decision for radial head fractures [86].
Recovery
- Most fractures of the radial head are stable and managed non-operatively with good long-term results [11].
- Patients report excellent Quick Disability of the Arm, Shoulder, and Hand scores at long-term follow-ups after radial head arthroplasty, despite any need for reoperation [39].
- Long-term outcomes for radial head arthroplasty are satisfactory [48].
- There is a high complication and revision rate for radial head arthroplasty [48].
- Implant survival for monopolar radial head replacement is 75.1% at 18 years [48].
- The highest annual failure rate for monopolar radial head replacement is observed in the first postoperative year [48].
- Midterm outcomes of EVOLVE radial head prosthesis are satisfactory [49].
- Associated complication rates for EVOLVE radial head prosthesis are low [49].
- Thirteen percent of patients with radial neck fractures require operative treatment [30].
- Twenty-one percent of patients with radial neck fractures who require operative treatment heal with fair or poor outcomes [30].
- The outcomes of the use of biodegradable implants for isolated radial head fractures were comparable to those of metallic implants [93].
- Biodegradable implants for isolated radial head fractures are associated with a longer average time to fracture union compared to metallic implants [93].
Key Evidence
- [L5] The challenge in the coming years will be to perform high-level clinical studies to obtain consensus regarding the most appropriate treatment for comminuted radial head fractures. [1] (10.1007/s00264-018-4082-9)
- [L4] The purpose of this article was to provide an overview of current concepts of the management of radial head fractures. [2] (10.5312/wjo.v6.i11.954)
- [L4] Radial head implants offer a reliable treatment for complex Mason type III and IV fractures, with good functional and survival outcomes and a low incidence of complications. [4] (10.1016/j.jse.2025.05.038)
- [L4] The complications of radial head fractures are characteristic to their classification. [5] (10.1016/j.jse.2018.11.047)
- [L4] Radial head fractures are common and frequently accompanied by associated osseous injuries. [6] (10.1016/j.jse.2009.10.015)
- [L4] The management of acute unreconstructable fractures of the radial head in unstable elbow injuries with radial head replacement has a high risk of reoperation, with the peak risk appearing within 1 year after implantation. [7] (10.1097/corr.0000000000000876)
- [L3] It is important to determine which structures need to be repaired to avoid complications that could lead to elbow instability. [8] (10.1016/j.jse.2019.07.006)
- [L4] Long-term patient-reported outcomes were excellent following the nonoperative management of isolated stable fractures of the radial head or neck. [9] (10.2106/jbjs.m.01354)
- [L2] Subsequent radiographs during nonoperative treatment of isolated radial head or neck fractures were unhelpful and might contribute to overtreatment. [10] (10.1016/j.jse.2016.03.007)
- [L5] Most fractures of the radial head are stable and managed non-operatively with good long-term results, while displaced unstable fractures require restoration of radiocapitellar contact via reconstruction or prosthetic replacement to prevent elbow instability. [11] (10.1302/0301-620x.95b2.29877)
- [Paper] The absence of the cortical irregularity can be used to correctly identify a non-fractured radial head. [12] (10.1007/s00402-016-2496-7)
- [L2] There is insufficient evidence to draw definitive conclusions on optimal treatment of type II-IV radial head fractures. [13] (10.1007/s00402-006-0240-4)
- [L5] Clinical outcome studies of metallic radial head arthroplasty systems indicate that head replacement is a reasonable option to offer patients with comminuted radial head fractures and complex elbow trauma. [14] (10.1016/j.jhsa.2005.12.005)
- [L4] Radial head and neck fractures have distinct epidemiological characteristics, and consideration for osteoporosis in a subset of patients is recommended. [16] (10.1016/j.jhsa.2011.09.034)
- [L4] Associated injuries must be considered carefully when treating radial head fractures. [17] (10.1097/01.blo.0000180606.30981.78)
- [L3] For radial head arthroplasties, acute trauma is the most common indication and Radial Head System the most commonly used implant. [20] (10.1177/1758573220987843)
- [L4] The incidence of associated, osseous injuries of the upper limb in radial head fractures is high. [22] (10.1007/s11751-008-0038-8)
- [L5] Adequate knowledge of the surgical indications, types of implants, and surgical technique are essential for a satisfactory outcome when a radial head prosthesis is used for the treatment of nonreconstructable radial head fractures. [23] (10.5435/jaaos-22-10-633)
- [L3] If impingement symptoms of radial head develop, secondary resection yields good results. [24] (10.1016/j.jse.2011.02.002)
- [L1] Recommendations for surgical treatment of radial head and neck fractures according to the Mason classification can now be given with the best available evidence. [25] (10.1016/j.injury.2013.04.003)
- [L4] [26] (10.1016/j.otsr.2015.06.026)
- [L1] [27] (10.1002/14651858.cd008987.pub2)
- [L4] Radial head replacement is recommended for comminuted fractures with satisfactory medium- and long-term results, though bipolar-cemented implants show lower revision rates. [29] (10.1016/j.injury.2013.09.019)
- [L4] Thirteen percent of patients with radial neck fractures require operative treatment, 21% of which heal with fair or poor outcomes. [30] (10.1097/bpo.0000000000000387)
- [L5] [34] (10.1530/eor-24-0035)
- [L4] ARIF is a safe and viable option for treating displaced radial head fractures. [35] (10.1016/j.xrrt.2024.08.001)
- [L4] Although radial head arthroplasty for fractures has a high potential for reoperation within the first year, survival rates with uncemented implants remain high at 10 years, and patients report excellent Quick Disability of the Arm, Shoulder, and Hand scores at long-term follow-ups, despite any need for reoperation. [39] (10.1016/j.jhsa.2023.04.020)
- [L4] When a radial head fracture is present, the wrist should be carefully examined for a scaphoid fracture, and vice versa. [40] (10.1054/jhsb.2000.0495)
- [L1] Based on the current evidence, conservative management of isolated Mason II radial head fractures yields favorable therapeutic outcomes with a low incidence of complications. [41] (10.1186/s13018-024-05039-6)
- [L3] Ultrasound imaging proved to be an effective method for diagnosing occult fractures of the radial head or neck when initial radiograms showed only intraarticular effusion. [45] (10.1016/j.injury.2015.10.050)
- [L3] Long-term outcomes for radial head arthroplasty are satisfactory; however, there is a high complication and revision rate, resulting in implant survival of 75.1% at 18 years with the highest annual failure rate observed in the first postoperative year. [48] (10.1016/j.jse.2020.11.031)
- [L2] Midterm outcomes of EVOLVE radial head prosthesis are satisfactory, and associated complication rates are low. [49] (10.1177/1758573219850111)
- [L4] The study also provided a treatment algorithm for radial head and neck fractures. [50] (10.1016/j.jseint.2024.09.031)
- [L3] Overall reoperation rates are high in patients undergoing operative treatment of radial head and neck fractures. [51] (10.1177/1558944719837691)
- [L3] Concomitant elbow fractures or dislocations do not affect the longer term outcomes of patients with unreconstructable radial head fractures requiring radial head arthroplasty. [52] (10.1016/j.jse.2017.06.031)
- [L5] This study described the relationship between the coronoid and radial head, noting that the difference in radiographic height between the tip of the coronoid and anterior radial head in the normal elbow averages 5 mm. [53] (10.1016/j.jse.2021.05.025)
- [L1] This study suggests that RHA is the best treatment of choice for efficacy and safety in the treatment of comminuted radial head fracture, while RHR is the safest choice to minimize postoperative complications and enable patients to perform all daily life activities. [56] (10.1007/s12306-020-00679-3)
- [L5] The ligaments have the most marked influence on stability, particularly when the upper limb is positioned such that valgus and varus gravity loads are applied to the elbow. [59] (10.1016/j.jse.2004.09.034)
- [L1] [61] (10.1016/0020-1383(94)90154-6)
- [L4] [68] (10.5312/wjo.v4.i2.80)
- [L4] ORIF and nonoperative treatment of isolated Mason type II radial head fractures provide comparably satisfactory functional outcomes, without significant differences. [71] (10.1016/j.jse.2020.10.011)
- [L3] The results of this study suggest that in terrible triad injuries, the imaging appearance of radial head fractures has no measurable influence on treatment recommendations. [74] (10.5397/cise.2022.01368)
- [L4] [75] (10.1007/s11999-007-0064-8)
- [L4] The review aims to shed light into overlengthening as a complication of radial head replacement and to help identify and treat it. [79] (10.1007/s00402-020-03619-9)
- [L5] The intraoperative decision to fix or replace the radial head is critical to optimize treatment outcomes. [81] (10.1016/j.hcl.2004.06.003)
- [L4] The study shows a positive association between radiographic findings and patient symptoms for postoperative complications after radial head arthroplasty, validating radiography as the preferred postsurgical modality of imaging. [82] (10.2214/ajr.11.7674)
- [L3] Anatomic radial head replacement has a risk of radiographic technical mistakes that correlate to poorer outcomes. [85] (10.1016/j.jseint.2026.101671)
- [L4] [86] (10.2106/00004623-196648060-00003)
- [L3] Our study demonstrates significant radiographic differences between two frequently used radial head arthroplasty implants. [91] (10.1097/bot.0000000000000876)
- [L4] [92] (10.5435/jaaosglobal-d-19-00055)
- [Paper] The outcomes of the use of biodegradable implants for isolated radial head fractures were comparable to those of metallic implants along with a longer average time to fracture union for biodegradable implants. [93] (10.1016/j.injury.2019.08.005)
References
[1] Radial head arthroplasty: a historical perspective. International Orthopaedics. 2018. DOI: 10.1007/s00264-018-4082-9
[2] Current concepts in the management of radial head fractures. World Journal of Orthopedics. 2015. DOI: 10.5312/wjo.v6.i11.954
[4] Long-term survival of Acumed anatomical radial head implant for Mason type III-IV fractures: a 15-year follow-up. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2025.05.038
[5] Surgical revision of radial head fractures: a multicenter retrospective analysis of 466 cases. Journal of Shoulder and Elbow Surgery. 2019. DOI: 10.1016/j.jse.2018.11.047
[6] The epidemiology of radial head fractures. Journal of Shoulder and Elbow Surgery. 2010. DOI: 10.1016/j.jse.2009.10.015
[7] High Risk of Further Surgery After Radial Head Replacement for Unstable Fractures: Longer-term Outcomes at a Minimum Follow-up of 8 Years. Clinical Orthopaedics & Related Research. 2019. DOI: 10.1097/corr.0000000000000876
[8] Isolated displaced type II partial articular radial head fracture: correlation of preoperative imaging with intraoperative findings of lateral ulnar collateral ligament tear. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2019.07.006
[9] Long-Term Outcomes of Isolated Stable Radial Head Fractures. Journal of Bone and Joint Surgery. 2014. DOI: 10.2106/jbjs.m.01354
[10] The yield of subsequent radiographs during nonoperative treatment of radial head and neck fractures. Journal of Shoulder and Elbow Surgery. 2016. DOI: 10.1016/j.jse.2016.03.007
[11] Fractures of the radial head. The Bone & Joint Journal. 2013. DOI: 10.1302/0301-620x.95b2.29877
[12] The cortical irregularity in the transition zone of the radial head and neck: a reliable radiographic sign of an occult radial head fracture. Archives of Orthopaedic and Trauma Surgery. 2016. DOI: 10.1007/s00402-016-2496-7
[13] Radial head fractures: effectiveness of conservative treatment versus surgical intervention. Archives of Orthopaedic and Trauma Surgery. 2006. DOI: 10.1007/s00402-006-0240-4
[14] Radial Head Arthroplasty. The Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsa.2005.12.005
[16] The Epidemiology of Radial Head and Neck Fractures. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2011.09.034
[17] Associated Injuries Complicating Radial Head Fractures. Clinical Orthopaedics and Related Research. 2005. DOI: 10.1097/01.blo.0000180606.30981.78
[18] Aaos Comprehensive Orthopaedic Review 3. Fractures of the Elbow > I. Radial Head Fractures.
[19] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > FRACTURE OF THE RADIAL HEAD (ICD-9:813.05).
[20] A registry study on radial head arthroplasties in the Netherlands: Indications, types and short-term survival. Shoulder & Elbow. 2021. DOI: 10.1177/1758573220987843
[21] Rockwood And Green S Fractures In Adults. 40: Fractures of the Proximal Forearm: Olecranon, Proximal Radius, and Radial Head > Assessment of Olecranon Fractures.
[22] The incidence of associated fractures of the upper limb in fractures of the radial head. Strategies in Trauma and Limb Reconstruction. 2008. DOI: 10.1007/s11751-008-0038-8
[23] Radial Head Arthroplasty. Journal of the American Academy of Orthopaedic Surgeons. 2014. DOI: 10.5435/jaaos-22-10-633
[24] Management of the radial head and linked total elbow arthroplasty. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2011.02.002
[25] Clinical results after different operative treatment methods of radial head and neck fractures. Injury. 2013. DOI: 10.1016/j.injury.2013.04.003
[26] Radial head replacement in adults with recent fractures. Orthopaedics & Traumatology: Surgery & Research. 2016. DOI: 10.1016/j.otsr.2015.06.026
[27] Surgical interventions for treating radial head fractures in adults. Cochrane Database of Systematic Reviews. 2013. DOI: 10.1002/14651858.cd008987.pub2
[28] Rockwood And Green S Fractures In Adults. 40: Fractures of the Proximal Forearm: Olecranon, Proximal Radius, and Radial Head > Potential Pitfalls and Preventive Measures.
[29] Radial head, radiocapitellar and total elbow arthroplasties: A review of recent literature. Injury. 2014. DOI: 10.1016/j.injury.2013.09.019
[30] Radial Neck Fractures in Children and Adolescents. Journal of Pediatric Orthopaedics. 2016. DOI: 10.1097/bpo.0000000000000387
[33] Tachdjian S Pediatric Orthopaedics From The Texas Scottish Rite Hospital For Children E Book. Pigmented Villonodular Synovitis and Giant Cell Tumor of the Tendon Sheath > Radial Head and Neck Fractures.
[34] Which radial head fractures are best treated surgically?. EFORT Open Reviews. 2024. DOI: 10.1530/eor-24-0035
[35] Arthroscopic reduction internal fixation for displaced radial head fractures: a systematic review of the outcomes and complications. JSES Reviews, Reports, and Techniques. 2024. DOI: 10.1016/j.xrrt.2024.08.001
[39] Radial Head Arthroplasty for Fracture: Implant Survivorship and Outcomes at Mean Follow-Up of 8 Years. The Journal of Hand Surgery. 2025. DOI: 10.1016/j.jhsa.2023.04.020
[40] The Incidence of Simultaneous Fractures of the Scaphoid and Radial Head. Journal of Hand Surgery. 2001. DOI: 10.1054/jhsb.2000.0495
[41] Comparison of operatively and nonoperatively treated isolated mason type II radial head fractures: a systematic review and meta-analysis. Journal of Orthopaedic Surgery and Research. 2024. DOI: 10.1186/s13018-024-05039-6
[42] Rockwood And Green S Fractures In Adults. 39: Elbow Dislocations and Terrible Triad Injuries > Radial Head Fractures.
[45] Diagnosis of occult radial head and neck fracture in adults. Injury. 2015. DOI: 10.1016/j.injury.2015.10.050
[46] Campbell S Operative Orthopaedics 4 Volume Set. OPEN REDUCTION AND INTERNAL FIXATION FOR DISPLACED OR ENTRAPPED MEDIAL EPICONDYLE > RADIAL HEAD AND NECK FRACTURES.
[47] Rockwood And Green S Fractures In Adults. 40: Fractures of the Proximal Forearm: Olecranon, Proximal Radius, and Radial Head > Operative Treatment of Radial Head and Neck Fractures.
[48] Long-term outcome and survival rate of monopolar radial head replacement. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2020.11.031
[49] Midterm outcomes of 146 EVOLVE Proline modular radial head prostheses: a systematic review. Shoulder & Elbow. 2019. DOI: 10.1177/1758573219850111
[50] A proposal for computed tomography–based algorithm for the management of radial head and neck fractures: the Proximal and Articular Radial fractures Management (PARMa) classification. JSES International. 2025. DOI: 10.1016/j.jseint.2024.09.031
[51] Reoperation Rates and Costs of Radial Head Arthroplasty Versus Open Reduction and Internal Fixation of Radial Head and Neck Fractures: A Retrospective Database Study. HAND. 2019. DOI: 10.1177/1558944719837691
[52] The effect of associated fractures/dislocations on outcomes of unreconstructable radial head fractures managed with radial head arthroplasty: a cohort comparison. Journal of Shoulder and Elbow Surgery. 2017. DOI: 10.1016/j.jse.2017.06.031
[53] Computed tomography analysis of the relationship between the coronoid and the radial head. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2021.05.025
[56] Clinical outcomes after internal fixation, arthroplasty and resection for treatment of comminuted radial head fractures: a systematic review and network meta-analysis. MUSCULOSKELETAL SURGERY. 2020. DOI: 10.1007/s12306-020-00679-3
[59] Kinematics and stability of the fractured and implant-reconstructed radial head. Journal of Shoulder and Elbow Surgery. 2005. DOI: 10.1016/j.jse.2004.09.034
[60] Green S Operative Hand Surgery. Radial Head.
[61] The non-operative management of radial head fractures: a randomized trial of three treatments. Injury. 1994. DOI: 10.1016/0020-1383(94)90154-6
[65] Rockwood And Green S Fractures In Adults. 40: Fractures of the Proximal Forearm: Olecranon, Proximal Radius, and Radial Head > Radial Head and Neck Fractures.
[66] Rockwood And Green S Fractures In Adults. 40: Fractures of the Proximal Forearm: Olecranon, Proximal Radius, and Radial Head > Treatment Options for Radial Head and Neck Fractures.
[68] Incidence and analysis of radial head and neck fractures. World Journal of Orthopedics. 2013. DOI: 10.5312/wjo.v4.i2.80
[71] The treatment of isolated Mason type II radial head fractures: a systematic review. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2020.10.011
[72] Orthopaedic Knowledge Update Trauma. Fractures of the Proximal Radius and Ulna and Dislocations of the Elbow > Radial Head and Neck Fractures > Treatment.
[74] Variation in radial head fracture treatment recommendations in terrible triad injuries is not influenced by viewing two-dimensional computed tomography. Clinics in Shoulder and Elbow. 2023. DOI: 10.5397/cise.2022.01368
[75] Documentation of Associated Injuries Occurring With Radial Head Fracture. Clinical Orthopaedics & Related Research. 2008. DOI: 10.1007/s11999-007-0064-8
[76] Orthopaedic Knowledge Update Sports Medicine 6. Acute/Traumatic Elbow Injuries > Radial Head Fractures.
[77] Rockwood And Green S Fractures In Adults. 39: Elbow Dislocations and Terrible Triad Injuries > Operative Treatment of Radial Head Fractures.
[79] Overlengthening of the radial column in radial head replacement: a review of the literature and presentation of a classification system. Archives of Orthopaedic and Trauma Surgery. 2020. DOI: 10.1007/s00402-020-03619-9
[81] Management of comminuted radial head fractures with replacement arthroplasty. Hand Clinics. 2004. DOI: 10.1016/j.hcl.2004.06.003
[82] Radial Head Arthroplasty: A Radiologic Outcome Study. American Journal of Roentgenology. 2012. DOI: 10.2214/ajr.11.7674
[85] Hawkins Award 2025: clinical implications of radiological findings associated with radial head replacement. A long-term follow-up study. JSES International. 2026. DOI: 10.1016/j.jseint.2026.101671
[86] Fractures of the Radial Head. The Journal of Bone & Joint Surgery. 1966. DOI: 10.2106/00004623-196648060-00003
[91] Radial Neck Dilatory Remodeling After Radial Head Arthroplasty With an Uncemented, Press Fit, Fully Chemically Etched Stem Design. Journal of Orthopaedic Trauma. 2017. DOI: 10.1097/bot.0000000000000876
[92] The Incidence and Risk Factors of Scaphoid Fracture Associated With Radial Head and Neck Fracture in Trauma Patients. JAAOS: Global Research and Reviews. 2019. DOI: 10.5435/jaaosglobal-d-19-00055
[93] WITHDRAWN: Internal fixation of unstable radial head fracture: A comparison of metallic and biodegradable implants. Injury. 2019. DOI: 10.1016/j.injury.2019.08.005