Clinicians › Elbow
Olecranon Fracture Fixation (ORIF)
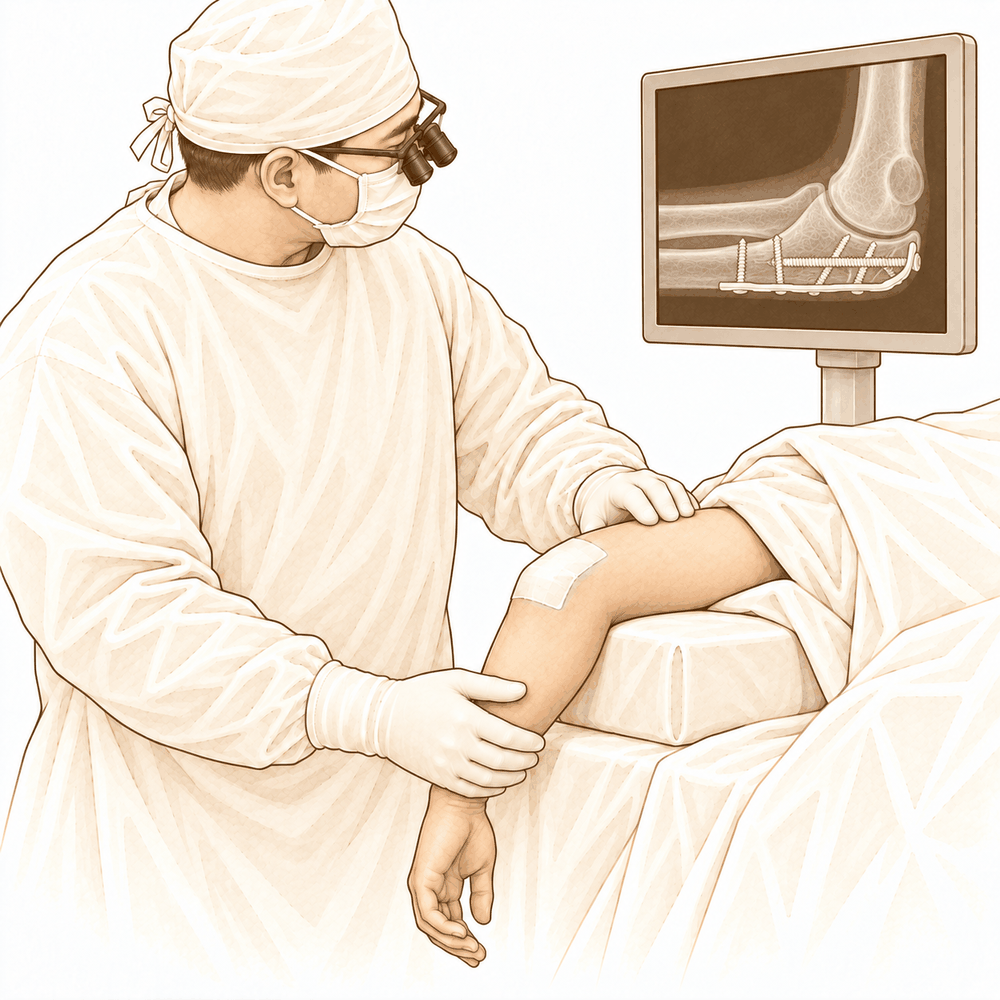
For patients: a plain-language version of this topic is available. See the patient guide.
Overview
Surgical management remains the standard of care for displaced olecranon fractures until more convincing evidence supports nonsurgical treatment [31]. No single technique is suitable for the management of all olecranon fractures [11]. While a majority of olecranon fractures heal uneventfully with good or excellent results, a small loss of motion is expected [9]. The timing of fixation for displaced fractures does not significantly increase the rate of early complications or reoperation [3]. Current randomized evidence suggests that tension band wiring and plate fixation may yield similar functional outcomes, though these findings are based on a limited number of RCTs [20]. No differences were found in clinical or patient-rated outcome measures between tension band wiring and plate fixation for displaced olecranon fractures [8].
Modern fixation techniques may offer superior functional outcomes, faster healing, and fewer complications than traditional tension band wiring [12]. Plate fixation has better efficacy and safety for Mayo II olecranon fractures compared to tension band wire [26]. Internal fixation by cable pin system is associated with a shorter healing time, fewer complications, and better function than tension band wiring [44]. Plating of the olecranon leads to predictable union, though the most common complication was lack of full extension in 39% of patients [6]. Low-profile double-plate osteosynthesis is a safe and effective alternative treatment with excellent subjective and objective clinical outcome measures [5]. Locking-plate osteosynthesis is an effective and safe treatment option for comminuted olecranon fractures, allowing early joint motion and yielding satisfactory radiologic and clinical results [27]. Suture anchor fixation of displaced olecranon fractures resulted in excellent midterm functional outcomes [4]. Suture anchor fixation in the elderly population provides excellent long-term radiographic and clinical outcomes without hardware complications associated with traditional fixation methods [16]. Fixation of simple olecranon fractures with an intramedullary screw is a safe and easy fixation method in young patients, leading to good functional and radiological results [23]. Single 2.7-mm mini-fragment plate fixation of olecranon osteotomies for distal humerus fractures is safe and effective with low rates of revision, hardware removal, and nonunion [21].
Surgical treatment of olecranon fractures is associated with a high rate of complications, and patients undergoing revisions beyond implant removal had poorer functional outcomes [15]. No significant differences in functional outcomes or secondary operations were found with respect to fracture type, gender, or surgical method after open reduction and fixation [15]. Patients who have operative fixation can be counseled that most patients keep their implants, that only 3% experience implant migration, and that technical factors such as the type or configuration of an implant seem less important than personal factors in determining who requests a second surgery for implant removal [1]. Non-operative treatment of olecranon fracture in patients aged ≥75 years provided excellent functional results at 6 months, without associated complications [7]. Displaced olecranon fractures in patients older than 70 years may be effectively managed with nonoperative measures to produce high satisfaction and functional range of motion [25]. Close radiographic follow-up for nonsurgically treated olecranon fractures is recommended [13].
Anatomy & Pathophysiology
Bony Anatomy
The elbow is a trocho-ginglymoid joint comprising medial and lateral articulations that provide bony stability [71]. The ulnohumeral joint forms where the trochlea articulates with the ulna within the greater sigmoid notch [71]. This joint provides highly congruent anatomy through almost 180° of articular contact, with the exception of a bare area on the greater sigmoid notch devoid of cartilage [71]. The trochlea is shaped like a spool with a central sulcus that articulates with the central ridge of the greater sigmoid notch of the proximal ulna [82]. It is covered by articular cartilage anteriorly, inferiorly, and posteriorly, creating an arc of almost 270 degrees [82], or a 300-degree arc of cartilage [79]. The olecranon fossa is located posteriorly and accepts the olecranon during extension, while the coronoid fossa is located anteriorly and accepts the coronoid during flexion [82]. These fossae are separated by a thin bony septum, which is occasionally absent [82]. The proximal ulna contains the olecranon process posteriorly, the coronoid process anteriorly, and the sigmoid or semilunar notch [79]. The coronoid process has medial and lateral facets that buttress the trochlea anteriorly [71]. The sublime tubercle is located just distal and medial to the coronoid and serves as the attachment site for the anterior bundle of the medial ulnar collateral ligament [71].
The radiocapitellar joint is formed by the articulation of the capitellum and radial head [71]. The radial head is a concave elliptical structure covered with articular cartilage along the radiocapitellar joint and approximately 270° of the articular margin [71]. The articular surface of the capitellum encompasses an arc of approximately 180 degrees in the sagittal plane [82]. A portion of the lateral trochlear ridge is covered with articular cartilage but is non-articulating throughout normal elbow range of motion [93]. The proximal radioulnar joint holds the radius in close approximation to the ulna via the annular ligament [71]. The lesser sigmoid notch is the area of the ulna that articulates with the margin of the radial head at the proximal radioulnar joint [71].
The distal humeral articulation is angled 30° from the longitudinal axis [71], or 30 degrees anterior to the humeral shaft axis [77]. The distal humerus consists of medial and lateral columns [77]. The medial column diverges from the humeral shaft at a 45-degree angle [79], or approximately 45 degrees in the coronal plane, and terminates as the medial epicondyle [82]. The lateral column diverges from the humeral shaft at a 20-degree angle [79], or approximately 20 degrees in the coronal plane [82]. The lateral column curves anteriorly creating a 35 to 40 degrees angle with the shaft in the sagittal plane [82]. The posterior aspect of the lateral column is relatively flat and wide, suitable for application of a posterolateral plate [82]. In the coronal plane, the trochlea is more distal than the capitellum, resulting in a valgus alignment of 4 to 8 degrees [82]. The overall elbow valgus angle in extension is 10 to 17 degrees, termed the carrying angle [82]. The distal humerus articular surface is internally rotated 3 to 8 degrees axially [82].
The axis of rotation is angulated 5° to 7° in the coronal plane relative to the epicondylar axis, with the medial side more distal than the lateral side [71]. The olecranon provides a broad attachment site for the triceps posteriorly [71]. The ulna bends approximately 8° medially at 8 cm from the tip of the olecranon [71]. The articulation to the tip of the coronoid is approximately 30° from the long axis of the ulna in the sagittal plane [71].
Ligamentous Anatomy
The medial ulnar collateral ligament (MUCL) is the primary restraint to valgus stress within functional elbow range of motion [77]. It originates on the posterior medial epicondyle and inserts on the sublime tubercle of the medial coronoid process [77]. The anterior bundle of the medial ulnar collateral ligament is the most important component for stability [72], and the most important portion of the medial or ulnar collateral ligament is the anterior portion, which attaches to a small process on the medial surface of the coronoid [79]. The posterior bundle of the medial ulnar collateral ligament becomes taut at flexion beyond 120 degrees [72] and is the primary restraint to valgus stress with the elbow in maximal flexion [77]. Stability in full extension is provided by the medial collateral ligament, joint capsule, and ulnohumeral articulation [77].
The lateral collateral ligament complex consists of the radial collateral ligament, the lateral ulnar collateral ligament, and the annular ligament [82]. The radial collateral ligament originates from an isometric point on the lateral epicondyle and fans out to attach to the annular ligament [82]. The lateral ulnar collateral ligament arises from an isometric point on the lateral epicondyle and attaches to the crista supinatoris of the proximal ulna [82]. The annular ligament attaches to the anterior and posterior margins of the lesser sigmoid notch [82]. The lateral ulnar collateral ligament is the posterolateral stabilizer of the elbow [72]. The lateral collateral ligament complex functions as an important restraint to varus and posterolateral rotatory instability [82].
The supinator-extensor muscle group attaches to the lateral epicondyle, which is slightly proximal and lateral to the capitellum [79]. The ulnar nerve lies in a bony groove covered and restrained by the arcuate ligament posterior to the medial epicondyle [80]. The anterior capsule attaches at a point approximately 6 mm distal to the tip of the coronoid [72]. The capsule allows maximum distension at approximately 70 to 80 degrees of flexion [72].
Muscular Anatomy
The triceps has a broad tendinous insertion into the olecranon posteriorly [79]. The primary elbow extensor, the triceps, inserts on the olecranon process [72]. Muscle insertions of the triceps have three distinct insertional areas to the olecranon corresponding to the posterior capsular insertion, the deep muscular portion, and the superficial tendinous portion [70]. The deep muscular head of the triceps corresponds to the medial head, and the tendinous portion corresponds to the long and lateral heads [70]. The width of the triceps insertion is 2.6 cm and is located 1.1 cm from the tip of the olecranon [70].
The brachialis inserts on the coronoid process and the tuberosity of the ulna anteriorly [79]. The brachialis is the strongest elbow flexor and attaches to the coronoid 11 mm distal to the tip [72]. The medial epicondyle is the origin of the flexor-pronator muscle group and the medial collateral ligament [80]. The lateral epicondyle is the origin of the extensor-supinator muscle group and the lateral collateral ligament complex [80].
Biomechanics and Kinematics
The normal elbow has a range of motion from 0° to 140° from extension to flexion [47], or 0 to 150 degrees [77]. The normal elbow has a range of motion of 75° and 85° in pronation and supination respectively [47], or 80 to 85 degrees in each direction [77]. A functional arc for the elbow is 100° for flexion and extension and forearm rotation [47], or 30 to 130 degrees flexion/extension and 50 degrees pronosupination [77]. The normal valgus carrying angle of the elbow is 5 to 10 degrees for men and 10 to 15 degrees for women [77].
In full extension, 60% of axial load is transmitted through the radiocapitellar joint [77]. Tensile forces are present at the medial elbow and compressive forces at the lateral elbow [72]. The ulnohumeral joint allows flexion and extension of the joint [79]. The radiocapitellar joint allows forearm rotation [79]. With the elbow in 90 degrees of flexion, the medial condyle, lateral condyle, and olecranon form a palpable triangle [79].
Elbow stability is determined by primary and secondary stabilizers [47]. The three primary stabilizers of the elbow are the ulnohumeral articulation, the medial ulnar collateral ligament, and the lateral ulnar collateral ligament complex [47]. Secondary stabilizers of the elbow include the radiocapitellar articulation, common flexor tendon, common extensor tendon, and joint capsule [47].
Pathophysiology and Injury Mechanisms
Olecranon fractures are the most common osseous injury of the elbow joint [41]. Up to 10% of all upper limb fractures involve the olecranon [41], representing about 10% of upper limb fractures [43]. The incidence of olecranon fractures is 12 cases out of 100,000 inhabitants per year [43]. The mean age for olecranon fractures is 57 years with a bimodal distribution [43]. Olecranon fractures show a bimodal distribution occurring in younger patients due to high-energy trauma and in elderly cohorts with low bone quality after low-energy falls [41]. Isolated fractures of the olecranon occur after low-energy trauma, especially in older women over 65 years [22]. Men show a higher proportion of high-energy trauma than women in both age groups [22]. Low-energy mechanisms for olecranon fractures are well-represented all year round but especially in winter [147]. High-energy injuries for olecranon fractures mainly occur in summer [147]. In men, high-energy and low-energy olecranon fractures are more frequent in summer and winter respectively [147].
The fracture mechanism in most cases is a direct impact to the posterior aspect in the range 60° to 110° flexion [41]. Direct trauma patients generally undergo a comminuted fracture [43]. Patients who suffer an indirect trauma undergo a transverse or oblique fracture [43]. Due to tension of the triceps brachii muscle, most olecranon fractures are dislocated and not suitable for conservative treatment [41]. Olecranon fractures lead to loss of function of the extensor system [43]. Disabilities associated with untreated olecranon fractures result from disruption of the extensor mechanism [55]. Functional limitations from untreated olecranon fractures include an inability to reach over the head or to push off [55]. The surgical indication for olecranon fractures is marked displacement, with rare exceptions for severe medical comorbidities [55].
Tension band wiring transforms the triceps’ tensile forces into compressive forces at the fracture site [43]. Fixation must be secure enough to permit early motion to avoid significant stiffness of the elbow joint [19]. The dogma that the elbow should never be immobilised remains valid, and mobilisation should start as early as possible [117]. Lengthening of the olecranon by increments of 2mm correlates positively with loss of elbow extension [111]. Screws placed into or across the olecranon fossa can block elbow extension if they impinge against the tip of the olecranon during attempted elbow extension [80]. The tolerances of the olecranon and coronoid fossae to accommodate their respective bony processes are narrow, so screw placement through the fossae should be avoided to prevent impingement and decreased elbow range of motion [82].
Classification
Multiple classification systems for olecranon fractures exist, including AO, Mayo, Schatzker, and Colton, but none are widely accepted or provide direct and reliable advice on operative strategies [41]. The low reproducibility rates of these existing systems raise questions about their utility in clinical and research contexts [41].
Mayo: The Mayo classification consists of three types with a modifier to indicate comminution, where Type I fractures are nondisplaced, Type II fractures are displaced, and Type III fractures have accompanying injuries [116]. Although designed to simplify categorization of olecranon fractures, the system does not achieve this goal due to poor reproducibility [110].
AO/OTA: The AO classification subsumes olecranon fractures to proximal forearm injuries [41].
Schatzker and Colton: The Schatzker and Colton classifications divide olecranon fractures into groups based on the quantity of fragments and fracture lines [41]. Among the Mayo, AO/OTA, and Colton & Schatzker classifications, the Colton classification demonstrates the best intra- and inter-observer agreement [43].
Other Considerations: A proposed fragment-specific classification system for complex olecranon fractures is anatomically based and considers the deforming forces from ligaments and tendons [54]. In a nationwide study of 2,462 adult olecranon fractures, 303 (12%) were proximal avulsion, 1,044 (42%) were simple central, 717 (29%) were comminuted central, and 398 (16%) were distal olecranon fractures [22]. In a cohort of 321 patients treated with plate fixation, 33 (10.3%) had Mayo Type I fractures, 253 (78.8%) had Mayo Type II fractures, and 35 (10.9%) had Mayo Type III fractures [29]. In a cohort of 30 patients aged 75 years or older with displaced olecranon fractures, 20 were Mayo Type II and 10 were Mayo Type III [57]. In a study of 44 patients treated with Kirschner wires with eyelets, 40 (91%) had Mayo Type IIA fractures and 4 (9%) had Mayo Type IIB fractures [122]. In a retrospective study of 78 patients, 33 were treated with tension band wire (21 type IIA and 12 type IIB) and 45 were treated with plate and screws (10 type IIA and 35 type IIB) according to the Mayo classification [36].
Clinical Presentation
Olecranon fractures typically result from low-energy trauma, a mechanism particularly common in older women over 65 years [22]. The demographic profile of these patients is essentially similar to those sustaining distal radius fractures [34]. While the majority of olecranon fractures heal uneventfully with good or excellent results, a small loss of motion is expected [9]. In the geriatric population, these injuries are associated with higher than expected 1-year mortality rates [56]. Articular impaction is a common feature of olecranon fractures in elderly patients [135].
Epidemiological data indicate that the incidence of olecranon fractures increased by 29% over a 20-year study period in Denmark [38]. Fractures of the ipsilateral olecranon associated with radial neck fractures are not as rare as previously reported [65]. Long-term outcomes show that the median incidence of post-traumatic osteoarthritis following isolated olecranon fractures is 19% at a median follow-up of 41 months [64].
Fracture morphology varies significantly across populations. In a Swedish register study of 2,462 adult olecranon fractures, the distribution was as follows: * Simple central: 42% [22] * Comminuted central: 29% [22] * Distal: 16% [22] * Proximal avulsion: 12% [22]
In a population-based study of 321 patients treated with plate fixation, 78.8% had Mayo Type II fractures and 52.6% had comminuted fracture patterns [29].
Investigations
Plain radiography: Plain radiographs remain the hallmark and best screening test for the evaluation of the elbow [47]. Standard radiographic views for elbow evaluation include AP, lateral, and oblique views [47]. Close radiographic follow-up is recommended for nonsurgically treated olecranon fractures in children [13].
CT: CT is helpful when assessing for malunion architecture and the location and pattern of osteophytes or loose bodies [85]. Three-dimensional CT is used to check for heterotopic ossification [85]. CT is not necessary when elbow stiffness is entirely soft-tissue related [85].
MRI: MRI can be used to evaluate ligaments and tendons, but it is rarely indicated for elbow stiffness [85].
Other Considerations: Electromyography and nerve conduction velocity studies should be performed if there is any question about neurologic dysfunction [85]. An assessment for ulnar nerve subluxation should be performed during the physical examination of the elbow [85]. Aggregate data support the non-operative treatment of isolated undisplaced olecranon fractures with good results [14]. Aggregate data support the operative treatment of olecranon fractures displaced ≥4 mm [14]. The Subjective Elbow Value (SEV) shows a high correlation to the most commonly used scoring systems for outcome evaluation after elbow injury [42].
Treatment
Non-Operative
Nonoperative treatment is a reasonable option for displaced stable olecranon fractures in elderly patients [28]. In elderly and medically unwell patients, nonoperative management of displaced fractures can result in reasonable range of motion, minimal pain, and maintenance of extension against gravity [139]. Close radiographic follow-up is recommended for nonsurgically treated olecranon fractures [13].
Operative
Indications: Surgical treatment of olecranon fractures is associated with a high rate of complications [15]. No single fixation technique is suitable for the management of all olecranon fractures [11]. No significant differences in functional outcomes or secondary operations were found with respect to fracture type, gender, or surgical method for olecranon fractures [15].
Surgical Approach / Technique: Olecranon osteotomy is attractive in its simplicity and remains one of the most popular exposures to the elbow worldwide, particularly for the purpose of managing fractures [128]. The use of wide-awake local anesthesia no tourniquet for olecranon fracture fixation is a simple, safe, low-cost, and reproducible technique that obviates the need for general anesthesia or tourniquets [115]. In comminuted olecranon fracture patterns, the articular portion of the olecranon is often detached from the posterior cortex [157]. In comminuted olecranon fractures, the joint surface may be completely malreduced despite an anatomic reduction of the posterior cortex [157]. A more appropriate reduction technique for comminuted olecranon fractures is to reduce the bone in layers, beginning with the articular surface [157]. In layer-by-layer reduction of comminuted olecranon fractures, the posterior cortex is the last layer, not the first, to be reduced [157].
Implant Selection: Tension band wiring is most appropriate for transverse or oblique fractures without significant comminution [43]. The tension band wiring technique remains the gold standard for the treatment of displaced and minimally comminuted olecranon fractures [62]. Both operative procedures of Kirschner wire tension band combined with anatomical locking plate effectively treat Mayo type II olecranon fractures [2]. When treating isolated, displaced 2-part and multifragmented olecranon fractures, tension band wiring was noninferior compared with plate fixation [45]. Internal fixation by cable pin system is an effective method for olecranon fracture and is associated with a shorter healing time, fewer complications, and better function than tension band wiring [44]. The suture tension band technique is a viable option for managing simple olecranon fractures or fractures with minimal comminution, yielding excellent clinical and radiographic outcomes while avoiding hardware-related complications [24]. Suture fixation is a reliable technique for simple olecranon fractures with low complication and reoperation rates compared to tension band wiring [60]. Transosseous suture with high strength thread is a valid alternative for treating Mayo IIA olecranon fractures in adult patients, decreasing re-operation rates for implant removal [63]. A novel technique using suture tension band fixation with eyelet wires for simple olecranon fractures is hypothesized to yield satisfactory outcomes regarding pain, functional scores, and radiographic union [46]. Tension band wiring may be used for revision of failed olecranon fixation [35]. All fractures in a case series of comminuted olecranon fractures treated with precut K-wires and tension band wiring healed without complications, with excellent elbow range of movements [32]. DSTBW technology provides stable fixation for olecranon fractures, reducing the risk of internal fixation migration and failure [39]. A minimally invasive tension band wiring technique is indicated for the treatment of 2-part transverse olecranon fractures [150]. A screw and minimally invasive tension band wiring technique is used for 2-part oblique olecranon fractures [150]. Methods described for preventing Kirschner wire backing out have been used with satisfactory results on fractures of the olecranon [129]. Plate fixation has better efficacy and safety for Mayo II olecranon fractures [26]. Locked plating of geriatric olecranon fractures with early mobilization leads to low fixation failure in patients over the age of 75 [17]. Surgical treatment with plate fixation and bone grafting in a patient with a displaced olecranon fracture through a persistent physis resulted in bony union, full range of motion, and return to sports without complications at 2.5 years [33]. Dual locking plates display biomechanical properties that suggest that they can be used in the fixation of comminuted olecranon fractures [53]. Cyclic physiological loading of osteoporotic olecranon fracture fixation resulted in sudden, catastrophic failure of the bone-implant interface rather than in gradual implant loosening [52]. Plate fixation is preferred for type IIIB fractures according to the Mayo classification in one department's algorithm [36].
Implant Retention and Complications: Most patients who have operative fixation of a fracture of the olecranon keep their implants [1]. Only 3% of patients with operative fixation of a fracture of the olecranon experience implant migration [1]. Technical factors such as the type or configuration of an implant seem less important than personal factors in determining who requests a second surgery for implant removal [1]. In a cohort of 30 displaced olecranon fractures in patients aged 75-93 years, complications developed in 40% of patients [57]. Of 21 fractures treated by tension-band wiring in patients aged 75-93 years, 33% were followed by complications and 8 required hardware removal [57]. Of 7 hook-plate fixations in patients aged 75-93 years, 71% were followed by complications and 43% required hardware removal [57]. In a cohort of 29 patients aged 75-93 years with displaced olecranon fractures, 37% required revision surgery [57]. Patients undergoing revisions beyond implant removal after olecranon fracture fixation had poorer functional outcomes [15].
Complications
General Outcomes and Union: ORIF for olecranon fractures demonstrates low short-term complication rates [58], with a majority of fractures healing uneventfully to good or excellent results, though a small loss of motion is expected [9]. Plating leads to predictable union [6], and current randomized evidence suggests tension band wiring and plate fixation yield similar functional outcomes for displaced fractures [20]. No differences were found in clinical or patient-rated outcome measures between these two techniques [8]. For Mayo II fractures, plate fixation demonstrates better efficacy and safety [26]. Suture fixation is a reliable technique for simple olecranon fractures, with preliminary evidence suggesting lower complication and reoperation rates compared to tension band wiring [60, 137]. In geriatric patients, locked plating with early mobilization leads to low fixation failure rates [17]. Proximal ulna fracture ORIF carries a low rate of systemic complications, with the most common morbidities being return to the operating room, blood transfusion, and urinary tract infections [158].
Hardware-Related Complications and Reoperation: Implant migration occurs in only 3% of patients following operative fixation [1]. However, hardware removal is extremely common after tension band wiring, with reported rates up to 82% [138, 143]. Tension band wiring may be associated with increased complication rates, with up to 75% of cases being symptomatic [138]. The most common cause of re-operation after tension band wiring is protrusion or migration of K-wires, which causes fracture displacement, pain, skin irritation, and possible wound breakdown [138]. These issues are specifically associated with the subcutaneous position and migration of the K-wires [143]. In one series, 82% of patients required hardware removal following tension band wiring [143]. The most common complication after plating is lack of full extension, observed in 39% of patients [6]. In a cohort of 96 patients undergoing ORIF with a plate and screw construct, 7 patients experienced loss of reduction postoperatively [130].
Infection and Wound Complications: Union delayed by infection and ulnar nerve palsy were reported in up to 10% of cases following tension band wiring [143]. Wound infections occurred in 4.2% of cases among 1,700 olecranon osteotomies [162]. Specific comorbidities, such as smoking and ascites, are associated with an increased risk of short-term complications after ORIF for olecranon fractures [58].
Nerve Palsy: Nerve complications following olecranon fracture fixation include median nerve palsy, anterior interosseous nerve injury, and ulnar neuropathy [138]. Union delayed by ulnar nerve palsy was reported in up to 10% of cases following tension band wiring [143].
Stiffness and Arthrofibrosis: A median osteoarthritis incidence of 19% was identified at a median follow-up of 41 months following isolated olecranon fractures [64]. ROM is typically preserved after reoperation of intra-articular proximal ulna fractures and improves when the indication for reoperation is elbow stiffness [50].
Other Considerations: Other complications following olecranon fracture fixation include delayed union, nonunion, malunion, loss of forearm rotation, heterotopic ossification, and posttraumatic arthrosis [138]. Olecranon fractures in the elderly have higher than expected 1-year mortality rates [56]. Union problems occurred in 3.7% among 1,700 olecranon osteotomies [162]. An ulnar artery pseudoaneurysm after tension band wiring can result in Volkmann's ischemic contracture [141]. Patients undergoing revisions beyond implant removal had poorer functional outcomes [15], although no significant differences in functional outcomes or secondary operations were found with respect to fracture type, gender, or surgical method [15]. A significant proportion of patients (35%) experience subsequent complications after reoperation of intra-articular proximal ulna fractures [50]. Patients treated with a trans-olecranon surgical approach for posterior Monteggia variant fractures demonstrate satisfactory clinical and radiographic outcomes with low rates of heterotopic ossification, nonunion, and infection [161]. Major complications are more common after ORIF than after total elbow arthroplasty in comminuted fractures of the distal humerus [159]. In a randomized trial of distal humerus fractures, 4 of 15 patients (27%) in the ORIF group underwent a second surgical procedure, including hardware removal for pain and ulnar neuritis, irrigation and debridement for wound infection, and conversion to total elbow arthroplasty for nonunion [142].
Recovery
Light activity (weeks): The evidence provided does not specify a typical week range for the resumption of desk work, driving, or light activities of daily living.
Full activity (months): The evidence provided does not specify a typical month range for the return to manual work, sport, or full range of motion and strength.
Complete recovery / outcome plateau (months): The evidence provided does not specify a month range for the stabilization of pain, strength, or final functional outcomes.
Rehabilitation protocol: Operative anatomic fixation with precontoured locked plates is associated with early mobilization in geriatric olecranon fractures [30]. No specific immobilisation duration, weight-bearing progression, or sling/brace removal timing is detailed in the provided evidence.
Functional milestones: A majority of olecranon fractures heal uneventfully with good or excellent results, though a small loss of motion is to be expected after healing [9]. Non-operative treatment in patients aged ≥75 years provided excellent functional results at 6 months [7]. No significant differences in functional outcomes were found with respect to fracture type, gender, or surgical method [15].
Other Considerations: Most patients who undergo operative fixation of a displaced olecranon fracture keep their implants, with only 3% experiencing implant migration [1]. Technical factors such as the type or configuration of an implant seem less important than personal factors in determining who requests a second surgery for implant removal [1]. Non-operative treatment of olecranon fracture in patients aged ≥75 years was without associated complications [7]. Operative anatomic fixation with precontoured locked plates and early mobilization has an acceptable failure rate in geriatric olecranon fractures [30]. More than 80% of patients with olecranon fracture dislocations were able to return to their pre-injury level of activity [145]. Professional baseball players who undergo ORIF of an olecranon fracture have a return to sport rate of 67.5%, which is no different from natural attrition among matched controls [149].
Key Evidence
- [L3] Patients who have operative fixation of a fracture of the olecranon can be counseled that most patients keep their implants, that only 3% experience implant migration, and that technical factors such as the type or configuration of an implant seem less important than personal factors in determining who requests a second surgery for implant removal. [1] (10.1007/s11999-015-4488-2)
- [L3] Both operative procedures effectively treat Mayo type II olecranon fractures. [2] (10.1186/s12891-025-08843-1)
- [L3] The timing of fixation of displaced olecranon fractures does not significantly increase the rate of early complications or reoperation. [3] (10.1016/j.jhsg.2023.09.002)
- [L4] Suture anchor fixation of displaced olecranon fractures resulted in excellent midterm functional outcomes. [4] (10.5397/cise.2023.00528)
- [L3] Low-profile double-plate osteosynthesis is a safe and effective alternative treatment of olecranon fractures with excellent subjective and objective clinical outcome measures. [5] (10.1016/j.otsr.2019.08.019)
- [L3] Plating of the olecranon leads to predictable union, though the most common complication was lack of full extension in 39% of patients. [6] (10.1016/j.injury.2016.04.015)
- [L4] Non-operative treatment of olecranon fracture in patients aged ≥75 years provided excellent functional results at 6 months, without associated complications. [7] (10.1016/j.otsr.2017.10.015)
- [L1] No differences were found in clinical or patient-rated outcome measures between the two most frequent fixation methods (tension band wiring and plate fixation) of displaced olecranon fractures. [8] (10.1177/1457496919893599)
- [L4] A majority of olecranon fractures heal uneventfully with good/excellent results with a small loss of motion to be expected. [9] (10.1016/j.hcl.2015.07.003)
- [Paper] No one technique is suitable for the management of all olecranon fractures. [11] (10.1016/j.injury.2008.12.013)
- [L1] Modern fixation techniques may offer superior functional outcomes, faster healing, and fewer complications than traditional tension band wiring for olecranon fractures. [12] (10.1186/s13018-025-06061-y)
- [L4] Close radiographic follow-up for nonsurgically treated olecranon fractures is recommended. [13] (10.5435/jaaos-d-25-00821)
- [L4] Aggregate data support the non-operative treatment of isolated undisplaced olecranon fractures with good results, and support the operative treatment of fractures displaced ≥4 mm. [14] (10.1302/2058-5241.5.190082)
- [L4] Surgical treatment of olecranon fractures is associated with a high rate of complications, and patients undergoing revisions beyond implant removal had poorer functional outcomes; however, no significant differences in functional outcomes or secondary operations were found with respect to fracture type, gender, or surgical method. [15] (10.1016/j.xrrt.2025.08.004)
- [L4] Suture anchor fixation of olecranon fractures in the elderly population provides excellent long-term radiographic and clinical outcomes without hardware complications associated with traditional fixation methods. [16] (10.1016/j.jse.2015.02.017)
- [L4] Locked plating of geriatric olecranon fractures with early mobilization leads to low fixation failure. [17] (10.1016/j.jse.2020.01.027)
- [L5] Fixation must be secure enough to permit early motion to avoid significant stiffness of the elbow joint. [19] (10.5435/00124635-200007000-00007)
- [L1] Current randomized evidence suggests that TBW and PF may yield similar functional outcomes for displaced olecranon fractures; however, these findings are based on a limited number of RCTs, with several secondary outcomes derived from only 2 studies. [20] (10.1016/j.xrrt.2026.100817)
- [L4] Single 2.7-mm mini-fragment plate fixation of olecranon osteotomies for distal humerus fractures is safe and effective with low rates of revision, hardware removal, and nonunion. [21] (10.1016/j.jse.2024.08.036)
- [L4] [22] (10.1007/s00068-021-01765-2)
- [L4] Fixation of simple olecranon fractures with an intramedullary screw is a safe and easy fixation method in young patients, leading to good functional and radiological results. [23] (10.1007/s00068-019-01114-4)
- [L4] The suture tension band technique is a viable option for managing simple olecranon fractures or fractures with minimal comminution, yielding excellent clinical and radiographic outcomes while avoiding hardware-related complications. [24] (10.1016/j.jseint.2025.04.032)
- [L4] Displaced olecranon fractures in patients older than 70 years may be effectively managed with nonoperative measures to produce high satisfaction and functional range of motion. [25] (10.1177/1558944720944261)
- [L1] Plate has better efficacy and safety for Mayo II olecranon fractures. [26] (10.1186/s13018-022-03262-7)
- [L4] Locking-plate osteosynthesis is an effective and safe treatment option for comminuted olecranon fractures, allowing early joint motion and yielding satisfactory radiologic and clinical results. [27] (10.1016/j.jse.2010.11.023)
- [L1] This supports nonoperative treatment as a reasonable option for displaced stable olecranon fractures in elderly patients. [28] (10.2106/jbjs.24.00655)
- [L4] [29] (10.1016/j.jse.2022.04.006)
- [L4] This study supports use of operative anatomic fixation with precontoured locked plates and early mobilization with an acceptable failure rate in geriatric olecranon fractures. [30] (10.1016/j.jseint.2021.02.013)
- [Letter] The authors of the original review acknowledge that nonsurgical management was limited to nondisplaced fractures due to editorial constraints but maintain that surgical management remains the standard of care for displaced olecranon fractures until more convincing evidence supports nonsurgical treatment. [31] (10.1016/j.jhsa.2013.04.013)
- [L4] All fractures in the 3 cases healed without any complications, with excellent elbow range of movements. [32] (10.1097/bth.0b013e31819225dc)
- [Case_report] Surgical treatment with plate fixation and bone grafting in a patient with a displaced olecranon fracture through a persistent physis resulted in bony union, full range of motion, and return to sports without complications at 2.5 years. [33] (10.1177/2325967119881647)
- [L3] Patients with olecranon fractures have essentially similar demographic characteristics compared to patients with distal radius fractures. [34] (10.1177/17585732221124301)
- [L4] This technique may be used for revision of failed olecranon fixation. [35] (10.5435/jaaosglobal-d-25-00049)
- [L3] [36] (10.1007/s00402-014-2021-9)
- [L3] The incidence of olecranon fractures increased by 29% over the 20-year study period. [38] (10.1186/s13018-025-05970-2)
- [Paper] DSTBW technology provides stable fixation for olecranon fractures, reducing the risk of internal fixation migration and failure. [39] (10.1186/s12891-023-06684-4)
- [L4] [41] (10.1016/j.jor.2019.09.017)
- [L4] The SEV shows a high correlation to the most commonly used scoring systems for outcome evaluation after elbow injury. [42] (10.1055/a-0946-2649)
- [L4] [43] (10.1016/j.injury.2024.111496)
- [L1] Internal fixation by CPS is an effective method for olecranon fracture and is associated with a shorter healing time, fewer complications and better function than TBW. [44] (10.1177/147323001204000324)
- [L1] When treating isolated, displaced 2-part and multifragmented olecranon fractures, tension band wiring was noninferior compared with plate fixation. [45] (10.2106/jbjs.24.01461)
- [L4] The authors describe a novel technique using suture tension band fixation with eyelet wires for simple olecranon fractures and hypothesize satisfactory outcomes regarding pain, functional scores, and radiographic union. [46] (10.1016/j.xrrt.2026.100707)
- [L4] While ROM is typically preserved after reoperation and improved when the indication for reoperation is elbow stiffness, a significant proportion of patients (35%) experience subsequent complications. [50] (10.1016/j.jseint.2024.12.017)
- [L5] Cyclic physiological loading of osteoporotic olecranon fracture fixation resulted in sudden, catastrophic failure of the bone-implant interface rather than in gradual implant loosening. [52] (10.1097/bot.0b013e3181f22465)
- [L5] Dual locking plates display biomechanical properties that suggest that they can be used in the fixation of comminuted olecranon fractures. [53] (10.1016/j.jhsa.2021.07.029)
- [L4] This proposed classification system is anatomically based and considers the deforming forces from ligaments and tendons. [54] (10.1016/j.jse.2023.12.021)
- [L5] [55] (10.1016/j.jhsa.2014.05.014)
- [L3] Olecranon fractures in the elderly have higher than expected 1 year mortality rates. [56] (10.1177/1758573221994860)
- [L4] [57] (10.1016/j.otsr.2021.103089)
- [L4] ORIF for olecranon fractures demonstrates low short-term complication rates; however, specific comorbidities such as smoking and ascites were associated with increased risk. [58] (10.1016/j.jseint.2025.06.017)
- [L4] Suture fixation is a reliable technique for simple olecranon fractures with low complication and reoperation rates compared to tension band wiring as reported in the literature. [60] (10.1177/17585732251400636)
- [L4] The technique remains the gold standard for the treatment of displaced and minimally comminuted olecranon fractures despite the introduction of new implants designed specifically to address the problems of wound irritation and metalwork removal. [62] (10.1016/j.jor.2014.04.018)
- [L4] Transosseous suture with high strength thread is a valid alternative for treating Mayo IIA olecranon fractures in adult patients, decreasing re-operation rates for implant removal. [63] (10.1016/j.injury.2020.02.011)
- [L4] This review identified a median OA incidence of 19% at a median follow-up of 41 months following isolated olecranon fractures. [64] (10.1016/j.jse.2026.02.024)
- [L3] Fractures of the ipsilateral olecranon associated with the radial neck are not so rare as previously reported. [65] (10.1186/s13018-021-02373-x)
- [L5] Our results suggest that there is a portion of the aLTR that, despite being covered with articular cartilage, is non-articulating throughout normal elbow range of motion. [93] (10.2106/jbjs.18.01270)
- [L5] The Mayo classification was designed to simplify categorization of olecranon fractures but does not achieve this goal due to poor reproducibility. [110] (10.1097/corr.0000000000000614)
- [L5] Lengthening of olecranon by increments of 2mm correlates positively with loss of elbow extension. [111] (10.1186/s12891-021-04936-9)
- [L4] The use of wide-awake local anesthesia no tourniquet for olecranon fracture fixation is a simple, safe, low-cost, and reproducible technique that obviates the need for general anesthesia or tourniquets. [115] (10.1016/j.jhsg.2022.12.006)
- [L4] [116] (10.1016/j.jhsa.2012.12.036)
- [L5] The dogma that the elbow should never be immobilised remains valid, and mobilisation should start as early as possible. [117] (10.1016/j.otsr.2018.05.016)
- [L4] [122] (10.1016/j.jhsa.2013.05.012)
- [L5] Yet, olecranon osteotomy is attractive in its simplicity and remains one of the most popular exposures to the elbow worldwide, particularly for the purpose of managing fractures. [128] (10.1097/00132589-200203000-00003)
- [L5] The methods described have been used with satisfactory results on fractures of the olecranon, malleoli and surgical neck of the humerus. [129] (10.1016/0020-1383(75)90062-5)
- [L3] [130] (10.1177/15589447221075667)
- [L4] Articular impaction is a common feature of geriatric olecranon fractures. [135] (10.5435/jaaos-d-20-01293)
- [L2] Current evidence suggests that SF/SAF of simple olecranon fractures is a safe and effective alternative to the current gold standard TBW fixation, with preliminary evidence suggestive of lower complication and reoperation rates. [137] (10.1177/17585732221094828)
- [L4] [138] (10.1302/2058-5241.5.190041)
- [L4] Displaced olecranon fractures in elderly and medically unwell patients treated nonoperatively can result in reasonable range of motion, minimal pain, and maintenance of extension against gravity. [139] (10.1016/j.jseint.2020.11.001)
- [Case_report] [141] (10.1016/j.jse.2009.06.007)
- [L2] [142] (10.1016/j.jse.2019.06.004)
- [L4] [143] (10.1016/j.injury.2009.01.129)
- [L3] More than 80% of patients with terrible triad and olecranon fracture dislocations were able to return to their pre-injury level of activity. [145] (10.1016/j.jseint.2025.01.019)
- [L4] [147] (10.1016/j.jseint.2021.11.015)
- [L3] Professional baseball players who undergo ORIF of an olecranon fracture have a return to sport rate of 67.5%, which is no different from natural attrition among matched controls. [149] (10.1177/0363546519844479)
- [L4] [150] (10.1097/bth.0b013e3182a9128c)
- [L5] [157] (10.1097/bth.0b013e3181f7ce5d)
- [L2] Proximal ulna fracture ORIF has a low rate of systemic complications, with the most common morbidities being return to the operating room, blood transfusion, and urinary tract infections. [158] (10.1016/j.jhsa.2016.08.020)
- [L3] TEA and ORIF lead to comparable functional results, but major complications are more common after ORIF. [159] (10.1007/s00264-014-2635-0)
- [L4] Patients treated with this trans-olecranon surgical approach demonstrate satisfactory clinical and radiographic outcomes with low rates of heterotopic ossification, nonunion, and infection. [161] (10.1016/j.jhsg.2022.07.009)
- [L2] A total of 447 complications were reported among 1,700 osteotomies, with wound infections occurring in 4.2% and union problems in 3.7%. [162] (10.5397/cise.2021.00591)
See Also
References
[1] Factors Associated With Reoperation After Fixation of Displaced Olecranon Fractures. Clinical Orthopaedics & Related Research. 2016. DOI: 10.1007/s11999-015-4488-2
[2] Efficacy evaluation of Kirschner wire tension band combined with anatomical locking plate in the treatment of Mayo type II olecranon fractures. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08843-1
[3] Timing of Olecranon Fracture Fixation Does Not Affect Early Complication or Reoperation Rates. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2023.09.002
[4] Midterm outcomes of suture anchor fixation for displaced olecranon fractures. Clinics in Shoulder and Elbow. 2024. DOI: 10.5397/cise.2023.00528
[5] Clinical evaluation of double-plate osteosynthesis for olecranon fractures: A retrospective case-control study. Orthopaedics & Traumatology: Surgery & Research. 2019. DOI: 10.1016/j.otsr.2019.08.019
[6] Outcomes after plating of olecranon fractures: A multicenter evaluation. Injury. 2016. DOI: 10.1016/j.injury.2016.04.015
[7] Results of non-operative treatment of olecranon fracture in over 75-year-olds. Orthopaedics & Traumatology: Surgery & Research. 2018. DOI: 10.1016/j.otsr.2017.10.015
[8] Treatment of Displaced Olecranon Fractures: A Systematic Review. Scandinavian Journal of Surgery. 2019. DOI: 10.1177/1457496919893599
[9] Olecranon Fractures. Hand Clinics. 2015. DOI: 10.1016/j.hcl.2015.07.003
[11] Olecranon fractures. Injury. 2009. DOI: 10.1016/j.injury.2008.12.013
[12] Modern fixation techniques versus traditional tension band wiring for olecranon fractures: a systematic review and meta-analysis of functional outcomes, healing time, and complications. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06061-y
[13] Further Displacement After Initial Nonsurgical Treatment of Minimally Displaced Olecranon Fractures in Children. Journal of the American Academy of Orthopaedic Surgeons. 2026. DOI: 10.5435/jaaos-d-25-00821
[14] Paediatric olecranon fractures: a systematic review. EFORT Open Reviews. 2020. DOI: 10.1302/2058-5241.5.190082
[15] Risk factors for complications and poor function after open reduction and fixation of olecranon fractures. JSES Reviews, Reports, and Techniques. 2025. DOI: 10.1016/j.xrrt.2025.08.004
[16] Suture anchor fixation of displaced olecranon fractures in the elderly: a case series and surgical technique. Journal of Shoulder and Elbow Surgery. 2015. DOI: 10.1016/j.jse.2015.02.017
[17] Locked Plating of Geriatric Olecranon Fractures and Early Mobilization Leads to Low Fixation Failure in Patients Over the Age of 75. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2020.01.027
[19] Olecranon Fractures: Treatment Options. Journal of the American Academy of Orthopaedic Surgeons. 2000. DOI: 10.5435/00124635-200007000-00007
[20] Comparative efficacy and safety of tension band wiring versus plate fixation for olecranon fractures: a meta-analysis and trial sequential analysis of randomized clinical trials. JSES Reviews, Reports, and Techniques. 2026. DOI: 10.1016/j.xrrt.2026.100817
[21] Mini-fragment plate fixation after olecranon osteotomy for distal humerus fractures. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2024.08.036
[22] Epidemiology, classification and treatment of olecranon fractures in adults: an observational study on 2462 fractures from the Swedish Fracture Register. European Journal of Trauma and Emergency Surgery. 2021. DOI: 10.1007/s00068-021-01765-2
[23] Intramedullary screw fixation for simple displaced olecranon fractures. European Journal of Trauma and Emergency Surgery. 2019. DOI: 10.1007/s00068-019-01114-4
[24] Outcomes of suture tension band technique for fixation of olecranon fractures: a retrospective case series. JSES International. 2025. DOI: 10.1016/j.jseint.2025.04.032
[25] Nonoperative Management of Olecranon Fractures in Elderly Patients: A Systematic Review. HAND. 2020. DOI: 10.1177/1558944720944261
[26] Efficacy and safety of tension band wire versus plate for Mayo II olecranon fractures: a systematic review and meta-analysis. Journal of Orthopaedic Surgery and Research. 2022. DOI: 10.1186/s13018-022-03262-7
[27] Results of open reduction and plate osteosynthesis in comminuted fracture of the olecranon. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2010.11.023
[28] Surgery for Olecranon Fractures in the Elderly (SOFIE). Journal of Bone and Joint Surgery. 2025. DOI: 10.2106/jbjs.24.00655
[29] Hardware complications and reoperations following precontoured plate fixation of the olecranon: a population-based study. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2022.04.006
[30] Locked plating of geriatric olecranon fractures leads to low fixation failure and acceptable complication rates. JSES International. 2021. DOI: 10.1016/j.jseint.2021.02.013
[31] Letter Regarding “Olecranon Fractures”. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2013.04.013
[32] Management of Comminuted Olecranon Fractures With Precut K-Wires and Tension Band Wiring. Techniques in Hand & Upper Extremity Surgery. 1922. DOI: 10.1097/bth.0b013e31819225dc
[33] Surgical Treatment of Displaced Olecranon Fracture Through a Persistent Physis: Case Report and Review of the Literature. Orthopaedic Journal of Sports Medicine. 2019. DOI: 10.1177/2325967119881647
[34] Mortality and subsequent fractures of patients with olecranon fractures compared to other upper extremity osteoporotic fractures. Shoulder & Elbow. 2022. DOI: 10.1177/17585732221124301
[35] Revision Olecranon Fixation: Is Tension Band Wiring the Solution? A Case Series and Review of the Literature. JAAOS: Global Research and Reviews. 2025. DOI: 10.5435/jaaosglobal-d-25-00049
[36] Simple and comminuted displaced olecranon fractures: a clinical comparison between tension band wiring and plate fixation techniques. Archives of Orthopaedic and Trauma Surgery. 2014. DOI: 10.1007/s00402-014-2021-9
[38] Epidemiology and Treatment of Olecranon Fractures: a nationwide register-based analysis of 27,880 cases in Denmark from 1999 to 2018. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05970-2
[39] The effect of ding’s screw and tension band wiring for treatment of olecranon fractures: a finite element study. BMC Musculoskeletal Disorders. 2023. DOI: 10.1186/s12891-023-06684-4
[41] Plate fixation and tension band wiring after isolated olecranon fracture comparison of outcome and complications. Journal of Orthopaedics. 2020. DOI: 10.1016/j.jor.2019.09.017
[42] Comparison of the Subjective Elbow Value with the DASH, MEPS und Morrey Score after Olecranon Fractures. Zeitschrift für Orthopädie und Unfallchirurgie. 2019. DOI: 10.1055/a-0946-2649
[43] Olecranon fractures: An old fixation device for a new surgical technique. Injury. 2024. DOI: 10.1016/j.injury.2024.111496
[44] Randomized Prospective Study of Olecranon Fracture Fixation: Cable Pin System versus Tension Band Wiring. Journal of International Medical Research. 2040. DOI: 10.1177/147323001204000324
[45] Tension Band Wiring Versus Precontoured Plate Fixation for 2-Part and Multifragmented Olecranon Fractures. Journal of Bone and Joint Surgery. 2025. DOI: 10.2106/jbjs.24.01461
[46] Suture tension band fixation of olecranon fractures: description and early outcomes of a novel technique. JSES Reviews, Reports, and Techniques. 2026. DOI: 10.1016/j.xrrt.2026.100707
[47] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Biomechanics, Physical Examination, and Imaging of the Elbow > Summary and Conclusions.
[50] Surgical outcomes after reoperation of intra-articular proximal ulna fractures. JSES International. 2025. DOI: 10.1016/j.jseint.2024.12.017
[52] Comparison of Olecranon Plate Fixation in Osteoporotic Bone: Do Current Technologies and Designs Make a Difference?. Journal of Orthopaedic Trauma. 2011. DOI: 10.1097/bot.0b013e3181f22465
[53] Biomechanical Comparison of Dual and Posterior Locking Plates in an Ex Vivo Comminuted Olecranon Fracture Model. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2021.07.029
[54] A novel fragment specific classification of complex olecranon fractures: 3-dimensional model design, radiological validation, and proposed surgical algorithm. Journal of Shoulder and Elbow Surgery. 2024. DOI: 10.1016/j.jse.2023.12.021
[55] Surgical Techniques of Olecranon Fractures. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.05.014
[56] Complications and mortality associated with olecranon fractures in the elderly: a retrospective cohort comparison from a large level one trauma centre. Shoulder & Elbow. 2021. DOI: 10.1177/1758573221994860
[57] Is surgery needed for displaced olecranon fractures in patients aged 75 years or over?. Orthopaedics & Traumatology: Surgery & Research. 2021. DOI: 10.1016/j.otsr.2021.103089
[58] Short-term complications of open reduction and internal fixation of olecranon fractures: a national database study. JSES International. 2025. DOI: 10.1016/j.jseint.2025.06.017
[60] Olecranon fractures treated with tension band suture fixation: Complication, reoperation rates and radiographic healing outcomes. Shoulder & Elbow. 2025. DOI: 10.1177/17585732251400636
[62] Does K-wire position in tension band wiring of olecranon fractures affect its complications and removal of metal rate?. Journal of Orthopaedics. 2015. DOI: 10.1016/j.jor.2014.04.018
[63] Olecranon mayo IIA fractures treated with transosseous high strength suture: A series of 29 cases. Injury. 2020. DOI: 10.1016/j.injury.2020.02.011
[64] Incidence of Post-traumatic Osteoarthritis in Olecranon Fractures and the Role of Instability and Comminution in its Development: A Systematic Review. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2026.02.024
[65] Management strategies of pediatric ipsilateral olecranon with associated radial neck fractures based on multicenter experience. Journal of Orthopaedic Surgery and Research. 2021. DOI: 10.1186/s13018-021-02373-x
[70] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Biomechanics, Physical Examination, and Imaging of the Elbow > Annotated References.
[71] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Biomechanics, Physical Examination, and Imaging of the Elbow > Anatomy > Bony Anatomy.
[72] Miller S Review Of Orthopaedics. SECTION 16 PATELLAR TRACKING IN TOTAL KNEE ARTHROPLASTY > TABLE 2.3 Shoulder Spaces.
[77] Miller S Review Of Orthopaedics. ELBOW.
[79] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > INJURIES AROUND THE ELBOW.
[80] Orthopaedic Knowledge Update Trauma. Distal Humerus Fracture > Anatomy.
[82] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Pathoanatomy and Applied Anatomy Related to Distal Humerus Fractures.
[85] Aaos Comprehensive Orthopaedic Review 3. Elbow Stiffness* > IV. Evaluation.
[93] Lateral Trochlear Ridge. Journal of Bone and Joint Surgery. 2019. DOI: 10.2106/jbjs.18.01270
[110] Classifications in Brief: Mayo Classification of Olecranon Fractures. Clinical Orthopaedics & Related Research. 2018. DOI: 10.1097/corr.0000000000000614
[111] The effect of post-fixation olecranon lengthening on range of motion of the elbow: a cadaveric study. BMC Musculoskeletal Disorders. 2021. DOI: 10.1186/s12891-021-04936-9
[115] Wide-Awake Olecranon Fracture Fixation: Is it Possible?. Journal of Hand Surgery Global Online. 2023. DOI: 10.1016/j.jhsg.2022.12.006
[116] Olecranon Fractures. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2012.12.036
[117] Prevention and management of early treatment failures in elbow injuries. Orthopaedics & Traumatology: Surgery & Research. 2019. DOI: 10.1016/j.otsr.2018.05.016
[122] Use of Kirschner Wires With Eyelets for Tension Band Wiring of Olecranon Fractures. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2013.05.012
[128] General Deep Approaches to the Elbow: Posterior Exposures. Techniques in Shoulder & Elbow Surgery. 2002. DOI: 10.1097/00132589-200203000-00003
[129] Tension band wiring: a method to prevent ‘backing out’ of the Kirschner wire. Injury. 1975. DOI: 10.1016/0020-1383(75)90062-5
[130] Risk Factors for Loss of Reduction After Open Reduction and Internal Fixation of Isolated Olecranon Fractures in Adults. HAND. 2022. DOI: 10.1177/15589447221075667
[135] Incidence and Management of Articular Impaction in Geriatric Olecranon Fractures. Journal of the American Academy of Orthopaedic Surgeons. 2021. DOI: 10.5435/jaaos-d-20-01293
[137] Novel suture/suture-anchor fixation versus tension band wiring for olecranon fractures: A systematic review. Shoulder & Elbow. 2022. DOI: 10.1177/17585732221094828
[138] Displaced olecranon fractures in the elderly: outcomes after non-operative treatment – a narrative review. EFORT Open Reviews. 2020. DOI: 10.1302/2058-5241.5.190041
[139] Outcomes of nonoperative management of displaced olecranon fractures in medically unwell patients. JSES International. 2021. DOI: 10.1016/j.jseint.2020.11.001
[141] Ulnar artery pseudoaneurysm after tension band wiring of an olecranon fracture resulting in Volkmann's ischemic contracture: A case report. Journal of Shoulder and Elbow Surgery. 2010. DOI: 10.1016/j.jse.2009.06.007
[142] Long-term outcomes of total elbow arthroplasty for distal humeral fracture: results from a prior randomized clinical trial. Journal of Shoulder and Elbow Surgery. 2019. DOI: 10.1016/j.jse.2019.06.004
[143] Olecranon fracture fixation with a new implant: Biomechanical and clinical considerations. Injury. 2009. DOI: 10.1016/j.injury.2009.01.129
[145] Differences in outcome and complications between 2 distinct complex traumatic elbow instability patterns. A retrospective comparison of terrible triad and olecranon fracture dislocations. JSES International. 2025. DOI: 10.1016/j.jseint.2025.01.019
[147] Epidemiology of isolated olecranon fractures: a detailed survey on a large sample of patients in a suburban area. JSES International. 2022. DOI: 10.1016/j.jseint.2021.11.015
[149] Performance and Return to Sport After Open Reduction and Internal Fixation of the Olecranon in Professional Baseball Players. The American Journal of Sports Medicine. 2019. DOI: 10.1177/0363546519844479
[150] Minimally Invasive Tension Band Wiring Technique for Olecranon Fractures. Techniques in Hand & Upper Extremity Surgery. 2013. DOI: 10.1097/bth.0b013e3182a9128c
[157] Management of Comminuted Proximal Ulna Fracture-dislocations Using a Multiplanar Locking Intramedullary Nail. Techniques in Hand & Upper Extremity Surgery. 2011. DOI: 10.1097/bth.0b013e3181f7ce5d
[158] Risk Factors for 30-Day Postoperative Complications Following Open Reduction Internal Fixation of Proximal Ulna Fractures. The Journal of Hand Surgery. 2016. DOI: 10.1016/j.jhsa.2016.08.020
[159] Arthroplasty compared to internal fixation by locking plate osteosynthesis in comminuted fractures of the distal humerus. International Orthopaedics. 2014. DOI: 10.1007/s00264-014-2635-0
[161] Outcomes of Posterior Monteggia Variant Fractures Repaired Through a Trans-Olecranon Approach. Journal of Hand Surgery Global Online. 2022. DOI: 10.1016/j.jhsg.2022.07.009
[162] Complications of olecranon osteotomy in the treatment of distal humerus fracture. Clinics in Shoulder and Elbow. 2022. DOI: 10.5397/cise.2021.00591